

What Does Gradual Weight Reduction With a Gastric Band Realistically Look Like Over Time?

Key Takeaways
- In the longest published follow-up, people who kept an adjustable gastric band for 15 years had lost about 47 percent of their excess weight, with pooled 10-year studies at about 54 percent.
- Roughly half of band patients in that 15-year series needed at least one further procedure, most for slippage or pouch problems and many as repairs rather than removals.
- Band erosion was reported in 28 percent of patients in one 12-year single-center series, a figure that helped drive the shift away from banding.
- A band does almost nothing until it is adjusted, so results depend heavily on access to regular clinic follow-up over years, not on the operation alone.
- Over-tightening causes reflux, regurgitation and a drift toward soft high-calorie foods, so loosening a band can paradoxically restart weight loss.
- Bands carry a far lower risk of vitamin and mineral deficiency than gastric bypass, but produce less weight loss and smaller metabolic improvements on average.
With an adjustable gastric band, weight comes off slowly over about two years rather than in months, and long-term studies with 10 to 15 years of follow-up report roughly half of excess weight lost among people who keep the band and attend regular adjustments. Many patients need a further operation over time for slippage, erosion, port problems or removal, which is why bands are now used far less often.
A woman in her late fifties sits in a follow-up clinic holding a folder of appointment letters that goes back twelve years. Her band was placed when it was the most common weight-loss operation in many countries. She has lost weight, regained some, had two adjustments loosened, and now wants to know one thing: is this still working, and for how long?
Her question is the one almost everyone with a band eventually asks, and the honest answer is more textured than either the early marketing or the later backlash suggested. Lap band results long term are neither a steady downward line nor a guaranteed failure. They are a slow curve, shaped by adjustments, eating patterns and the mechanical behavior of a silicone ring sitting on a moving stomach.
This article lays out what the follow-up studies actually show year by year, what tends to go wrong and when, how long a band can realistically stay in place, and the signs that should send you back to your surgical team without delay.
How a gastric band actually works
A laparoscopic adjustable gastric band is a soft silicone ring placed around the upper part of the stomach through keyhole incisions. It creates a small pouch above the ring, roughly the size of a golf ball, with a narrow opening into the rest of the stomach below. Nothing is cut, stapled or rerouted, which is why the band is described as a purely restrictive procedure: it limits how much you can eat comfortably rather than changing how food is absorbed.
The ring is connected by thin tubing to a small access port stitched under the skin of the abdomen. Saline injected into or withdrawn from that port tightens or loosens the band. The MedlinePlus overview of laparoscopic gastric banding explains that this adjustability is the defining feature: the band is tuned over months rather than set once on the operating table.
What the band does physiologically is more subtle than squeezing the stomach shut. A correctly adjusted band slows the passage of food into the lower stomach and stimulates stretch receptors in the upper pouch, sending early fullness signals to the brain. Patients often describe eating a few small bites and feeling satisfied for hours. When the band is too tight, that signal is replaced by pressure, regurgitation and a drift toward soft, calorie-dense foods that slide through easily.
Because the digestive tract is otherwise untouched, nutrient absorption stays close to normal. The National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) notes that the band carries a lower risk of vitamin and mineral deficiency than bypass procedures, though weight loss is also typically smaller and slower. That trade-off sits at the heart of every long-term result.
What do lap band results long term actually look like year by year?
Researchers measure bariatric outcomes in percentage excess weight loss, meaning the share of weight above a healthy-range reference that has been lost. A person carrying 100 pounds above that reference who loses 50 pounds has 50 percent excess weight loss. Keep that unit in mind, because it is the number most studies report.

The best long-term dataset comes from a 15-year follow-up of adjustable gastric banding published in Annals of Surgery, which also pooled other studies with at least 10 years of follow-up. Among patients who still had a band at 15 years, mean excess weight loss was about 47 percent; across the pooled long-term studies the figure was about 54 percent. Roughly half of patients had needed at least one further procedure over that period, most often in the earlier years for slippage or pouch problems.
| Time point | What published follow-up tends to show | What it usually feels like |
|---|---|---|
| 0–6 months | Weight loss begins slowly while the band is being adjusted | Frequent clinic visits, learning new eating rhythm |
| 1–2 years | Most of the total loss is reached; the curve flattens | Clothes change size, adjustments become less frequent |
| 3–5 years | Partial regain is common; revision operations cluster here | Hunger returns for some, band may need loosening or repair |
| 10–15 years | About half of excess weight lost among those still banded; roughly half have had a reoperation | Stable for some, band removed or converted for others |
Those averages hide wide variation. Some people lose a great deal and keep it off; others lose little from the start. The NHS and NIDDK both describe the band as producing less weight loss than sleeve gastrectomy or gastric bypass, and the long-term data support that description.
The first days and weeks after band placement
Compared with other weight-loss operations, the early recovery is short. MedlinePlus notes that most people go home the same day or the day after surgery, because nothing has been divided or stapled inside the abdomen. Shoulder-tip pain from the gas used to inflate the abdomen during keyhole surgery is common for a day or two and usually settles with walking.
Eating is relearned in stages. A liquid-only phase typically lasts around two to three weeks, followed by pureed and then soft foods, with a gradual return to solid textures over roughly six weeks, according to the MedlinePlus patient guidance. The point of this slow progression is not weight loss; it is to let the stomach tissue around the band heal without being stretched by solid food too early.
Many people are surprised that the band is placed empty, or nearly so, at surgery. Hunger often returns within the first few weeks, which can feel like failure. It is not. Swelling needs to subside before the first adjustment, and the NHS recovery guidance for weight-loss surgery describes a return to normal activities within a few weeks for keyhole procedures, with heavier lifting delayed longer on surgical advice.
Walking from the first day matters for two reasons. It eases trapped gas, and it reduces the risk of blood clots in the legs, a known hazard after any abdominal surgery, particularly in people with higher body weight. Your team will give specific instructions on activity, wound care and when to drive; those instructions, not general ranges, are the ones to follow.
Band adjustments: why fills shape the whole curve
An adjustment, often called a fill, is a short clinic procedure in which a clinician uses a fine needle to add or remove saline through the port under the skin. Sometimes X-ray guidance is used to watch how a swallowed contrast liquid passes through the band. The first adjustment usually happens several weeks after surgery, once healing is complete, and the process continues over the following months until the band reaches what surgeons call the green zone: full after small meals, no regurgitation, steady weight loss.
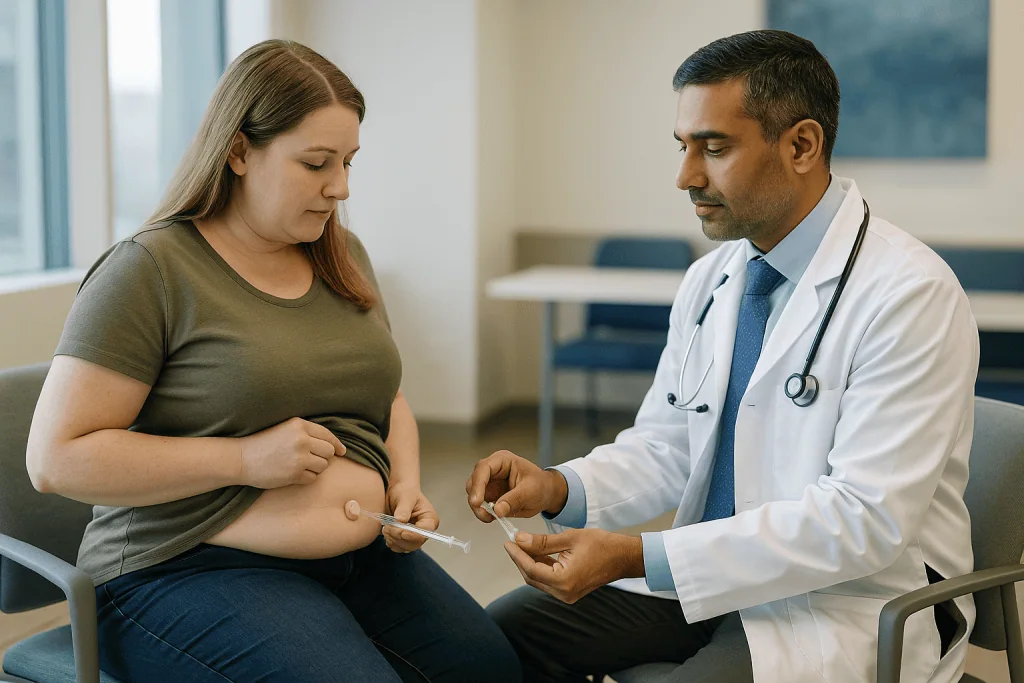
This is where gradual weight reduction with a gastric band diverges most sharply from stapled procedures. A sleeve or bypass does most of its work in the first year without any tuning. A band does almost nothing until it is adjusted, and the results depend heavily on how often the patient can attend follow-up. The Annals of Surgery 15-year series was run by a program with intensive follow-up, and its authors were explicit that results elsewhere, with less frequent review, were often weaker.
Adjustments also run in both directions. Pregnancy, intercurrent illness, planned surgery, or symptoms of a tight band are all reasons to withdraw fluid. People sometimes resist loosening because they fear regaining weight, but a band that is too tight pushes eating toward ice cream, chocolate and other soft, high-calorie foods that pass easily. Paradoxically, loosening can restart weight loss.
A practical consequence for anyone considering or living with a band: the operation is the beginning of a relationship with a clinic, not a one-off event. Programs that cannot offer years of accessible follow-up struggle to reproduce the published results.
Who a gastric band is usually for, and who is usually asked to wait
Eligibility for any weight-loss operation in the UK follows the National Institute for Health and Care Excellence (NICE) criteria, summarised on the NHS website: a body mass index (BMI) of 40 or more, or 35 to 40 with a serious weight-related condition such as type 2 diabetes or high blood pressure, together with a genuine attempt at other weight-management approaches. BMI is weight in kilograms divided by height in meters squared, a crude but widely used screening measure. Thresholds are adjusted downward for people of South Asian and some other backgrounds, who develop metabolic complications at lower BMI.
Within that group, the band has historically appealed to people who wanted the least invasive, fully reversible option, who were uneasy about stapling or rerouting the intestine, or who had medical reasons to avoid malabsorption. Mayo Clinic’s bariatric surgery overview describes it as the option with the lowest early surgical risk and the smallest average weight loss.
Teams are usually more cautious, or suggest a different procedure, in several situations:
- Significant gastroesophageal reflux disease or a large hiatal hernia, because the band can worsen reflux.
- Difficulty attending frequent follow-up for adjustments, for geographic, work or financial reasons.
- A pattern of grazing or high-calorie liquid intake, which a purely restrictive device does little to change.
- Very high BMI where the expected loss from a band is unlikely to be enough.
- Untreated mental health conditions or active substance use disorders, which bariatric programs assess before any operation.
None of these is an absolute exclusion. They are reasons for a longer conversation, and the decision rests with the multidisciplinary team, including a dietitian and often a psychologist, who will weigh the whole picture rather than a single number.
Gastric band long term side effects: slippage, erosion and pouch dilation
The problems that define lap band results long term are mechanical, and they tend to arrive years rather than days after surgery. Understanding each one helps make sense of the reoperation figures.
Band slippage means part of the lower stomach has worked its way up through the ring, enlarging the pouch above and often kinking the outlet. It presents as sudden intolerance of food, regurgitation, reflux and sometimes pain. Pouch dilation is a slower version of the same process: the small upper stomach stretches over time, often because of persistent overeating against a tight band, so fullness signals weaken and hunger returns. Both are among the leading reasons for revision in long-term series.
Band erosion is rarer but more serious: the silicone gradually wears through the stomach wall and ends up partly inside the stomach. It can be surprisingly quiet, showing up as loss of restriction, a port-site infection or vague upper abdominal pain. In a Belgian single-center series followed for about 12 years, published in Archives of Surgery, erosion was found in 28 percent of patients, a strikingly high figure that helped shift surgical opinion. Erosion requires band removal.
Port and tubing problems, including a flipped port that cannot be accessed, tubing disconnection and leaks, account for a steady trickle of smaller procedures. Esophageal dilation, where the swallowing tube above the band stretches and loses its squeeze, can develop when a band stays too tight for years, and it may not fully recover even after the band is loosened or removed.
NIDDK’s summary is blunt: the band carries a higher chance of needing additional operations to adjust, repair or remove the device than other bariatric procedures. That is the central long-term side effect, and it is one of planning rather than panic.
Reflux, swallowing changes and the soft-food trap
Ask people who have lived with a band for a decade what bothers them most and heartburn often comes up before weight. A band changes the pressure dynamics at the top of the stomach. When it is well adjusted, many people with mild reflux actually improve. When it is tight, or when the pouch has enlarged or slipped, acid and food sit above the ring and travel back up the esophagus, especially at night.
Night-time regurgitation deserves particular respect. Waking coughing, with a sour taste, or finding a damp pillow in the morning can mean food and acid are reaching the airway. Repeated episodes raise the risk of aspiration into the lungs. Long-term banding studies repeatedly cite reflux and esophageal symptoms as a leading reason for loosening or removing the band, and NHS guidance lists acid reflux among recognised complications of weight-loss surgery.
Swallowing itself can change. Dense proteins such as steak or dry chicken, fibrous vegetables and bread are the classic offenders, lodging briefly above the band. Chewing thoroughly and eating slowly becomes a lifelong habit. The unhelpful adaptation is the opposite one: abandoning solid food in favor of soups, milky drinks, soft desserts and snacks that slide through. Surgeons call this maladaptive eating. It relieves discomfort, but calories climb while the band appears to be working perfectly on examination.
If solid food has become hard to manage, the answer is almost never to live on soft food. It is to have the band checked and, if needed, loosened. A band that only tolerates liquids is not tight enough; it is too tight, and the long-term results of leaving it that way are poor for both weight and the esophagus.
How long can you have a lap band? Longevity, removal and conversion
There is no fixed expiry date on a gastric band. The silicone is designed to remain in place indefinitely, and some people from the earliest series still have a functioning band after 15 years or more. The honest question is not how long the device lasts but how long it continues to help without causing problems, and the long-term studies answer that in probabilities rather than certainties.
In the Annals of Surgery 15-year follow-up, about 5 to 6 percent of patients had the band permanently removed, while close to half had some form of revision procedure, many of which repaired or repositioned the band so it could keep working. In the Belgian Archives of Surgery series, nearly one in five patients had been converted to a gastric bypass by the 12-year mark, and a substantial proportion no longer had a band at all. Two centers, two very different removal rates, and that spread itself is the lesson: outcomes depend on surgical technique, band design, follow-up intensity and patient factors.
Removal is usually a keyhole operation and is technically straightforward when the band has not eroded. What happens to weight afterward is predictable. Without restriction, most people regain, which is why removal is often combined with, or followed by, conversion to a sleeve gastrectomy or gastric bypass. Conversion operations carry higher complication rates than first-time surgery because of scar tissue around the stomach, and surgical teams weigh this carefully.
For someone with a well-functioning band, there is no evidence that it should be removed simply because of its age. For someone with recurrent slippage, erosion, progressive reflux or esophageal dilation, the question shifts from whether to how and when. Either way, that judgment belongs to the surgical team, informed by imaging and endoscopy.
Why are lap bands no longer used as often?
Fifteen years ago the band was, in many countries, the single most common bariatric operation. It has since fallen to a small fraction of procedures in most registries, and NIDDK’s current patient information states plainly that gastric band surgery is less common today because it is associated with more complications, particularly the need for additional operations to remove or replace the band.
Three threads explain the decline. The first is the long-term data described above: durable but modest weight loss combined with a high and ongoing reoperation rate. The second is the arrival of the sleeve gastrectomy, an operation that removes about three-quarters of the stomach, produces more weight loss than a band with a single procedure and needs no adjustments. The third is a change in how we understand obesity itself. Pure restriction turned out to be a weaker lever than the hormonal changes triggered when stomach tissue is removed or the intestine is rerouted, changes that reduce hunger signals rather than just making overeating uncomfortable.
Does the decline mean the band was a mistake? Not quite. For patients who wanted a reversible, low-risk operation and who had access to committed follow-up, it delivered meaningful, lasting weight loss for many, and the long-term authors argue exactly that. It also carried the lowest short-term mortality and almost no risk of the nutritional deficiencies that follow bypass.
What the field learned is that a device needing years of fine-tuning performs poorly when health systems cannot provide that tuning, and that mechanical devices sitting on a moving organ accumulate mechanical problems. Newer approaches, including sleeve, bypass and the newer injectable medicines that mimic gut hormones, have shifted the balance of risk and benefit for most new patients. People who already have a band working well are a different group, and declining popularity is not by itself a reason to act.
Lap band 10 years later: regain, health and what the studies show
Weight regain after bariatric surgery is normal physiology, not a character flaw. Every procedure shows some rebound after the two-year low point, as the body defends its weight through appetite hormones and lower energy expenditure. The question for the band is how much, and for whom.
In the pooled analysis of studies with at least 10 years of follow-up, mean excess weight loss settled around 54 percent, with the 15-year single-center cohort at about 47 percent. Put differently, a person who had lost 60 percent of excess weight at year two might sit closer to half by year ten. Some regain nearly everything, often after a band is loosened for reflux or removed. Others hold steady for decades, usually those who kept attending and kept eating solid food in small portions.
Health effects beyond the scale are harder to pin down for the band specifically, because much of the strongest outcome research involves bypass. What NIDDK and Mayo Clinic summarize across bariatric procedures is that sustained weight loss improves type 2 diabetes control, blood pressure, sleep apnea and joint pain in many people, with larger improvements generally following larger and more durable weight loss. The band’s smaller average loss translates, on average, into smaller metabolic gains, and remission of diabetes is less frequent than after bypass in comparative studies.
The flip side is reassuring. Band patients rarely develop the iron, vitamin B12, calcium and vitamin D deficiencies that require lifelong monitoring after bypass, and dumping syndrome, the rapid emptying of sugary food into the intestine that causes sweating and faintness, does not occur. Bone density is less affected. Twenty years after a band, the typical story is not malnutrition but a device that either still helps modestly or has already been dealt with surgically.
Living with a band: nutrition and daily life over the years
The daily discipline of a band is textural rather than mathematical. Three small meals of solid food, eaten slowly with thorough chewing, and liquids kept separate from meals so they do not wash food through the pouch. Protein first on the plate, because small volumes make it easy to fall short, and because protein sustains fullness longest. Those habits, more than any particular fill level, distinguish people who keep weight off.
Fluids need attention from the other direction. Because meals are tiny and drinking with food is discouraged, dehydration is a quiet risk, especially in hot weather or during illness. Carbonated drinks are usually discouraged because gas stretches the pouch, and alcohol is absorbed quickly and delivers calories without fullness.
Supplements are less demanding than after bypass, but NHS guidance recommends a daily multivitamin and mineral supplement and periodic blood tests after any weight-loss surgery, since small portions over years can leave gaps, particularly in iron for people who menstruate and in vitamin D more generally. Your team sets the specific plan.
A few practical situations recur over a lifetime with a band:
- Pregnancy: bands are usually loosened to allow adequate nutrition, then readjusted afterward.
- Illness with vomiting: repeated vomiting can trigger slippage; a temporary loosening is often advised.
- Other surgery or imaging: the port and tubing are visible on X-ray and MRI-compatible for most designs, but tell every clinician you have a band.
- Air travel and altitude: pressure changes do not meaningfully affect a fluid-filled band, though some people notice tighter restriction when flying.
Periodic review matters even when nothing feels wrong. An enlarged pouch or early slippage can be silent, and a routine contrast swallow or endoscopy picks up problems before they become emergencies.
What people often get wrong about lap band results long term
Myths cluster around the band more than any other weight-loss operation, partly because it was heavily promoted and then heavily criticized. A few deserve a direct correction.
“The band does the work; you just eat less automatically.” A band only limits comfortable volume. It does nothing to soft, calorie-dense food or liquids, and it does not change the hormones that drive hunger the way stapled procedures do. The long-term results above come from programs with years of dietitian support.
“Tighter is always better.” Over-tightening is the most common path to regurgitation, reflux, esophageal dilation and the soft-food trap. The published goal is comfortable restriction with solid food, not maximum tightness.
“Bands were banned because they are dangerous.” They were not banned. They fell out of favor because long-term data showed modest weight loss and frequent reoperations compared with alternatives, as NIDDK explains. Short-term mortality remained the lowest of all bariatric operations.
“If weight comes back, the band has failed.” Partial regain after year two is expected with every procedure. What matters is whether the band still provides useful restriction and whether a mechanical problem is driving the change.
“Once it’s in, it never needs attention.” Roughly half of patients in the longest follow-up series needed a further procedure, most of them repairs that allowed the band to keep working. A band is maintained, like a joint replacement or a pacemaker.
“Removal brings you back to square one.” Removal usually brings weight regain, which is why surgeons often discuss conversion to another procedure at the same time rather than removal alone.
The thread running through all of these is the same: a band is a tool whose results depend on how it is tuned, monitored and lived with, not a fixed outcome delivered on the day of surgery.
Questions to ask your care team
Whether you are considering a band, living with one, or wondering whether to have it removed, the most useful conversations are specific. These questions tend to surface the information that matters.
If you are considering a band or any weight-loss operation:
- What weight loss would you expect for someone with my BMI and health conditions with a band compared with a sleeve or bypass, based on your own program’s data?
- How often will I need adjustments in the first two years, and how are they arranged if I live far away or cannot easily take time off?
- What is your program’s reoperation and removal rate over five and ten years?
- Do I have reflux or a hiatal hernia that would make a band a poor choice?
- What dietitian and psychological support continues after the first year?
If you already have a band:
- When was my pouch and band position last checked by imaging, and should it be checked now?
- Are my current symptoms, such as heartburn, regurgitation or returning hunger, signs that the band is too tight, too loose, or has moved?
- Which blood tests do I need each year, and what were my latest results?
- If this band stops working or causes problems, what are my options, and what does conversion involve for someone with my history?
- Who do I contact out of hours if I suddenly cannot keep fluids down?
Write the answers down. Long-term band care spans many years and often several clinicians, and your own record of fill volumes, imaging dates and symptoms is frequently the most complete history available. Every decision about adjusting, repairing, removing or converting the band rests with your treating team, who can see the pictures and the whole picture.
When to call your doctor
Most of the time, living with a gastric band is uneventful. The complications that matter, slippage, erosion and obstruction, usually announce themselves, and acting quickly on those signals is what keeps a fixable problem from becoming an emergency. Both MedlinePlus and NHS guidance on weight-loss surgery advise contacting your surgical team or seeking urgent care rather than waiting for symptoms to pass.
Seek care the same day, or go to an emergency department, if you have:
- Inability to swallow your own saliva, or vomiting that prevents you from keeping any fluids down for more than a few hours.
- Sudden, severe or worsening upper abdominal or chest pain, especially after eating.
- Vomiting blood or passing black, tarry stools.
- A fever with abdominal pain, or redness, swelling, warmth or discharge at the port site.
- Night-time regurgitation with coughing, choking or breathlessness, which can signal food reaching the airway.
- Pain, swelling or warmth in one calf, or sudden breathlessness, which can indicate a blood clot, particularly in the weeks after any operation.
Arrange a routine but prompt appointment if you notice:
- New or worsening heartburn or regurgitation over several weeks.
- Loss of the fullness you used to feel after small meals, or a steady drift toward only tolerating soft foods and liquids.
- Difficulty accessing the port at adjustment, or a port that feels as though it has moved.
- Unexplained weight gain or loss, persistent tiredness, hair thinning or mouth soreness, which can point to nutritional gaps.
You know your band’s normal better than anyone. A change from that normal, even without pain, is reason enough to be seen. Your team can order a contrast swallow or endoscopy, adjust the band, and decide with you on next steps.
Frequently asked questions
What are the long-term side effects of lap band surgery?
The main long-term problems are mechanical: band slippage, enlargement of the stomach pouch, erosion of the band into the stomach wall, port or tubing faults, and reflux with regurgitation. Esophageal dilation can develop if a band stays too tight for years. NIDDK notes the band carries a higher chance of additional operations than other bariatric procedures, while nutritional deficiencies are less common than after bypass.
What happens 20 years after bariatric surgery with a gastric band?
Published data extend to about 15 years, and the picture at that point is a device that either still provides modest restriction, with roughly half of excess weight lost among those still banded, or has already been repaired, removed or converted. By two decades most people fall into one of those groups. Routine imaging and annual blood tests remain sensible for anyone whose band is still in place.
How long can you have a lap band?
There is no set expiry. Some people retain a functioning band for 15 years or longer, and the silicone itself is designed to stay indefinitely. The practical limit is whether the band keeps helping without causing slippage, erosion, reflux or esophageal problems. In long-term series, about 5 to 6 percent had permanent removal in one program and far more in another, so the answer varies widely between individuals and centers.
Why are lap bands no longer used as often?
Bands declined because long-term studies showed smaller average weight loss than sleeve gastrectomy or bypass combined with frequent reoperations for slippage, erosion and port problems, as NIDDK summarizes. The sleeve offered more weight loss in a single procedure without adjustments, and understanding of obesity shifted toward hormonal mechanisms that restriction alone does not address. Bands were never banned, and a well-functioning band is not removed simply because of this trend.
How much weight do people lose with a gastric band in the first year?
Weight loss with a band is slower than with stapled procedures and depends on adjustments, so the first few months may show little change. Most of the total loss is typically reached by around two years rather than one. MedlinePlus and NIDDK both describe the band as producing less weight loss than sleeve or bypass, with long-term averages near half of excess weight among people who keep the band.
Does weight come back after lap band surgery?
Some regain after the two-year low point is normal with every bariatric operation, and the band is no exception. Long-term series show average excess weight loss drifting from its peak toward roughly half by 10 to 15 years. Larger regain often follows loosening for reflux, removal, or a shift toward soft high-calorie foods. A sudden loss of restriction should prompt a check for slippage or pouch enlargement.
Can a lap band be removed, and what happens to your weight?
Yes, removal is usually a keyhole operation and is straightforward when the band has not eroded. Without restriction, most people regain weight over the following months and years, which is why surgeons frequently discuss conversion to a sleeve gastrectomy or gastric bypass at the same time. Conversion carries higher risks than first-time surgery because of scar tissue, so the decision is made with the full surgical team.
Is heartburn normal years after a gastric band?
Mild reflux can improve with a well-adjusted band, but new or worsening heartburn, especially with night-time regurgitation, usually means the band is too tight, the pouch has enlarged or the band has slipped. It is one of the most common reasons for loosening or removal in long-term studies. Persistent symptoms warrant imaging or endoscopy rather than long-term reliance on acid-suppressing medicine alone.
Do you need vitamins for life after a gastric band?
The band does not cause malabsorption, so deficiencies are far less common than after bypass. NHS guidance still recommends a daily multivitamin and mineral supplement and periodic blood tests after any weight-loss surgery, because very small portions over many years can leave gaps, particularly in iron and vitamin D. Your dietitian and surgical team set the specific plan based on your results.
How often does a gastric band need adjusting in the long term?
Adjustments are most frequent in the first one to two years while the band is being tuned, then taper to occasional visits. Later adjustments are often loosening rather than tightening: for pregnancy, illness with vomiting, reflux or planned surgery. Even when no adjustment is needed, periodic review with imaging is advised because slippage and pouch enlargement can develop quietly.
References
- MedlinePlus: Laparoscopic gastric banding
- NHS: Weight loss surgery
- NIDDK (NIH): Types of weight-loss surgery
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Is a Mini Gastric Bypass Performed? The Pouch, the Loop and the Laparoscopic Steps
A mini gastric bypass, also called a one-anastomosis gastric bypass, is performed laparoscopically through a few small abdominal incisions. The surgeon staples the stomach…

When Lifestyle Measures Are Not Enough: How Doctors Decide a Gastric Sleeve Is the Next Step
A gastric sleeve is usually recommended when someone has a body mass index of 40 or more, or 35 or more with a weight-related…

Preparing for Robotic Bariatric Surgery: Sleep Study, Endoscopy and the Dietitian Visit
Preparing for robotic bariatric surgery usually involves three core steps: a sleep study to check for obstructive sleep apnea so anesthesia can be planned…

Long-Term Obesity Management: How Follow-Up Visits Keep Lifestyle Changes on Track
Long term obesity management works best as ongoing care rather than a single push. Regular follow-up visits let a care team track weight, waist…

Gastric Bypass vs Gastric Sleeve: Why Reflux, Diabetes and Eating Habits Shape the Choice
For people with established acid reflux, gastric bypass is usually favored over a gastric sleeve, because the small pouch produces little acid and the…
Mini Gastric Bypass vs Standard Gastric Bypass: One Connection or Two, and Why It Matters
A mini gastric bypass (one anastomosis gastric bypass) joins a long, narrow stomach pouch to the small intestine with a single connection, while a…