

What Happens During an Echocardiogram, and How Long Does the Scan Usually Take?
Key Takeaways
- A standard transthoracic echocardiogram takes 15 to 60 minutes according to the NHS, with most appointments running about 40 to 60 minutes including check-in.
- Echocardiography uses sound waves and no ionizing radiation, so it can be repeated over many years without cumulative exposure.
- A stress echo takes about an hour and images the heart before and immediately after exercise or a heart-stimulating medicine, per Mayo Clinic.
- A transesophageal echo scan lasts around 20 minutes but requires fasting, sedation, and someone to drive you home, per the NHS.
- An echo measures chamber size, valve function, and ejection fraction, which the American Heart Association describes as normally 55 to 70 percent, but it cannot image the coronary arteries.
- Results are usually reported by a cardiologist and sent to the referring doctor rather than given at the scanner, so a silent sonographer is protocol, not a warning.
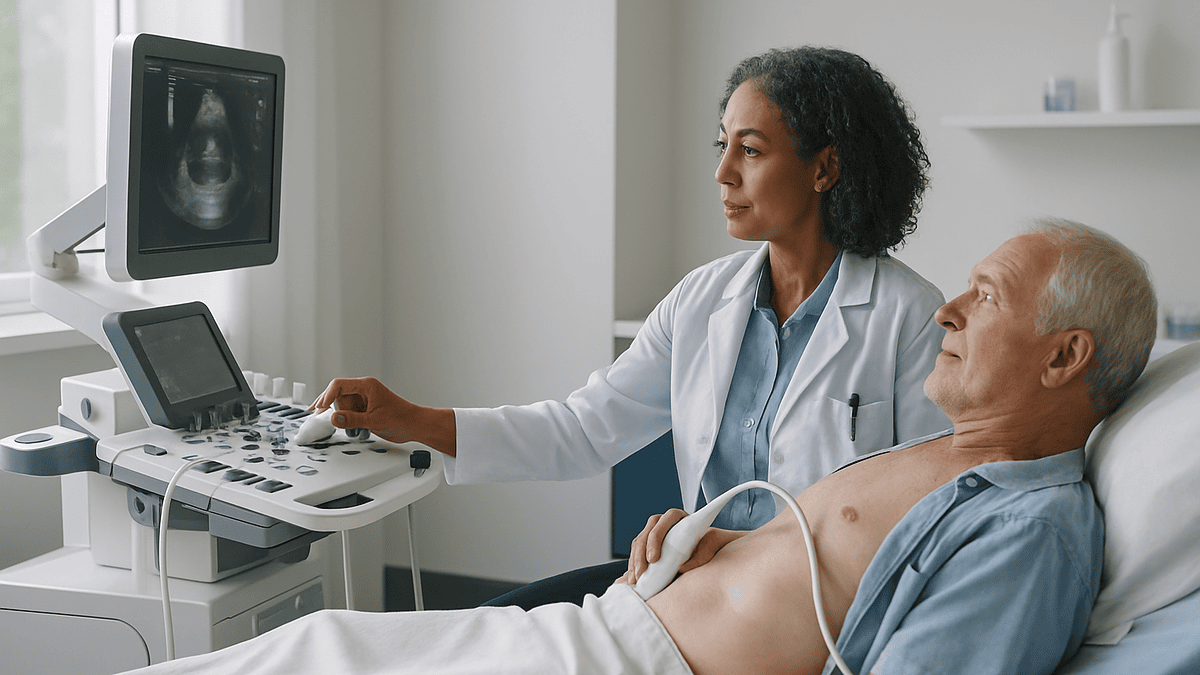
A standard echocardiogram, the ultrasound scan of the heart done through the chest wall, usually takes 15 to 60 minutes according to the NHS, with most appointments landing around 40 to 60 minutes once check-in and undressing are included. Stress echocardiograms and transesophageal scans take longer because of exercise or sedation. The scan itself is painless and uses no radiation.
The referral letter arrives on a Tuesday, tucked between a utility bill and a supermarket flyer. One line stands out: “Echocardiogram, cardiology department.” You read it twice. Nobody said the word “scan” in the consultation, or if they did, it got lost behind the phrase “just to be thorough.” Now the practical questions crowd in. Can this fit into a lunch break? Will there be needles? Is it safe to drive home afterward?
Most people searching how long does an echocardiogram take are not really asking about minutes. They are asking whether the day will be ordinary or frightening, whether they can plan childcare, whether the word “echo” hides something worse. It helps to know that this is one of the gentlest tests in cardiology: sound waves, gel, a dim room, a technician who has done it thousands of times.
What follows walks through the appointment as it actually unfolds, from the waiting-room chair to the moment results reach your doctor, with the timings tied to what mainstream sources report rather than to reassurance for its own sake.
How long does an echocardiogram take, from check-in to walking out?
The short version: budget about an hour for a standard scan, and you will rarely be caught out. The NHS puts the transthoracic echocardiogram, the version done with a probe on the chest, at 15 to 60 minutes, while Cleveland Clinic describes a typical appointment of roughly 40 to 60 minutes. The spread is wide for honest reasons. A routine follow-up in a slim person with easy-to-image heart walls can be finished quickly. A first-ever scan in someone with lung disease, a larger chest, or a valve that needs measurement from several angles takes longer, because the sonographer keeps hunting for clearer views.
Where do those minutes actually go? Very little of the time is waiting in the traditional sense. You check in, change into a gown from the waist up, and lie on a narrow couch. Three sticky electrodes go on to track your heart rhythm alongside the pictures. Then the scanning begins, and it is continuous: probe, gel, small adjustments, a pause while measurements are typed in, then the next window on the heart.
Two things stretch the visit beyond the scan itself. The first is a second look, if a supervising cardiologist or physician wants an extra view before you leave; that can add ten or fifteen minutes and is not a bad sign. The second is department flow, which no source can predict for you. Arriving a few minutes early, with a list of your medicines and any prior heart test results, keeps the part you control as smooth as possible.
If your letter mentions a stress echo or a transesophageal echo, the timing changes substantially, and those are covered in their own sections below.
What is an echocardiogram, and how does ultrasound actually see a beating heart?
An echocardiogram is an ultrasound scan of the heart: high-frequency sound waves are sent into the chest and the echoes that bounce back are turned into moving pictures. The physics is the same principle a bat uses to navigate a dark barn. The probe, called a transducer, emits pulses far above the range of human hearing, then listens. Sound travels at different speeds through blood, muscle, and valve tissue, and reflects at the boundaries between them. A computer measures how long each echo took to return and how strong it was, then paints a real-time image, frame after frame, dozens of times a second.

That live motion is the whole point. A chest X-ray shows the heart’s silhouette; an echo shows the heart working. You can watch the left ventricle, the main pumping chamber, squeeze and relax. You can see the mitral and aortic valves open and snap shut. Add Doppler, the technique that detects the shift in pitch from moving blood, and the machine can color-code flow: one color toward the probe, another away, with turbulence lighting up where a valve leaks or narrows.
From those images the sonographer takes measurements. The best known is the ejection fraction, the percentage of blood the left ventricle pushes out with each beat; the American Heart Association describes a normal range of roughly 55 to 70 percent. Wall thickness, chamber size, and the pressure gradient across a valve are all estimated from the same recording.
None of this involves radiation. MedlinePlus notes that echocardiography has no known risks from the sound waves themselves, which is why it can be repeated as often as a clinician needs to track a condition over years.
What happens step by step during a standard transthoracic echocardiogram?
Picture the room first: dim lighting, a monitor angled toward the technician, a couch with a drop-away section on the left side so the probe can reach around the ribs. You lie on your left side with your left arm tucked under your head. That position lets the heart fall toward the chest wall, closer to the probe, which is why sonographers are so particular about it.
The sequence usually runs like this:
- Electrodes are attached to your chest so the machine can label each image with the moment in the heartbeat it was captured.
- Cool gel is applied to the probe or your skin. It removes the air gap between probe and chest; sound waves cannot cross air.
- The probe is placed beside the breastbone, then under the ribs near the left nipple, then at the tip of the heart, and finally at the top of the abdomen and the base of the neck. Each spot is a “window” between ribs and lungs.
- At each window the sonographer records short clips, freezes frames, and traces outlines with a cursor. You will hear a whooshing or clicking sound when Doppler is switched on; that is blood flow rendered as audio.
- Near the end you may be asked to roll onto your back for the last views.
Mayo Clinic lists these positional changes and breath-holds as routine parts of the test. The gel is wiped off, the electrodes come away, and you can dress and leave. There is no recovery period after a transthoracic scan, no restriction on driving, and no reason to avoid eating beforehand unless your letter says otherwise. Most people describe the experience as a long, slightly awkward massage of one side of the chest.
Why does the sonographer press so hard, and why the breath-holds?
This is the question people whisper afterward, half-embarrassed. The pressure has a purpose. Ribs and lungs are enemies of ultrasound; bone blocks the beam and air scatters it. The only clear paths are narrow gaps, and the sonographer angles into them by pushing the probe firmly and tilting it a few degrees at a time. On someone with a barrel chest or a lot of lung inflation, those gaps are smaller and the pressing is firmer. Uncomfortable, occasionally, particularly under the ribs; painful, rarely. If it hurts, say so. A different angle or a moment’s rest usually solves it.
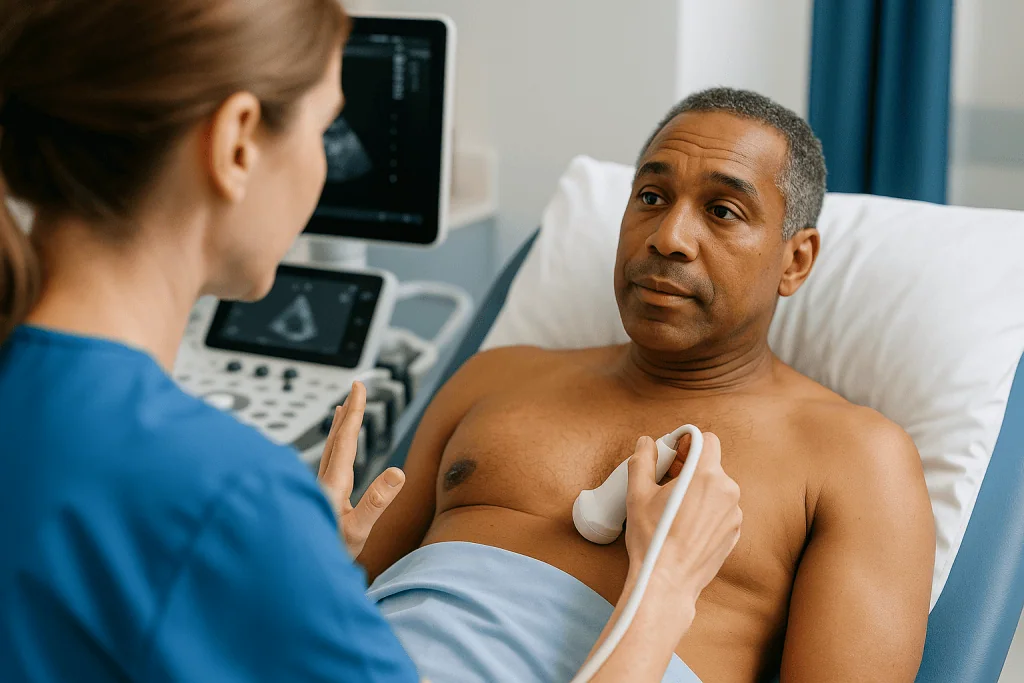
Breath-holds work the same way. When you exhale and hold, the diaphragm rises and the lungs shrink, pulling air out of the way and letting the heart settle against the chest wall. The sonographer may ask you to breathe out and hold for a few seconds while a clip records, or to take a slow breath in for a different view. Cleveland Clinic describes these instructions as a normal part of the scan, and they are usually brief.
Two more things puzzle first-timers. The first is silence. Sonographers often say very little while they work, not because they are hiding something but because measuring a valve while explaining the image is like typing and talking at once. The second is that they generally will not interpret the pictures for you. In most services the technician acquires the images and a cardiologist reads them afterward; the person holding the probe is not the person authorized to give you a diagnosis. Asking “does it look OK?” tends to get a kind, non-committal answer, and that is protocol rather than evasion.
What are the different types of echocardiogram, and how do their timings compare?
“Echo” is a family of tests rather than a single one. The letter you received will name the type, and the type determines how long you are in the building, whether you fast, and whether you need someone to take you home. The table below summarizes what mainstream sources describe.
| Type | How it is done | Typical time | Preparation and aftercare |
|---|---|---|---|
| Transthoracic (TTE) | Probe on the chest wall | 15 to 60 minutes (NHS); often 40 to 60 with check-in (Cleveland Clinic) | No fasting; no recovery; drive yourself |
| Stress echo | Images before and after treadmill or bike exercise, or after a medicine that speeds the heart | About an hour, per Mayo Clinic | Light food only for a few hours before; bring comfortable shoes; caffeine guidance from your team |
| Transesophageal (TEE/TOE) | Thin probe passed down the throat under sedation and throat numbing | Scan itself around 20 minutes (NHS); expect several hours on site | Fasting beforehand; no driving that day; someone to accompany you |
| Fetal echo | Probe on the pregnant abdomen | Varies; often comparable to a detailed pregnancy ultrasound | No special preparation |
The transthoracic scan is the default and what most people mean by “an echo.” A stress echo is requested when the question is how the heart behaves under load, since some problems with blood supply only show when the muscle is working hard. The transesophageal version trades convenience for clarity: the esophagus sits directly behind the heart, so the probe gets an unobstructed view of the valves and the left atrium without ribs or lungs in the way. It is reserved for questions the chest scan cannot answer well, such as looking for clots before a rhythm procedure or examining an artificial valve.
Which type you have is a clinical decision, made by the team that knows the question they are trying to answer.
How long does a stress echocardiogram take compared with a resting scan?
A stress echo roughly doubles the involvement without doubling the scan. Mayo Clinic describes the whole appointment as taking about an hour, and the structure explains why. First comes a resting scan, shorter than a full transthoracic study because it targets specific views. Then you exercise, typically on a treadmill or stationary bike, while electrodes track your rhythm and someone watches your blood pressure. The goal is to push your heart rate toward a target set from your age, or until you reach the point where you would naturally stop. That effort phase is often only several minutes for a reasonably fit adult; it feels longer.
Immediately afterward, and this is the part that surprises people, you are asked to lie down fast and the probe goes back on. The imaging window after exercise is brief, because heart rate falls quickly once you stop. The sonographer moves briskly, capturing the same views taken at rest so the cardiologist can compare them side by side. A segment of heart wall that squeezes well at rest but slackens under stress hints that its blood supply cannot keep up.
Some people cannot exercise safely, whether because of joint problems, balance, or breathing limits. In that case a medicine given through a small cannula in the arm speeds the heart or opens the coronary vessels to mimic exertion. The medicine acts within minutes and wears off within minutes once stopped, which is why this version fits into a similar time slot. Any choice between exercise and medicine, and any decision to stop the test early, rests with the team supervising it.
Plan for the hour, wear shoes you could walk a hill in, and expect to feel sweaty rather than sore.
How to prepare for an echocardiogram: do you need to fast?
For a standard chest echo, preparation is almost disappointingly simple. Eat normally. Take your usual medicines unless the referring clinician has said otherwise; do not stop or skip anything on your own initiative, because a medicine that slows the heart or lowers pressure may be exactly what the reading needs to account for. The NHS and Mayo Clinic both note that no special preparation is needed for the transthoracic test.
A few practical choices make the visit easier:
- Wear a top that comes off easily; you will be undressed from the waist up and given a gown that opens at the front.
- Skip body lotion on the chest that morning. Gel grips better on clean skin, and the electrodes stick more reliably.
- Bring a list of your medicines and any previous heart test results, particularly an earlier echo. Comparison is one of the most valuable things a cardiologist can do with a new scan.
- If you have a pacemaker or an implanted defibrillator, mention it; it changes nothing about safety but helps the sonographer interpret what they see.
Preparation changes for the other types. Before a stress echo, Mayo Clinic advises against eating or drinking anything but water for a few hours beforehand, and your team may give instructions about caffeine and about certain heart medicines that could blunt the response. Before a transesophageal echo, fasting for several hours is standard, because a numbed throat and sedation raise the risk of food or fluid going the wrong way. You will also need someone to take you home, since sedatives impair judgment and reflexes well after you feel awake.
The single most useful preparation is asking, when you book, which type you are having. Everything else follows from that answer.
Who is usually referred for an echocardiogram, and who is asked to wait?
The echo sits at the crossroads of cardiology because it answers so many different questions. Clinicians commonly request one when a stethoscope picks up a murmur, when breathlessness or ankle swelling raises the possibility of heart failure, after a heart attack to see how much muscle was affected, when palpitations or fainting need a structural explanation, or when an irregular rhythm such as atrial fibrillation is diagnosed. The American Heart Association lists valve disease, cardiomyopathy, congenital defects, and clots inside the heart among the findings it can reveal. People on certain cancer treatments known to strain the heart may have scans at intervals to watch for change.
Not everyone with a heart-shaped worry gets one immediately, and that is appropriate rather than dismissive. Chest pain assessed as coming from the chest wall or the stomach, a murmur in a child that has all the features of an innocent flow sound, or palpitations with a normal electrical tracing and no other findings may be handled without imaging, or with an echo scheduled later if symptoms persist. Routine echocardiograms in people with no symptoms and no findings are not supported by guidelines, because a normal scan in a low-risk person adds little and occasionally throws up incidental findings that lead to further tests without benefit.
Urgency also varies. A new murmur with fainting, or symptoms suggesting fluid on the lungs, tends to be scanned quickly; a stable, known valve condition on a monitoring schedule can safely wait for its planned slot. If your appointment feels a long way off and your symptoms are changing in the meantime, that is a reason to contact the referring clinician rather than assume the wait has been calibrated to your current state. They can re-prioritize; you cannot.
Is an echocardiogram painful, and what are the real risks?
The honest answer for the standard scan is: not painful, sometimes uncomfortable. The discomfort comes from probe pressure under the ribs and from lying on one side for a stretch, which can make a shoulder ache. The gel is cool. The electrodes can tug fine chest hair when removed. MedlinePlus states plainly that there is very little risk from the test, and that the ultrasound itself has no known harmful effects at diagnostic levels. Pregnant women, children, and people who have had dozens of scans over a lifetime are imaged without concern for cumulative exposure, because there is nothing to accumulate.
Stress echocardiography carries the risks of the exercise or the medicine rather than of the imaging. Mayo Clinic notes that complications are uncommon and that the test is supervised so that any chest pain, rhythm disturbance, or pressure change can be acted on immediately. People often feel breathless, flushed, or briefly nauseated with the medicine-based version; these sensations pass as the drug clears.
The transesophageal version is where genuine, if small, risks appear. Passing a probe down the throat can cause a sore throat afterward, and rarely a minor injury to the lining of the esophagus. Sedation brings its own considerations, which is why you are monitored and cannot drive that day. The NHS advises not eating or drinking until the throat numbing has fully worn off, usually about an hour, to avoid choking.
Set against these, the risk of not having a needed scan is missing a treatable valve problem or a weakening heart muscle. That is the balance your clinician has weighed before writing the request.
What can an echocardiogram show, and what can't it?
Think of the echo as a structural and mechanical report. It measures chamber sizes, so it can show a stretched left atrium or a thickened ventricle wall. It assesses pumping, expressed as ejection fraction and, in more detailed analysis, as the motion of each wall segment. It inspects every valve for narrowing and leaking and estimates how severe each is. It estimates pressure in the lung circulation from the speed of blood flowing back through the right-sided valves. It sees fluid around the heart, holes between chambers, and, particularly in the transesophageal version, clots and infections on valve surfaces. Cleveland Clinic and the American Heart Association both list these among its core uses.
What it cannot do is look inside the coronary arteries. The vessels that supply the heart muscle are too small and too mobile for ultrasound to map. An echo can infer that a region of muscle is starved, because that segment moves poorly, but it cannot show the blockage causing the problem. That is the job of a CT coronary angiogram or an invasive angiogram, tests that use contrast dye and X-rays.
It also does not record the heart’s electrical activity in the way an ECG or a wearable monitor does. Palpitations that come and go for seconds at a time need a rhythm recording, not a picture. And the echo gives one snapshot; a heart that looks structurally fine today does not guarantee it will in a decade, which is why some conditions are monitored on a schedule.
The scan is one instrument in an orchestra. A normal echo is genuinely reassuring about structure and pumping. It is not a clean bill of health for every possible cardiac question, and your clinician will read it alongside symptoms, blood tests, and rhythm tracings.
Echocardiogram results: how long until you hear, and what the following days and weeks look like
Here is the part the referral letter never explains. The sonographer records the images and often takes preliminary measurements, but a cardiologist or trained physician reviews and reports the study afterward. The NHS notes that results are usually sent to the doctor who requested the test rather than handed to you at the scanner. How quickly the report is written varies by department; a matter of days is common, and urgent findings are flagged the same day. In a few services a physician reads the images while you are still on the couch, and you may leave with a verbal summary, but this is not the norm and its absence is not a warning sign.
The days after a standard echo are ordinary. There is nothing to recover from. Stress echo leaves the same fatigue as any brisk workout. After a transesophageal scan, a scratchy throat for a day or two is typical, and the sedative can make you feel foggy into the evening, which is why the NHS advises against driving, operating machinery, or signing important documents until the following day.
The following weeks depend entirely on what the images show. Three broad paths exist. A normal or reassuring scan often closes the loop, with a letter or a brief follow-up appointment. A finding that needs watching, such as a mildly leaky valve, typically leads to a repeat echo at an interval your team chooses, sometimes a year or more away. A finding that changes management, whether a reduced ejection fraction or a significantly narrowed valve, leads to a conversation about treatment options, further tests, or referral to a specialist clinic. Which path applies, and on what timeline, is a decision for the treating team.
What people often get wrong about echocardiograms
Myth one: “They found something, or they wouldn’t have ordered it.” Echoes are ordered to answer questions, and a great many of those questions are answered with “no.” A murmur that turns out to be benign flow, breathlessness that turns out to be lung-related or deconditioning, palpitations with a structurally normal heart: these are common outcomes, and the scan earned its place by ruling things out.
Myth two: “An echo is basically an ECG with pictures.” They measure different things. An ECG records electrical signals over seconds; an echo images structure and motion. A person can have a perfectly normal ECG and a significantly narrowed valve, or a worrying rhythm and a structurally normal heart. Clinicians frequently want both.
Myth three: “The technician looked serious, so it must be bad.” Sonographers concentrate. Measuring a valve gradient while adjusting a probe and monitoring a rhythm tracing does not leave much face for smiling. Their neutrality is professional, not prognostic.
Myth four: “It involves radiation, so I should limit how many I have.” It does not. Ultrasound carries no ionizing radiation, which MedlinePlus and the NHS both state. Repeat scans over years are routine in valve surveillance precisely because they are safe to repeat.
Myth five: “A normal echo means my arteries are clear.” It means the muscle is pumping well and the valves are working, which is valuable. It does not image the coronary arteries. Someone with a normal echo can still have significant coronary disease, and someone with heart-attack damage can have a clearly abnormal one. If your question is about arteries, a different test answers it.
Myth six: “I need to stop my heart tablets so the scan is accurate.” No. Unless your team gives explicit instructions, which they sometimes do before a stress test, take everything as usual.
Questions to ask your care team before and after the scan
A few well-aimed questions turn a passive appointment into something you understand. Before the scan, the most useful ones are logistical and diagnostic at the same time:
- Which type of echocardiogram am I having, and does it involve exercise, sedation, or fasting?
- What is the specific question you are hoping this scan will answer?
- Should I take all my usual medicines that morning, or has anything been paused for the test?
- Do I need someone to bring me home?
- Will anyone talk to me about the images on the day, or will the results go to you first?
After the scan, the questions shift toward meaning and next steps:
- Was the heart’s pumping function normal, and if a number such as ejection fraction was measured, where does mine sit against the usual range?
- Did the valves look normal, and if not, how severe is the finding and does it need watching or acting on?
- Does this result change anything about my current treatment?
- Will I need a repeat scan, and roughly when?
- If the scan was normal, what do you think is causing my symptoms, and what happens next?
One more question is worth asking if you have had an echo before: “Has anything changed since the last one?” Comparison over time is often more informative than any single measurement, which is why bringing prior reports matters. Write the answers down. Cardiology appointments compress a lot of information into a few minutes, and the details that feel obvious in the room have a way of blurring by the time you reach the car park.
When to call your doctor: red-flag signs around an echocardiogram
The scan itself almost never causes harm, so the important warning signs are about the heart condition being investigated, not the test. Do not wait for a scheduled echocardiogram if you develop chest pain or pressure lasting more than a few minutes, especially with sweating, nausea, or pain spreading to the arm, jaw, or back; sudden severe breathlessness or breathlessness that wakes you from sleep; fainting or near-fainting, particularly during exertion; a racing or irregular heartbeat with dizziness or chest discomfort; or rapidly worsening swelling of the legs or abdomen. These are reasons to seek emergency care immediately, not to wait for a report. The American Heart Association and the NHS list these among the symptoms that need urgent assessment.
After a stress echocardiogram, contact your doctor the same day if chest discomfort continues after you have rested and recovered, or if you feel faint or notice palpitations that do not settle within an hour or so.
After a transesophageal echocardiogram, a mild sore throat is expected. Call the team that performed the test if you have severe throat or chest pain, difficulty swallowing that worsens rather than eases, vomiting blood, a fever, or a persistent feeling of something stuck in the throat. These are uncommon but need checking.
Between the scan and your results, call your referring clinician if your symptoms change meaningfully, if you were expecting a result and several weeks have passed without word, or if you are unsure what the plan is. Chasing a result is not a nuisance; it closes a loop that matters. And if anything on this list happens, the decision about what it means and what to do belongs to the clinicians who can examine you, not to a search engine.
Frequently asked questions
How long does an echocardiogram take if it is my first one?
Plan for around an hour. The NHS gives a range of 15 to 60 minutes for the transthoracic scan, and first studies tend to sit toward the longer end because the sonographer records a full set of measurements with no earlier scan to compare against. Body shape and lung conditions can add time. You can leave immediately afterward with no recovery period.
How to prepare for an echocardiogram the night before?
For a standard chest echo, nothing special: eat and sleep normally and take your usual medicines unless told otherwise. Skip chest lotion in the morning and wear a top that is easy to remove. If you are having a stress or transesophageal echo, your letter will specify fasting and any medicine instructions; follow those exactly and ask the department if anything is unclear.
Is an echocardiogram painful or uncomfortable?
It is not painful, though firm probe pressure under the ribs and lying on your left side for a while can be uncomfortable. The gel feels cool and electrodes may tug when removed. MedlinePlus describes the risk from the ultrasound itself as very low. Tell the sonographer if anything hurts; a small change in angle usually fixes it.
What are the main types of echocardiogram?
The three you are likely to encounter are transthoracic, done with a probe on the chest; stress echo, which adds exercise or a heart-stimulating medicine; and transesophageal, where a thin probe is passed down the throat under sedation for a clearer view. Fetal echocardiography images an unborn baby’s heart through the abdomen. Your referral letter should name which one you are having.
Echocardiogram results: how long until my doctor gets them?
Usually within days, though this varies by department. A cardiologist or trained physician reviews the images after the scan and sends a report to the doctor who requested it, as the NHS describes. Urgent findings are flagged the same day. If several weeks pass without contact, call the referring clinic; chasing a result is reasonable and expected.
Can I drive home after an echocardiogram?
After a standard transthoracic echo, yes; there is no sedation and no recovery period. After a stress echo, most people can drive once they have rested, unless the team advises otherwise. After a transesophageal echo you must not drive that day, because the sedative impairs reflexes and judgment even when you feel alert, so arrange for someone to accompany you.
Does an echocardiogram show blocked arteries?
Not directly. Ultrasound cannot image the coronary arteries, which are too small and mobile. A stress echo can show a region of heart muscle that moves poorly under exertion, which suggests reduced blood supply, but confirming a blockage needs a CT coronary angiogram or an invasive angiogram. Your clinician chooses the test that matches the question.
Why did the sonographer not tell me what they saw?
Because in most services the sonographer acquires the images and a cardiologist interprets and reports them afterward. The technician is usually not authorized to give a diagnosis, and a non-committal answer reflects protocol rather than bad news. Ask your referring doctor when and how you will receive the result so you know what to expect.
Is an echocardiogram safe during pregnancy?
Yes. Echocardiography uses sound waves and no ionizing radiation, and MedlinePlus notes no known harmful effects at diagnostic levels. Pregnant women are scanned when breathlessness, palpitations, or a murmur need explanation, and fetal echocardiography images the baby’s heart through the abdomen. Tell the department you are pregnant so positioning can be adjusted for comfort.
How often do people need repeat echocardiograms?
It depends entirely on the finding. A normal scan for a question that has been answered may never need repeating. Mild valve leaks or stable cardiomyopathy are often re-scanned at intervals of a year or more, while some conditions or treatments call for closer monitoring. The interval is set by your treating team based on what the images show and how your symptoms evolve.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Is a Pulmonary Embolism Treated? Anticoagulants, Thrombolysis and Catheter Options
A pulmonary embolism is treated mainly with anticoagulant medicines, which stop the clot from growing and prevent new ones while the body gradually dissolves…

Stroke Volume Explained: The Heart’s Output per Beat
Stroke volume is the amount of blood the heart's left ventricle pumps out with a single contraction — roughly 70 milliliters in a healthy…

Does Insulin Cause Weight Gain? Why It Happens and How to Manage It
Insulin therapy can contribute to modest weight gain — in long-term trials, roughly 4 kilograms (about 9 pounds) over several years, with most of…

Type 1 vs Type 2 Diabetes: The Difference, and Which Is More Serious
Type 1 diabetes is an autoimmune condition in which the immune system destroys the pancreas's insulin-producing cells, so insulin must be replaced from diagnosis…

How to Lower Cholesterol Naturally: What Moves LDL Without a Prescription
You can lower LDL cholesterol meaningfully without medication by replacing saturated fats with unsaturated ones, eating 5 to 10 grams of soluble fiber daily…

ECG Explained: What It Shows, How Long It Takes and What Happens
An ECG (electrocardiogram) records your heart's electrical activity through sticky skin electrodes, showing heart rate, rhythm, and patterns that can suggest arrhythmias, reduced blood…