

What Pancreatitis Feels Like, Where the Pain Is and Whether It Comes and Goes
Key Takeaways
- Pancreatitis pain is typically steady and boring rather than cramping, and it usually starts just below the breastbone before spreading through to the back.
- Lying flat tends to worsen the pain while curling forward eases it, a positional pattern that is uncommon in stomach bugs or simple heartburn.
- Acute pancreatitis persists for days rather than flickering on and off, and the NHS reports most people begin to feel better within about a week.
- Gallstones cause roughly half of acute cases and alcohol about a quarter, so many people admitted with pancreatitis have never drunk heavily.
- Chronic pancreatitis often announces itself through greasy, pale, floating stools and unexplained weight loss long before the pain becomes constant.
- No home test exists; diagnosis rests on blood tests for pancreatic enzymes and imaging, and those enzyme levels rise within hours of an attack.
Pancreatitis usually feels like a deep, steady, boring pain high in the abdomen, just below the ribs, that often spreads through to the back and worsens after eating or lying flat. Acute pancreatitis comes on over hours and persists for days; chronic pancreatitis can flare and settle, sometimes becoming constant. Nausea, vomiting and fever are common. Sudden severe abdominal pain needs urgent medical assessment.
A colleague once described it as “someone pressing a fist into my stomach from the inside and refusing to let go.” She had spent the evening folded over the kitchen counter, knees drawn up, convinced the salmon was to blame. By morning the pain had wrapped around to her spine, and the emergency department found her pancreas swollen and inflamed.
Her story is typical in one specific way: almost nobody suspects the pancreas. It is a slim, pale gland tucked behind the stomach, roughly the length of a hand, and most people could not point to it. So the pain gets blamed on indigestion, a pulled back muscle or last night’s dinner, sometimes for a day or more.
What follows is an honest walk through what the pain genuinely feels like, where it sits, how it behaves over hours and weeks, and how clinicians tell it apart from the crowd of conditions that imitate it.
What does pancreatitis pain actually feel like?
People who have lived through it reach for the same three words: deep, boring, constant. Not the cramping wave of a stomach bug that builds and then releases, and not the sharp, catch-your-breath stab of a strained muscle. Pancreatitis pain sits behind the abdominal wall and leans on you. Mayo Clinic describes it as upper abdominal pain that may spread to the back and feel worse after eating; the NHS notes it usually builds quickly to a severe, steady ache.
Why so relentless? The pancreas manufactures digestive enzymes designed to break down fat and protein once they reach the intestine. When the gland becomes inflamed, those enzymes switch on early, inside the tissue that made them, and the organ effectively begins digesting itself. Swelling stretches the thin capsule around the gland and irritates the dense web of nerves running behind it, right against the spine. That anatomy explains why the sensation feels deep rather than surface-level, and why it so often reaches through to the back.
Intensity varies more than people expect. Some describe a heavy, bruised feeling that lets them pace the room but not face food. Others cannot stand upright, vomit repeatedly and need hospital care within hours. In chronic pancreatitis the same pain may become duller and grinding, punctuated by sharper flare-ups after meals.
One caution for anyone trying to self-diagnose from adjectives: pain quality alone never identifies the pancreas. It narrows the field. Blood tests and imaging finish the job.
Where exactly is pancreatitis pain felt?
Lay a hand flat across your abdomen with the top edge touching the lower ribs, roughly in the center. That region, the epigastrium, is where pancreatitis pain most often begins. Because the pancreas lies horizontally across the back of the upper abdomen, its head tucked into the curve of the small intestine on the right and its tail stretching toward the spleen on the left, the pain can favor the left side or feel like a band drawn across the whole upper belly.
The signature feature, and the one that separates it from ordinary heartburn, is radiation. Many people describe the pain traveling straight through to the back, typically between the shoulder blades or a little lower, a pattern noted by both the NHS and Mayo Clinic. Some feel it mainly in the back and only later notice the abdomen. Anatomically this makes sense: the inflamed gland sits directly in front of the spine, and the nerves supplying it share pathways with nerves from the back.
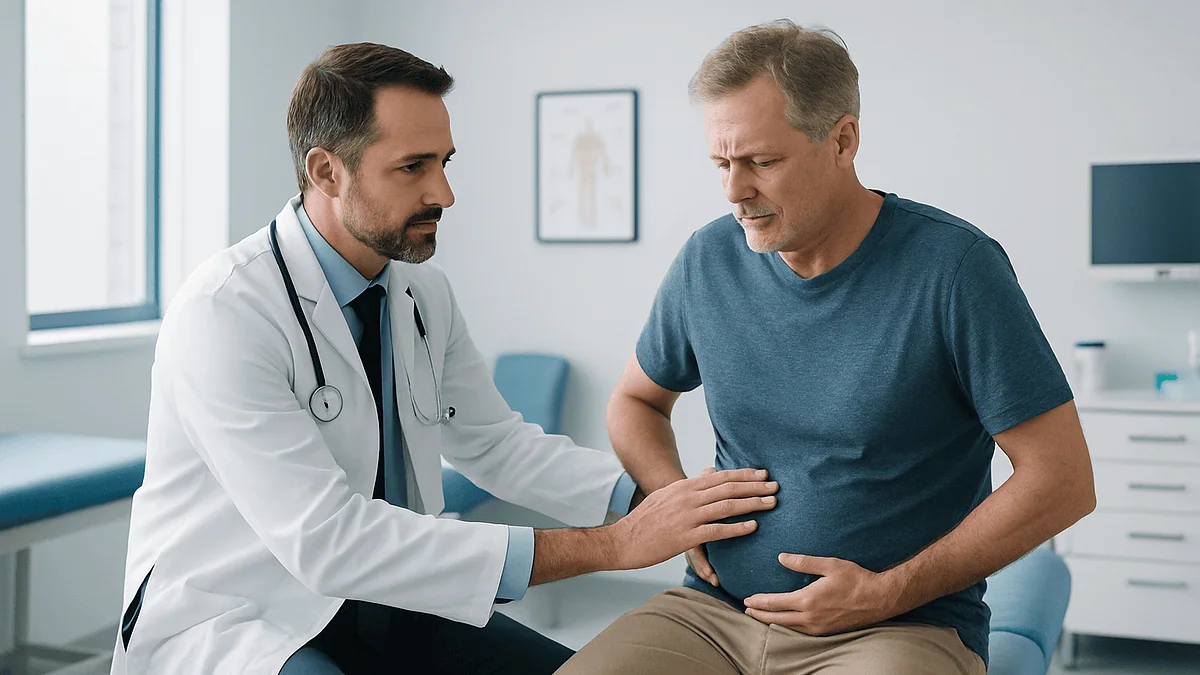
Two habits are worth knowing. Lying flat tends to make the pain worse, presumably because it stretches the inflamed tissue; people instinctively curl forward or sit hunched with a pillow pressed to the belly, a position the NHS lists as one that can ease the pain. And the upper abdomen is usually tender to touch; in more severe cases it may look distended and feel firm.
What the pain generally does not do is start low in the pelvis, sit sharply under the right rib margin (more typical of the gallbladder) or wander around the abdomen the way trapped gas does. Location earns the pancreas a spot on the list. It does not close the case.
Does pancreatitis pain come and go?
The honest answer is: it depends which kind of pancreatitis you have, and on what timescale you mean.
Acute pancreatitis behaves like a single, sustained event. The pain usually comes on over minutes to a few hours, climbs to a plateau and then stays there. It does not flicker on and off across an evening. Over the following days, as inflammation settles, it fades gradually rather than switching off. The NHS reports that most people with acute pancreatitis start to feel better within about a week, though tiredness and tenderness can linger longer.
Pain that genuinely comes and goes minute to minute, building to a peak and then easing before the next wave, is more characteristic of colic, the pattern seen when a gallstone lodges in a duct or the bowel squeezes against a blockage. Confusingly, gallstones are also the leading cause of acute pancreatitis, so a person can experience colicky waves first and a steady pancreatic ache afterward.
Chronic pancreatitis is the form that truly comes and goes. According to the NHS, people experience repeated episodes of upper abdominal pain lasting hours or several days, separated by intervals of weeks or months. Episodes are often triggered by eating, particularly fatty meals, or by alcohol. Over years the pattern can shift, and for some people the pain becomes constant with sharper flares layered on top.
A third pattern, recurrent acute pancreatitis, means separate full-blown attacks with complete recovery in between. The gap between them can be months or years, which is why each attack can catch people off guard.
What are the early warning signs of pancreatitis?
People searching for early warning signs usually want a whisper before the shout, a sensation that signals trouble a day ahead. For acute pancreatitis that whisper rarely exists. The first sign is most often the pain itself, arriving suddenly or building over a few hours, as the NHS describes. Some people recall a vague fullness or loss of appetite beforehand, but it is indistinguishable from ordinary indigestion.
The earliest clue is therefore not a separate symptom but the behavior of the pain. It settles high in the abdomen instead of moving. It intensifies rather than easing after a couple of hours. It refuses to respond to burping, passing wind or a change of position, except that leaning forward may take the edge off. Nausea arrives, then vomiting, and unlike a stomach bug, vomiting brings no relief because the problem is not in the stomach.
Chronic pancreatitis is the form with genuine early signs, and they are quiet ones. Repeated bouts of upper abdominal discomfort after meals that get filed under “my digestion.” Stools that turn pale, greasy, bulky and hard to flush, a sign that the gland is no longer releasing enough enzyme to digest fat. Weight drifting down without trying. Bloating. Later, the appearance of diabetes, because the same organ makes insulin. Mayo Clinic and the NHS both list these as hallmarks of chronic disease.
The pattern to respect is a recurring one: upper abdominal pain that returns after eating, especially alongside changes in your stools or weight. That combination deserves a clinician’s attention rather than a dietary experiment.
Symptoms beyond pain: what else pancreatitis does to the body
Pain dominates the conversation, but pancreatitis rarely arrives alone. The accompanying symptoms are often what convinces someone the situation is serious.
Nausea and vomiting are almost universal in acute attacks, according to Mayo Clinic and the NHS. Vomiting tends to be repeated and unsatisfying; the stomach empties, and the pain does not budge. Fever follows in many cases, with the NHS citing a temperature of 38°C (about 100.4°F) or higher as a typical threshold. The heartbeat quickens, partly from pain and partly from fluid shifting out of the bloodstream into inflamed tissue. People often look pale, sweaty and unwell in a way that friends notice before they do.
Jaundice appears when a gallstone blocks the shared duct that drains both the pancreas and the liver. The skin and whites of the eyes take on a yellow tint, urine darkens to the color of strong tea and stools turn pale. The NHS lists this trio as a recognized feature, and it points strongly toward a gallstone cause.
Severe attacks affect organs far from the abdomen. Breathlessness, confusion, a dramatic drop in urine output or a cold, clammy feeling all signal that inflammation has spilled over into the whole system. The NHS notes that around 1 in 5 cases of acute pancreatitis are severe, with complications that need intensive support.
Chronic pancreatitis adds a slower set of changes: oily stools, weight loss, vitamin deficiencies and eventually diabetes, each reflecting a gland that has lost working tissue.
Acute vs chronic pancreatitis: how the two feel different
The same organ, the same underlying inflammation, yet two conditions that feel almost unrelated to the person living through them. Acute pancreatitis is an emergency with a beginning and, for most people, an end. Chronic pancreatitis is a long-term condition in which repeated inflammation gradually scars the gland and erodes its ability to digest food and regulate blood sugar. The table below sets the two side by side using descriptions from the NHS and Mayo Clinic.
| Feature | Acute pancreatitis | Chronic pancreatitis |
|---|---|---|
| How it starts | Suddenly, or building over a few hours | Gradually, over months or years of recurring episodes |
| Pain character | Severe, steady, deep; often spreads to the back | Dull, grinding, recurring; may become constant over time |
| Duration of pain | Days, easing over roughly a week in most cases | Episodes of hours to days, with pain-free gaps |
| Triggers | Often none obvious at the moment of onset | Eating, especially fatty meals; alcohol |
| Other symptoms | Nausea, vomiting, fever, fast pulse, sometimes jaundice | Greasy pale stools, weight loss, bloating, diabetes |
| Most common causes | Gallstones, alcohol | Long-term heavy alcohol use, smoking, genetic factors |
| Typical course | Most people recover fully; about 1 in 5 cases are severe | Damage is permanent; symptoms are managed long term |
One nuance matters here. A first episode of severe pain does not tell you which column you belong in. Chronic pancreatitis frequently begins with an attack that looks entirely acute, and only the years that follow reveal the pattern. That is a reason to take a first attack seriously and to follow up with your care team afterward rather than treating it as a closed chapter.
How do I know if pain is from my pancreas?
You cannot know for certain from the outside, and neither can an experienced physician standing at the bedside. What you can do is read the cluster of clues that makes the pancreas likely enough to justify testing.
Start with position and direction. Pain centered high in the abdomen that bores through to the back scores highly. Then consider behavior: steady rather than colicky, worse after eating, worse lying flat, eased slightly by leaning forward. Add the company it keeps: nausea and vomiting that bring no relief, a tender upper belly, perhaps a fever.
Context tips the balance further. Known gallstones, a heavy drinking session in the previous day or two, very high triglycerides on a past blood test, a recent endoscopic procedure on the bile ducts, or a family history of pancreatic disease all raise the odds. Certain medications are also recognized triggers, which is why clinicians review your full list; that judgment belongs to the prescribing team.
Now the honest limits. Heartburn, gallbladder inflammation and a peptic ulcer can all produce upper abdominal pain with nausea. The back can hurt for a dozen other reasons. Pressing on your own abdomen tells you it hurts, not why.
MedlinePlus and the NIH’s digestive diseases institute are clear that diagnosis rests on blood tests showing raised pancreatic enzymes plus imaging, not on symptoms alone. The practical rule is simple: if the cluster above sounds like you, the next step is a clinical assessment the same day, not another hour of guessing.
What can mimic pancreatitis pain?
The upper abdomen is crowded real estate. Stomach, gallbladder, liver, duodenum, pancreas and the lower edge of the heart all report pain to overlapping nerves, so several conditions can wear a convincing pancreatitis costume.
Gallbladder disease is the most frequent impostor and the most frequent companion. Biliary colic produces intense pain under the right ribs after a fatty meal, arriving in waves that peak and ease. Inflammation of the gallbladder adds fever and tenderness on the right. Because gallstones cause about half of acute pancreatitis cases, per the NHS, the two often occur together.
A peptic ulcer or gastritis causes a burning or gnawing pain in the same central spot, sometimes eased by food, sometimes worsened. If an ulcer perforates, the abdomen turns suddenly rigid and the pain becomes excruciating, which is itself an emergency.
The heart deserves special mention. Mayo Clinic notes that a heart attack can present as upper abdominal pain with nausea and sweating rather than classic chest pressure, particularly in older adults, in women and in people with diabetes. Any upper abdominal pain accompanied by breathlessness, sweating or pain spreading into the arm or jaw should be treated as cardiac until proven otherwise.
Other mimics include bowel obstruction, kidney stones (pain usually in the flank), pneumonia in the lower lung, shingles in the days before the rash appears and, rarely, problems with the aorta.
Notice that most of these are at least as urgent as pancreatitis. The mimic list is not a reason for reassurance; it is a reason the same-day assessment applies whichever organ turns out to be responsible.
What causes pancreatitis, and who is most at risk?
Ask a room of people what causes pancreatitis and most will say alcohol. The evidence tells a broader story. According to the NHS, gallstones account for around half of acute cases, while alcohol accounts for about a quarter. Plenty of people admitted with pancreatitis have never drunk heavily, and framing the condition as a drinker’s disease delays diagnosis for everyone else.
The gallstone mechanism is mechanical. The pancreatic duct and the bile duct usually merge before emptying into the small intestine. A stone that lodges at that junction dams up pancreatic juice, pressure builds and enzymes activate inside the gland. Alcohol works differently, injuring the enzyme-producing cells directly and thickening secretions so they drain poorly. Heavy drinking over years is also the leading cause of chronic pancreatitis, as the NHS notes, with smoking as an independent contributor that accelerates damage.
A longer tail of causes accounts for the rest. Very high blood triglycerides, high blood calcium, certain medicines (identified and managed by the prescribing clinician), viral infections, abdominal injury, complications of endoscopic procedures on the bile ducts, autoimmune inflammation and inherited gene variants all appear on the lists published by Mayo Clinic and the NIH. In a meaningful minority of cases no cause is ever found.
Risk is therefore not a single profile. Someone with gallstones and no other risk factor, a person with a family history of pancreatic disease and a person who drinks heavily face the same inflamed gland by different routes. What they share is the same need for prompt assessment when the pain arrives.
How can I check if I have pancreatitis?
There is no home test, no app and no position or pressure point that confirms pancreatitis. The check happens in a clinical setting, and it has two parts.
Blood tests come first. When the pancreas is inflamed, digestive enzymes leak into the bloodstream, and levels of two of them, amylase and lipase, rise sharply, often within hours of the pain beginning. MedlinePlus and the NIH describe these as the central diagnostic tests for an acute attack. Clinicians also check white cell count, liver tests, calcium, triglycerides, blood sugar and kidney function, partly to find the cause and partly to judge how hard the body is being hit.
Imaging comes second. An ultrasound scan looks for gallstones and a dilated bile duct. A CT scan shows the swollen gland, fluid collections and any areas where tissue has been damaged, and is often reserved for cases that are severe or unclear. MRI of the ducts can reveal small stones or structural narrowing that other scans miss.
Chronic pancreatitis is harder to pin down. Enzyme levels may be normal because the scarred gland has little left to leak. Diagnosis leans on imaging showing calcification or duct changes, stool tests measuring undigested fat or a marker of enzyme output, and the clinical picture over time.
If you are in pain now and wondering whether to wait and see, the timing question resolves itself: enzyme levels and scans are most informative early. Being assessed promptly gives you a clearer answer, not just a faster one.
When should you see a doctor about suspected pancreatitis?
Sudden severe pain in the upper abdomen is a reason to seek emergency care the same day, regardless of what you think is causing it. The NHS advises contacting a doctor immediately if you develop symptoms of acute pancreatitis, and calling emergency services or going to the emergency department if the pain is severe. In the United States that means calling 911 or heading to the nearest emergency room, not waiting for a morning appointment.
Certain red flags raise the urgency further. Seek emergency help without delay if severe upper abdominal pain comes with any of the following:
- Vomiting that will not stop, or an inability to keep fluids down
- A fever, or feeling shivery and unwell alongside the pain
- Yellowing of the skin or eyes, dark urine or pale stools
- A racing heartbeat, breathlessness, faintness or a cold, clammy feeling
- Confusion or unusual drowsiness
- A belly that has become rigid, swollen or exquisitely tender
- Pain following heavy drinking, or in someone with known gallstones
Remember that chest pain can masquerade as stomach pain. Upper abdominal pain with sweating, breathlessness or discomfort spreading to the arm, neck or jaw should be treated as a possible heart problem.
The slower pattern needs attention too. Recurring upper abdominal pain after meals, greasy or pale stools, unexplained weight loss or newly diagnosed diabetes together warrant a prompt appointment with your primary care clinician so that chronic pancreatitis can be considered and investigated. Bring a note of when the pain occurs, what precedes it and how long it lasts; that timeline is as useful to your doctor as any single test.
What happens after diagnosis, and what does treatment involve?
Acute pancreatitis is almost always managed in hospital, and much of the early care is supportive rather than dramatic. Inflammation pulls fluid out of the circulation, so intravenous fluids restore it. Pain is controlled with analgesic medication chosen and adjusted by the treating team based on severity and your other health conditions. Oxygen is given if levels drop. Nutrition is reintroduced as soon as it can be tolerated; the NHS notes that eating early, rather than resting the gut for days, is now the usual approach when the person can manage it.
Monitoring is the quiet backbone of care. Pulse, blood pressure, urine output, oxygen and blood tests are tracked closely because the NHS reports that about 1 in 5 cases are severe, and severity often reveals itself over the first 48 hours rather than at the door. Complications such as fluid collections, infected tissue or organ strain may require imaging, drainage procedures or intensive care.
Treating the cause comes next. When gallstones are responsible, removal of the gallbladder is usually recommended, sometimes during the same admission and sometimes soon after, to prevent another attack. A stone stuck in the duct may be removed endoscopically. When alcohol is the trigger, support to stop drinking is part of the treatment plan, not an afterthought.
Chronic pancreatitis is managed over years: pain strategies, replacement of the digestive enzymes the gland no longer makes, attention to blood sugar, stopping smoking and alcohol, and in selected cases endoscopic or surgical procedures on the ducts. Every one of these decisions belongs to you and your treating team.
What recovery and living with pancreatitis really feel like
People expect recovery from an acute attack to mirror the onset: fast. It rarely does. The pain subsides over days, but the fatigue that follows a serious inflammatory illness can last weeks. Appetite creeps back before energy does. The upper abdomen may stay tender to pressure for a while, and a large meal can feel heavier than it used to. Care teams commonly advise a period without alcohol during recovery and sometimes a lower-fat diet at first; the specifics depend on cause and severity and should come from the clinicians who know your case.
The follow-up matters as much as the admission. A first attack prompts the question every person should ask: why did this happen, and can it happen again? If gallstones were found, that conversation is about gallbladder surgery. If no cause was identified, it may involve further blood tests or scans. Skipping this step is how a preventable second attack arrives.
Chronic pancreatitis asks for a different mindset. The NHS describes a long-term condition in which flare-ups of pain, digestive symptoms and eventually diabetes are managed rather than cured. Many people learn their own triggers, notice that smaller and less fatty meals sit better, and work with dietitians on maintaining weight and vitamin levels. Long-standing chronic pancreatitis also carries a raised risk of pancreatic cancer, which is why regular follow-up and reporting new or changed symptoms is part of living well with it.
The through-line is not fear. It is attention: to the pattern of pain, to what your body does after meals, and to the value of a care team that knows your history.
Frequently asked questions
What are the early warning signs of pancreatitis?
For acute pancreatitis, the first sign is usually the pain itself: a steady ache high in the abdomen that builds over hours, spreads to the back and brings nausea and vomiting that offer no relief. Chronic pancreatitis has quieter early signs, including recurring upper abdominal discomfort after meals, pale greasy stools that are hard to flush, bloating and unexplained weight loss. Any of these patterns deserves a medical assessment rather than a wait-and-see approach.
How do I know if pain is from my pancreas?
You cannot confirm it without tests, but a recognizable cluster raises the likelihood. Pain centered just below the ribs that bores through to the back, stays constant rather than coming in waves, worsens after eating or lying flat and eases slightly when leaning forward is characteristic. Nausea, vomiting, fever and a tender upper abdomen add weight. Known gallstones or recent heavy drinking add more. Blood tests for pancreatic enzymes and imaging provide the actual answer.
How can I check if I have pancreatitis?
There is no reliable home check. Pancreatitis is diagnosed through blood tests that measure the pancreatic enzymes amylase and lipase, which rise sharply within hours of an acute attack, along with imaging such as ultrasound, CT or MRI to see the gland and look for gallstones or complications. Chronic pancreatitis may need stool tests and specialized scans because enzyme levels can be normal. If you suspect it, seek same-day medical assessment.
What can mimic pancreatitis pain?
Gallbladder disease is the most common look-alike, producing upper abdominal pain after fatty meals, and it often occurs alongside pancreatitis because gallstones cause both. Peptic ulcers, gastritis, bowel obstruction, kidney stones, lower-lobe pneumonia and early shingles can also imitate it. A heart attack can present as upper abdominal pain with nausea and sweating, particularly in older adults, women and people with diabetes. Most of these mimics are just as urgent, so the same-day assessment applies either way.
Does pancreatitis pain come and go?
In acute pancreatitis the pain is continuous, building over hours and persisting for days before gradually easing. Pain that switches on and off minute to minute is more typical of gallstone or bowel colic. Chronic pancreatitis genuinely comes and goes, with episodes lasting hours to days separated by pain-free weeks or months, often triggered by eating or alcohol. Over years the pattern can shift toward constant background pain with sharper flare-ups layered on top.
Where is pancreatitis pain felt?
Pancreatitis pain is felt mainly in the upper middle abdomen, just below the breastbone, and may favor the left side or stretch as a band across the upper belly. Its defining feature is radiation straight through to the back, usually between or just below the shoulder blades. The area is typically tender to touch. Pain that begins low in the pelvis or sits sharply under the right ribs points more toward other organs, though the gallbladder and pancreas often act together.
Can you have pancreatitis without severe pain?
Yes, though it is less common. Some people with acute pancreatitis describe a heavy, bruised sensation rather than agony, and older adults or those with other serious illnesses may present mainly with vomiting, confusion or a rapid pulse. Chronic pancreatitis can progress with mild recurring discomfort, while greasy stools, weight loss or new diabetes are the more prominent clues. Severity of pain does not reliably reflect severity of disease, which is why testing matters.
Does pancreatitis pain get worse after eating?
It often does. Eating signals the pancreas to release digestive enzymes, and an inflamed gland responds with more swelling and pressure, so pain frequently intensifies within an hour or so of a meal. Fatty foods and alcohol are the most consistent triggers, particularly in chronic pancreatitis, where meals are the classic prompt for a flare. Loss of appetite is common for the same reason: the body learns quickly that food hurts.
How long does pancreatitis pain last?
In acute pancreatitis the pain typically lasts several days, easing gradually as inflammation settles. According to the NHS, most people improve within about a week, although around 1 in 5 cases are severe and take considerably longer, sometimes requiring intensive care. Chronic pancreatitis produces episodes lasting hours to days that recur over months and years, and in some people the pain eventually becomes constant. Tiredness and tenderness can outlast the pain itself.
Can pancreatitis be mistaken for back pain?
It can, and it regularly is. Because the pancreas sits directly in front of the spine and shares nerve pathways with the back, some people feel the pain mainly between the shoulder blades or in the mid-back and blame a muscle strain. The clue is company: back pain from pancreatitis usually arrives with nausea, vomiting, loss of appetite or upper abdominal tenderness, and it does not improve with rest or changes in posture the way a mechanical back problem often does.
References
- NHS: Acute pancreatitis
- NHS: Chronic pancreatitis
- MedlinePlus: Pancreatitis
- Cleveland Clinic: Pancreatitis
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Asthma Is Diagnosed: Breathing Tests, History and What to Expect at the Clinic
Asthma is diagnosed by combining a detailed symptom history with objective breathing tests. Clinicians look for a pattern of cough, wheeze, chest tightness or…

Living with One Kidney: What Changes and What Does Not
Yes. Most people with one healthy kidney live a normal, full life. The remaining kidney enlarges and increases its filtering capacity, typically providing around…
Can Lupus Be Fatal? What Decides the Risk and How Modern Treatment Changes It
Lupus can be fatal, but for most people today it is not. Serious risk comes from a small number of complications: kidney inflammation, cardiovascular…

Can Crohn’s Disease Be Fatal? What Actually Decides the Risk
Crohn's disease is rarely fatal on its own. Most people with Crohn's live long lives, and average life expectancy is only modestly shorter than…

How IBS Is Diagnosed (and the ‘Do I Have IBS?’ Question)
IBS is diagnosed clinically, not with a single test. A clinician confirms that recurrent abdominal pain has been linked to bowel movements or changes…

Can You Get HIV from Kissing or Oral Sex? What the Evidence Says
Closed-mouth kissing does not transmit HIV, and saliva on its own has never been shown to spread it. The CDC describes deep, open-mouth kissing…