

When Does Graves Disease Affect the Eyes, and When Is an Eye Specialist Brought In?

Key Takeaways
- About 30 percent of people with Graves disease develop noticeable eye involvement, and most of those cases are mild (NIDDK; NHS).
- Thyroid eye disease is a separate autoimmune process in the eye socket and can begin before, during, or after thyroid hormone levels are controlled (Mayo Clinic).
- The active, inflammatory phase typically lasts six months to two years, and immune-directed treatment is aimed at that window (Cleveland Clinic).
- Structural surgery for alignment, lid position, or prominence is usually deferred until measurements have been stable for several months, except when sight is threatened.
- Smoking is the strongest modifiable risk factor for developing and worsening thyroid eye disease, and the risk falls after stopping (NHS; NIDDK).
- Radioactive iodine can worsen eye disease in some people, especially smokers and those with active inflammation, which is why eye specialists are often consulted before it is chosen (NIDDK; Mayo Clinic).
Graves disease affects the eyes in roughly one in three people, usually around the time thyroid symptoms appear but sometimes months before or after, when the same antibodies inflame the fat and muscle behind the eye. An eye specialist is typically brought in for persistent grittiness with swelling, visible bulging, double vision, eye pain, or any change in vision, and urgently for color loss, dimming, or an eye that cannot close.
Maria noticed it in a photograph before she felt it. Her left eye looked a little wider than her right, as if she had been startled mid-blink. She had been treated for an overactive thyroid for four months and assumed the tremor and racing heart were the whole story. The gritty, sandpaper feeling on waking she had blamed on screens.
Her endocrinologist looked, asked a few pointed questions, and said the words a lot of people hear at this point: it may be time to involve a Graves disease eye specialist. Not because something catastrophic was happening, but because the eyes in this condition run on their own clock, and the earlier someone who studies eye sockets joins the conversation, the more options stay open.
This explainer follows that handover. It covers why the thyroid and the eye sockets share an illness, which signs make a referral timely rather than optional, and what actually happens once you are in the chair.
Why does Graves disease affect the eyes at all?
The same immune misfire that speeds up the thyroid has a second target. In Graves disease, the body makes antibodies against the TSH receptor, the docking site that normally tells the thyroid to make hormone. Those antibodies switch the gland on without permission. The twist is that cells in the tissue behind the eye, called orbital fibroblasts, carry the same receptor, along with a partner receptor for insulin-like growth factor 1 (IGF-1). When antibodies bind there, the fibroblasts behave as if wounded: they multiply, recruit inflammatory cells, and release water-attracting sugars that swell the tissue like a soaked sponge.
The orbit, the bony socket that holds the eye, has almost no spare room. It is a cone of bone open only at the front. So when the six small muscles that move the eye thicken and the fat pad expands, the only direction available is forward. That forward push is proptosis, sometimes called exophthalmos: the eye sits further out than it should. Eyelids that once met comfortably may no longer close fully, the surface dries, and stiff muscles pull the two eyes out of alignment so their images stop overlapping.
Two points follow from this mechanism and shape everything else in this article. First, the eye problem is a separate autoimmune process, not a side effect of high hormone levels. It can begin while thyroid tests are still normal or after they have been brought under control (Mayo Clinic). Second, because the driver is inflammation with a natural beginning and end, the illness behaves differently in its early hot phase than in its later quiet one, and the eye specialist’s job is largely to judge which phase you are in and act accordingly.
How common is eye involvement, and when in the illness does it start?
Most people with Graves disease never need more than lubricating drops. Around 30 percent develop noticeable eye involvement, according to the National Institute of Diabetes and Digestive and Kidney Diseases, a figure the NHS rounds to about one in three among those whose overactive thyroid is caused by Graves disease. Within that group the majority have mild disease: dryness, puffiness, a wider stare. Only a small minority progress to double vision that interferes with daily life or to pressure on the optic nerve, the cable carrying images from eye to brain (Cleveland Clinic).
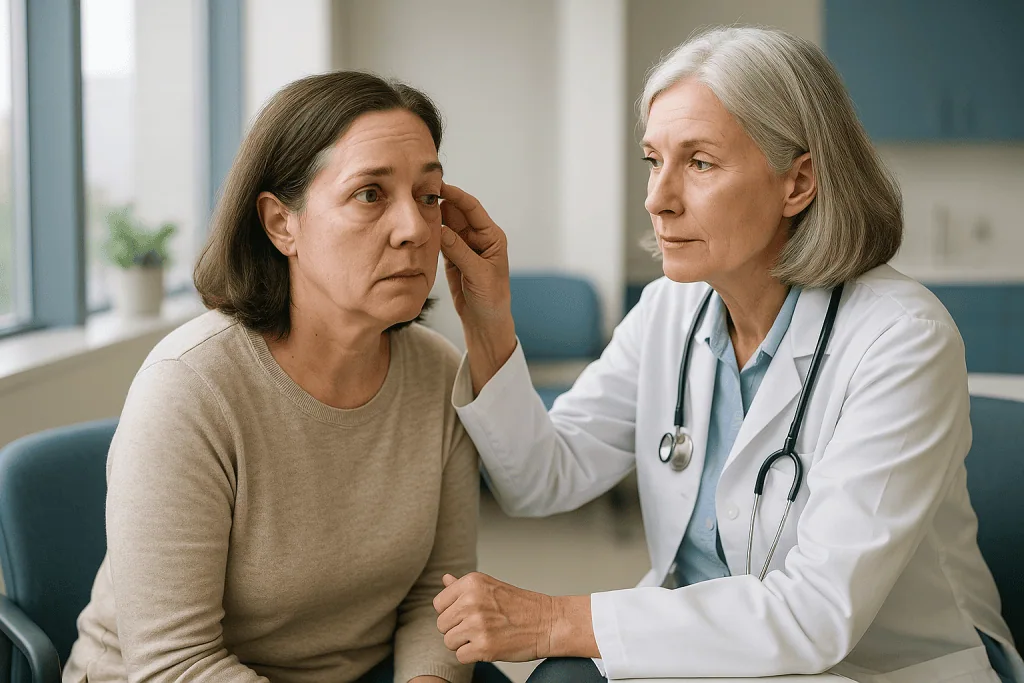
Timing is less tidy than people expect. Eye signs most often surface within the same stretch of months as the thyroid diagnosis, but they can lead the way or trail behind long after hormone levels are settled (Mayo Clinic). Some people are diagnosed with thyroid eye disease first and only then discover the gland is the source. Others develop eye changes later, sometimes after a treatment such as radioactive iodine, discussed further down.
Certain circumstances tilt the odds. Smoking is the clearest, and the risk rises with how much a person smokes (NHS). High antibody levels, thyroid function that swings between too high and too low, and radioactive iodine therapy given while eye inflammation is already active are the other well-documented contributors (NIDDK). Women are affected more often, in line with Graves disease overall (Mayo Clinic). None of these factors predicts an individual’s course, which is why specialists prefer a measured baseline early rather than a guess made later.
Thyroid eye disease symptoms: what people usually notice first
The first complaints are rarely dramatic, which is exactly why they get missed. People describe a gritty, sandy feeling on waking, eyes that water in wind, redness that does not respond to allergy drops. Eyelids look puffy in the morning and settle by afternoon. A partner or a photograph notices a staring quality before the person does. Bright light becomes uncomfortable. There may be a dull ache behind the eyes or a sense of pressure that worsens when looking up.
Later changes are more specific. Double vision, called diplopia, often shows up first when glancing upward or to one side, or when tired at the end of the day. Because the muscle that lifts the eye is commonly involved, checking a high shelf or looking at a ceiling can split an image in two. The upper lid may retract so more white shows above the iris. One eye is often ahead of the other, and that asymmetry is a useful clue that this is not simple dry eye or hay fever.
What matters medically is not the list but the pattern and pace. An eye specialist wants to know whether symptoms are new or years old, stable or shifting week to week, and whether anything has changed in what you can actually see. Blurring that clears with a blink usually reflects a dry surface. Blurring that persists, colors that look washed out, or a dimming that feels like a lamp turned down are different and are treated as urgent, because they can signal pressure on the optic nerve. If something on this page sounds familiar, the right next step is a conversation with the clinician managing your thyroid, who can examine you and decide whether referral is needed.
When is a Graves disease eye specialist brought in?
No single blood test or scan triggers a referral. The decision rests on symptoms, examination, and the thyroid team’s comfort with what they see. Guideline groups broadly agree on the pattern: mild, stable eye involvement can often be watched by the endocrinologist or family doctor with simple measures, while anything beyond mild, anything changing, and anything touching vision warrants an ophthalmologist.

In practice a Graves disease eye specialist is usually brought in when one or more of these applies: double vision at any time of day; eye pain, especially pain on moving the eyes; visible or measured forward displacement of one or both eyes; redness and swelling that persists for weeks despite lubricants; lids that do not fully close in sleep; or any reported change in the sharpness or color of vision. Many endocrinologists also refer smokers and people with high antibody levels before radioactive iodine is considered, so that the eyes have a documented baseline and any active inflammation is identified first (NIDDK).
Speed depends on the finding. Vision changes, fading color perception, an eye that cannot be closed, or a cornea that looks cloudy are same-day or next-day referrals. New double vision or rapidly increasing swelling is typically seen within a couple of weeks. Concern about appearance with stable measurements can wait for a routine slot, though the wait should still have a date attached.
Some centers run combined thyroid eye clinics where an endocrinologist and an ophthalmologist see patients together. Where that is not available, the two clinicians write to each other and the patient moves between them. Either model works if someone owns the plan. Ask who that is, and write the name down.
Which Graves disease eye specialist will you actually see?
The phrase eye specialist hides several different jobs. An ophthalmologist is a physician trained in eye diseases and eye surgery; most thyroid eye disease referrals go here first. Within ophthalmology, an oculoplastic or orbital surgeon concentrates on the eyelids, tear system, and the socket behind the eye, and is the person who performs decompression and eyelid procedures if they are ever needed. A neuro-ophthalmologist focuses on the optic nerve and the brain’s control of eye movement, and is often consulted when vision is threatened or when double vision has an unusual pattern. A strabismus surgeon realigns the eye muscles once double vision has settled into a fixed misalignment.
Two further roles matter. An orthoptist is a specialist who measures eye movements and alignment with precision and fits prisms, thin wedges added to glasses that bend light so two images merge into one. An optometrist may be the first to spot proptosis or lid retraction during a routine eye test and can start the referral. Neither replaces the ophthalmologist for decisions about inflammation or surgery.
Your endocrinologist does not step back when the eye team steps in. Thyroid hormone levels that are too high or too low both aggravate the eye disease (NIDDK), so the two specialties work in parallel: one steadies the gland, the other watches the orbit. In some places a single joint clinic does both under one roof; elsewhere you carry letters between offices. Whatever the arrangement, you should expect the eye specialist to know your current thyroid status and any planned thyroid treatment, and the thyroid specialist to know whether your eyes are active or quiet. If either seems unaware, say so; that gap is where problems hide.
What actually happens at the first eye appointment
Expect the visit to run longer than a routine eye check, and expect a lot of measuring. The specialist begins with your story: when the eyes changed, how quickly, whether one side led, whether you smoke, and what thyroid treatment you have had. Then come the tests, most of them painless.
Visual acuity is read from a chart. Color vision is tested with numbered plates, because red saturation fades early when the optic nerve is under pressure. Pupil reactions are checked with a light. The examiner asks you to follow a target in nine directions and notes where movement is limited or where images double. An exophthalmometer, a small ruler that rests on the bony rim beside each eye, records how far forward the cornea sits, and the reading is compared at every later visit. Eyelid position is measured against the pupil. Eye pressure is checked, sometimes in more than one gaze position, because a stiff muscle can raise it artificially. At the slit lamp, a microscope with a bright beam, the cornea is inspected for dry spots and the lids for swelling. The optic disc at the back of the eye is examined, and a visual field test may be added.
These findings are summarized in two ways. A Clinical Activity Score tallies signs of current inflammation such as pain, redness, and swelling; it answers whether the disease is hot right now. A severity grading, mild, moderate to severe, or sight threatening, describes how much the disease has already done. The two do not always move together, and treatment choices hinge on the pairing.
Photographs are taken for comparison. A CT or MRI scan of the orbits is not always necessary but is ordered when the diagnosis is uncertain, when the nerve may be compressed, or when surgery is being planned. You leave with a baseline, and everything afterward is judged against it.
The thyroid eye disease timeline: active phase versus inactive phase
Thyroid eye disease is not a fixed state. It moves through phases, and the shape of that journey was sketched decades ago as a rising and falling curve: inflammation builds, peaks, then subsides, leaving behind whatever structural change occurred at the height of the storm.
The active phase, when the immune system is driving swelling and redness, typically lasts six months to two years (Cleveland Clinic). Symptoms fluctuate, measurements shift between visits, and this is the window in which anti-inflammatory treatment can alter the course. The inactive, or fibrotic, phase follows: inflammation has burned out, but stretched muscles and expanded fat may have set into scar. Appearance and alignment are now stable but not necessarily normal. Care here is rehabilitative rather than suppressive.
| Phase | What is happening in the orbit | Typical duration | Usual focus of care |
|---|---|---|---|
| Active (inflammatory) | Immune cells and fluid swell muscle and fat; measurements changing | About 6 months to 2 years (Cleveland Clinic) | Protect the surface, control inflammation, guard the optic nerve |
| Plateau | Inflammation easing; changes slowing | Variable | Monitor; confirm stability over repeated visits |
| Inactive (fibrotic) | Scarred, stable tissue; no new inflammation | Long term | Correct what remains: alignment, lid position, prominence, if wanted |
The practical consequence is a rule most specialists apply: medicines that quiet the immune system are used while the disease is active, and structural surgery waits until it has been quiet for a sustained stretch, usually judged over several months of unchanged measurements. The exception is a threat to sight, which is treated whenever it arises. Knowing which phase you occupy is the single most useful thing to carry out of an eye appointment, and it is a fair question to ask directly.
Who is usually treated now, and who is usually asked to wait
People are often surprised, and sometimes hurt, to be told to wait. It helps to understand that waiting in this condition is an active choice with a rationale, not a dismissal.
Those usually offered treatment promptly fall into two groups. The first is anyone with a threat to vision: optic nerve compression, or a cornea exposed because the lids cannot close. These situations are treated urgently regardless of phase. The second is people with moderate to severe disease that is clearly active, meaning inflammation scores are high and measurements are worsening; here immune-directed treatment has its best chance of changing the trajectory, because there is still a fire to put out.
Those usually asked to wait, or more accurately to watch, are people with mild disease. Mild does not mean trivial; it means the changes are small, the eyes are not in danger, and the balance of benefit and risk favors simple measures: lubricants, stopping smoking, steady thyroid levels, and review at set intervals. A proportion of mild cases settle on their own as the active phase passes (Cleveland Clinic). A second waiting group is people whose disease has become inactive and who want correction of double vision, lid position, or prominence. Surgery is generally deferred until measurements have been stable for a sustained period, because operating on tissue that is still changing risks having to operate again.
Between those poles sit people whose inflammation is settling but not settled, or whose thyroid levels are not yet controlled. For them the plan is usually a defined interval, a repeat set of measurements, and a decision at the next visit. That interval should be stated, not left open. If your symptoms change before it arrives, the appointment moves forward, and you should feel free to ask that it does.
Graves ophthalmopathy treatment options, explained by how they work
Every treatment in this field aims at one of three things: comfort for the surface of the eye, control of inflammation in the orbit, or correction of structural change once inflammation has gone. Choices are made by the ophthalmologist and endocrinologist together, and nothing here is a recommendation for any individual.
Comfort measures come first for everyone. Preservative-free lubricating drops by day and thicker gels at night compensate for lids that do not fully cover the eye. Prisms in glasses merge doubled images while alignment is still changing.
Controlling inflammation relies on medicines that dampen the immune response. Glucocorticoids, the steroid family, have the longest track record in moderate to severe active disease and are generally given in courses arranged by the specialist; they reduce swelling and pain but carry risks to blood sugar, bone, mood, sleep, and the liver that have to be weighed for each person. A newer class blocks the IGF-1 receptor on orbital fibroblasts, interrupting the signal that makes them swell; teprotumumab is the generic name of the agent in this class. Trials have shown reductions in proptosis, but it has its own side effects, including hearing changes and blood sugar effects, and longer-term data are still accumulating. Other immunosuppressants and orbital radiotherapy, low-dose radiation directed at the socket, are used in selected cases, often alongside steroids.
Correcting structure is surgical and follows a sequence. Orbital decompression removes bone or fat from the socket to let the eye settle back; it comes first because it can shift alignment. Strabismus surgery then repositions muscles to remove double vision in straight-ahead and reading gaze. Eyelid surgery comes last to adjust retraction or remove excess tissue. Each step carries the ordinary risks of surgery plus specific ones, such as new double vision after decompression, which the surgeon will describe. Not everyone needs all three; many need none.
How your thyroid treatment choices interact with your eyes
Getting the thyroid right is eye treatment too. Hormone levels that run high or swing low both feed the inflammation in the orbit, and the eye team will want your endocrinologist aiming for steady, normal levels rather than a rapid overshoot into underactivity (NIDDK).
Three routes exist for the gland, and they interact with the eyes differently. Antithyroid drugs, the thionamide class, block the enzyme the thyroid uses to build hormone; they act over weeks and are adjusted by blood tests. They do not worsen eye disease and are often preferred while the eyes are active, because they leave the gland in place and allow gradual control. Radioactive iodine is swallowed, concentrates in thyroid cells, and destroys them from within over weeks to months. It is effective for the gland but can worsen eye disease in a proportion of people, particularly smokers and those whose eye inflammation is already active (NIDDK; Mayo Clinic). For that reason it is sometimes deferred, avoided, or given with a protective course of steroids arranged by the treating team. Surgical removal of the thyroid takes away the antibody-stimulating gland and does not carry the same eye-worsening signal; it involves general anesthesia and the standard risks of neck surgery.
After radioactive iodine or surgery, the thyroid becomes underactive and lifelong hormone replacement follows. That transition matters for the eyes: a spell of untreated underactivity is itself a risk for eye deterioration, so blood tests are scheduled closely around it. None of this decides the treatment for you. It explains why your eye specialist may ask to be consulted before a thyroid plan is finalized, and why that request is worth honoring even when it adds a few weeks.
Thyroid eye disease and smoking, plus the everyday measures with real evidence
If one fact from this article changes something, let it be this one. Smoking is the strongest modifiable risk factor for developing thyroid eye disease, for it becoming severe, and for it responding poorly to treatment (NHS; NIDDK). The mechanism is thought to involve low oxygen in orbital tissue and direct stimulation of fibroblasts by components of smoke. The risk is related to how much a person smokes, and it falls after stopping. Nobody treating thyroid eye disease considers cessation optional, and most will offer or point to structured help rather than a lecture.
Beyond that, the daily measures with evidence are modest but genuine. Sleeping with the head raised on an extra pillow lets fluid drain overnight and reduces morning lid swelling. Wraparound sunglasses outdoors ease light sensitivity and wind-driven watering. Lubricating drops during the day and a thicker gel at night protect a surface the lids no longer fully cover; when closure is poor in sleep, some specialists suggest taping the lids or a moisture shield. Prisms, either stick-on or ground into lenses, are fitted by an orthoptist and can restore single vision for reading and driving while alignment is unstable. Covering one eye for a specific task is a blunt but effective way to stop double vision.
Selenium comes up often. Trial evidence, mainly from parts of Europe where dietary intake is relatively low, suggests modest benefit in mild, early disease, and European guidance mentions it as an option to discuss in that setting. Evidence from regions where diets are already selenium-rich is weaker, and it has no established role in moderate or severe disease. It is a conversation for your specialist, not a self-prescription, and supplements are not a substitute for the measures above.
What the following weeks and months usually look like
After the first eye visit, life settles into a rhythm of measurement. In the active phase, review is usually every few weeks to a few months, depending on how fast things are moving; each visit repeats the acuity, color, movement, and exophthalmometer readings and sets them beside the baseline. Photographs taken in the same lighting help catch subtle shifts. Thyroid blood tests continue in parallel, and the two clinics compare notes.
Symptoms will not move in a straight line. Grittiness is often worse in winter heating and on windy days. Morning swelling may improve within weeks of raising the bed and stopping smoking, while proptosis, if present, changes slowly and is measured rather than felt. Double vision can appear, shift, or disappear as different muscles swell and settle, so prisms may need remeasuring. People starting immune-directed treatment often notice pain and redness easing first, over weeks, with changes in eye position lagging behind (Cleveland Clinic).
Driving deserves a specific mention. Double vision that is not corrected by prisms or by covering one eye is generally incompatible with safe driving, and licensing rules in many places require it to be reported. Your eye specialist can explain how that applies to you.
Stability is declared, not assumed. Most surgeons want a stretch of unchanged measurements, commonly judged over several months, before planning any structural surgery, so a quiet period of watchful appointments is part of the pathway rather than a delay in it. Throughout, keep a short diary: dates, what changed, a photograph now and then. It is the most useful thing you can bring to a follow-up, and it turns a vague sense that things are worse into something a clinician can act on.
What people often get wrong about Graves disease and the eyes
Treating the thyroid fixes the eyes. It helps, but the orbit runs its own immune process. Steady hormone levels remove a fuel source; they do not switch off the inflammation, which is why eye disease can flare after the gland is well controlled (Mayo Clinic).
Bulging eyes mean the thyroid is still overactive. Proptosis reflects swollen tissue in the socket, not hormone levels. People with normal or even low thyroid tests can have active eye disease, and people with very high levels can have entirely normal eyes.
It is only cosmetic. Appearance matters and deserves respect, but the medical concerns are surface exposure, double vision, and pressure on the optic nerve. Specialists grade the condition on function first and appearance second.
Surgery can be done at any time. Structural surgery is deferred until the inflammatory phase has passed and measurements are stable, because operating on tissue that is still changing invites revision. Urgent decompression for a threatened nerve is the exception, not the rule.
Steroids are the whole treatment. They are one tool, used in active moderate to severe disease, with real side effects. Many people never need them; some are offered other classes or radiotherapy; most need lubricants, smoking cessation, and time.
Once it stops, it never returns. Reactivation is uncommon but recognized, particularly after radioactive iodine or a return to smoking, which is why follow-up continues after the active phase ends.
Everyone with Graves disease gets it. Around 30 percent develop noticeable eye involvement (NIDDK), and most of those cases are mild. A diagnosis of Graves disease is a reason for an eye baseline, not a forecast of what will happen to your face.
Questions to ask your care team
A good appointment is partly what you bring to it. The questions below are the ones specialists say they wish more people asked, because the answers shape everything that follows. Take them written down; the room can feel rushed, and measurements are easier to remember than judgments.
- Is my eye disease active or inactive right now, and how did you decide?
- How severe is it on your grading, and which findings put it there?
- What are today’s measurements for eye position, lid position, and eye movements, so I can compare them next time?
- How often will you see me during this phase, and what would make you bring the appointment forward?
- Are you and my thyroid doctor in contact, and does the thyroid plan need to change because of my eyes?
- If radioactive iodine is being considered, does my eye status affect that choice?
- Which everyday measures do you want me to use, and is there anything you would rather I did not try?
- If treatment is suggested, what is it meant to change, what are its main risks, and what happens if I do nothing for now?
- Which symptoms should make me call the same day rather than wait for my next visit?
- Do I need to report anything about my vision for driving?
One more, less comfortable, is worth asking early: who is coordinating my care between the two specialties? The answer might be the endocrinologist, the ophthalmologist, a nurse specialist, or a joint clinic. Any of those works. An absence of an answer is a problem you can fix by asking.
Finally, ask how to reach the team between visits. Thyroid eye disease is a condition of change, and the value of a specialist lies partly in being reachable when the change is sudden.
When to call your doctor
Most of thyroid eye disease is slow, and most of it is managed at planned visits. A few things are different and should not wait for the next scheduled appointment. Call your eye specialist or thyroid team the same day, or seek urgent care if you cannot reach them, if you notice any of the following.
- Vision in one or both eyes becomes blurred and does not clear with blinking or lubricating drops.
- Colors look faded or washed out, especially red, or one eye sees colors differently from the other.
- Sight dims, as if a light has been turned down, or part of your field of view disappears.
- Sudden or rapidly worsening eye pain, particularly pain on moving the eyes.
- Double vision that appears suddenly or changes sharply over a day or two.
- One eye seems to have moved forward noticeably over days rather than months.
- An eyelid will not close, or you wake with a scratchy, very painful eye that feels as if something is in it.
- The clear front of the eye looks cloudy or white, or the eye is intensely red and sensitive to light.
These signs can indicate pressure on the optic nerve or damage to the exposed cornea, both of which are time-sensitive and treatable when caught early (Cleveland Clinic). Do not put drops in and wait to see.
Separately, tell your thyroid team promptly if you develop a racing or irregular heartbeat, marked tremor, unexplained weight change, or new swelling in the neck, since shifting hormone levels affect the eyes as well as the rest of the body. And if you are ever unsure whether something counts as urgent, the safer call is the phone call. Every decision about what happens next belongs to the team examining you; your job is to give them the chance to make it in time.
Frequently asked questions
When should I see an eye specialist for Graves disease?
A referral is usually made when there is double vision, eye pain, visible forward displacement of an eye, persistent redness and swelling despite lubricants, lids that do not close in sleep, or any change in vision. Vision changes, color loss, or an eye that cannot close are urgent. Mild dryness and puffiness with stable measurements can often be watched by your thyroid team first.
What are the earliest thyroid eye disease symptoms?
The earliest changes are usually a gritty or sandy feeling on waking, watering in wind, redness that allergy drops do not fix, morning eyelid puffiness, light sensitivity, and a staring look others notice before you do. These are not a self-diagnosis tool; an examination by the clinician managing your thyroid decides whether they point to eye involvement and whether a specialist should be involved.
How long does the thyroid eye disease timeline usually run?
The active inflammatory phase typically lasts six months to two years, after which the disease enters a stable, inactive phase (Cleveland Clinic). Symptoms fluctuate during the active period and settle afterward, though structural changes such as prominence or misalignment may remain. Follow-up continues beyond the active phase because reactivation, while uncommon, is recognized.
Does thyroid eye disease and smoking really go together?
Yes. Smoking is the strongest modifiable risk factor for developing thyroid eye disease, for it becoming severe, and for a weaker response to treatment (NHS; NIDDK). The risk rises with how much a person smokes and falls after stopping. Specialists treat cessation as part of the treatment plan rather than a side note, and structured support is usually offered.
Can I have thyroid eye disease if my thyroid tests are normal?
Yes. The eye disease is driven by antibodies acting on tissue behind the eye, not by hormone levels themselves, so it can appear when thyroid tests are normal, before the thyroid becomes overactive, or after it has been treated (Mayo Clinic). That is why an eye specialist may be involved even when your endocrinologist is satisfied with your blood results.
What does graves ophthalmopathy treatment involve?
Treatment depends on phase and severity. Everyone uses lubricants and stops smoking. Active moderate to severe disease may be treated with medicines that dampen the immune response, such as glucocorticoids or an IGF-1 receptor blocker, chosen by the specialist. Once the disease is inactive, surgery can correct prominence, double vision, or lid position in a set sequence. Many people need lubricants and monitoring only.
Will radioactive iodine make my eyes worse?
It can in a proportion of people, particularly smokers and those whose eye inflammation is already active (NIDDK; Mayo Clinic). For that reason it is sometimes deferred, avoided, or given with a protective course of steroids arranged by the treating team. Antithyroid drugs and thyroid surgery do not carry the same signal. The choice belongs to your endocrinologist and eye specialist together.
Which type of eye doctor treats thyroid eye disease?
Most referrals go to an ophthalmologist, a physician trained in eye disease and surgery. Within that field, oculoplastic or orbital surgeons manage the socket and lids, neuro-ophthalmologists focus on the optic nerve, and strabismus surgeons correct fixed double vision. Orthoptists measure alignment and fit prisms. Your endocrinologist continues to manage the thyroid alongside them.
Why is surgery for bulging eyes delayed?
Because operating on tissue that is still inflamed and changing risks needing a second operation. Surgeons usually wait until measurements have been stable for several months, showing the disease has entered its inactive phase. The exception is a threat to sight from optic nerve compression, which is treated urgently regardless of phase.
Can I drive with double vision from thyroid eye disease?
Uncorrected double vision is generally incompatible with safe driving, and licensing authorities in many places require it to be reported. Prisms fitted by an orthoptist or covering one eye may restore single vision for driving in some cases, but your eye specialist should confirm what applies to you and your local rules before you get behind the wheel.
References
- Graves' Disease – National Institute of Diabetes and Digestive and Kidney Diseases (NIH)
- Thyroid Eye Disease (TED) – Cleveland Clinic
- Overactive thyroid (hyperthyroidism) – Complications – NHS
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

After Pheochromocytoma Surgery: Intensive Care Monitoring, Early Walking and Going Home
After pheochromocytoma surgery, most people spend the first night in an intensive care or high-dependency unit so nurses can track blood pressure, heart rhythm…

Traveling With Adrenal Insufficiency: Emergency Information, Time Zones and Care Abroad
Traveling with adrenal insufficiency is usually possible with planning. The core steps are: carry replacement steroid medicine and an emergency injection kit in hand…

Graves Disease Symptoms to Report Promptly: Palpitations, Breathlessness, Fever and Eye Pain
With Graves disease, call your doctor the same day for an irregular or persistent racing heartbeat, new breathlessness or ankle swelling, eye pain, double…
TSI or TRAb Test: What Is the Difference, and When Is Each Thyroid Antibody Test Ordered?
TRAb and TSI tests both look for antibodies that attack the thyroid's TSH receptor, the immune fault behind Graves' disease. A TRAb test detects…
Parathyroidectomy Step by Step: How Surgeons Find and Remove an Overactive Gland
A parathyroidectomy is an operation to remove one or more overactive parathyroid glands in the neck, most often to treat primary hyperparathyroidism. Surgeons locate…

Calcium, Vitamin D and Blood Thinners: What Is Reviewed Before Hyperparathyroidism Surgery
Before parathyroid surgery, the care team reviews calcium and vitamin D supplements, blood thinners (anticoagulants and antiplatelets), and any medicine that can shift blood…