

Why a Blood Lipid Check Often Comes Before Xanthelasma Surgery and What It Can Reveal

Key Takeaways
- Xanthelasma plaques are made of cholesterol-filled immune cells, the same foam cells found in the fatty streaks of artery walls.
- Roughly half of people with xanthelasma have lipid results in the normal range, so the plaque is a prompt for testing, not proof of high cholesterol.
- In the Copenhagen City Heart Study, xanthelasma predicted heart attack and cardiovascular death independently of cholesterol levels, while the corneal ring called arcus did not.
- Familial hypercholesterolemia affects about one in 250 people and often goes undiagnosed; xanthelasma in a younger adult is one of its classic external clues.
- Lowering blood cholesterol rarely shrinks established plaques, but it reduces the chance of new ones appearing after removal.
- Every removal technique treats only the visible deposit, and recurrence is documented after all of them, which is why lipid assessment comes first.
A blood lipid check usually comes before xanthelasma surgery because the yellowish eyelid plaques are deposits of cholesterol, and clinicians want to know whether they signal a treatable lipid disorder or raised cardiovascular risk. The test can reveal high LDL cholesterol, high triglycerides, an inherited condition such as familial hypercholesterolemia, or secondary causes like an underactive thyroid. Results guide overall care, not just the removal decision.
The mirror is where most people meet their xanthelasma. A faint, buttery-yellow patch near the inner corner of one upper eyelid, easy to mistake for a smudge of concealer until it refuses to wipe off. Months pass. A second patch appears on the other side, as if the two are keeping each other company. Eventually someone books a consultation hoping to hear one sentence: yes, we can take these off.
What they often hear first is different. Before any talk of scalpels or lasers, the clinician asks whether a xanthelasma cholesterol test has been done recently, and if not, arranges one. For a person who arrived thinking about appearance, being sent for a blood draw can feel like a detour.
It is not a detour. Those small plaques are made of the same fatty material that lines arteries, and the blood test is the quickest way to find out whether the eyelid is telling a larger story about the rest of the body.
What is xanthelasma, and why does it point straight to cholesterol?
Xanthelasma palpebrarum, usually shortened to xanthelasma, is a soft, flat or slightly raised yellow plaque that forms in the skin of the eyelids, most often near the nose. The name comes from the Greek for yellow and plate, and the color is not a coincidence. Under the microscope these patches are crowded with foam cells: immune cells called macrophages that have swallowed so much cholesterol that they look bubbly and pale. The same cell type sits inside the fatty streaks of an artery wall.
Why the eyelid? Skin there is among the thinnest on the body, and it moves thousands of times a day with every blink. That combination of thin tissue and constant micro-movement seems to make it a convenient place for lipid-laden cells to gather and stay put. Once formed, the plaques do not hurt, itch or threaten sight, though large ones can weigh on the lid or catch on eyeglass frames.
According to Cleveland Clinic, xanthelasma is the most common form of xanthoma, the broader family of cholesterol deposits that can also appear on tendons, elbows and knees. It shows up most often in middle adulthood and somewhat more frequently in women. Because it is painless and grows slowly, many people live with it for years before mentioning it to anyone.
The key point for anyone weighing removal is this: the plaque is a symptom of how the body is handling fats, not a disease of the eyelid itself. Cutting it away removes the visible deposit. It does nothing to the process that produced it. That is why the very first question in most clinics is not which technique to use, but what the blood shows.
Why do doctors order a xanthelasma cholesterol test before removal?
Three reasons sit behind the request, and none of them is red tape.
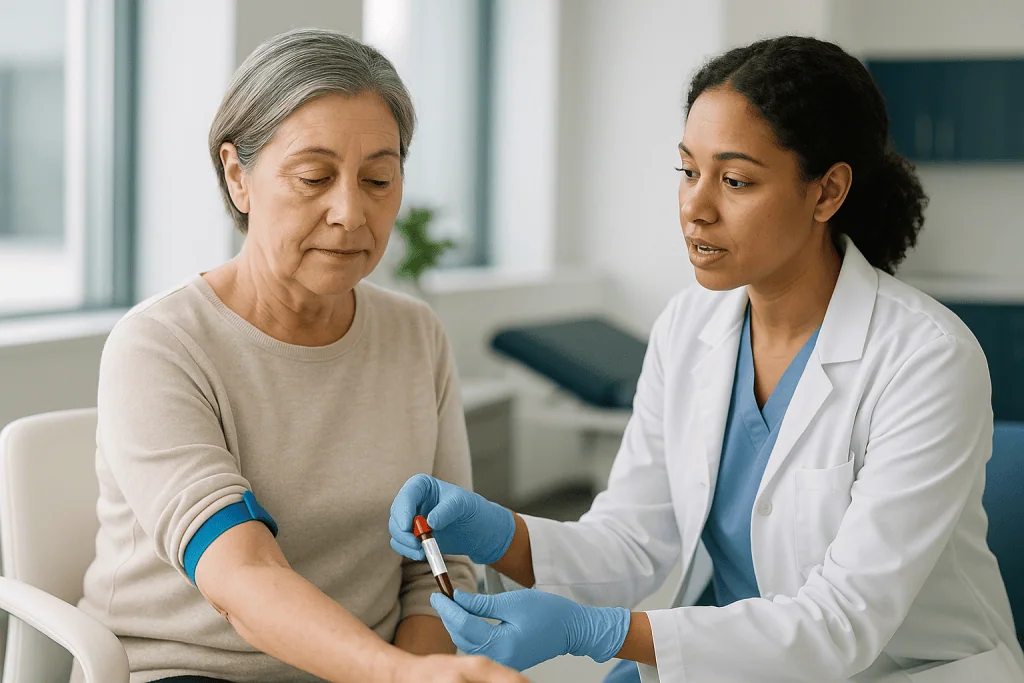
The first is screening. A person who has never had a lipid panel, or whose last one was years ago, has walked into the clinic carrying a visible clue that their fat metabolism deserves a look. The American Heart Association advises that healthy adults have cholesterol checked every four to six years, more often if risk factors are present, and a new xanthelasma is a sensible prompt to check whether that schedule has slipped.
The second is planning. If the lipid panel reveals a marked abnormality, the treating team may want to understand and begin addressing it before removing the plaques. A deposit removed while the underlying lipid picture is unchanged is more likely to be joined by new ones. Knowing the numbers helps the surgeon set realistic expectations and helps the patient decide whether now is the right moment.
The third is safety in the broadest sense. Xanthelasma has been linked in population studies to higher rates of heart attack and cardiovascular death, a finding discussed in detail below. A clinician who removes the plaques without checking lipids would be treating the cosmetic issue while walking past a potential warning sign. Most feel that would be poor medicine.
There is a practical angle too. The xanthelasma cholesterol test is inexpensive in effort: a single blood draw, results within days, and a report the surgeon, primary care physician and patient can all read. Compared with the small procedure that follows, it is the easiest step in the whole pathway, and arguably the most informative.
What does a lipid panel actually measure, and how does the test work?
A lipid panel, sometimes called a lipid profile, is a set of measurements taken from one tube of blood. MedlinePlus lists its standard components: total cholesterol; LDL cholesterol, the low-density lipoprotein often labeled harmful because it delivers cholesterol into artery walls; HDL cholesterol, the high-density lipoprotein that carries cholesterol back to the liver; and triglycerides, the main form in which the body stores dietary fat. Some laboratories add non-HDL cholesterol, which is simply total minus HDL, and a few add lipoprotein(a) or apolipoprotein B when an inherited disorder is suspected.
Fasting used to be routine. MedlinePlus notes that some clinicians still ask for nine to twelve hours without food or drink other than water, mainly to give an accurate triglyceride reading, since a recent meal can push that number up temporarily. Many panels are now done without fasting, and the ordering clinician will say which applies.
The mechanics are ordinary. A phlebotomist draws blood from a vein in the arm, the sample goes to a laboratory, and the results usually return within a few days. Nothing about the test is specific to xanthelasma; it is the same panel used in routine heart-health screening.
Interpreting the results is where expertise matters. Thresholds for what counts as high depend on age, sex, blood pressure, smoking status, diabetes and family history, and guideline bodies fold these into a ten-year cardiovascular risk estimate rather than judging any single number in isolation. Mayo Clinic explains that a value considered acceptable for one person may prompt treatment discussions for another with more risk factors. The lipid panel gives the raw data; the conversation with the doctor turns it into a plan.
Does xanthelasma always mean high cholesterol? The normal-cholesterol puzzle
Here is the fact that surprises most patients: a substantial share of people with xanthelasma have lipid results in the expected range. Cleveland Clinic puts the figure at roughly half. The plaques are strongly associated with raised cholesterol, but they are not a guarantee of it.

Several explanations are plausible. Lipids fluctuate over years, and a person whose levels were high in their thirties may have improved through weight change, diet or medication by the time the plaques become visible. Local factors in the eyelid skin, such as the way lipoproteins leak through thin capillary walls and are trapped by immune cells, may matter as much as the concentration in the bloodstream. Some studies have also found altered lipoprotein composition or function in normolipidemic patients even when the standard numbers look fine.
The Copenhagen City Heart Study, published in the BMJ and indexed on PubMed, added a striking twist. Following more than 12,000 adults, the researchers found that xanthelasma predicted heart attack, ischemic heart disease and death even after adjusting for cholesterol levels and other conventional risk factors. In other words, the plaque carried information that the lipid panel alone did not capture.
What should a person with xanthelasma and a normal panel take from this? Not alarm, but attention. A normal result is genuinely good news about one measurable risk factor. It does not erase the association seen in population data, so most clinicians treat it as a reason to keep an eye on the wider picture: blood pressure, blood sugar, smoking, family history and weight. The eyelid has raised a question; the blood test answers part of it. The rest is a longer conversation.
What can the xanthelasma cholesterol test reveal beyond LDL?
Most people picture a single number when they hear cholesterol test. The panel is richer than that, and each component can open a different door.
Very high LDL, particularly in someone young or with a relative who had early heart disease, raises the possibility of familial hypercholesterolemia, an inherited condition in which the liver cannot clear LDL efficiently. MedlinePlus describes it as affecting roughly one in 250 people, many of whom do not know they have it. Xanthelasma, tendon xanthomas and a grayish ring at the edge of the cornea called arcus are classic external clues. Identifying the condition matters far beyond the eyelid, because it changes lifelong risk and prompts testing of siblings and children.
High triglycerides tell a different story. They tend to accompany insulin resistance, type 2 diabetes, excess alcohol intake, certain medications and some kidney and liver conditions. A clinician who sees markedly raised triglycerides will often add a blood glucose or HbA1c test, liver enzymes and kidney function to the work-up.
Low HDL is less a diagnosis than a marker, but it strengthens the overall risk estimate and can reflect smoking, inactivity or metabolic syndrome.
The panel can also point toward secondary causes of high cholesterol that have nothing to do with genetics or diet. An underactive thyroid slows LDL clearance and is a well-recognized culprit; the NHS lists hypothyroidism alongside kidney disease, liver disease and some medicines among conditions that push cholesterol up. A thyroid test is a common add-on when lipids come back unexpectedly high.
None of these findings is a verdict. Each is a lead the treating team may follow, and the xanthelasma has done its job by prompting the search.
Xanthelasma and heart disease risk: what the evidence really shows
The strongest data on this question come from the Copenhagen City Heart Study, a prospective cohort published in the BMJ. Researchers examined 12,745 adults for xanthelasma and arcus, then followed them for decades. About 4 percent had xanthelasma at the start. Over the follow-up period, those individuals had roughly 1.5 times the risk of heart attack compared with those without the plaques, along with higher rates of ischemic heart disease, severe atherosclerosis and death from any cause. The associations held after adjusting for cholesterol, blood pressure, smoking, diabetes and body weight.
Two details deserve emphasis. First, the elevated risk was independent of lipid levels, which is why the finding is described as adding information rather than merely reflecting high cholesterol. Second, arcus, the corneal ring often mentioned in the same breath, did not independently predict events once other factors were considered. The eyelid plaque was the informative sign; the corneal ring was not.
How should this be read? As association, not destiny. The absolute risk increase in the study varied widely with age and sex and was highest in older men. Most people with xanthelasma will not have a heart attack because of it. What the data support is a modest but real upward adjustment in estimated risk, and a stronger argument for the routine assessment that guideline bodies recommend anyway: lipid panel, blood pressure, glucose, smoking review, and a frank look at family history.
A single cohort study, however large, is one piece of evidence. Smaller studies have produced mixed results, some confirming the link and others finding it weaker after adjustment. The honest summary is that xanthelasma is a credible external marker of cardiovascular risk, and that its appearance justifies a check-up rather than a crisis.
Who is usually offered xanthelasma removal, and who is asked to wait?
Removal is elective in almost every case. The plaques do not damage the eye, and there is no medical urgency. That gives the treating team room to sequence things sensibly, and a few patterns are common.
People typically offered removal in a straightforward way are those whose lipid panel has been reviewed and either falls within target or is already being managed, whose plaques are stable in size, and whose expectations are realistic about scarring and the chance of recurrence. Lesions that interfere with eyeglasses, cause the lid to droop or repeatedly get irritated strengthen the functional case.
People who are often asked to wait include those with a newly discovered and significant lipid abnormality that has not yet been addressed. The logic is simple: the internal environment that made the plaques is still active, so new deposits are more likely soon after surgery. Some clinicians prefer to see the lipid picture settled first. Others proceed with removal in parallel with lipid management, reasoning that the cosmetic and cardiovascular problems can be handled at the same time. Both approaches are defensible; the choice rests with the treating team and the patient.
Other reasons for delay are the usual ones for any small eyelid procedure: active skin infection near the site, uncontrolled diabetes that may slow healing, blood-thinning medication that needs a plan, or a plaque whose appearance is unusual enough that a biopsy should come first. Pregnancy is another common reason to postpone purely cosmetic work.
A person who is asked to wait has not been refused. In most cases they have been offered something more useful in the short term: a clear picture of their lipids and a plan for them, with the eyelid procedure to follow once the ground is prepared.
How is xanthelasma removed? Techniques compared
Several methods exist, and the right one depends on the size, depth and position of the plaques, the surgeon’s experience, and the patient’s skin type and priorities. Cleveland Clinic lists the main options; the table below summarizes them in neutral terms.
| Method | What happens | Commonly cited considerations |
|---|---|---|
| Surgical excision | The plaque is cut out under local anesthetic and the skin closed with fine stitches | Complete removal in one session; leaves a fine scar; larger plaques may need staged surgery or skin adjustment |
| Laser ablation (carbon dioxide or erbium) | Focused light vaporizes the lipid-laden tissue layer by layer | Good control of depth; possible temporary redness or pigment change, especially in darker skin |
| Chemical peeling (trichloroacetic acid) | An acid solution applied by the clinician destroys the superficial plaque | Suits flat, superficial lesions; often needs repeat sessions; risk of pigment change or scarring if too deep |
| Cryotherapy | Controlled freezing destroys the tissue | Less commonly used on eyelids because of pigment and swelling risk |
| Radiofrequency or electrodesiccation | Heat energy destroys the plaque | Precise for small lesions; depth control depends heavily on operator skill |
No single method is superior for everyone, and the evidence comparing them consists mostly of small case series rather than large randomized trials. All share two truths: they treat the visible deposit only, and recurrence is possible whichever technique is chosen. Cleveland Clinic notes that plaques can return after removal, particularly if lipid levels remain high.
The eyelid is unforgiving territory. The skin is thin, the margin is close, and any technique that goes too deep risks pulling the lid outward, a complication called ectropion. This is why the procedure is usually performed by a dermatologist, oculoplastic surgeon or plastic surgeon familiar with the anatomy, and why the discussion of technique should include an honest account of scarring and pigment risk for the individual patient.
Will xanthelasma go away if I lower my cholesterol?
This is the question almost everyone asks, and the honest answer is: usually not on its own.
Cholesterol that has been packed into foam cells in the eyelid behaves differently from cholesterol circulating in the blood. Lowering blood levels reduces the supply of new lipid to the area and appears to slow the growth of existing plaques and the appearance of new ones. It rarely reverses established deposits to any noticeable degree. Cleveland Clinic states plainly that xanthelasma does not go away by itself and that treatment of the underlying lipid problem is aimed at preventing recurrence and protecting the heart, not at dissolving what is already there.
There are scattered case reports of partial regression after aggressive lipid lowering, particularly in people with very high starting levels or in the context of treating an underlying cause such as hypothyroidism. These are exceptions, and they involve small numbers of patients. Nobody should be told to expect their plaques to fade because their LDL has improved.
Why does this matter for the surgical decision? Because it separates two goals that are easy to blur. Goal one is cardiovascular health, which the lipid panel and any resulting management address. Goal two is appearance, which only physical removal addresses. Doing the first does not accomplish the second, and doing the second does not accomplish the first. A person who takes their lipid results seriously and also chooses removal is not being inconsistent; they are answering both questions.
What good lipid control does offer the surgical patient is a better chance that the result lasts. The plaques came from somewhere, and a body that is no longer flooding its tissues with excess LDL is a less hospitable place for them to return.
What medicine can dissolve xanthelasma? Separating lipid drugs from plaque removal
No medicine dissolves xanthelasma. Searches for one turn up a mixture of lipid-lowering drugs, which act on the blood, and topical acids or creams, which act on the skin. It helps to keep the two categories apart.
Lipid-lowering medicines work inside the body. Statins reduce the liver’s production of cholesterol and increase its removal of LDL from the blood. Ezetimibe blocks absorption of cholesterol from the gut. Newer injectable agents that target a protein called PCSK9 help the liver keep more LDL receptors active. Fibrates and prescription omega-3 preparations mainly lower triglycerides. The NHS describes these classes and notes that a doctor chooses among them based on the lipid pattern, other conditions and overall risk. Each is prescribed to protect arteries over years, not to clear eyelid plaques over weeks, and none has been shown to reliably remove established xanthelasma.
Topical treatments applied by a clinician, chiefly trichloroacetic acid, destroy the plaque by chemically injuring the tissue. That is a controlled procedure done in a clinic with careful attention to depth and eye protection, not a medicine in the everyday sense, and certainly not something to attempt at home. Products marketed online as xanthelasma creams range from mild exfoliants that do nothing to caustic preparations that can scar the eyelid or injure the eye. There is no good evidence that any over-the-counter cream removes these plaques.
If a lipid panel reveals a problem, the prescribing clinician will discuss whether medication is appropriate and, if so, which class fits. That decision belongs with them and depends on far more than the eyelid. The plaques themselves, if they are to go, will need a physical method chosen by the treating team.
Xanthelasma removal recovery: what the days and weeks afterward usually look like
Because the procedure is small and done under local anesthetic, recovery is generally measured in days rather than weeks, though the eyelid’s tendency to swell and bruise can make the first few days look more dramatic than they feel.
After surgical excision, expect a small dressing or none at all, some tightness when blinking, and bruising that spreads into the surrounding lid before fading. Fine stitches are typically removed at a follow-up visit within the first week or so, though the exact timing is set by the surgeon. Cold compresses, keeping the head elevated when resting, and avoiding rubbing the area are the usual instructions. Makeup and contact lenses are generally held off until the wound has sealed.
After laser or chemical treatment there is no wound to stitch, but the treated area forms a crust that lifts off gradually. The skin underneath is pink and may stay so for several weeks. Sun protection matters during this phase because healing skin is prone to darkening, a concern Cleveland Clinic flags as a possible side effect, particularly in people with more melanin.
Scars mature slowly. What looks like a distinct line at two weeks generally softens over months as collagen remodels. Most surgeons ask patients to judge the final appearance no sooner than several months out.
Recurrence, when it happens, tends to show over months to years rather than days, which is another reason the lipid panel matters: a person whose cholesterol has been assessed and managed heads into that period with one fewer factor working against them. A repeat lipid check on whatever schedule the primary care physician sets closes the loop between the eyelid and the bloodstream.
What can mimic xanthelasma? Conditions clinicians rule out first
A yellow patch on the eyelid is not always xanthelasma, and part of the pre-surgical assessment is making sure the diagnosis is right before anything is removed. This is a job for a clinician with a good light and, when needed, a biopsy, not for a mirror at home. Still, it helps patients to know what else is on the list.
Syringomas are small, firm, skin-colored or faintly yellow bumps that arise from sweat gland ducts and cluster on the lower lids. Milia are tiny white cysts of trapped keratin. Sebaceous hyperplasia produces yellowish dome-shaped bumps with a central dimple, usually on the face rather than the lid margin. Each of these is benign, but the treatment differs from xanthelasma and none is linked to cholesterol.
More important are the mimics that are not benign. Basal cell carcinoma, the most common skin cancer, can present on the eyelid as a pearly or waxy nodule that may be mistaken for a lipid deposit, especially early on. Sebaceous carcinoma, a rare eyelid cancer, can masquerade as a persistent chalazion or a yellowish thickening. Necrobiotic xanthogranuloma, an uncommon condition that produces yellow plaques around the eyes, is associated with blood protein disorders and warrants a very different work-up.
A clinician will weigh the texture, symmetry, color and history of the lesion. Xanthelasma is typically soft, flat, symmetric and slow-growing. Features that prompt a biopsy include a single lesion that is firm, ulcerated, bleeding, growing quickly or pulling the lashes out of line. Cleveland Clinic advises that any new eyelid growth be evaluated rather than assumed to be harmless.
The lipid panel and the diagnostic examination therefore run side by side. One confirms what the plaque is; the other asks what it means.
What people often get wrong about cholesterol bumps on eyelids
Xanthelasma attracts a remarkable amount of folklore. A few corrections, each grounded in the sources cited in this article.
Myth: if my cholesterol is normal, the bumps are meaningless. A normal panel is reassuring about one risk factor. The Copenhagen cohort found that xanthelasma predicted cardiovascular events independently of lipid levels, so the plaque still earns a broader risk review.
Myth: removing the plaques lowers heart risk. Removal changes appearance only. The deposit is a marker, not a cause, and excising it leaves arteries exactly as they were.
Myth: eating less cholesterol will make them disappear. Diet influences blood lipids, but established plaques rarely regress. Cleveland Clinic is clear that xanthelasma does not go away on its own.
Myth: they are just a sign of aging. They are more common in middle age, but age is not the mechanism. Foam cells full of cholesterol are, and that process can occur at any age, notably early in people with inherited lipid disorders.
Myth: home acid kits work as well as clinic treatment. The eyelid sits millimeters from the eye. Unsupervised caustic products risk scarring, pigment loss, eyelid distortion and corneal injury, with no reliable evidence of benefit.
Myth: once removed, they are gone for good. Recurrence is well documented after every technique. Managing lipids improves the odds but does not guarantee a permanent result.
Myth: only people with heart disease get them. Many people with xanthelasma have no cardiac history at all. The plaques are common, the population is broad, and the point of the blood test is precisely to sort out who among that broad population needs closer follow-up.
Questions to ask your care team before xanthelasma surgery
Consultations move fast, and the questions that matter most are easy to forget once the conversation turns to technique. A short list, written down beforehand, tends to serve patients well.
- What did my lipid panel show, and how does it fit with my other cardiovascular risk factors such as blood pressure, blood sugar, smoking and family history?
- Does anything in my results suggest an inherited lipid disorder, and should my close relatives be tested?
- Do you recommend addressing my lipids before removal, at the same time, or does the order not matter in my case?
- Are you confident these are xanthelasma, or is a biopsy worth considering first?
- Which removal method do you suggest for my plaques and skin type, and why that one over the alternatives?
- What will the scar look like, how might my skin pigment respond, and what is the risk of the eyelid being pulled out of position?
- How likely is recurrence for someone with my lipid picture, and what would we do if it happened?
- What does recovery involve day by day, when can I drive, work, wear makeup and use contact lenses, and when is the follow-up visit?
- If my lipids need managing, who will oversee that, and how will the two parts of my care talk to each other?
- What would make you advise against surgery for me right now?
The last question is the one most people skip and the one most surgeons respect. A clinician who can explain why they might say no is one who is weighing the whole picture rather than just the plaque. Every answer belongs to the treating team, and every decision that follows, including whether to proceed at all, sits with them and with the patient together.
When to call your doctor
Xanthelasma itself is rarely an emergency, but two situations deserve prompt attention: changes in the eyelid lesion that suggest it may not be xanthelasma, and problems after a removal procedure.
Before any treatment, contact a clinician without waiting for a routine appointment if an eyelid growth is bleeding, ulcerated, crusting repeatedly, growing quickly, firm rather than soft, present on one side only with an irregular edge, or pulling the lashes out of alignment. These features are not typical of xanthelasma and are among the signs Cleveland Clinic and other sources list as reasons for a new eyelid lesion to be examined.
After removal, call the surgical team the same day if you notice spreading redness, increasing rather than easing pain, pus or a foul smell from the wound, a wound edge that has opened, fever, or bleeding that does not stop with gentle pressure. Seek urgent care immediately for any change in vision, severe eye pain, a sensation of something in the eye that will not clear, or an eyelid that will not close fully, since the surface of the eye depends on the lid for protection.
Separately, if a lipid panel done as part of this work-up has revealed very high results, and you develop chest pain or pressure, breathlessness on exertion, pain spreading to the arm or jaw, sudden weakness or facial drooping, or difficulty speaking, treat those as an emergency and call emergency services. The American Heart Association describes these as warning signs of heart attack or stroke that should never be waited out.
For everything less dramatic, the right path is a message or call to the treating team. They know the plan, they know the lipid results, and they can judge quickly what needs a look.
Frequently asked questions
Will xanthelasma go away if I lower my cholesterol?
Usually not. Established plaques are cholesterol trapped inside skin immune cells, and lowering blood levels rarely reverses them to a visible degree. Cleveland Clinic states that xanthelasma does not resolve on its own. Better lipid control does help prevent new deposits and protects the heart, so it remains worthwhile; it simply does not substitute for physical removal if appearance is the goal.
Does xanthelasma always mean high cholesterol?
No. Around half of people with xanthelasma have lipid panels in the expected range, according to Cleveland Clinic. The plaques are strongly associated with raised cholesterol but not caused exclusively by it. Population data suggest they carry some cardiovascular risk information even when lipids are normal, which is why clinicians still recommend a broader risk review rather than dismissing a normal result.
What can mimic xanthelasma on the eyelid?
Benign mimics include syringomas, milia and sebaceous hyperplasia. More serious look-alikes include basal cell carcinoma, sebaceous carcinoma and necrobiotic xanthogranuloma. A clinician distinguishes them by texture, symmetry, growth pattern and, when needed, biopsy. Any eyelid growth that is firm, ulcerated, bleeding or enlarging quickly should be examined rather than assumed to be a cholesterol deposit.
Does insurance cover xanthelasma removal?
It depends on the insurer and the reason for removal. Removal purely for appearance is commonly classed as cosmetic and may not be covered, while removal for functional problems such as a plaque that interferes with vision, eyelid closure or eyeglass fit may be assessed differently. Coverage rules vary widely; the clinic’s administrative team and the insurer can clarify before any procedure is scheduled.
What medicine can dissolve xanthelasma?
None reliably does. Statins, ezetimibe and other lipid-lowering drugs act on blood cholesterol to protect arteries; they are not designed to clear eyelid plaques and rarely do. Clinic-applied trichloroacetic acid destroys plaque tissue chemically, but that is a supervised procedure, not a medicine. Over-the-counter creams lack good evidence and caustic home kits can injure the eye or scar the lid.
Do I need to fast before a xanthelasma cholesterol test?
Sometimes. MedlinePlus notes that some clinicians ask for nine to twelve hours without food, mainly to obtain an accurate triglyceride reading. Many lipid panels are now done without fasting, and the ordering clinician will specify which applies. The test itself is a standard blood draw from the arm, identical to routine cholesterol screening, with results typically returned within a few days.
Is xanthelasma with high cholesterol a sign of heart disease?
It is a marker of increased risk, not a diagnosis. The Copenhagen City Heart Study found roughly 1.5 times the risk of heart attack in people with xanthelasma, independent of lipid levels. Most people with the plaques will not have a heart attack because of them, but the finding justifies a full cardiovascular risk assessment covering blood pressure, glucose, smoking and family history.
How long does xanthelasma removal recovery take?
Recovery is typically measured in days. After excision, bruising and swelling settle over the first week or so, and stitches are removed at a follow-up visit set by the surgeon. After laser or chemical treatment, a crust lifts gradually and pinkness can persist for several weeks. Scars soften over months, and surgeons usually ask patients to judge the final appearance no sooner than that.
Can xanthelasma come back after removal?
Yes. Recurrence is documented after every technique, including surgical excision, laser and chemical peels, because removal addresses only the visible deposit and not the lipid process behind it. Cleveland Clinic notes that plaques are more likely to return if cholesterol remains high. Managing lipids and other risk factors improves the odds of a lasting result but does not guarantee one.
Should my family be tested if I have xanthelasma and high cholesterol?
Possibly, and it is worth asking. Very high LDL combined with xanthelasma, especially in a younger adult or someone with a relative who had early heart disease, can indicate familial hypercholesterolemia, an inherited condition affecting about one in 250 people according to MedlinePlus. Because it runs in families and is often undiagnosed, clinicians commonly recommend testing first-degree relatives when it is identified.
References
- Cleveland Clinic: Xanthelasma
- MedlinePlus: Cholesterol Levels (Lipid Panel)
- MedlinePlus Medical Encyclopedia: Familial hypercholesterolemia
- PubMed: Xanthelasmata, arcus corneae, and ischaemic vascular disease and death in general population (BMJ, Copenhagen City Heart Study)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Filler Migration: Why It Happens, How It Is Diagnosed and How Filler Is Dissolved
Filler migration is when injected dermal filler drifts away from the spot where it was placed, most often appearing as a soft ridge above…
Staged Excision for Larger Tattoos: How Surgeons Remove Tattooed Skin in Steps
Staged tattoo excision is a surgical approach in which a larger tattoo is cut out in two or more planned operations, spaced weeks to…

Chemical Peel Side Effects: Normal Tightness vs the Redness or Crusting You Report
After a chemical peel, tightness, mild stinging, pinkness and fine flaking for a few days are expected while the skin sheds and rebuilds. Redness…

Recovery After Microsurgery: Circulation Checks, Splints and How Sensation Returns Slowly
Microsurgery recovery unfolds in stages. For the first few days, nurses check the repaired tissue's color, warmth and blood flow around the clock because…

Brow Lift vs Blepharoplasty: Which One Addresses Heavy Upper Eyes?
An upper blepharoplasty removes excess eyelid skin and is usually appropriate when the heaviness comes from the lid itself, while a brow lift repositions…

Mesotherapy vs Microneedling for Skin Rejuvenation: How the Two Approaches Differ
Mesotherapy and microneedling both use fine needles, but they do different jobs. Microneedling creates controlled micro-injuries so the skin builds new collagen on its…