

Why Do Some Chickenpox Spots Leave Scars and How Is Early Healing Supported?

Key Takeaways
- A typical case of chickenpox produces 250 to 500 blisters, yet most people are left with only one or two true pitted scars, almost always at spots that were scratched open or became infected.
- The blister sits at the junction of the epidermis and dermis; a scar forms only when damage reaches the dermis, which is why undisturbed crusts that fall off on their own rarely leave marks.
- Red and brown marks visible when crusts come off are healing skin and pigment change, not scars, and NHS guidance puts their fading at weeks to months rather than years.
- Scars keep remodeling for up to two years, so any judgment about permanence or treatment made before six months is likely to overestimate the final result.
- Sun exposure on freshly healed skin darkens and prolongs pigment marks, making shade and sun protection the most reliable everyday tool for fading dark spots after chickenpox.
- Two doses of varicella vaccine are more than 90 percent effective at preventing chickenpox according to the CDC, and vaccinated people who still catch it usually have far fewer and milder spots.
Most chickenpox spots heal without a mark. Scars form when a blister damages deeper skin, usually because it was scratched open, infected, or healed with extra inflammation. Early healing is supported by controlling itch, keeping nails short and skin clean, leaving scabs to fall off on their own, and protecting new pink skin from sun; scar treatments are considered only after full healing.
Ten days into her son’s chickenpox, a mother stands in the doorway of his bedroom at 2 a.m. He is asleep at last, one hand curled against his cheek, and under that hand is the spot he could not leave alone. By morning it will have bled again. She already knows which one of the two hundred she will still be able to find on his face when he starts school.
That is the strange arithmetic of chickenpox scars. A child can carry hundreds of blisters and walk away with skin that looks untouched, or carry a single pale pit on the temple for life. The difference is rarely luck alone. It comes down to how deep each blister went, what happened to it while it healed, and how the skin around it responded.
This explainer follows the story of one spot from red bump to fading mark, and looks honestly at what the evidence says about preventing scars, what fades on its own, and what treatment can and cannot do.
What actually happens in the skin when a chickenpox spot heals
Chickenpox is caused by the varicella-zoster virus, which travels through the bloodstream and settles in the skin. Each spot begins as a small red bump, rises within hours into a clear, fluid-filled blister that Mayo Clinic describes as looking like a dewdrop on a rose petal, and then clouds, bursts and crusts over. The CDC notes that it typically takes four to seven days for all the blisters to become scabs, and a typical case produces somewhere between 250 and 500 of them.
The blister itself sits high in the skin, at the border between the epidermis (the thin outer layer that constantly renews itself) and the dermis (the thicker living layer underneath that holds collagen, blood vessels and hair follicles). This location matters enormously. Skin that loses only its epidermis grows back from the edges and from the base with no visible change, the same way a shallow graze disappears. Skin that loses part of its dermis cannot regrow that tissue exactly; it fills the gap with a patch of repair collagen laid down in bundles rather than the original basket-weave, and that patch is what we call a scar.
Beneath the crust, the body is running a repair program in three overlapping phases: inflammation to clear debris and virus, proliferation to build new cells and collagen, and remodeling, in which the new collagen is slowly reorganized and thinned. The first two phases take days to a couple of weeks. The third, according to the NHS, continues for many months and can keep changing a scar’s color and texture for up to two years. Early healing is about protecting the first two phases so that the third has less to correct.
Why do some chickenpox spots leave scars and others don't?
Picture two blisters side by side on the same arm. One is left alone, dries into a crust, and the crust lifts off by itself when the new skin below is ready. The other is scratched. The roof of the blister tears, the raw base is exposed, bacteria from under the fingernail move in, and the wound now has to heal an injury that reaches well below the level the virus ever damaged. The second one scars. The first almost never does.
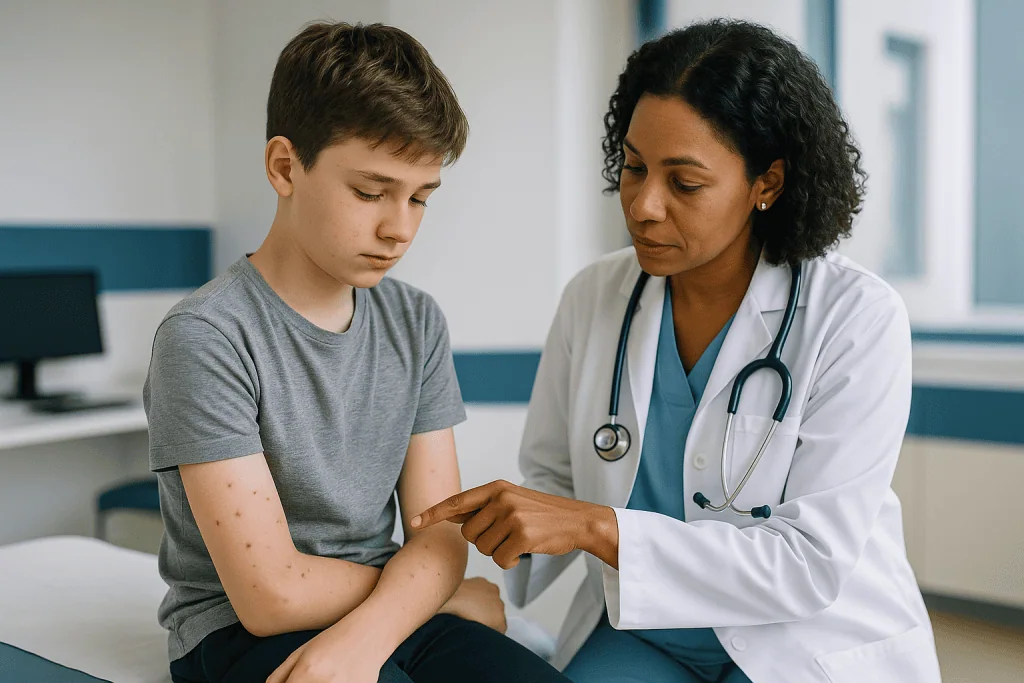
Scratching is the single most important variable, but it is not the only one. Several factors push a spot toward a lasting mark:
- Depth of the original blister. A minority of chickenpox lesions are larger and deeper than the rest, especially in older children, teenagers and adults, whose illness tends to be more severe according to the CDC. Deeper blisters carry a higher scar risk even without scratching.
- Secondary bacterial infection. Skin bacteria entering an open blister cause a deeper, more prolonged inflammation. The NHS and CDC both list bacterial skin infection as one of the most common complications of chickenpox, and infected spots are the ones that most often leave pits.
- Premature crust removal. A scab that is picked off before the skin underneath has closed leaves a fresh wound that has to start over.
- Location. Skin on the face, chest and shoulders is more prone to visible scarring and to pigment change than skin on the limbs.
- Individual skin biology. Some people form thicker scar tissue than others, and people with more melanin in their skin are more likely to develop dark marks where a spot has been.
None of these is a moral failing on the part of a child who scratched. Itch is a neurological signal, and children under five have very little capacity to override it. The realistic goal is to reduce the number of spots that are scratched open or infected, not to achieve zero.
Pitted, raised, dark or pale: the different kinds of chickenpox scars
The phrase “chickenpox scar” covers several different changes in the skin, and they behave differently over time. Sorting out which kind you are looking at is the first step in understanding whether it is likely to fade and what, if anything, might help.
Atrophic (pitted) scars are the classic chickenpox mark: small round or oval depressions, often a few millimeters across, with soft or sharply defined edges. They form when dermal collagen and fat are lost and the surface sinks to fill the gap. These are true scars. Their edges soften and their color normalizes with time, but the depression itself does not fill in on its own.
Hypertrophic scars are raised, firm and sometimes pink or red. They stay within the borders of the original spot and, as the Cleveland Clinic explains, often flatten and fade over one to two years. Keloids, which grow beyond the original wound edge, are uncommon after chickenpox but can occur in people who are prone to them, particularly on the chest, shoulders and earlobes.
Post-inflammatory hyperpigmentation is a flat brown or gray mark, not a scar at all in the structural sense. Inflammation stimulates pigment cells to release extra melanin, which is deposited in the skin as the spot heals. It is more common and more persistent in darker skin tones.
Post-inflammatory hypopigmentation is the opposite: a flat pale patch where pigment cells were disrupted. It tends to be more noticeable in darker skin and after tanning, because the surrounding skin darkens while the patch does not.
Most children end up with a mix: a great many flat marks that fade, and a small number, often just one or two, of true pits. Only the pits need to be thought of as permanent, and even those change character as a child grows.
How long do chickenpox scars take to fade, and what do the following weeks look like?
The timeline runs in stages, and knowing the stages spares a lot of unnecessary worry in the first month, when the skin looks its worst.

Days 1 to 7. New spots keep appearing in waves. The Mayo Clinic notes that bumps, blisters and crusts are usually present at the same time. This is the window in which itch control and infection prevention matter most.
Days 5 to 10. Crusts form. The NHS advises that a person stops being infectious once every spot has crusted over, which typically happens around five days after the rash begins.
Weeks 2 to 3. Crusts lift away by themselves, revealing shiny pink or red new skin. According to the NHS, the spots usually take a week or two to fade after they have scabbed. The redness at this point is normal healing, not scarring, and it looks alarming precisely because it is fresh.
Months 1 to 6. Red marks fade toward skin color. Brown marks in darker skin are often at their most noticeable during this period, then begin to lighten. Any true pits become visible now, once the surrounding swelling has settled.
Months 6 to 24. Scar remodeling continues. The NHS scars guidance describes scars continuing to soften and pale for up to two years. Pigment changes generally resolve within this window, though hypopigmented patches can be slow.
Two practical points follow. First, judging a scar before six months have passed almost always overestimates how it will look. Second, sun exposure during the pink and brown stages deepens and prolongs discoloration, so shade, clothing and, in children over six months, sunscreen on healed skin are genuinely protective rather than cosmetic fuss.
Supporting early healing while the spots are still active
Everything that prevents chickenpox scars happens in the first ten days, and almost all of it is low-technology care that a parent or the person who is unwell can carry out at home. The guidance below reflects what the NHS, CDC and Mayo Clinic recommend; none of it involves a prescription.
Reduce the itch, because itch drives scratching. Cool or lukewarm baths, several times a day if needed, soothe the skin. The CDC and Mayo Clinic mention adding colloidal oatmeal or baking soda to bathwater as a traditional comfort measure. Pat rather than rub the skin dry. Loose, soft cotton clothing and cool rooms help, since heat and sweat make itch worse. Over-the-counter soothing lotions and, where a clinician or pharmacist advises, antihistamine medicines are commonly used to blunt the itch signal; which one suits a particular child is a decision for that conversation, not this article.
Make scratching less damaging when it happens. Keep fingernails trimmed short and clean. Soft mittens or cotton socks over a young child’s hands at night are a long-standing NHS suggestion. Distraction works better than instruction with small children.
Keep the skin clean without stripping it. Gentle daily washing with lukewarm water and a mild, fragrance-free cleanser reduces the bacteria available to infect any blister that does break. Vigorous scrubbing removes crusts too early.
Leave scabs alone. A crust is the body’s own dressing; it protects the wound and falls off when the skin beneath is ready. Picking it, however tempting when it looks nearly loose, resets the healing clock.
Watch for infection. A spot that becomes increasingly red, hot, swollen, painful, or that leaks yellow fluid, needs a clinician’s eye. Treating an infected spot early is one of the more reliable ways to prevent a pit.
Do antiviral medicines reduce chickenpox scars?
People often ask whether medicine can shorten the illness and therefore protect the skin. The honest answer is: sometimes, for some people, and mainly by a different route than most imagine.
Antiviral medicines for chickenpox belong to a class that blocks the enzyme the virus uses to copy its own genetic material. Because the medicine only stops new virus being made rather than removing virus already present, it works best when started within the first day or so of the rash, and it shortens the illness modestly rather than dramatically. The Mayo Clinic explains that healthy children usually are not offered antivirals, since their illness is self-limiting, while people at higher risk of complications, including adults, adolescents, pregnant women, newborns and people with weakened immune systems, may be.
Where scarring is concerned, the logic is indirect. Fewer and shorter-lived blisters mean fewer opportunities for scratching and infection, and a milder illness in a teenager or adult, who would otherwise tend to have larger, deeper lesions, may translate into fewer deep marks. Trials of these medicines were designed to measure fever, new lesion formation and time to crusting, not scars, so no clinician can promise a cosmetic result from them.
Two things are worth stating plainly. Antibiotics have no effect on the virus and are used only if a bacterial skin infection develops. Aspirin should never be given to children or teenagers with chickenpox because of the risk of Reye’s syndrome, a rare but serious condition affecting the liver and brain; the CDC and NHS both carry this warning. Whether any medicine is appropriate, and when to start it, sits with the prescribing clinician who knows the person’s age, health and how far the rash has progressed.
Do chickenpox scars go away on their own?
This is the question behind most late-night searches, and the answer splits cleanly along the lines described earlier.
Flat marks, whether red, brown or pale, are not structural scars and usually do go away. The redness of fresh healing fades within weeks. Brown post-inflammatory marks can take several months, occasionally longer in deeply pigmented skin, but the pigment is sitting in a layer of skin that renews itself, and it is gradually shed and replaced. Pale patches are slower and sometimes incomplete, but they too tend to blend as pigment cells migrate back in and as the surrounding skin loses any summer tan.
True pits are different. The tissue that was lost is not regenerated, and the NHS scars guidance is candid that pitted scars are permanent, although they fade and soften. What does change is their visibility. A depression that looks obvious at three months on a bright red background can be hard to find at two years once the color has normalized. In children there is an extra effect: the skin around a scar continues to grow while the scar does not, so a pit on a toddler’s cheek often appears proportionally smaller on the same child at fifteen.
Raised scars follow a middle course. The Cleveland Clinic describes hypertrophic scars often flattening and fading over one to two years without intervention, though a minority stay raised.
Put together, the realistic expectation is this: most of what you see in the first month will disappear; the small number of pits will stay but will matter less over time; and any decision about treating those pits is best made after the skin has finished its own work, which means waiting at least six months and ideally a year.
How to fade dark spots after chickenpox
Dark marks are the most common lingering complaint after chickenpox, especially for people with medium to deep skin tones, and they are also the most responsive to sensible care. The mechanism is worth understanding because it explains what helps.
Inflammation releases chemical messengers that switch on melanocytes, the pigment-producing cells at the base of the epidermis. They produce extra melanin, which is passed to the surrounding skin cells and, in deeper inflammation, drops into the upper dermis where it is cleared much more slowly. Ultraviolet light does the same thing, which is why a healing spot that gets sun turns darker and stays darker.
Three measures have the strongest grounding in mainstream dermatology guidance:
- Sun protection from the moment the crust falls off. Shade, hats and clothing for infants; broad-spectrum sunscreen on intact, healed skin for children over six months and adults. This is the single intervention that consistently shortens the life of a dark mark.
- No picking, no scrubbing. Exfoliating a brown mark irritates it and, by adding inflammation, tends to make it darker rather than lighter.
- Time. The NHS notes that pigment changes following skin injury usually improve over months. For most people this alone is enough.
Where marks are stubborn, dermatologists sometimes use topical agents that slow melanin production or speed skin turnover. These include retinoid-class creams and other lightening agents that are available only through a clinician in many settings, partly because they can irritate skin and worsen pigmentation if misused. Some of them are not suitable during pregnancy or for young children. Any decision to use one belongs with a dermatologist or the treating team, who can also confirm that a mark is post-inflammatory pigmentation and not something else.
Who is usually offered chickenpox scar treatment, and who is asked to wait
Scar treatment is elective. Nobody needs it for their health, so the decision rests on how much a mark bothers the person carrying it, how mature the scar is, and whether the likely benefit justifies the discomfort, downtime and risk. Clinicians tend to sort people into a few broad groups.
Usually asked to wait:
- Anyone whose chickenpox healed within the last six to twelve months. The scar is still remodeling, and treating a scar that is going to improve on its own exposes the person to risk for a gain the skin may have delivered for free.
- Young children. Most procedures for pitted scars involve needles, lasers or acids, and a child cannot meaningfully consent to discomfort for a cosmetic goal. Because childhood scars often become proportionally smaller with growth, many dermatologists suggest revisiting the question in the mid to late teens.
- People whose main concern is pigment rather than texture, since pigment is likely to fade with sun protection and time.
- People with active skin infection, uncontrolled eczema or a recent tan at the treatment site.
Often considered suitable for assessment:
- Teenagers and adults with mature pitted scars, particularly on the face, that remain clearly visible after at least a year.
- People with raised scars that have not flattened over one to two years, or that itch or pull.
- Anyone for whom a scar is affecting confidence or wellbeing enough to warrant the conversation.
Extra caution applies to people with a personal or family history of keloids, those with very dark skin tones (some laser types carry a higher risk of pigment change), people taking medicines that affect healing, and anyone pregnant. None of these rule out treatment, but they shape which options are offered. The assessment itself, and the final decision, sit with the dermatologist or treating team.
Chickenpox scar treatment options compared
Treatment aims to make a pit shallower, a raised scar flatter or a discolored mark closer to the surrounding skin. No method removes a scar entirely, and the NHS is direct that treatments improve appearance rather than erase it. The table summarizes the main approaches described in mainstream dermatology sources, in neutral terms.
| Approach | How it works | Best suited to | Typical considerations |
|---|---|---|---|
| Silicone sheets or gels | Hydrate and gently flatten scar tissue over weeks to months | Raised or fresh maturing scars | Low risk; needs consistent use; little effect on pits |
| Topical retinoids and lightening agents | Speed skin turnover, reduce pigment production | Dark marks, very shallow texture change | Can irritate; sun sensitivity; prescription in many settings |
| Microneedling | Fine needles create controlled micro-injury that stimulates new collagen | Shallow to moderate pits | Several sessions; redness for days; lower pigment risk in darker skin |
| Chemical peels | Acid solution removes outer layers, evening tone and softening edges | Pigment change, shallow pits | Depth varies; deeper peels carry more risk |
| Laser resurfacing | Light energy removes or heats skin to trigger remodeling | Moderate pits, redness | Downtime; pigment change risk; choice of laser depends on skin tone |
| Subcision | A needle releases the fibrous band tethering a pit downward | Deep, anchored pits | Bruising; often combined with other methods |
| Dermal fillers | Injected material lifts the floor of a pit | Isolated deep pits | Temporary unless a longer-lasting filler is used |
| Punch excision or grafting | The scar is cut out and closed or replaced with a tiny graft | Single deep, sharp-edged pits | Trades a pit for a fine line scar |
Most published reviews conclude that combining methods matched to scar type produces better results than any single approach, and that results vary considerably between individuals. A dermatologist will usually recommend a course over several months rather than one appointment. What no reputable clinician will do is quote a percentage improvement in advance; skin is too individual for that.
Can chickenpox scars be prevented in the first place?
The most effective way to avoid chickenpox scars is to avoid chickenpox, and for most children that is now possible. The varicella vaccine, introduced into routine childhood schedules in the United States in the mid-1990s, contains a weakened form of the virus that trains the immune system without causing the full illness. The CDC reports that two doses are more than 90 percent effective at preventing chickenpox, and that people who are vaccinated and still catch it usually have a much milder illness with fewer spots, low or no fever, and faster recovery. Fewer, shallower spots mean fewer opportunities to scar.
Vaccination policy differs between countries. The United States, Canada, Australia and several European countries include varicella in routine childhood schedules; the United Kingdom has historically offered it only to specific groups, though its advisory committee has recommended broader use. Whether a particular child should have the vaccine, and on what schedule, is a question for the child’s own clinician and the national program.
For someone who has already been exposed but not yet developed the rash, the CDC notes that vaccination within a few days of exposure may prevent or lessen the illness, and that certain high-risk people may be offered a preparation of ready-made antibodies instead. Again, those are clinical decisions made case by case.
Once the rash has appeared, prevention shifts to the skin-care measures covered earlier: itch control, short nails, clean skin, undisturbed crusts, early attention to any infected spot and sun protection afterward. Parents sometimes feel that these are small things against a large problem. The evidence points the other way. Nearly every deep chickenpox pit began as a spot that was scratched open or infected, and those are exactly the events this care prevents.
What people often get wrong about chickenpox scars
Myths around this topic are stubborn, and several of them actively make scarring more likely. The most common ones deserve a direct correction.
“Scabs should be picked off once they look loose, so the skin can breathe.” Skin does not breathe through a wound. A crust is a protective barrier, and removing it early exposes tissue that is not yet closed. The scabs that fall off unaided are the spots least likely to scar.
“Every mark left at three weeks is a scar for life.” Almost none of them are. The pink and brown marks visible when the crusts come off are healing skin and pigment change, and the NHS timeline puts their fading at weeks to months. Judging outcomes before six months has passed is like judging a cake ten minutes into baking.
“Scratching only matters if it bleeds.” Even rubbing that does not break the surface can tear the roof of a blister and introduce bacteria. Infection, not bleeding, is what deepens a wound.
“Applying antiseptic or drying agents to every spot prevents scars.” Harsh antiseptics can irritate healing skin and slow the process. Mainstream guidance recommends gentle cleansing and leaving intact blisters alone; targeted treatment is for spots that are actually infected.
“Home remedies such as lemon juice, toothpaste or vitamin E oil fade scars.” There is no reliable evidence that any of these improve scars, and acidic or perfumed products can inflame skin and darken marks. Vitamin E applied to scars has been studied and has not shown consistent benefit; in some studies it caused skin irritation.
“Adults don’t need to worry; chickenpox is a children’s illness.” The CDC notes that adults tend to have more severe chickenpox with a higher risk of complications, and their lesions are often larger and deeper. Adults are, if anything, more likely to scar.
“Scar treatment removes scars.” It improves them. Anyone promising otherwise is not describing dermatology.
Questions to ask your care team
Whether you are sitting in a pediatrician’s office during the illness or in a dermatology consultation years later, the right questions turn a short appointment into a useful one. These are the ones that tend to matter most, grouped by stage.
During the illness
- Does this child fall into a group for whom antiviral treatment is usually considered, and if so, is it still early enough to help?
- Which itch-relief measures are appropriate for this age, and which should we avoid?
- How will I recognize a spot that is becoming infected, and how quickly should I bring them back if I see one?
- Are there signs that would mean this is no longer a routine case?
Once the skin has healed
- Are these marks pigment change, which should fade, or true pitted scars?
- How long would you suggest we wait before considering any treatment, and why that length of time?
- What sun protection is appropriate for this age and skin tone?
If considering scar treatment
- Which type of scar do I have, and which approaches are usually matched to that type?
- What does a realistic improvement look like for someone with my skin tone and scar depth, and what would count as a disappointing result?
- How many sessions are typical, how far apart, and what is the recovery like after each one?
- What are the specific risks for my skin type, including pigment change and the chance of making a scar more visible?
- What happens if I do nothing?
A good clinician will welcome the last question. Doing nothing is a legitimate option for a scar that is fading on its own or that the person can live with comfortably, and it is the only option with no side effects. The decision about whether and how to treat a chickenpox scar always sits with the person, or the parent, in conversation with the treating team.
When to call your doctor
Chickenpox is usually a mild illness that is managed at home, and scars are a cosmetic concern rather than a medical emergency. Certain signs, however, indicate a complication or a higher-risk situation and should prompt a call to a clinician or, in the most serious cases, emergency care. Both the NHS and the MedlinePlus guidance list the following.
Call your doctor promptly if:
- Any spot becomes increasingly red, warm, swollen, painful or leaks pus, or the redness spreads outward; these are signs of bacterial skin infection, which is the leading cause of deep scars and can spread further.
- Fever lasts more than four days, or returns after having settled.
- The person is a newborn, pregnant, over the age of twelve and unvaccinated, or has a weakened immune system or a long-term condition affecting the skin or lungs.
- The rash spreads to one or both eyes, or the eyes become red and painful.
- The person is not drinking enough and shows signs of dehydration, such as passing much less urine.
- The itch is severe enough that sleep is impossible despite home measures.
Seek emergency care immediately if there is:
- Difficulty breathing, fast breathing or chest pain.
- Unusual drowsiness, confusion, difficulty waking, a stiff neck, or a severe headache that keeps worsening.
- Repeated vomiting, a seizure, or trouble walking or with balance.
- A rash that becomes very tender to touch, or skin that turns dusky, purple or blistered over a wide area.
- Bleeding into the skin or spots that look like bruises.
Never give aspirin to a child or teenager with chickenpox. If a clinician has prescribed any medicine, use it exactly as directed and raise concerns with them rather than adjusting it yourself.
For scars themselves, a routine appointment is enough. Seek an earlier review if a healed scar becomes painful, grows beyond its original edges, changes color unevenly, bleeds or develops a sore that does not heal, since those changes warrant a proper examination.
Frequently asked questions
Can chickenpox scars go away completely?
Flat red, brown or pale marks usually do go away, over weeks to months, because they are healing skin and pigment change rather than structural damage. True pitted scars, where dermal tissue was lost, are permanent according to NHS guidance, although they soften, lose their color and often become proportionally smaller as a child grows. Treatment can make pits shallower and less visible but does not remove them entirely.
How long do chickenpox scars take to fade?
Fresh redness fades within a few weeks once crusts fall off; the NHS notes spots usually fade within a week or two of scabbing. Brown pigment marks commonly take several months, longer in deeply pigmented skin. Scar tissue itself keeps remodeling and paling for up to two years. Most dermatologists suggest waiting at least six to twelve months before judging a scar or considering treatment, because the skin does much of the work on its own.
How much does it cost to remove chickenpox scars?
This article does not publish prices, because costs vary widely by country, healthcare system, insurance coverage, type of procedure and number of sessions needed, and quoted figures quickly become misleading. Scar treatment is elective and usually not covered as a medical necessity. The most useful step is to ask the dermatology team, at the assessment stage, for a written outline of what a realistic course would involve and what it would cost in your particular setting.
How can I remove dark spots caused by chickenpox?
Dark spots after chickenpox are post-inflammatory hyperpigmentation, and most fade over months with strict sun protection and no picking or scrubbing. Shade, hats and clothing help infants; sunscreen on healed skin is appropriate from six months of age. Where marks persist, a dermatologist may suggest topical agents that slow pigment production or speed skin turnover, or a superficial peel. These can irritate skin and are not suitable for everyone, so the choice belongs with the treating clinician.
Do chickenpox scars go away on their own in children?
Most marks in children do resolve without treatment. Pigment changes fade, raised scars often flatten within one to two years, and pitted scars, while permanent, tend to look smaller relative to the face as the child grows. For this reason many dermatologists advise waiting until the mid to late teens before considering procedures for childhood chickenpox pits, since the scar seen at age four is rarely the scar seen at fourteen.
What is the best chickenpox scar treatment?
There is no single best treatment; the right approach depends on whether the scar is pitted, raised or discolored, on skin tone, and on how much downtime a person will accept. Microneedling, chemical peels, laser resurfacing, subcision, fillers and small excisions are the main options for pits, often combined. Silicone products suit raised scars, and topical agents suit pigment. A dermatologist matches the method to the scar; results vary between individuals and no reputable clinician promises a percentage improvement.
Does scratching chickenpox always cause scars?
No, but it is the biggest controllable risk. Scratching tears the roof of a blister, exposes the base and lets skin bacteria in; the resulting infection deepens the wound into the dermis, where scars form. A scratched spot that stays clean and closes quickly may heal without a mark. Keeping nails short and clean, controlling itch with cool baths and soothing measures, and treating any infected spot early all lower the chance that a scratched spot becomes a pit.
Why do adults scar more from chickenpox than children?
The CDC notes that chickenpox tends to be more severe in adolescents and adults, with more lesions, higher fever and a greater risk of complications. Adult blisters are often larger and extend deeper, and adults are more prone to bacterial superinfection of the skin. Deeper lesions and infection are the two main drivers of pitted scarring, which is why adults commonly end up with more marks despite scratching less than a young child would.
Do home remedies like vitamin E, lemon juice or toothpaste fade chickenpox scars?
There is no reliable evidence that any of these improve scars, and several can make things worse. Lemon juice and toothpaste are irritants that can inflame healing skin and darken pigment marks. Vitamin E applied to scars has been studied and has not shown consistent benefit; in some studies it caused contact irritation. The measures with genuine support are gentle cleansing, leaving crusts alone, sun protection and time, with clinician-guided treatment for scars that persist.
Can the chickenpox vaccine prevent scars?
Indirectly, yes. The CDC reports that two doses are more than 90 percent effective at preventing chickenpox altogether, and that vaccinated people who do catch it usually have a much milder illness with fewer, smaller spots and quicker recovery. Fewer and shallower blisters mean far fewer opportunities for scratching, infection and deep healing. Whether and when a child receives the vaccine depends on national schedules and the child’s own clinician.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

What the Start of Chickenpox Looks Like: Early Spots, Symptoms and Day-By-Day Changes
Chickenpox usually starts with a day or two of fever, tiredness and loss of appetite, followed by pink or red spots on the face,…

When Do Babies’ Eyes Change Color? The Melanin Timeline
Most babies' eyes change color gradually over the first year as melanin builds up in the iris. The most noticeable shifts usually happen between…

How Whooping Cough Is Diagnosed: Nasal Swab, Blood Tests and Why Early Sampling Matters
Whooping cough is usually diagnosed with a swab taken from the back of the nose, tested by PCR or culture for the bacterium Bordetella…

When Do Babies Start Teething? Signs, Timeline and Soothing
Most babies cut their first tooth around 6 months of age, usually a lower front incisor, though anywhere from 4 to 12 months falls…

Neuroblastoma Survival Rate: What the Statistics Mean, Stage by Stage, and What Changes Them
Neuroblastoma survival depends far more on risk group than on stage alone. According to the National Cancer Institute, more than 95% of children with…
Childhood Liver Cancer: What It Means, What to Expect and When to See a Specialist
Childhood liver cancer is rare, accounting for roughly 1 to 2 percent of cancers in children. The two main types are hepatoblastoma, usually found…