

Will You Be Awake During Eye Surgery? Drops, Blocks, Sedation and General Anesthesia

Key Takeaways
- Adult cataract surgery is usually done awake with numbing drops or a local block, and the NHS puts the typical operation at 30 to 45 minutes.
- Sedation calms the brain but does not numb the eye, so it is always layered on top of drops or a block rather than replacing them.
- A sub-Tenon's block uses a blunt cannula rather than a sharp needle behind the eye, which is one reason many teams prefer it for routine cases.
- General anesthesia is reserved mainly for children, complex or long operations, and adults who cannot lie still or cooperate.
- There is no bed rest after routine cataract surgery; most people go home within hours and resume ordinary activities within days, with full healing over roughly four to eight weeks.
- If a gas bubble is placed in your eye during retinal surgery, nitrous oxide anesthesia and flying can dangerously expand it, so future anesthesia teams must be told.
Most adults are awake for eye surgery. Cataract, glaucoma and many laser procedures are usually done with numbing drops or a local anesthetic injection around the eye, often with light sedation to help you relax. General anesthesia, which puts you fully to sleep, is reserved for children, longer or more complex operations, or people who cannot lie still. Your anesthesia team decides with you.
The paper cap is on, the arrow is drawn above the correct eyebrow, and the nurse has just asked, for the third time, which eye. Somewhere down the corridor a machine beeps. The person in the next chair leans over and whispers the question everyone in the room is thinking: “They’re not going to knock us out, are they?”
It is a fair thing to wonder. The eye is small, exquisitely sensitive, and about as close to the brain as a surgeon ever works. Yet anesthesia for eye surgery is one of the quieter success stories of modern medicine, precisely because it so rarely involves being unconscious. Most people walk in, lie down, watch a soft kaleidoscope of light for half an hour, and walk out.
This explainer walks through the four options your team may discuss, what each one feels like from the inside, who tends to get which, and what the first days afterward usually look like.
What kind of anesthesia is used for eye surgery?
Think of anesthesia for eye surgery as a dial rather than a switch. At the lightest setting are anesthetic eye drops, which numb the surface of the eye and nothing else. One notch up is an eye block, an injection of local anesthetic placed beside or behind the eyeball to numb the whole eye and often stop it moving. Sedation, a medicine given through a small cannula in the back of the hand to make you calm and drowsy, can be layered on top of either. At the far end of the dial sits general anesthesia, where you are fully unconscious and your breathing is supported.
Cataract surgery, the most common operation performed on adults in many countries, sits firmly at the light end. According to the NHS, it is usually carried out under local anesthetic with the patient awake, and the operation itself typically takes 30 to 45 minutes. The Mayo Clinic describes the same picture: local anesthesia, sometimes with a sedative, and home the same day.
Which option you receive depends on three things more than any other: how long the surgeon needs, how still the eye must be, and how comfortable you can realistically be lying flat with a drape over your face. A person having a five-minute laser treatment for glaucoma needs nothing more than drops. A toddler having squint surgery needs to be asleep. Between those poles, the choice is a conversation, not a rule.
One detail surprises many people: the specialist making that call is usually an anesthesiologist or an ophthalmologist trained in local techniques, and often both are in the room. The surgeon operates; the anesthesia clinician watches you.
How does anesthesia for eye surgery actually work?
Every local anesthetic, from the drops to the deepest block, works by the same trick. Nerves carry pain messages as tiny electrical pulses, and those pulses depend on sodium ions rushing through channels in the nerve membrane. Local anesthetics temporarily plug those channels. The nerve is still there and still healthy; it simply cannot send its message for a few hours. Cleveland Clinic’s overview of local anesthesia describes exactly this mechanism and notes that the effect fades as the medicine is carried away by the bloodstream and broken down.

The eye has two things a surgeon wants to switch off. The first is sensation: the cornea, the clear front window, has one of the densest nerve supplies in the body, which is why a stray eyelash feels like a boulder. Drops handle that beautifully. The second is movement. Six small muscles swivel the eyeball, and if they keep twitching while a surgeon works inside a space a few millimeters wide, precision suffers. An injected block bathes those muscles and the nerves feeding them, so the eye goes quiet and still. Drops alone cannot do that, which is why patients under topical anesthesia are asked to fix their gaze on the microscope light.
Sedation is a different mechanism altogether. It acts on the brain, dampening anxiety and awareness, and it does nothing for pain on its own. That is why sedation is always paired with a local technique rather than replacing it.
General anesthesia takes over the whole system: consciousness, memory, pain response and movement. Because the muscles that control breathing are also relaxed, an anesthesiologist supports your airway throughout. It is safe and routine, but it is also the biggest intervention of the four, which is exactly why teams reach for it last.
What kind of anesthesia is used for cataract surgery? Numbing drops explained
Topical anesthesia, meaning anesthetic applied to the surface as drops or a gel, is now the most common approach for routine cataract surgery in many centers. The drops sting for a second or two, then the eye feels oddly heavy and distant, a bit like a cheek after dental work. Some surgeons add a small amount of anesthetic inside the eye at the start of the operation to numb the iris, the colored ring that can otherwise register a dull ache when instruments pass nearby.
You will not see the surgery in any meaningful sense. The microscope light is bright enough to wash out detail, and most people describe shifting colors, shadows and a sensation of light pressure. You will hear the surgeon speaking and the soft hum of the machine that breaks up and removes the cloudy lens. The NHS notes that patients are awake throughout and that the procedure is not painful, although you may feel touch and mild pressure.
Drops have real advantages. There is no needle near the eye, no bruising, and your vision and eye movement return almost immediately, which is one reason MedlinePlus describes most cataract patients going home within a few hours. The trade-off is that you must cooperate: keep looking at the light, avoid squeezing your eyelids, and speak up rather than moving if something bothers you.
That is also why drops alone are not for everyone. Someone with a tremor, a persistent cough, severe anxiety, difficulty understanding instructions, or a very dense cataract that will take longer may be better served by a block or sedation. The surgeon weighs those factors at the pre-assessment visit, and the plan can change on the day if the eye behaves differently than expected.
Eye block anesthesia: sub-Tenon's, peribulbar and retrobulbar
An eye block delivers local anesthetic to the space around the eyeball so that the whole globe is numb and, usually, still. Three techniques are in common use, and the names describe where the medicine goes.
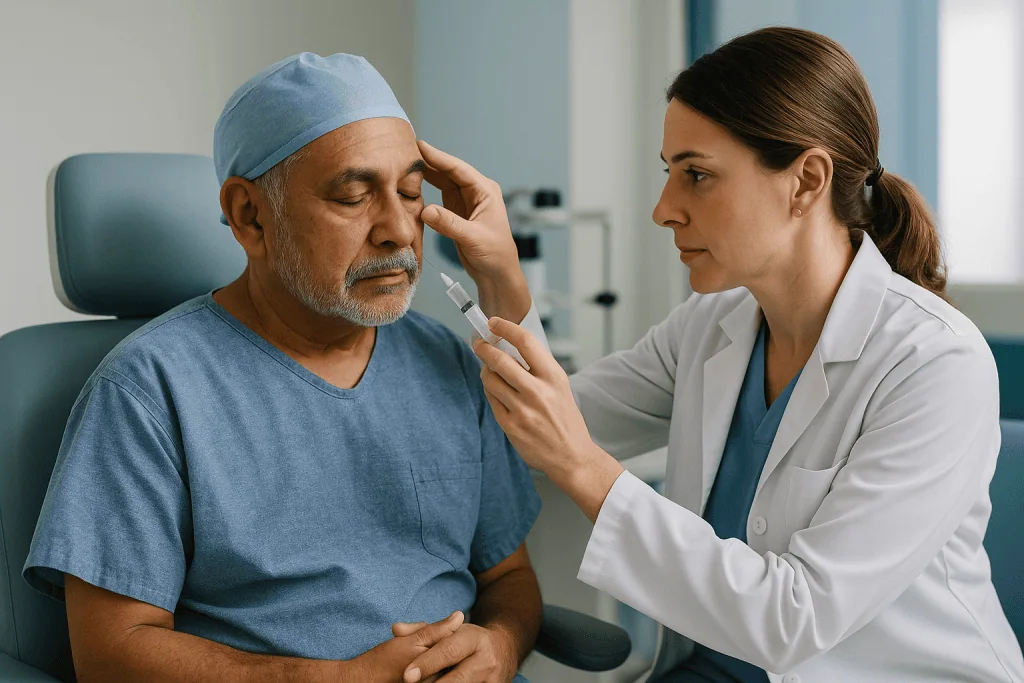
A sub-Tenon’s block uses no sharp needle at the eye itself. After numbing drops, the clinician makes a tiny opening in the conjunctiva, the thin membrane covering the white of the eye, and slides a blunt, curved cannula beneath Tenon’s capsule, a fibrous sleeve that wraps the eyeball. Anesthetic spreads around the globe from there. Because nothing sharp passes behind the eye, this approach is favored where bleeding risk or anatomy is a concern.
A peribulbar block places anesthetic with a fine needle beside the eyeball, outside the cone formed by the eye muscles. A retrobulbar block goes deeper, into that muscle cone behind the eye. Retrobulbar blocks act quickly and reliably stop movement, but because the needle travels close to the optic nerve and blood vessels, many teams now prefer the shallower peribulbar or sub-Tenon’s routes for routine cases.
Whichever technique is used, you feel pressure and a spreading numbness, then the eyelid droops and the eye stops moving. Vision on that side dims or disappears for the duration, which can be disconcerting if no one has warned you. It returns as the block wears off over several hours, and the NHS notes that local anesthetics typically fade within a few hours of injection.
Blocks are the workhorse for operations that need a still eye or run longer than a quick cataract: many retinal procedures, complex glaucoma surgery, corneal transplants and some eyelid or tear-duct operations. Bruising around the eye is the most common aftermath, and it usually looks worse than it feels.
Sedation for cataract surgery: awake but not anxious
“Twilight” is the word patients use; “conscious sedation” or “monitored anesthesia care” is what appears on the consent form. The idea is the same. A sedative, most often from the benzodiazepine class or a short-acting intravenous anesthetic given in small amounts, takes the edge off fear without switching you off. You can still follow the instruction to look at the light. You may still remember the operation, though many people recall it as brief and hazy.
Sedation is not automatic. Plenty of cataract patients have drops or a block alone and describe the experience as calm, even boring. Sedation earns its place when anxiety is likely to make someone tense, breathe fast or squeeze their eyelids, or when a block is being placed and a moment of relaxation makes the injection easier. The Mayo Clinic describes cataract surgery as performed with local anesthesia and, in some cases, a sedative to help you relax.
The medicine goes in through a cannula in the hand or forearm. Within a minute or two the room feels further away. Throughout, a monitor tracks your heart rhythm, blood pressure and oxygen level, and a clinician whose only job is to watch those numbers stays at your side. Oxygen through a soft tube under the nose is common, partly to compensate for the fact that the drape over your face traps a little carbon dioxide.
Deeper is not better here. Someone who drifts fully asleep under sedation may wake with a start and move, which is the one thing a surgeon working inside the eye cannot afford. Good sedation for eye surgery is deliberately light. If you have had heavier sedation for a colonoscopy or dental work and expect to remember nothing, it is worth resetting that expectation in advance.
Can you be put to sleep for eye surgery? When general anesthesia is chosen
Yes, and for some people it is clearly the right choice. General anesthesia means you are unconscious, unable to feel pain, and unaware of the operation from start to finish. The NHS describes it as a state of controlled unconsciousness produced by medicines given through a cannula or as a gas you breathe, with an anesthesiologist present throughout.
Children are the largest group. A six-year-old cannot be expected to lie motionless under a drape for forty minutes, so squint correction, examinations under anesthesia and pediatric cataract or glaucoma surgery are almost always done asleep. Adults join that list when they have severe anxiety or claustrophobia that sedation would not settle, a learning disability or dementia that makes cooperation unrealistic, a movement disorder, an inability to lie flat because of breathing or spinal problems, or a known allergy to local anesthetics.
Surgical reasons matter too. Operations that are long, involve both eyes at once, require a completely still and softened eye, or follow trauma to the eye may be safer under general anesthesia. Repair of a ruptured globe is a good example: an injection behind an already damaged eye could raise pressure inside it, so surgeons often prefer the patient asleep.
General anesthesia carries obligations for you. You will be asked to fast for a set period beforehand, to arrange someone to take you home and stay with you, and to avoid driving, alcohol and important decisions for the first day or two. The NHS lists tiredness, nausea, a sore throat and shivering as common, short-lived effects. Serious complications are rare, and your anesthesiologist will review your heart, lung and medication history to assess your individual risk. The decision, as always, is made with the treating team.
Who is usually offered which option, and who is asked to wait
Pre-assessment is where the anesthesia plan is really made. A nurse or clinician reviews your medical history, current medicines, allergies, previous anesthetics and how you managed them, and asks practical questions: Can you lie flat for half an hour? Do you cough a lot? Do you understand and hear instructions in a noisy room? The answers steer the choice more than the diagnosis does.
Drops alone suit people who are calm, can fix their gaze, and are having a short, straightforward operation. A block is offered when the eye must be still or the case is longer, and to anyone who would rather not feel touch at all. Sedation is added for anxiety or to ease block placement. General anesthesia is chosen for children and for the adult situations described above.
Blood thinners deserve a specific mention. Because sub-Tenon’s and topical approaches carry little bleeding risk, many patients on anticoagulants can proceed without interrupting their medicine. Sharp-needle blocks behind the eye are considered more carefully. Never stop or alter a prescribed anticoagulant on your own; the surgical team and the prescriber decide together.
Some people are asked to wait. An active chest infection, uncontrolled blood pressure on the day, a very high blood sugar reading, or a recent heart event may lead a team to postpone, particularly if general anesthesia or sedation is planned. Eye infections such as conjunctivitis or an active flare of blepharitis are also reasons to reschedule, since operating through an infected surface raises the risk of infection inside the eye. A delay is disappointing, but it is a safety decision rather than a judgment.
Pregnancy is another pause point for elective eye surgery, mainly to avoid unnecessary medicines, unless the operation is urgent.
Anesthesia options for eye surgery compared side by side
Seeing the four approaches in one place helps most people understand why their surgeon suggested a particular plan. The table summarizes typical features; individual experiences vary, and your team may combine methods.
| Approach | How it is given | Awareness | Eye movement | Commonly used for | Typical trade-offs |
|---|---|---|---|---|---|
| Topical drops or gel | Drops on the eye surface, sometimes with anesthetic inside the eye | Fully awake | Eye still moves; you fix on the light | Routine cataract surgery, laser procedures, minor surface work | Requires cooperation; may feel pressure or touch |
| Eye block (sub-Tenon’s, peribulbar, retrobulbar) | Local anesthetic injected around the eye after numbing drops | Awake; vision on that side dims | Usually stopped | Retinal, glaucoma, corneal and longer cataract cases | Bruising, temporary double vision; rare needle-related complications |
| Sedation (added to drops or block) | Medicine through a hand cannula | Drowsy, calm, often patchy memory | Depends on the local technique beneath it | Anxious patients; easing block placement | Requires an escort home; does not relieve pain by itself |
| General anesthesia | Intravenous medicine and/or gas; airway supported | Unconscious | Completely still | Children, complex or long operations, patients unable to cooperate | Fasting, longer recovery, nausea and grogginess; small but real systemic risks |
Two patterns stand out. First, the amount of anesthesia rises with the demand for stillness rather than with how frightening the operation sounds. Second, the lightest option that will let the surgeon work safely is usually preferred, because every step up the dial adds recovery time and a little risk. The NHS and Mayo Clinic both describe local anesthesia as the standard for adult cataract surgery for exactly this reason.
What you will see, hear and feel during awake eye surgery
The room is cooler than you expect. You lie on a narrow bed that tilts your head back, and a sticky plastic drape is placed over your face with a window cut for the operative eye. A small tube under the drape delivers fresh air or oxygen so that space never feels stuffy. A gentle clip called a speculum holds the eyelids open; with drops or a block in place, you cannot feel the urge to blink.
Then the microscope light comes on, and the world becomes color. People describe swirling pinks, blues and whites, occasionally a shadow moving across. You will not see instruments or the surgeon’s hands in any recognizable form. Under a full block you may see nothing at all, which is normal and temporary.
Sound is the most vivid sense. You hear the surgeon asking for instruments, the rhythmic whirr of the machine used during cataract surgery, and, often, someone reminding you to keep looking straight ahead. Many teams play quiet music.
Touch registers as pressure, tugging, or a cool sensation when fluid flows across the eye. Sharp pain is not expected, and if you feel it, saying so calmly lets the team add anesthetic. The rule everyone will repeat is simple: talk, do not move. A raised hand is a good agreed signal if you need to cough or sneeze.
The end arrives sooner than most people anticipate. The NHS gives 30 to 45 minutes for a typical cataract operation. A clear shield is taped over the eye, the drape comes off, and you sit up slowly. If you had sedation, the first cup of tea in recovery is often the moment the whole thing suddenly feels done.
Anesthesia for different eye procedures, from LASIK to retina surgery
Cataract surgery gets most of the attention, but the anesthesia logic scales across the specialty.
Laser vision correction such as LASIK, in which a laser reshapes the cornea to reduce the need for glasses, is done with numbing drops alone. MedlinePlus describes the procedure as lasting roughly 10 to 15 minutes per eye with the patient awake, and a mild oral sedative is sometimes offered to help with nerves. You will be asked to stare at a target light while the laser works.
Glaucoma treatments range widely. Office laser procedures need only drops. Trabeculectomy or tube surgery, which create new drainage pathways for fluid inside the eye, are commonly done under a block, with or without sedation.
Retinal surgery, including vitrectomy, where the jelly filling the back of the eye is removed and replaced, usually involves a block because the eye must be still and the operation can run longer. General anesthesia is chosen for some complex or bilateral cases. A specific caution follows any retinal operation in which a gas bubble is left inside the eye: the anesthetic gas nitrous oxide expands that bubble and can dangerously raise eye pressure, so you must tell any future anesthesiologist about the bubble, and your surgeon will specify how long you must avoid flying or altitude.
Corneal transplants are typically performed under a block or general anesthesia, since the eye is open for a period and movement is hazardous. Eyelid, tear-duct and orbital surgery often use local anesthetic injected into the skin, with sedation or general anesthesia for longer reconstructions.
Children and adults who cannot cooperate, as discussed, are almost always asleep regardless of the operation. The procedure sets the floor; the patient sets the rest.
Risks and side effects of anesthesia for eye surgery
Honest risk talk should start with proportion. Serious anesthesia complications in eye surgery are uncommon, and the shift toward drops and sub-Tenon’s blocks over the past few decades has been driven largely by a wish to make them rarer still. That said, every approach has a characteristic set of nuisances and a short list of rare but real hazards.
Drops can sting briefly and may leave the surface slightly rough for a day, adding to the gritty feeling that follows cataract surgery anyway. Some people find the pressure sensations under drops alone unpleasant.
Blocks commonly cause a bruised, puffy eyelid and a red patch on the white of the eye where a small vessel bled; both settle over days. Double vision or a droopy lid for a few hours is expected as the muscles wake. Rarely, a sharp needle can puncture the globe, injure the optic nerve, cause bleeding behind the eye, or allow anesthetic to spread toward the brainstem, producing drowsiness or breathing difficulty. These events are why teams monitor you after a block and why blunt-cannula techniques have gained ground.
Sedation can cause a drop in oxygen level or blood pressure, disinhibition, or an unexpected slide into deeper sleep. Continuous monitoring exists to catch and correct these within seconds.
General anesthesia adds the systemic picture the NHS describes: nausea, sore throat, shivering, confusion in older adults, and rare complications such as allergic reaction or aspiration. Age, heart and lung disease, and certain medicines change the balance, which is why the anesthesiologist’s pre-operative questions matter.
Discuss your own risk profile rather than the averages. The team will explain which of these apply to you and how they plan to reduce them.
How long is bed rest after cataract surgery? The days and weeks afterward
Here is a myth worth killing early: there is no bed rest after routine cataract surgery. The NHS notes that most people go home a few hours after the operation and can return to most normal activities within a few days. Being up and gently active is encouraged; lying flat in a darkened room is not part of modern recovery.
The first hours depend on your anesthesia. After drops, the eye feels gritty and sensitive to light, and vision is blurry. After a block, the eyelid may stay droopy and vision dim until the anesthetic fades over the following hours; you may also notice double vision briefly. After sedation you will feel washed out for the rest of the day, and after general anesthesia the NHS advises avoiding driving, alcohol and signing legal documents for 24 to 48 hours.
The eye itself follows its own timeline. The Mayo Clinic notes that vision often begins to improve within a few days, though colors may look startlingly bright at first, and describes complete healing as typically taking about eight weeks. The NHS puts full recovery at roughly four to six weeks and advises against swimming during that period, along with avoiding rubbing the eye, strenuous exercise and eye makeup in the early weeks.
Most people are asked to wear a plastic shield at night for a while, use prescribed anti-inflammatory and antibiotic drops exactly as directed, and attend a follow-up review. Driving resumes only when your surgeon confirms your vision meets the legal standard. Return to desk work is often possible within days; heavy or dusty manual work takes longer. Your surgeon’s instructions override any general timeline, including this one.
What people often get wrong about being awake for eye surgery
The most stubborn misconception is that being awake means seeing the scalpel. You do not. The microscope light and the drape mean that even under drops, the experience is of colors and shadows, not instruments. Under a block, many people see nothing at all.
A close second is the fear of blinking or flinching at the wrong moment. The speculum holds the lids, the anesthetic removes the blink reflex, and surgeons are trained to pause the instant an eye moves. Talking is allowed; moving your head is what to avoid.
Many people also assume general anesthesia is the safest option because it feels the most thorough. In eye surgery the reverse is closer to the truth. General anesthesia involves the heart, lungs and airway; a local block involves one eye. For most healthy adults having cataract surgery, local anesthesia carries fewer systemic risks and a faster recovery, which is why the NHS and Mayo Clinic describe it as the standard approach.
Another mix-up: sedation is not the same as anesthesia. Sedation calms; it does not numb. If you want to feel nothing, that is the job of drops or a block, and sedation is the optional companion.
Then there is the question a surprising number of people type into search engines: “Which is better, anesthesia or ophthalmology?” They are not competitors. Ophthalmology is the surgical specialty that operates on the eye; anesthesiology is the specialty that keeps you safe and comfortable while it happens. In an eye theater they work as a pair.
Finally, being awake is not a sign the team is cutting corners. It is a sign that your operation is short, precise and well suited to the lightest anesthesia that keeps you safe.
Questions to ask your care team about anesthesia for eye surgery
Pre-assessment goes better when you arrive with questions rather than trying to think of them afterward. These are the ones that tend to change how a person feels on the day.
- Which anesthesia approach are you planning for me, and why that one rather than the alternatives?
- Will I have an injection near my eye? If so, will it be a blunt-cannula sub-Tenon’s technique or a needle block, and what will I feel?
- Will sedation be offered, and can I choose to have it, or to decline it?
- Will my vision on that side disappear during the operation, and for how long afterward?
- Do I need to fast, and from when? Which of my regular medicines should I take that morning?
- I take a blood thinner or diabetes medicine; who decides whether anything changes, and when will I hear?
- How will we communicate during surgery if I need to cough, sneeze or report discomfort?
- Who will be monitoring me, and will an anesthesiologist be present throughout?
- Do I need someone to take me home and stay overnight?
- When can I expect to drive, return to work, read and use screens comfortably?
- If a gas bubble is used, how long must I avoid flying, and what should I tell future anesthesia teams?
- What symptoms after surgery mean I should call you the same day?
Write the answers down or bring someone who will. If anything in the plan worries you, say so at pre-assessment rather than in the anesthetic room; options such as adding sedation or switching to a block are far easier to arrange with notice. Bring a list of all medicines and supplements, including over-the-counter products, since some interact with sedatives or affect bleeding.
When to call your doctor after eye surgery
Mild grittiness, light sensitivity, watering and blurred vision are expected in the first days, and a bruised lid after a block is unremarkable. Certain signs are not. Contact your surgical team or emergency eye service the same day, and do not wait for your scheduled follow-up, if you notice any of the following.
- Pain that is increasing rather than settling, or pain not relieved by the measures your team suggested.
- Vision that was improving and then becomes worse, or a sudden drop in vision.
- A new curtain or shadow across part of your vision, or a shower of new floaters and flashing lights, which can signal a retinal detachment.
- Increasing redness, a sticky yellow or green discharge, or the eyelid becoming hot and swollen.
- Nausea and vomiting together with a painful, hard-feeling eye, which may indicate raised pressure inside it.
- Any of these symptoms in the days after a gas bubble was placed, or after flying or travelling to altitude against advice.
After sedation or general anesthesia, seek urgent help for breathing difficulty, chest pain, a rash spreading across the body, persistent vomiting, or confusion that does not clear as the day goes on. The NHS lists these among the reasons to contact medical services after an anesthetic.
Infection inside the eye after surgery is rare, but it is an emergency measured in hours, and outcomes depend on speed. If in doubt, phone the number on your discharge sheet. No one on an eye unit minds a call that turns out to be unnecessary; every experienced clinician has stories about the call that came too late. Your treating team knows your operation, your anesthetic and your eye. Their instructions, and their judgment, come before anything written here.
Frequently asked questions
What kind of anesthesia is used for eye surgery?
Most eye operations use local anesthesia, either as numbing drops on the eye surface or as an injection of local anesthetic around the eye, called a block. Light sedation is often added to help you relax. General anesthesia, which makes you fully unconscious, is used for children, longer or more complex procedures, and adults who cannot lie still. The choice is made at your pre-assessment with the anesthesia team.
Can you be put to sleep for eye surgery?
Yes. General anesthesia is available and is the standard for children and for adults with severe anxiety, movement disorders, dementia, an inability to lie flat, or complex operations such as repair of an injured eye. For routine adult cataract surgery, though, local anesthesia is preferred because it carries fewer systemic risks and a quicker recovery. If you feel you need to be asleep, raise it early so the plan can be arranged.
What kind of anesthesia is used for cataract surgery?
Cataract surgery is usually performed under local anesthesia while you are awake, according to both the NHS and Mayo Clinic. Many surgeons use anesthetic drops or gel, sometimes with a small amount of anesthetic placed inside the eye. Others use a sub-Tenon’s or peribulbar block to numb and still the whole eye. A sedative through a hand cannula may be offered if you are anxious. You go home the same day.
Does eye block anesthesia hurt?
An eye block is placed after numbing drops, so most people feel pressure and a spreading heaviness rather than sharp pain. The sub-Tenon’s technique uses a blunt cannula and no needle at the eye; peribulbar and retrobulbar blocks use a fine needle beside or behind the eyeball. Afterward the eyelid droops and vision dims for several hours until the anesthetic wears off. A bruised lid or red patch on the white of the eye is common and settles over days.
Is sedation for cataract surgery necessary?
No. Sedation is optional and many people have cataract surgery with drops or a block alone. It is offered when anxiety might make you tense or move, or to ease the placement of a block. Sedation for eye surgery is kept deliberately light so you can still follow instructions to look at the light; you may remember parts of the operation. Sedation does not numb the eye, so it is always combined with a local technique.
Will I see the surgeon operating on my eye?
Not in any recognizable way. The microscope light is bright enough to wash out detail, and a drape covers your face with only the operative eye exposed. Under drops, people describe swirling colors, shadows and light pressure. Under a full block, vision on that side often disappears entirely until the anesthetic wears off. You will hear the team talking and the hum of equipment, and many units play quiet music.
What happens if I blink, cough or move during eye surgery?
A small clip called a speculum holds your eyelids open and the anesthetic removes the blink reflex, so blinking is not a problem. If you need to cough or sneeze, tell the team or use an agreed hand signal; the surgeon pauses instantly and lifts instruments clear. Talking is allowed. The one thing to avoid is a sudden head movement, which is why people who cannot keep still are offered sedation or general anesthesia instead.
How long is bed rest after cataract surgery?
There is no bed rest after routine cataract surgery. The NHS notes that most people go home within hours and return to normal activities within a few days, while full recovery takes about four to six weeks. Gentle activity is encouraged. You will be asked to avoid rubbing the eye, swimming, strenuous exercise and eye makeup for a period your surgeon specifies, to wear a shield at night, and not to drive until your vision has been checked.
Which is better, anesthesia or ophthalmology?
They are not alternatives. Ophthalmology is the medical and surgical specialty that treats the eye; anesthesiology is the specialty that keeps you safe, still and comfortable during an operation. In an eye theater, an ophthalmic surgeon operates while an anesthesiologist or trained anesthesia clinician monitors your breathing, heart rate and comfort. The two work as a team, and the anesthesia plan is chosen to suit the operation the surgeon needs to perform.
How long does the local anesthetic take to wear off after eye surgery?
Numbing drops fade within an hour or so, leaving a gritty, light-sensitive eye. An injected block typically wears off over several hours, during which the eyelid may droop and vision on that side stays dim or doubled; the NHS notes local anesthetics generally fade within a few hours. After sedation you will feel tired for the rest of the day, and after general anesthesia the NHS advises not driving or drinking alcohol for 24 to 48 hours.
References
- NHS: Cataract surgery: What happens
- NHS: Cataract surgery: Recovery
- NHS: General anaesthesia
- MedlinePlus: LASIK eye surgery
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

When Do Glaucoma Drops Give Way to Laser or Surgery? How Treatment Usually Escalates
Glaucoma drops usually give way to laser or surgery when eye pressure stays above the target the eye specialist has set, when visual-field or…

Reading Your Glaucoma Treatment Plan: Target Pressure, Follow-Up Intervals and What to Ask
A glaucoma treatment plan usually sets a target eye pressure, chosen individually to slow damage to the optic nerve, and a follow-up interval for…

Questions to Ask Your Retina Specialist About Macular Degeneration Injections and Follow-Up
Before macular degeneration injections begin, ask your retina specialist what type and stage of AMD you have, which scans confirmed it, how the anti-VEGF…

Steroid Injection vs Surgical Removal for a Chalazion: How Doctors Weigh the Two
For a chalazion that has not settled with warm compresses, doctors usually choose between a corticosteroid injection into the lump and surgical drainage under…

Before Your Conjunctivitis Appointment: Lenses Out, Makeup Off and Which Details to Bring
Before a conjunctivitis appointment, take out contact lenses and switch to glasses, skip eye makeup so the examiner can judge redness, lid margins and…

Does a Robot Operate on Your Eye Alone? Robotic Ophthalmology Myths, Put Right
No. Today, no robot performs eye surgery on its own. In every approved procedure, a trained ophthalmologist makes the decisions and controls the instruments.…