

Acne Scar Treatment for Darker Skin: Why Pigment Risk Changes the Method and the Prep

Key Takeaways
- Flat brown marks after acne are post-inflammatory hyperpigmentation, not scars, and they respond to sun protection and topical care rather than resurfacing.
- Heat is the main trigger for new pigment in melanin-rich skin, which is why microneedling, subcision, superficial peels and fillers are favored over ablative resurfacing.
- Lasers are used in darker skin, but with longer wavelengths, fractional non-ablative delivery, lower energy and a test spot observed for weeks beforehand.
- Ice pick scars are the hardest depressed scars to treat because their base lies too deep for surface-safe methods, so they are usually treated one pit at a time.
- Post-treatment hyperpigmentation often appears one to three weeks after visible healing ends, so daily sun protection must continue well beyond the redness phase.
- Keloids form more often in darker skin on the jaw, chest, shoulders and back, and a personal keloid history changes how conservatively any scar procedure is approached.
Acne scar treatment for darker skin usually starts by calming active acne and fading post-inflammatory hyperpigmentation before any resurfacing, because melanin-rich skin reacts to heat and injury by producing more pigment. Clinicians then favor lower-energy, fractionated or non-thermal methods such as microneedling, superficial peels, subcision and fillers, often with weeks of topical preparation, sun protection and a small test area first.
She had done everything the internet told her. The acne itself was finally quiet, yet the mirror still showed a map of it: a cluster of shallow dents along the cheek, and around each one a brown halo that had outlasted the pimple by a year. A friend with fair skin had a laser session and came back glowing. A cousin with skin much like hers tried a similar treatment and came back with a patchwork of darker squares that took longer to fade than the scars they were meant to fix.
That gap between two experiences is the heart of acne scar treatment for darker skin. The scars are the same shapes as anyone else’s. What differs is how the skin responds to the treatment itself, and that response changes which method is chosen, how strong it is set, and how much quiet groundwork happens before anyone picks up a needle or a handpiece.
This explainer walks through that logic, so the conversation with your dermatologist starts from an informed place rather than a hopeful one.
Why acne scar treatment for darker skin starts with a different question
Most people arrive asking which device works best. Dermatologists treating darker skin tend to flip the order and ask first: how will this skin heal afterward? The reason sits in the pigment-producing cells called melanocytes. In skin that is naturally rich in melanin, these cells are more reactive to any inflammation, whether from a pimple, a scrape or a deliberate treatment injury. The Cleveland Clinic describes this reaction as post-inflammatory hyperpigmentation, or PIH: a flat, darker patch left behind after inflammation settles, which can persist for months (see reference on PIH).
That single biological fact reshapes everything. A treatment that trades a brief period of redness for smoother skin in a lighter complexion may, in a darker one, trade the same smoothing for a new patch of brown that is more noticeable than the original scar. So the goal is not the strongest method but the one that improves texture while keeping inflammation and heat below the threshold that wakes up melanocytes.
Clinicians often describe skin using the Fitzpatrick scale, a six-step classification of how skin responds to sun, where types IV to VI tan easily and rarely burn. It is a rough guide rather than a diagnosis, and two people with the same type can heal quite differently. A good consultation therefore looks beyond the scale to your own history: how did past cuts, bites, waxing or breakouts heal? Did marks darken, lighten, or thicken into raised scars? Those answers predict risk better than any chart, and they are what a careful practitioner will want to hear before recommending anything.
Which mark do you actually have? Dark spots, red spots and true scars
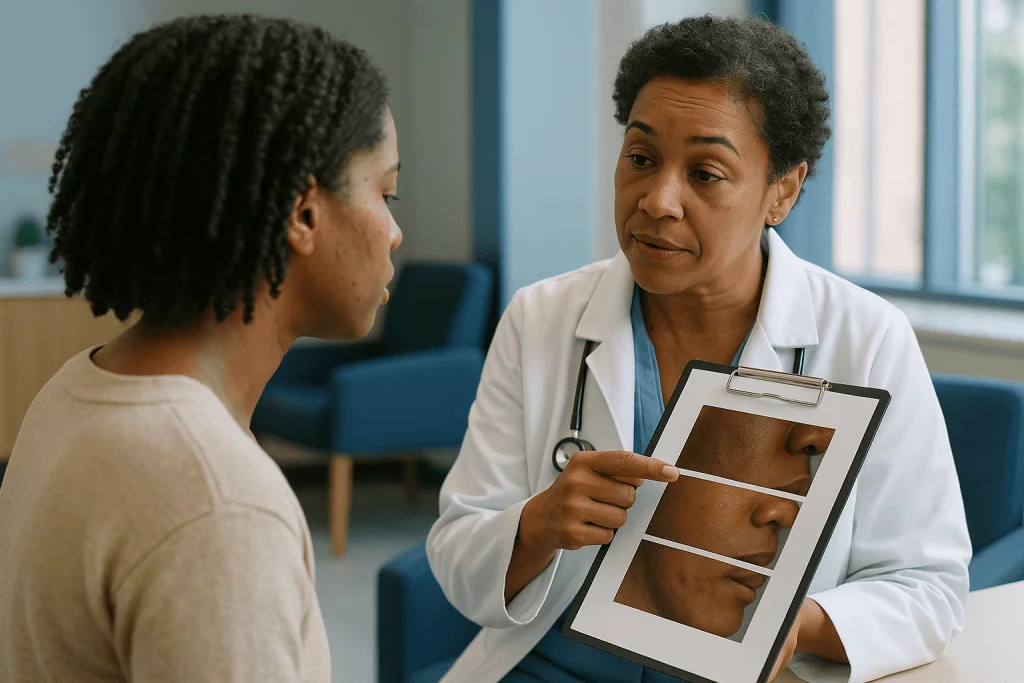
Much frustration comes from treating the wrong thing. Not every mark that follows acne is a scar, and the distinction decides the plan. The Mayo Clinic groups true acne scars into depressed (atrophic) scars, where tissue was lost, and raised (hypertrophic or keloid) scars, where too much collagen was laid down. Flat color changes are a separate category altogether.
| What you see | What it is | Typical approach in darker skin |
|---|---|---|
| Flat brown or gray-brown patch, no texture change | Post-inflammatory hyperpigmentation (excess melanin in the upper skin) | Sun protection, topical pigment-modulating creams, very superficial peels; time |
| Flat pink or red mark | Post-inflammatory erythema (lingering dilated blood vessels) | Often fades on its own; vascular treatments used cautiously |
| Small, deep, narrow pit | Ice pick scar | Focused chemical reconstruction (TCA CROSS), punch techniques |
| Wider dent with sharp edges | Boxcar scar | Microneedling, low-energy fractional resurfacing, fillers |
| Broad, soft, wave-like dip | Rolling scar (tethered by fibrous bands beneath) | Subcision, fillers, microneedling |
| Raised, firm, sometimes itchy scar | Hypertrophic or keloid scar | Steroid injections, silicone, pressure; avoid aggressive resurfacing |
Run your fingertip across the area with your eyes closed. If it feels perfectly smooth, you are dealing with color, not structure, and the plan will lean on gentler tools. If you feel dips or bumps, the texture needs its own approach, and the pigment risk still shapes how that approach is delivered.
Dark spots from acne: why pigment is treated first, not last
Treating the brown marks before the dents can feel backward. The dents are what bother most people, and pigment seems like the easy part. Yet clinicians tend to sequence it this way for two practical reasons.
First, active hyperpigmentation is a sign that the skin is still in an inflammatory mood. Resurfacing an area that is actively producing excess melanin tends to produce more of it. Calming the pigment response, and confirming that the skin can settle, gives useful information about how it will tolerate a procedure.
Second, some of the pigment will fade on its own with patience and sun protection. The Cleveland Clinic notes that post-inflammatory hyperpigmentation often improves over months and can take much longer to resolve fully in deeper skin tones. Spending that waiting time on preparation, rather than on a procedure that resets the clock, is time well used.
The topical options a dermatologist may discuss work by different mechanisms. Retinoids, a class derived from vitamin A, speed the turnover of pigmented surface cells and thin the outer layer so other agents penetrate. Azelaic acid and hydroquinone, mentioned here only as generic examples, interfere with the enzyme that manufactures melanin. Whether any of these is appropriate, and for how long, is a decision for the prescribing clinician, because each carries its own irritation risk, and irritation in darker skin is itself a trigger for more pigment.
The unglamorous cornerstone is daily broad-spectrum sun protection. Ultraviolet light is the single most reliable amplifier of PIH. Without it, every other step is working against a headwind.
How pigment-safe acne scar treatment for darker skin actually works
Every scar procedure shares one mechanism: controlled injury. The skin is wounded in a deliberate pattern, and as it repairs itself it produces fresh collagen, the protein scaffold that gives skin its firmness. New collagen fills depressions from below and softens their edges. The Mayo Clinic lists the tools that create this injury, from needling and chemical peels to lasers, dermabrasion, and surgical release of tethered scars.

The pigment-safe version of this idea rests on three adjustments.
- Less heat. Heat spreading into surrounding tissue is what most reliably provokes melanocytes. Methods that injure mechanically (needles, blades, cannulas) or chemically (acids) deliver little heat. Light-based methods that do generate heat are chosen and set so that the energy stays concentrated in tiny columns rather than spreading.
- Less surface damage. Techniques that spare the outer layer, or treat only a small percentage of the surface per session, leave healthy skin between treated points to speed repair and reduce inflammation.
- More sessions, more gently. Spreading the same total effect across several modest treatments keeps each healing episode below the threshold that triggers pigment.
A fourth element sits outside the treatment room: preparation of the skin for weeks beforehand and protection for weeks afterward, covered later in this article. Practitioners experienced with darker skin often describe their work as a low-and-slow approach. It asks more patience of the patient, and it usually offers a more predictable outcome than a single dramatic session. Neither route can promise a particular result; the aim is improvement, and the degree varies from person to person.
Is microneedling for dark skin safe, and what does it involve?
Microneedling has become a first-line texture treatment for deeper skin tones, and the reason is mechanical rather than fashionable. A device studded with fine sterile needles is passed over numbed skin, creating thousands of micro-punctures that reach the dermis, the collagen-producing middle layer, while leaving the surface largely intact. No heat is delivered in standard microneedling, which removes the main trigger for pigment. The Cleveland Clinic lists microneedling among the established procedures for depressed acne scars, typically performed as a course of several sessions spaced weeks apart (see acne scars reference).
Radiofrequency microneedling is a variant in which the needle tips release heat energy deep in the dermis. Because the heat is delivered below the surface and the tips can be insulated along their length, this approach is also used in darker skin, but the added energy means settings and depth matter more and the margin for error narrows. It is a reasonable question to ask which version a clinic proposes and why.
What the session feels like: numbing cream is applied for a period, the treatment itself brings a scratching or vibrating sensation, and the skin looks sunburned and feels tight afterward. Pinpoint bleeding is expected and stops quickly.
Safety in darker skin is not automatic. Needles that are too long for the area, excessive passes, or treating skin that still has active acne can all provoke pigment. Some practitioners also apply topical products immediately after needling; introducing an ingredient into freshly opened skin raises the risk of reaction, so ask what, if anything, will be applied. Microneedling is best understood as gentler and more forgiving, not as risk-free.
Which lasers are used on darker skin, and why the settings matter more than the brand
Lasers work by delivering a specific wavelength of light that is absorbed by a target in the skin. The complication for darker skin is that melanin absorbs many of those wavelengths eagerly. A laser aimed at water in the dermis to stimulate collagen may also heat the melanin in the epidermis on its way in, and heated melanocytes respond by producing more pigment, or occasionally by shutting down and leaving a paler patch.
Clinicians manage this in several ways. Longer wavelengths are absorbed less by melanin, so certain infrared lasers are preferred. Non-ablative lasers, which heat tissue beneath the surface without removing the top layer, are generally favored over ablative lasers, which vaporize the surface and demand a longer, more inflamed recovery. Fractionated delivery treats only a grid of tiny columns per pass, leaving untreated skin between them to speed healing. Lower energy per pulse, fewer passes, and effective skin cooling all reduce the heat load.
The Mayo Clinic notes that laser resurfacing carries a higher risk of pigment changes in people with darker skin, which is why a test spot, a small area treated and observed for several weeks, is common practice before committing the whole face.
Two points deserve emphasis. Device brand names circulate widely online, but the same machine can be safe or harmful depending on how it is set and who is holding it. And the question that matters is not whether lasers can be used in darker skin, which they can, but whether the practitioner regularly treats skin like yours and can explain their parameter choices in plain language.
Chemical peel for dark skin: why shallower and slower wins
A chemical peel uses an acid solution to dissolve the bonds holding surface cells together, so those layers shed and are replaced by fresher skin. Peels are described by how deep they reach. Superficial peels affect only the epidermis, the outermost layer; medium peels reach the upper dermis; deep peels go further and are rarely used in darker skin because of the pigment risk the Mayo Clinic flags for stronger resurfacing.
For darker complexions the pattern is a series of superficial peels rather than one strong one. Common agents include glycolic, salicylic, lactic and mandelic acids at low concentrations. Salicylic acid dissolves in oil and reaches into pores, which is useful when acne is still smoldering. Mandelic acid has a larger molecule that penetrates more slowly and evenly, a property some clinicians value for reactive skin. Each of these is named here only to explain mechanism, not as a recommendation.
Superficial peels help mainly with the color component of acne marks and with overall surface texture. They will not lift a boxcar scar or release a rolling one; expecting that leads to disappointment, or to escalating peel strength until pigment problems appear.
A separate technique borrows peel chemistry for deep scars. TCA CROSS applies a concentrated trichloroacetic acid solution precisely into the base of individual ice pick scars with a fine applicator, deliberately injuring only the pit so it fills from below. Because the acid never touches the surrounding surface, it can be used in darker skin, though a temporary dark ring around each treated pit is common and expected before it fades. Frosting, the white appearance of treated skin during a peel, is normal; patchy darkening days later is what you watch for.
Subcision, fillers and the scars that are hardest to treat
Rolling scars behave like a tent pegged down from below. Fibrous bands tether the skin to deeper tissue, and no amount of surface work will lift a dip that is anchored. Subcision addresses the anchor directly: after numbing, a fine needle or blunt cannula is inserted beneath the scar and swept back and forth to cut the bands. Blood pools in the freed space and, as it organizes, stimulates new collagen. Because the surface is barely touched, subcision is a pigment-friendly option and is frequently combined with needling or fillers.
Dermal fillers, gel-like substances injected beneath a depression, lift it from underneath. The Mayo Clinic lists both fillers and surgical release among established acne scar methods. Most fillers are temporary and dissolve over months; some are longer-lasting. Filler under a scar has little to do with pigment risk, so it is one of the few tools whose use barely changes with skin tone.
People often ask which scar is hardest to treat. Ice pick scars earn that reputation. They are narrow but deep, often reaching well into the dermis, so resurfacing that is safe for the surface simply does not reach their base. Treatment is usually per-scar rather than per-area, using TCA CROSS or punch excision, in which a tiny circular blade removes the scar and the edges are closed. Each is slow and fiddly, and every excision creates its own small wound with its own pigment potential.
Widespread hypertrophic and keloid scarring is arguably harder still, because the tools that help depressed scars can worsen raised ones. The next sections turn to that risk.
Who is usually a candidate, and who is asked to wait
The ideal starting point is skin that has been free of new inflammatory acne for several months, with hyperpigmentation that has stabilized or is fading, and a clear understanding of which marks are color and which are texture. Age matters less than skin state, though many clinicians prefer that adolescent acne has fully settled before scar work begins, since new breakouts undo progress and create new scars.
People are commonly asked to wait, or to change course, in these situations:
- Active acne. Treating scars while new lesions are forming means treating a moving target and inflaming skin that is already inflamed. The Mayo Clinic advises controlling acne before addressing scars.
- Recent oral isotretinoin. This vitamin A derivative changes how skin heals, and many practitioners defer resurfacing for a period after a course ends. The exact interval is the prescriber’s call.
- A history of keloids. Anyone who has formed a raised, spreading scar after a piercing, surgery or injury needs a cautious plan, because scar procedures are themselves injuries.
- Recent sun exposure or a planned sun-heavy trip. Tanned skin and healing skin do not mix well.
- Pregnancy, breastfeeding, or certain medical conditions. Some topical preparations and procedures are deferred; the treating team decides.
- Unrealistic goals. Scar treatments improve; they do not erase. A practitioner who hears an expectation of flawless skin may ask for more conversation before booking.
Waiting is not a rejection. It is usually the safest version of a yes, delivered when the skin is in a state that gives the procedure its best chance.
What the weeks of preparation actually involve
Preparation is where treatment for darker skin differs most visibly from the standard version, and it is often the part that surprises people. Instead of booking a procedure for next week, the plan may open with several weeks of groundwork.
The purpose is to bring melanocytes into a calmer state before they are challenged. A dermatologist may prescribe a topical regimen built from the same pigment-modulating classes discussed earlier: a retinoid to normalize cell turnover, and an agent that slows melanin production. Starting these weeks ahead has a practical benefit, since it reveals whether your skin tolerates them without irritation, a useful preview of how it will handle the procedure. Which agents, and for how long, are decisions for the prescriber; this article describes the logic, not a protocol.
Strict sun protection begins now, not after. Skin that has recently tanned has activated melanocytes, and treating it invites uneven results.
Many practitioners perform a test spot at this stage: a small area, often behind the ear or at the jawline, treated with the intended settings and then observed for several weeks. If it heals cleanly, the full treatment proceeds. If it darkens, the parameters change or the method does.
You will typically be asked to pause exfoliating acids, scrubs and retinoids for a few days immediately before the session so the surface is not already compromised, and to arrive without makeup. If you have a history of cold sores, tell the team, because resurfacing can trigger an outbreak and they may want to plan for it. None of this is glamorous. All of it stacks the odds.
What the following days and weeks usually look like
Recovery depends on the method, but the pattern for pigment-safe approaches is short and manageable, precisely because the treatments are chosen to be shallow.
After microneedling or a superficial peel, expect redness, warmth and tightness on the day, easing over the next 1–3 days. Peeling or flaking often follows as the surface turns over. The Cleveland Clinic describes superficial peels as having minimal downtime with redness and flaking for a few days (see acne scars reference). Non-ablative fractional laser produces a similar picture, sometimes with a fine bronzed or gritty texture as treated columns shed over roughly a week.
Subcision leaves bruising and swelling that can be noticeable for a week or more; this is expected and reflects the mechanism, since the pooled blood is doing useful work. TCA CROSS leaves each treated pit with a small scab and, in darker skin, a dark ring that can take weeks to fade.
Collagen remodeling continues long after the skin looks normal. Improvement in texture is typically judged at several months rather than several weeks, and courses of several sessions are usually spaced weeks apart to let each round of remodeling progress (Mayo Clinic, acne scars). Photographs taken in the same light at each visit are more honest than memory.
Aftercare in darker skin is not optional. Gentle cleansing, a bland moisturizer, no picking at flakes or scabs, and diligent sun protection every day are the standard instructions. Hyperpigmentation that appears after treatment often shows up 1–3 weeks later rather than immediately, so the watchful period extends beyond the moment the redness settles.
Acne scars on Black skin: understanding keloid risk and where it matters
Keloids are raised scars that grow beyond the borders of the original wound, sometimes continuing to enlarge for months. MedlinePlus notes that they are more common in people with darker skin and tend to form on the chest, shoulders, upper back, jawline and earlobes. This matters for acne in two ways.
First, acne on the jaw, chest and back can itself leave keloids or hypertrophic scars, the latter being raised scars that stay within the wound’s edges. These need a different approach from depressed scars. Options MedlinePlus and the Mayo Clinic describe include corticosteroid injections into the scar to flatten it, silicone sheets or gels, pressure, cryotherapy, and in some cases laser to reduce redness. Aggressive resurfacing over a keloid-prone area risks provoking new raised scars, so a practitioner will usually avoid it.
Second, a personal history of keloids changes the risk calculation for any scar procedure on the face, even though facial skin forms keloids less often than the chest. Subcision, punch excision and deeper needling all create wounds. A careful team will start conservatively and observe how a small area heals before proceeding.
It bears saying plainly that there is no single best acne treatment for African American skin, or for any group defined by ancestry. Skin tone, oiliness, scar type and healing history vary enormously within any population. What is consistent is the principle: prevent new inflammation, protect against pigment triggers, and choose methods whose injury stays below the skin’s reactive threshold. The label on a chart does not treat anyone; the assessment does.
What people often get wrong about treating acne scars in deeper skin tones
“Lasers are off-limits for dark skin.” They are not off-limits; they are used with more constraints. Longer wavelengths, non-ablative fractional delivery, lower energy and test spots make light-based treatment possible. The myth pushes some people toward unregulated alternatives, which is the opposite of safer.
“The stronger the treatment, the better the result.” In melanin-rich skin, strength past a certain point buys pigment, not smoothness. Several gentle sessions usually outperform one intense one, and the intense one can leave marks that take longer to fade than the scars did.
“Dark marks are scars, so they need scar treatment.” Flat brown marks are pigment, and pigment responds to sun protection, time and topical agents. Resurfacing them can make them worse.
“Skin-lightening creams from a market stall will do the same job.” Unregulated products may contain potent steroids or mercury and have caused thinning, uneven whitening and systemic harm. Pigment-modulating creams belong under a prescriber’s supervision.
“Sunscreen is for fair skin.” Melanin offers some protection against burning, not against the ultraviolet stimulation that deepens existing marks. Daily sunscreen is arguably more relevant to pigment outcomes in darker skin, not less.
“If the redness has gone, I’m in the clear.” Post-treatment hyperpigmentation frequently appears a week or more after the visible healing ends. Protection continues well past the point where the skin looks normal.
“Filler is a quick fix.” Filler lifts what it sits under and does nothing for tethered or pitted scars. It is one tool within a plan, not a shortcut around one.
Questions to ask your care team before any acne scar procedure
A good consultation is a two-way conversation, and the questions you bring shape the plan you leave with. These are the ones that matter most when pigment risk is in play.
- Which of my marks are pigment, which are texture, and which types of scar do I have?
- How often do you treat skin of my tone, and can I see healed results in comparable skin, not just immediate post-treatment photos?
- Why this method rather than the alternatives, and what settings or depth will you use for my skin specifically?
- Will you do a test spot first, and how long will you observe it?
- What preparation do you want me to follow beforehand, for how long, and what should I stop before the session?
- What will you apply to my skin during and immediately after the procedure?
- What does normal healing look like for me, and what would you consider a warning sign?
- If I develop hyperpigmentation after treatment, what is the plan to manage it, and who do I contact?
- How many sessions do you anticipate, how far apart, and when would we judge whether it is working?
- What would make you advise against proceeding, either now or at all?
Notice what is missing from the list: any question about which machine is newest or which technique is trending. Those answers are marketing. The answers that protect you concern the practitioner’s experience with skin like yours, the reasoning behind their choices, and their plan for the outcome nobody wants. Write the answers down; the details are easy to lose in the moment.
When to call your doctor
Most recovery from pigment-safe scar treatments is uneventful: redness, tightness, flaking and, after subcision, bruising. A short list of signs falls outside that normal range and warrants prompt contact with the team that treated you, or urgent care if they are unavailable.
- Signs of infection: spreading redness, increasing rather than easing pain, warmth, swelling, yellow or green discharge, or a fever. Treated skin is an open door for bacteria for a few days.
- Blistering or weeping beyond what you were told to expect, or skin that looks white, gray or dusky, which can indicate a deeper injury than intended.
- Clusters of small painful blisters, particularly if you have a history of cold sores; a herpes outbreak across freshly treated skin needs quick attention.
- Patchy darkening or lightening appearing in the weeks after treatment. Early pigment change is often manageable; the sooner it is assessed, the more options remain.
- A raised, firm, itchy or growing scar at a treated site, which may signal hypertrophic or keloid formation.
- After filler: severe or worsening pain, skin that turns pale or blotchy purple, or any change in vision. These are rare but serious and require immediate medical attention.
- An allergic reaction: hives, swelling of the lips or eyes, or difficulty breathing, which needs emergency care.
Trust your own sense of what feels wrong. Practitioners would far rather hear about a concern that turns out to be normal healing than learn late about one that was not. Every decision about pausing, adjusting or continuing treatment rests with the clinicians who examined your skin, not with an article or a forum.
Frequently asked questions
What is the best treatment for dark acne scars?
There is no single best option; the right one depends on whether the mark is pigment or texture. Flat dark spots are treated with sun protection, prescription topical agents and time. Depressed scars in darker skin are usually addressed with microneedling, subcision, superficial peels, fillers or carefully set fractional lasers, chosen to minimize heat and inflammation. A dermatologist’s assessment decides the sequence.
What is the best acne treatment for African American skin?
Acne itself is treated with the same evidence-based classes regardless of ancestry: topical retinoids, benzoyl peroxide, antibiotics and, for severe cases, oral options prescribed by a clinician. The difference in darker skin is a stronger emphasis on preventing irritation and on controlling inflammation early, because each inflamed lesion can leave a long-lasting dark mark. Scar work waits until acne is quiet.
What is the best scar treatment for African American skin?
Practitioners generally favor methods that create controlled injury without much heat: microneedling, subcision for rolling scars, TCA CROSS for ice pick scars, and fillers for depressions. Non-ablative fractional lasers are used at conservative settings after a test spot. Raised or keloid scars need a different route, often steroid injections and silicone. Preparation with topical pigment control and strict sun protection is part of the treatment.
What is the hardest acne scar to get rid of?
Ice pick scars are widely regarded as the most stubborn depressed scars because they are narrow and deep, reaching below the level that surface-safe treatments can affect. They are usually treated individually with focused acid application or punch excision over several sessions. Extensive keloid scarring is arguably harder still, since the tools that help depressed scars can worsen raised ones. No method removes scars completely.
Is microneedling for dark skin safe?
Standard microneedling is considered one of the more pigment-friendly texture treatments because it injures mechanically without heat. It is not risk-free: excessive needle depth, too many passes, treating active acne or applying reactive products afterward can all provoke hyperpigmentation. Radiofrequency microneedling adds heat below the surface and requires more careful settings. Experience with deeper skin tones matters as much as the device.
Can you get a chemical peel for dark skin acne scars?
Yes, but the pattern is a series of superficial peels rather than a single medium or deep one. Low-strength glycolic, salicylic, lactic or mandelic acid peels help with pigment and surface texture while keeping inflammation low. They will not lift boxcar or rolling scars. Deep peels are generally avoided in darker skin because of the risk of uneven pigment change.
How long do dark spots from acne take to fade?
Post-inflammatory hyperpigmentation often improves over several months, and the Cleveland Clinic notes it can take considerably longer in deeper skin tones, sometimes a year or more, particularly without consistent sun protection. Prescription topical agents may speed fading, but the timeline varies widely between individuals. New sun exposure or new breakouts in the same area can prolong it.
Why do treatments cause acne scars on Black skin to darken instead of improve?
Melanocytes, the pigment cells, are more reactive in melanin-rich skin and respond to heat or inflammation by producing extra melanin. A treatment that is too hot, too deep or delivered to skin that is already inflamed can trigger this response, leaving a patch darker than the original scar. Conservative settings, weeks of preparation, a test spot and rigorous aftercare reduce that risk but cannot eliminate it.
Do lasers work for acne scars in darker skin?
They can, when chosen and set appropriately. Longer wavelengths are absorbed less by melanin, non-ablative fractional delivery limits surface damage, and lower energy with cooling reduces heat spread. The Mayo Clinic flags a higher risk of pigment change with laser resurfacing in darker skin, so many clinicians start with a test area. Results vary and multiple sessions are typical.
Should I treat my acne or my scars first?
Acne first. Active breakouts create new scars and keep the skin inflamed, which raises the chance that any scar treatment will provoke hyperpigmentation. Most dermatologists want several months without new inflammatory lesions before beginning scar work. Using that waiting period for sun protection and, where prescribed, topical pigment care often leaves the skin in a better state for the procedure.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Recovery After Retinal or Glaucoma Laser Treatment: Blurry Hours, Follow-Up and Milestones
After most retinal or glaucoma laser treatments, vision is blurry or dazzled for a few hours, mainly because of dilating drops, the bright treatment…

Flap or Graft? How Reconstructive Surgeons Choose Between the Two Ways to Rebuild Tissue
A skin graft is tissue detached completely from one site and laid onto a wound, where it must grow a new blood supply from…
Recovery After Xanthelasma Removal: Eyelid Swelling, Ointments and Stitch Care Week by Week
Xanthelasma surgery recovery usually follows a predictable arc: eyelid swelling and bruising peak in the first two to three days and largely settle within…

Realistic Results From Cellulite Treatment: Softer Texture, Not a Different Body
Realistic cellulite treatment results mean a softer, smoother skin texture and shallower dimples, not a different body and not permanent removal. Cellulite comes from…

Neck Laxity Surgery: Real Options for a Sagging Neck, From Lifts to Non-Surgical Care
Surgery for a sagging "turkey neck" usually means a neck lift (lower rhytidectomy), often combined with platysmaplasty to tighten the paired neck muscles, or…
Why Skin Grafts Sometimes Fail: Pressure, Infection, Smoking and the Signs Your Team Watches
Skin grafts fail most often because something separates the graft from the wound bed before new blood vessels can grow into it: a pocket…