

Blood Thinners, Prostate Medicines and Cataract Treatment: What Your Surgeon Checks First

Key Takeaways
- Routine cataract surgery is performed through a small incision in the cornea, a tissue with no blood vessels, which is the main reason bleeding risk is low even in people taking anticoagulants.
- The historic bleeding complications of eye anesthesia came from sharp-needle blocks behind the eye, and topical or sub-Tenon's techniques have largely removed that risk.
- Warfarin users may be asked for a pre-operative INR test to confirm the result sits in their usual target range, not to prove the medicine has been stopped.
- Alpha-blockers such as tamsulosin block the same receptor that drives the iris dilator muscle, causing intraoperative floppy iris syndrome, which surgeons manage with dilating agents, viscoelastic gels, iris hooks or expansion rings.
- Stopping tamsulosin for a few weeks does not reliably restore iris tone because the muscle changes persist long after the medicine is withdrawn, so disclosure matters far more than discontinuation.
- The NHS describes the operation as taking around 30 to 45 minutes with full healing over roughly 4 to 6 weeks, during which your regular medicines continue exactly as your prescriber directs.
Most people do not need to stop blood thinners for routine cataract surgery, because the operation uses a small incision and usually topical anesthetic, so bleeding risk is low; any change is decided by the prescribing clinician, never by the patient alone. Prostate alpha-blockers such as tamsulosin are different: they can make the iris floppy during surgery, so the surgeon needs to know in advance and plans around them.
The pre-assessment nurse slides a form across the desk and asks the question Ray has been dreading: what medicines do you take? He lists the one for his heart rhythm, the one for his prostate, and then hesitates. A neighbor told him he would have to come off the anticoagulant for a week. His cardiologist, when he rang, sounded faintly alarmed at the idea. Nobody has told him what the eye surgeon actually wants.
This is one of the most common tangles in eye clinics, and the confusion around cataract surgery blood thinners is understandable. Two very different kinds of medicine end up on the same form, and they matter to the surgeon for completely different reasons. One is about bleeding. The other is about a muscle inside the eye that most people have never heard of.
The good news is that the evidence here is unusually settled. The checklist is short, the logic is clear, and the decisions belong to the team who prescribed the medicines, not to a neighbor over the fence.
Why cataract surgery blood thinners questions come up at every pre-op visit
A cataract is a clouding of the eye’s natural lens, the clear disc behind the pupil that focuses light onto the back of the eye. Surgery replaces it with a plastic implant. It is one of the most frequently performed operations in medicine, and the people who need it are, on average, older. Older people also take more medicines. That overlap is the whole reason the pre-operative form exists.
Two groups of medicines earn a specific question from the surgical team. Blood thinners, which reduce the blood’s ability to clot, raise an obvious worry: will the eye bleed? Prostate medicines of the alpha-blocker type raise a less obvious one: will the iris, the colored ring that controls the pupil, behave itself during the operation? Neither question is a reason to panic, and neither is a reason to change anything on your own.
What the surgeon is really doing at this stage is sorting risk. The questions that matter most are: which exact medicine, why it was prescribed, how the eye will be numbed, and whether anything about this particular eye makes the operation harder. A person on an anticoagulant for a mechanical heart valve is not in the same situation as someone taking a low-dose antiplatelet for general heart protection. A person who has taken tamsulosin for years is not in the same situation as someone who started it last month. The form flattens these differences; the assessment restores them.
The thread running through this article is a single principle supported by mainstream guidance: for routine cataract surgery, stopping a blood thinner usually carries more risk than continuing it, and the final call always sits with the clinician who prescribed it. Everything else is detail.
What actually happens during modern cataract surgery
The technique used in almost all routine cases is phacoemulsification, a word worth defining once: an ultrasound probe breaks the cloudy lens into fragments that are suctioned out through a small incision at the edge of the cornea, the clear front window of the eye. A folded artificial lens is then slipped through the same opening and unfolds into place. According to the NHS, the operation usually takes 30 to 45 minutes and most people go home the same day.
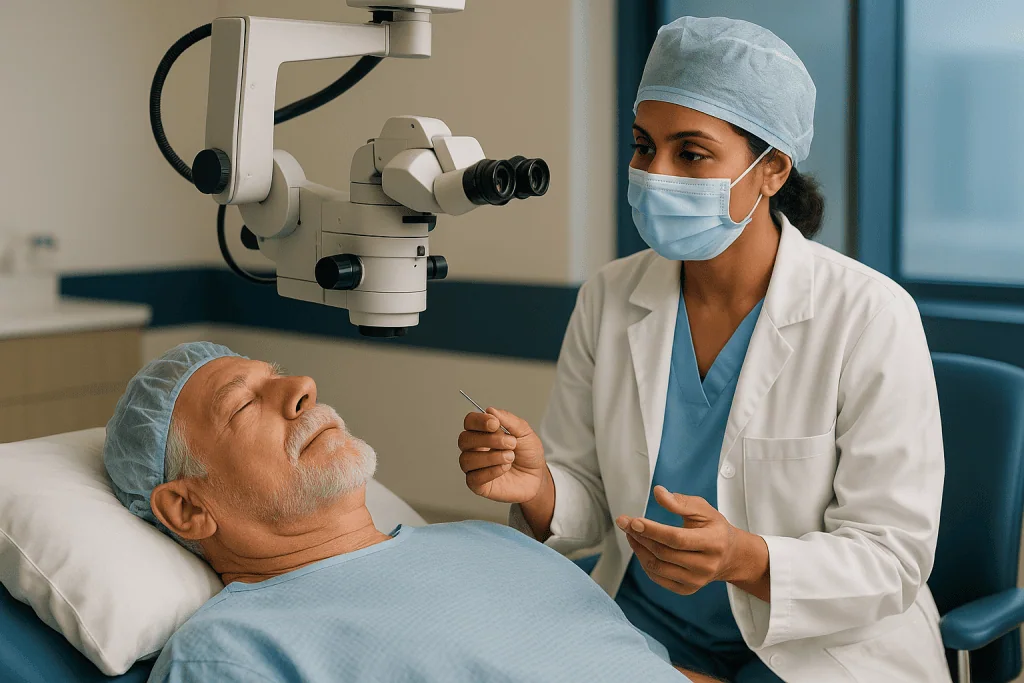
Three features of this procedure explain why bleeding is rarely the main concern. First, the incision is tiny and sits in the cornea, which has no blood vessels. Second, the work happens inside a closed, fluid-filled chamber at the front of the eye, well away from the blood-rich tissues at the back. Third, the eye is most often numbed with anesthetic drops or a gel applied to the surface, rather than with a needle pushed behind the eyeball. Each of those choices removes a place where bleeding could start.
You are usually awake. You will see light and movement and hear the surgeon talking, but the lens itself has no pain fibers, so the sensation is pressure rather than pain. A sedative is sometimes offered for anxiety. General anesthetic is reserved for people who cannot lie still or cooperate, which is uncommon.
At the end, the incision is usually self-sealing. A shield or pad goes over the eye, and you walk out. The entire experience is closer to a dental appointment than to what most people imagine when they hear the word surgery, and that modest scale is exactly why the medicine rules are more relaxed than for, say, a hip replacement.
Can you take blood thinners before cataract surgery?
In most cases, yes, and that is the direction mainstream guidance has moved. The phrase blood thinner covers two families that work differently. Anticoagulants slow the chemical cascade that forms a clot; this group includes warfarin and the newer direct oral anticoagulants such as apixaban, rivaroxaban, dabigatran and edoxaban. Antiplatelets stop platelets, the small cell fragments that plug damaged vessels, from clumping together; aspirin and clopidogrel are the familiar examples.
Both families are prescribed to prevent clots that cause strokes, heart attacks, deep vein thrombosis or blockages in artificial heart valves and stents. Interrupting them, even briefly, reopens that door. The whole risk calculation for cataract surgery therefore weighs a small chance of eye bleeding against a real chance of a clot elsewhere in the body. For an operation done through an avascular cornea under topical anesthetic, that balance generally favors continuing.
The Mayo Clinic’s patient guidance notes that a doctor may advise temporarily stopping medicines that increase bleeding risk, which reflects the honest reality: there are exceptions. Someone whose anticoagulation is poorly controlled, or who needs a needle block, or who is having a combined operation with another procedure on the eye, may be handled differently. The point is not that blood thinners are never adjusted. The point is that the decision is made jointly by the eye surgeon and the prescriber, based on your specific reason for taking the medicine.
What you should do is simple. Bring an accurate list, including anything bought over the counter, and tell the clinic why each medicine was prescribed. What you should not do is stop a tablet because a well-meaning relative had a different operation years ago. Those two actions sound similar; one keeps you safe and the other does not.
Warfarin and cataract surgery: the INR question
Warfarin is the oldest oral anticoagulant and the one that generates the most paperwork. It works by blocking vitamin K, which the liver needs to make several clotting proteins. Its effect varies with diet, other medicines and individual metabolism, so it is monitored with a blood test called the INR, the international normalized ratio, which measures how much longer than normal the blood takes to clot.

This variability is why warfarin gets special attention before an operation. The NHS advises that people on warfarin may need a blood test before cataract surgery. The purpose is not to prove that the warfarin has been stopped; it is to confirm that the INR sits inside the range your prescriber already aims for. A result within that target range is, for most surgeons, reassurance to proceed as normal.
A result above the target range is a different matter, and it is a matter for the anticoagulation clinic or prescribing doctor rather than the eye surgeon alone. Options may include rescheduling, or adjusting monitoring, but those are their decisions. A patient who takes it upon themselves to skip warfarin for several days to bring the number down has made a cardiac decision without a cardiologist, which is precisely the scenario the system is designed to avoid.
Two practical points help. First, tell the pre-assessment team how your warfarin is monitored and where your most recent result can be found; it saves repeat testing. Second, if your surgery date falls near a planned INR check, mention it, so the two can be coordinated. People with mechanical heart valves or a history of clots on treatment should expect their prescriber to be especially cautious about any interruption, and that caution is appropriate.
Newer anticoagulants and antiplatelets: what changes and what does not
The direct oral anticoagulants were designed to avoid warfarin’s unpredictability. They act on a single clotting protein, reach a steady effect within hours, and wear off within a day or two of the last dose rather than over the better part of a week. There is no routine blood test to monitor them, which puzzles some patients who expect an INR appointment before every procedure. The absence of a test is a feature of the medicine, not a gap in your care.
For routine cataract surgery under topical anesthetic, these medicines are usually continued. Where a prescriber does decide to pause one, the window is typically short because the drug clears quickly, but that is a judgment they make based on your kidney function, your clot risk and the type of anesthetic planned. Nothing about the general rule should be applied to you without that conversation.
Antiplatelet medicines sit at the low-risk end for eye surgery. Aspirin and clopidogrel are commonly continued, and anyone who has a coronary stent should be particularly wary of unsupervised interruption, because stent thrombosis is a serious event. Cardiology guidance from bodies such as the American Heart Association consistently stresses that stopping antiplatelet therapy after stenting should only happen with the cardiologist’s agreement.
What about the supplements people forget to mention? Fish oil, high-dose vitamin E, ginkgo and garlic preparations are often described as having mild antiplatelet effects. The evidence that they cause meaningful surgical bleeding is weak, but the surgical team would still rather know. The guiding habit is the same across every category: disclose everything, change nothing on your own, and let the people who know your heart and your eye talk to each other.
Why the anesthetic choice matters more than the tablet
If you want to understand the modern approach to anticoagulants in eye surgery, look at the anesthetic rather than the medicine. The bleeding complications that historically worried surgeons were almost never caused by the lens operation itself. They came from the needle used to numb the eye.
Older techniques, called retrobulbar and peribulbar blocks, place local anesthetic behind or beside the eyeball with a sharp needle. The space behind the eye is packed with blood vessels, and a vessel nicked in a person with reduced clotting can produce a retrobulbar hemorrhage, a bleed behind the eye that raises pressure and, in severe cases, threatens vision. That risk was the original reason some surgeons asked patients to stop anticoagulants.
Two developments changed the calculation. Topical anesthesia, meaning drops or gel on the surface, uses no needle at all. The sub-Tenon’s technique, in which a blunt cannula is slid under a thin membrane covering the white of the eye, avoids sharp penetration of the vessel-rich area. Both are widely used for routine cataract surgery, and both carry a far lower bleeding risk than sharp-needle blocks. Once the needle leaves the picture, the main argument for stopping the blood thinner leaves with it.
This is why the pre-assessment questions include how the eye will be numbed, and why a patient who is likely to need a sharp-needle block, perhaps because they cannot keep still or have unusual anatomy, might be handled differently from the standard pathway. Ask which technique is planned for you. The answer tells you more about your bleeding risk than the name of your anticoagulant does.
Tamsulosin and cataract surgery: why a prostate pill affects the eye
The second half of the form has nothing to do with bleeding. Alpha-blockers are medicines prescribed mainly for an enlarged prostate; they relax smooth muscle in the prostate and bladder neck so urine flows more easily. Tamsulosin is the best known, with alfuzosin, doxazosin, terazosin and silodosin in the same family. They are also prescribed to some women for urinary retention and to help pass kidney stones, which is why the question is asked of everyone.
The connection to cataract surgery is anatomical. The iris contains a thin dilator muscle that widens the pupil, and that muscle is driven by the same type of alpha receptor the prostate medicine blocks. Tamsulosin is especially selective for this receptor subtype, which is why the Mayo Clinic’s pre-operative guidance specifically tells patients to mention prostate medicines because they can interfere with the operation.
During surgery the consequences are threefold. The pupil may not dilate as widely as expected despite the usual drops. The iris, deprived of muscle tone, can billow and ripple like a sheet in the wind as fluid moves through the eye. And the pupil may progressively constrict during the operation, narrowing the surgeon’s working space just when it is needed most.
None of this makes surgery impossible. It makes it technically more demanding, and the difference between a smooth case and a difficult one is often simply whether the surgeon knew in advance. The dilator muscle appears to undergo lasting change after prolonged exposure, so even people who stopped the medicine years ago should mention it. Think of it as information the surgeon needs rather than a problem you need to fix.
What is intraoperative floppy iris syndrome and how do surgeons manage it?
The pattern described above has a name: intraoperative floppy iris syndrome, usually shortened to IFIS. It was first linked to tamsulosin in the mid-2000s, when surgeons noticed the same unusual iris behavior in a cluster of patients who shared a prescription. The syndrome is now well recognized, and planning for it is routine in cataract practice.
Why does a floppy iris matter? Phacoemulsification relies on a wide, stable pupil so the probe can reach the lens without touching the iris. An iris that drifts toward the incision can be caught by instruments or sucked toward the probe, risking tears, pigment loss and a distorted pupil afterward. A pupil that constricts mid-operation can hide the edge of the lens capsule, raising the chance of a capsule tear, which in turn can complicate placement of the implant.
Surgeons have a well-stocked toolkit for this. A dilating medicine can be injected directly into the front chamber of the eye at the start of the case to stiffen the iris. Thicker, more cohesive viscoelastic gels, the clear substances used to hold space open inside the eye, help keep the iris pushed back. Small mechanical devices can be deployed: flexible hooks placed through tiny side incisions to hold the pupil open, or a ring that expands the pupil to a fixed diameter for the duration of the case. Adjusting fluid flow and the position of incisions also reduces the chance of iris prolapse.
Each of these is a decision made during the operation, not something you need to request. Your single contribution is accurate disclosure. In clinics where the question is asked systematically and the answer is recorded, IFIS has become a manageable variable rather than a surprise.
Should you stop a prostate medicine before cataract surgery?
The intuitive answer is to stop the tablet for a while and let the iris recover. The evidence does not support that intuition. Alpha-blocker exposure appears to produce changes in the iris dilator muscle that persist long after the medicine is withdrawn; floppy iris behavior has been reported in people who stopped tamsulosin months or even years earlier. Pausing the medicine for a few weeks therefore does not reliably restore normal iris function, and it does cost something: the urinary symptoms that led to the prescription typically return.
Guidance from major eye and urology bodies reflects this. Routine discontinuation before cataract surgery is not generally recommended. The emphasis instead falls on communication: tell the surgeon, and the surgeon prepares. Some surgeons do prefer a short pause in specific circumstances, and some prescribers will consider whether an alternative medicine suits a patient who is known to need cataract surgery in the near future. Those are individual judgments, made by the people involved in your care.
A related question concerns timing of the prescription itself. Where a person is awaiting cataract surgery and has not yet started an alpha-blocker, some clinicians prefer to sequence the eye operation first, because the medicine is easier to add after the iris no longer matters surgically. That is a conversation for the urologist or family doctor, and it only applies when both conditions are being managed at once.
What about the other prostate medicines? The 5-alpha-reductase inhibitors, such as finasteride and dutasteride, shrink the prostate through a hormonal route and are not associated with floppy iris in the same way. Some herbal products marketed for prostate health have been reported alongside IFIS, so they belong on the list too. The rule holds: disclose, do not self-adjust.
Who is usually a straightforward case, and who is asked to wait
Most people on blood thinners or alpha-blockers proceed on a standard pathway. A straightforward candidate typically has a cataract that affects daily life, an eye without other significant disease, an anticoagulant that is well controlled for its purpose, and a plan for topical or sub-Tenon’s anesthesia. For such a person the medicines are noted, the surgeon prepares, and the day goes ahead much like anyone else’s.
Some situations prompt a pause, and it helps to know which ones.
- An INR well above the target range on the pre-operative test, which is referred back to the anticoagulation clinic rather than being resolved on the day.
- A recent cardiac event, stroke or stent placement, where cardiology teams often prefer a period of uninterrupted therapy before any elective procedure is scheduled.
- Active eye disease such as uncontrolled glaucoma, a recent retinal problem or an eye infection, each of which generally needs to settle first.
- Poorly controlled diabetes, because high blood sugar affects healing and infection risk and often leads to a rescheduled date rather than cancellation.
- An inability to lie flat or keep still, which may change the anesthetic plan and therefore the bleeding calculation.
Waiting is not a judgment on you. Cataract surgery is elective, meaning it can be timed, and a short delay to bring another condition under control usually costs little in sight while removing avoidable risk. The NHS lists discussion of your general health and medicines as a standard part of pre-assessment precisely so that these decisions are made before, not on, the day.
Where two specialists disagree, for instance a surgeon who would prefer a pause and a cardiologist who would not, the resolution is a conversation between them, with you informed of the reasoning. You should never be the messenger carrying competing instructions.
Blood thinners, prostate medicines and other items on the surgeon's checklist
Seeing the medicines side by side makes the logic clearer. The table summarizes what each group does, why it matters in the operating room and what the usual approach looks like. Every row ends in the same place: the plan is set by your clinicians, not by a general rule.
| Medicine group | What it does | Why the surgeon asks | Usual approach in routine cataract surgery |
|---|---|---|---|
| Warfarin | Blocks vitamin K-dependent clotting factors | Variable effect; bleeding risk if INR is high | Pre-operative INR check; usually continued if within target range |
| Direct oral anticoagulants | Block a single clotting protein; wear off within days | Bleeding risk, mainly with needle blocks | Usually continued; any pause decided by prescriber |
| Antiplatelets (aspirin, clopidogrel) | Stop platelets clumping | Low eye-bleeding risk; high clot risk if stopped after stents | Usually continued |
| Alpha-blockers (tamsulosin and related) | Relax smooth muscle, including the iris dilator | Floppy iris and poor dilation | Continued; surgeon plans with dilating agents, hooks or rings |
| 5-alpha-reductase inhibitors | Shrink prostate hormonally | Not clearly linked to floppy iris | Noted; no specific change |
| Herbal prostate products | Varied, poorly standardized | Reports alongside floppy iris | Disclose; noted in surgical plan |
The remaining checklist items are less dramatic but just as routine. Diabetes medicines matter because fasting instructions, if any, affect blood sugar. Steroid tablets and immune-suppressing medicines affect healing and infection risk. Allergies to iodine-based antiseptic or to latex change what is used in theater. Previous eye surgery, a high glasses prescription or a history of eye inflammation all shape the surgical plan.
Notice what the table does not contain: any instruction to stop. That absence is the message.
What the days and weeks after cataract surgery usually look like
Recovery is quick for most people, though the eye does not read the leaflet. The NHS notes that vision is often noticeably improved within a few days, while full healing takes around 4 to 6 weeks; MedlinePlus similarly describes most people being able to return to everyday activities within a few days. Grittiness, mild aching, watering and a sensitivity to light are common in the first few days and usually fade. Some people see a halo around lights or notice colors appear brighter, which reflects the removal of a yellowed lens rather than a problem.
Drops are the main task. Anti-inflammatory and often antibiotic drops are prescribed for a set period, and the schedule the clinic gives you is the one to follow. If you take a blood thinner, nothing about the drops interacts with it, and you continue your tablets exactly as your prescriber directed. If a pause was agreed, the instruction about when to restart will have come from the prescriber, and that is the moment to confirm it rather than guess.
A clear shield over the eye at night for the first week or so, avoiding rubbing, and keeping soap and water out of the eye are standard advice. Heavy lifting and swimming are usually deferred for a few weeks. Reading, television, walking and light housework are generally fine from the first day, and most people are told they may fly once the surgeon is satisfied at the first check.
For those who took an alpha-blocker, the surgeon will have noted whether the iris behaved unusually. If a pupil-expansion device was used, the pupil may look slightly irregular for a while, and the follow-up appointment is where that is reviewed. The second eye, if it needs surgery, is planned once the first has settled, and the same medicine information carries forward.
What people often get wrong about cataract surgery and their medicines
The myths here are persistent because they were once partly true. Separating what has changed from what never applied saves a great deal of worry.
Myth one: you must stop blood thinners before any surgery. That rule grew up around operations with large incisions, deep tissue and needle anesthesia. Cataract surgery through an avascular cornea under drops does not fit the template, and mainstream guidance now leans toward continuing. The exceptions exist, but they are identified by your clinicians, not assumed by you.
Myth two: a quick break from the tablet is harmless. Anticoagulants and antiplatelets are prescribed because the body is primed to clot. The days off treatment are precisely when a stroke, a stent blockage or a leg clot can occur. The eye operation lasts less than an hour; the consequences of an unplanned interruption can be permanent.
Myth three: stopping tamsulosin for a few weeks will fix the floppy iris. Evidence suggests the iris changes persist long after withdrawal, so the pause brings back urinary symptoms without reliably restoring iris tone. Disclosure, not discontinuation, is what helps the surgeon.
Myth four: only men need to answer the prostate question. Alpha-blockers are also prescribed to women for bladder problems and to anyone passing a kidney stone, which is why the clinic asks everybody.
Myth five: if the surgeon did not mention it, it did not matter. Pre-assessment forms are efficient but blunt. A medicine started between the assessment and the operation, a supplement bought over the counter, or a medicine stopped years ago can all be missed. Volunteering the information is never an imposition.
The common error beneath all five is treating a general principle as a personal instruction. Medicine rules are written for populations; your plan is written for you.
Questions to ask your care team before cataract surgery
A short, specific list of questions does more than a long anxious one. These are the ones that tend to change the plan or settle the mind.
- Which anesthetic technique is planned for me: drops, sub-Tenon’s or a needle block? This single answer frames the bleeding discussion.
- Do you want me to continue my anticoagulant or antiplatelet exactly as usual, and has that been agreed with the doctor who prescribes it?
- If I take warfarin, do I need an INR test before the operation, and who will act on the result?
- I take, or have taken, a prostate or bladder medicine; is it on my surgical record, and do you plan to use any pupil-support measures?
- Are there any supplements, eye drops or over-the-counter products you would prefer I pause, and who makes that decision?
- Which of my other conditions, such as diabetes or glaucoma, might affect the timing of my operation?
- After surgery, is there any change to how I take my regular medicines, and when do I restart anything that was paused?
- What signs after the operation should prompt me to call, and which number do I use out of hours?
Bring the answers home in writing, or ask that they be added to your discharge sheet. People leaving pre-assessment often recall the instructions about drops and forget the ones about tablets, because the drops are new and the tablets are familiar. If two clinicians have given you different advice about the same medicine, say so plainly and ask them to resolve it between themselves. That is not being difficult; it is how a safe system is supposed to work, and good teams welcome it.
When to call your doctor after cataract surgery
Most recovery is quiet, which makes the exceptions easier to spot. Two groups of warning signs matter here: those relating to the eye, and those relating to the medicines you take for other reasons.
Contact the eye clinic the same day, or use the emergency number you were given, if you notice any of the following in the operated eye. Vision that was improving and then gets worse. Pain that increases rather than settles, particularly if it comes with nausea or vomiting, which can indicate raised pressure inside the eye. Redness that spreads or deepens over hours. Sticky discharge or swelling of the lids. A sudden shower of new floaters, flashes of light, or a shadow or curtain across part of your vision, which can signal a problem at the back of the eye and needs prompt assessment. Infection inside the eye after cataract surgery is uncommon but serious, and the NHS lists worsening pain, redness and vision loss among the symptoms that need urgent review.
If you take a blood thinner, two further scenarios deserve attention. Bleeding that seems out of proportion, such as a rapidly expanding dark patch on the white of the eye with pain, should be reported. More important, if your anticoagulant was paused and you develop sudden weakness or numbness on one side, difficulty speaking, a drooping face, chest pain, breathlessness, or a painful swollen calf, treat it as an emergency and call the emergency services; these can be signs of stroke, heart attack or a clot, and the eye operation becomes irrelevant beside them.
A person on an alpha-blocker who notices the pupil of the operated eye looks a different shape should mention it at follow-up; it is rarely urgent but worth recording. When in doubt, call. Eye units would far rather hear about a false alarm than miss a real one, and the treating team is the right place for every decision about what happens next.
Frequently asked questions
Can you take blood thinners before cataract surgery?
Usually yes. Because routine cataract surgery uses a small corneal incision and most often anesthetic drops rather than a needle, mainstream guidance leans toward continuing anticoagulants and antiplatelets. Exceptions exist, for example a very high INR on warfarin or a planned sharp-needle block, but any change is decided jointly by the eye surgeon and the doctor who prescribed the medicine. Never pause a blood thinner on your own initiative.
What is the connection between tamsulosin and cataract surgery?
Tamsulosin blocks alpha receptors to relax prostate and bladder muscle, and the iris dilator muscle uses the same receptor type. During surgery the pupil may dilate poorly, the iris can billow toward the incision and the pupil may constrict mid-operation. This pattern is called intraoperative floppy iris syndrome. Surgeons who know in advance plan around it with dilating agents and small pupil-support devices, which is why disclosure matters.
Is intraoperative floppy iris syndrome dangerous?
It is a manageable surgical challenge rather than a danger in itself. The risk comes when it is unexpected, because a floppy iris can be caught by instruments or a shrinking pupil can hide the lens capsule, raising the chance of complications. When the surgeon is warned, pupil-expansion rings, iris hooks, specific gels and dilating medicines injected into the eye keep the working space stable, and most operations proceed routinely.
What happens with warfarin and cataract surgery?
People on warfarin are often asked for an INR blood test before the operation, as the NHS notes. If the result sits within the target range set by the anticoagulation clinic, surgery usually goes ahead with warfarin continued. A result above range is referred back to the prescriber, who may reschedule or adjust monitoring. Patients should not skip doses to lower the number themselves.
Should I stop my prostate medicine before cataract surgery?
Routine discontinuation is not generally recommended. Evidence suggests alpha-blockers cause lasting changes in the iris dilator muscle, so a short pause does not reliably restore normal iris behavior but does bring back urinary symptoms. Some surgeons or prescribers make individual exceptions, and that is their call. Your task is to make sure the medicine, including any you stopped years ago, is on the surgical record.
Do women need to answer the prostate medicine question?
Yes. Alpha-blockers such as tamsulosin are also prescribed to women for urinary retention and to anyone passing a kidney stone, and the effect on the iris is the same regardless of why the medicine was taken. Clinics ask everybody for this reason. Herbal products marketed for urinary health have also been reported alongside floppy iris, so they belong on your list too.
Does the type of eye anesthetic change the blood thinner decision?
It is often the deciding factor. Sharp-needle blocks placed behind or beside the eyeball pass through vessel-rich tissue and can cause bleeding behind the eye in people with reduced clotting. Topical drops and the blunt-cannula sub-Tenon’s technique avoid that area, which is why anticoagulants are usually continued for routine cases. Asking which technique is planned tells you more about your bleeding risk than the name of your tablet.
What about aspirin or clopidogrel after a heart stent?
These antiplatelet medicines are usually continued through cataract surgery because the eye-bleeding risk is low and the risk of a stent blockage if they are stopped is serious. Cardiology guidance from bodies such as the American Heart Association stresses that interruption after stenting should happen only with the cardiologist’s agreement. If an eye clinic suggests a pause, ask that it be discussed directly with your cardiology team first.
How long does recovery from cataract surgery take?
The NHS describes vision improving within a few days and full healing over roughly 4 to 6 weeks, with most everyday activities resuming quickly. Drops are used for a set period, a shield protects the eye at night in the first week or so, and heavy lifting and swimming are deferred. Your regular medicines, including blood thinners, continue exactly as the prescriber directed unless a specific restart instruction was given.
What warning signs after cataract surgery need an urgent call?
Worsening rather than improving vision, increasing pain especially with nausea, spreading redness, discharge, or new flashes, floaters or a shadow across your sight all need same-day contact with the eye clinic. If a blood thinner was paused and you develop one-sided weakness, slurred speech, chest pain, breathlessness or a swollen painful calf, call emergency services immediately, as these can signal a stroke, heart attack or clot.
References
- NHS: Cataract surgery
- NHS: Cataract surgery, recovery
- MedlinePlus: Cataract removal
- National Eye Institute (NIH): Cataract surgery
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Eye Angiography Is Done: Dilating Drops, the Dye Injection and the Photo Sequence
Eye angiography is done in three stages. First, drops widen the pupils so the camera can see the back of the eye. Next, a…

What Makes Super LASIK Personalized: Wavefront Maps and Custom Corneal Reshaping
Super LASIK is a marketing label some providers use for wavefront-guided LASIK. An instrument called an aberrometer measures how light is distorted as it…

How Long Does LASIK Take? The Flap, the Laser Seconds and the Waiting Room Before
LASIK usually takes about 30 minutes or less for both eyes, and the excimer laser reshapes each cornea in well under a minute. Most…

Astigmatism That Is Not Simple: Why Irregular Corneas Are Treated Differently
Irregular astigmatism happens when the cornea is warped unevenly, most often from keratoconus, scarring, or earlier eye surgery, so ordinary glasses cannot fully sharpen…
LASIK Complications Explained Honestly: Flap Problems, Dry Eye and Night Vision Changes
LASIK complications are uncommon but real. The most frequent are dry eye, which often improves over several months, and night-vision changes such as glare…

Dryness, Glare and Blurry Days After ILASIK: What Is Normal and When to Call
Dry, gritty eyes, glare or halos around lights at night, and vision that shifts through the day are common ILASIK side effects, and they…