

Can Manual Therapy Help Back and Neck Pain? When Hands-On Care Fits the Treatment Plan
Key Takeaways
- Systematic reviews summarized by the NIH find that spinal manipulation gives small, mostly short-term improvements in nonspecific low back pain, roughly comparable to exercise or usual care rather than superior to them.
- UK national guidance and the NHS recommend manual therapy only as part of a package that includes exercise, never as a standalone treatment for back pain.
- The audible pop during manipulation is cavitation, gas released from joint fluid, not a bone returning to place, and it is not required for relief.
- Mobilization (slow, low-velocity movement) carries fewer specific risks than manipulation, and no evidence shows the thrust technique is reliably better for nonspecific back or neck pain.
- The Mayo Clinic lists severe osteoporosis, limb numbness or weakness, spinal cancer, elevated stroke risk and upper-neck bone abnormalities as reasons not to have spinal manipulation.
- According to the NHS, most episodes of back and neck pain improve within a few weeks, and staying active shortens recovery while prolonged bed rest lengthens it.
Manual therapy for back pain, hands-on mobilization or manipulation of the spine by a trained clinician, can modestly ease pain and stiffness for some people with nonspecific low back or neck pain, mainly in the short term. Guidelines support it only as part of a plan that includes exercise and staying active, not as a standalone treatment. Your treating team decides whether it fits your situation.
The moment usually arrives somewhere ordinary. Reaching into the back seat for a bag. Straightening up from the dishwasher. Turning to check a blind spot and finding that the neck simply will not go there. What follows is a small negotiation with the body: shallow breaths, a careful shuffle to a chair, and the question that sends millions of people to a search bar every year, do I need someone to work on this?
Manual therapy for back pain sits in an odd position. Almost everyone has an opinion about it. A neighbor swears by the clinician who put their back right in one visit; a colleague says it did nothing. Both stories can be true, and neither settles the matter.
What the research actually supports is more measured than either camp likes to hear. Hands-on care can help, for the right person, at the right point, alongside the right movement plan. Here is how to tell whether that describes you.
What is manual therapy for back pain, and what actually happens on the table?
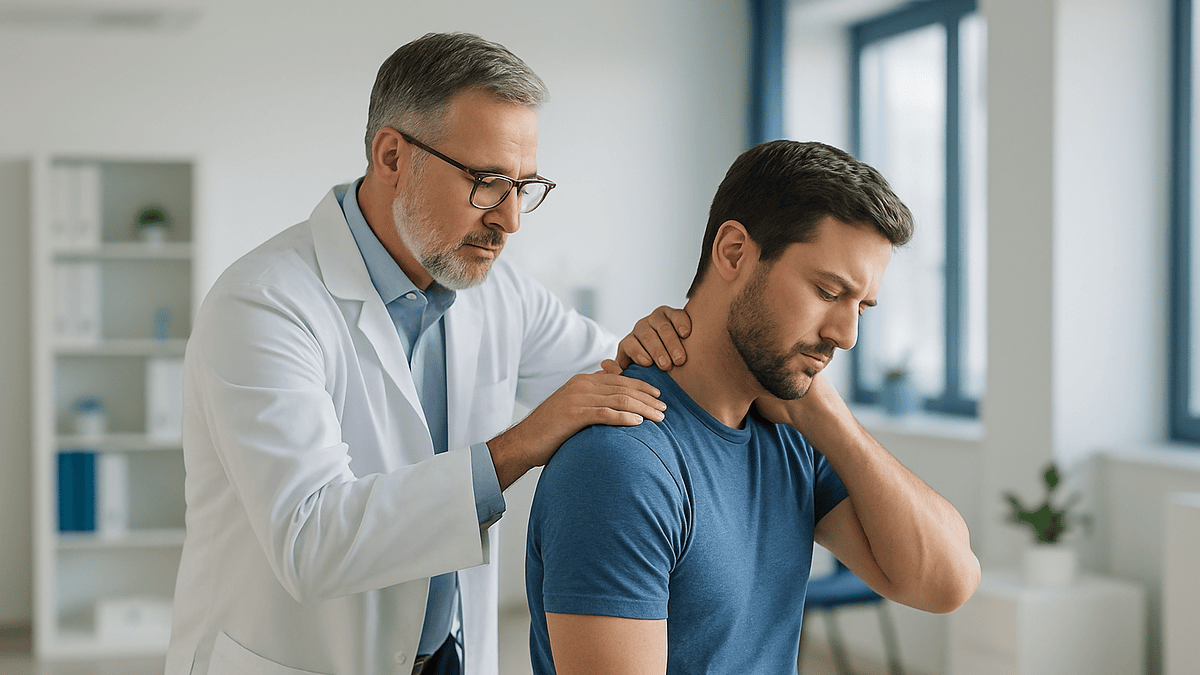
Manual therapy is a group of hands-on techniques in which a clinician, most often a physical therapist, osteopath or chiropractor, uses their hands to move joints and soft tissue. The word covers a spectrum, from slow, rhythmic pressure on a stiff segment of the spine to the quick, controlled thrust most people picture when they hear the phrase.
A typical session for low back pain looks less dramatic than the internet suggests. You lie on a padded table, sometimes face down, sometimes on your side with one knee bent. The clinician finds the level of the spine that feels stiff or tender, then applies graded pressure with the heel of the hand or the thumbs. The pressure builds and eases in slow cycles, a little like kneading dough. Nearby muscles may be stretched or pressed. Only some sessions include a manipulation, and only if the clinician judges it appropriate and you agree to it.
Why would pressing on a joint change how it feels? Several mechanisms are proposed, and none is fully proven. Movement may temporarily restore the normal glide of a stiff facet jointthe small paired joints at the back of each vertebra. Firm, rhythmic input may dampen the nervous system’s pain signaling for a period, in the same way rubbing a bumped shin makes it hurt less. Muscle tone around the sore segment may relax. And the simple experience of being examined, reassured and moved without harm can lower the guarding that keeps a back rigid.
The National Institutes of Health describes spinal manipulation as generally safe when performed by a trained, licensed professional, while noting the evidence for its benefit is modest and variable. That honest framing, helpful for some, transformative for few, is the right place to start.
Spinal mobilization vs manipulation: what is the difference?
Two words get used interchangeably in waiting rooms, and they should not be. Mobilization is slow, repeated, low-velocity movement of a joint that stays within your control; you could stop it at any point. Manipulation is a single high-velocity, low-amplitude thrust that takes a joint briefly to the end of its range. The audible pop that sometimes follows is called cavitation, a release of gas from the joint fluid. It sounds decisive. It is not a sign that anything has been put back into place.

The distinction matters for three reasons. First, comfort: many people prefer the gentler approach, and there is no evidence that the thrust technique is reliably superior for nonspecific back pain. Second, safety: manipulation of the neck carries a small set of specific risks that mobilization does not, discussed later in this article. Third, consent: you can ask for one and not the other, and a good clinician will explain which they plan to use before their hands are on you.
Both approaches share the same basic idea, moving a joint that has stopped moving well, and both are usually combined with soft-tissue work on the surrounding muscles. Neither is a substitute for the active part of recovery.
The Mayo Clinic’s overview of chiropractic adjustment describes manipulation as the application of a controlled, sudden force to a joint, and lists the common short-lived effects afterward: mild soreness, fatigue and a temporary headache. Those effects usually settle within a day or two, according to that same source. If you are offered manipulation and feel unsure, saying so is not awkward; it is exactly the conversation that should happen.
Does manual therapy work? What the evidence actually shows
The most useful answer is a graded one. For acute or subacute nonspecific low back pain, pain without a specific structural cause, lasting under about twelve weeks, systematic reviews summarized by the NIH’s National Center for Complementary and Integrative Health find that spinal manipulation produces small improvements in pain and function, roughly comparable to other commonly recommended treatments such as exercise or standard medical care. It does not appear clearly better than those alternatives; it appears to be one reasonable option among them.
For chronic low back pain, lasting longer than twelve weeks, the picture is similar: small to moderate short-term benefit, more uncertainty about whether that benefit lasts, and a consistent finding that adding manual therapy to an exercise program tends to help more than manual therapy alone.
Several things are genuinely unknown. Researchers cannot yet predict which individuals will respond well. The quality of many trials is limited by small numbers and the difficulty of designing a convincing placebo for a hands-on treatment. And the effect sizes, while real, are modest, meaningful relief for some, little change for others.
This is why major guidelines land where they do. UK national guidance on low back pain recommends considering manual therapy only as part of a treatment package that includes exercise, with or without psychological support, and not as a standalone treatment. The NHS’s patient guidance echoes this, listing manual therapy among options a specialist may offer alongside exercise and staying active.
So the honest reading is not that manual therapy is a myth, and not that it is a key that unlocks the spine. It is a supporting player with a modest, real, mostly short-term contribution, valuable when it helps you move, less valuable when it becomes the whole plan.
Manual therapy for neck pain: is the picture different?
Neck pain follows many of the same rules as back pain, with two important differences. The first is anatomy: the vertebral arteries, which supply blood to the back of the brain, run through small openings in the neck vertebrae. This is why manipulation of the neck, as opposed to gentle mobilization, has been linked in rare case reports to arterial injury and stroke. The Mayo Clinic notes this as a rare but serious complication of neck manipulation. Whether the association is causal or reflects people seeking care for neck pain that was itself an early symptom of arterial dissection remains debated. The risk is small in absolute terms; it is not zero.

The second difference is how commonly neck pain settles on its own. The NHS advises that most neck pain improves within a few weeks with gentle movement, staying active and simple pain relief if needed. Hands-on care is one of several options for people whose pain lingers or who are struggling to move.
What does the evidence say? Reviews summarized by the NIH suggest that mobilization and manipulation may offer short-term relief for mechanical neck pain and that combining them with exercise appears more useful than either alone: a pattern strikingly similar to the low back findings. There is no clear evidence that the thrust technique outperforms slower mobilization for the neck, which is a reasonable argument for choosing the gentler approach when both are on the table.
If your neck pain arrived after a car collision, a fall or a sports impact, or comes with dizziness, visual disturbance, slurred speech or difficulty swallowing, those are reasons to be assessed medically before anyone applies force to the neck. A clinician should screen for these before treating.
Why hands-on care is paired with exercise, never used alone
Think of the spine as a set of joints held in balance by muscles that have to work all day. A stiff joint can be moved by someone else’s hands, but the muscles that keep it moving well tomorrow are yours. That, in plain terms, is why every mainstream guideline pairs manual therapy with active rehabilitation.
There is a practical logic too. Pain makes people move less, and moving less makes the back stiffer, weaker and more sensitive. Manual therapy can interrupt that spiral by reducing pain enough to make movement tolerable: a window, not a destination. Exercise in that window builds the strength, endurance and confidence that keep the spiral from restarting.
The evidence supports this sequencing. Trials comparing manual therapy plus exercise against manual therapy alone tend to favor the combination for both pain and function over the following weeks and months. The Mayo Clinic’s guidance on back pain treatment describes physical therapy as centered on exercises to increase flexibility, strengthen back and abdominal muscles and improve posture, with hands-on components as an adjunct.
What does the exercise part look like? Usually not heroic. Gentle range-of-motion movements early on, then progressive strengthening of the trunk, hips and legs, then a return to walking, lifting and the activities that matter to you. The clinician’s hands help you get started; the program keeps you going.
One further point matters more than most people realize. If a course of hands-on care is not moving you toward doing more for yourself, the plan needs revisiting. Relief that depends entirely on returning to the table indefinitely is a sign the balance has tipped in the wrong direction.
Who manual therapy for back pain is usually for, and who is usually asked to wait
The people most likely to be offered hands-on care share a few features. Their pain is nonspecific, meaning a clinician has assessed them and found no sign of a serious underlying cause. They have stiffness or restricted movement that is limiting daily life. They are willing to combine sessions with exercise. And, often, their pain has persisted beyond the first couple of weeks, when the natural tendency of back pain to settle has not quite delivered.
Sciaticapain running down the leg from an irritated spinal nerve, does not automatically rule manual therapy out, but it changes the approach, and clinicians tend to be more cautious with thrust techniques when nerve symptoms are present.
Some people are usually asked to wait, or steered toward other options first. According to the Mayo Clinic, chiropractic adjustment should not be performed in the presence of severe osteoporosis (fragile, thinning bones), numbness or tingling or loss of strength in an arm or leg, cancer affecting the spine, an increased risk of stroke, or a known bone abnormality in the upper neck. Recent spinal fracture or surgery, active infection, inflammatory arthritis flaring in the spine and pregnancy are other situations where the treating team will weigh the approach individually.
None of this is a judgment about the person; it is a judgment about mechanics and risk. Bone that is fragile does not tolerate force well. A nerve that is already compressed does not need more compression. In each of these cases the right move is assessment first, and a decision about hands-on care made by the team that knows your history.
If you are unsure which group you fall into, that is precisely what the initial assessment is for.
Hands-on physical therapy techniques: what to expect at a first appointment
A first visit for back or neck pain begins with talking, not touching. Expect questions about when the pain started, what makes it better or worse, whether it travels into a limb, how you are sleeping and what you have already tried. The clinician will also screen for the warning signs that would redirect you to a doctor, which are covered in the final section of this article.
Then comes the physical examination. You will be asked to bend, twist and straighten while the clinician watches how you move and where movement stops. They may test reflexes, sensation and strength in your legs or arms. They will press along the spine to find tender or stiff segments. Imaging is not usually needed for nonspecific back pain; the NHS and Mayo Clinic both note that scans rarely change treatment in the absence of red flags.
Hands-on treatment, if it happens on day one, is usually brief and gentle. Common techniques include:
- Joint mobilization, slow, oscillating pressure applied to a specific spinal level.
- Soft-tissue release, sustained pressure or gliding strokes on tight muscles around the spine and hips.
- Muscle energy techniques: you push gently against the clinician’s resistance, then relax while they take the joint a little further.
- Manipulation: a quick thrust, offered only when appropriate and with your agreement.
You should leave with at least one or two movements to practice at home and a rough sense of how many sessions are proposed and why. Most treatment plans for uncomplicated back pain run for a limited course of weeks, with progress reviewed as you go rather than a fixed number booked in advance. If the plan feels open-ended, ask what the endpoint looks like.
How manual therapy compares with other back pain treatments
The table below puts hands-on care next to the other approaches guidelines commonly discuss for nonspecific back and neck pain. It is a summary of direction and role, not a ranking; the right mix depends on the person and is set by the treating team.
| Approach | What it involves | What mainstream evidence broadly shows | Usual role |
|---|---|---|---|
| Staying active and self-care | Continuing normal activity as tolerated, heat, gentle movement | Consistently recommended; most acute episodes improve within weeks (NHS, Mayo Clinic) | Foundation for everyone |
| Structured exercise | Supervised or home programs building strength, flexibility and endurance | Moderate benefit for pain and function, especially in persistent pain | Core of most plans |
| Manual therapy | Mobilization, manipulation, soft-tissue work | Small to moderate short-term benefit; best evidence when combined with exercise (NIH) | Adjunct within a package |
| Pain-relief medicines | Anti-inflammatory class most commonly discussed; decisions rest with the prescriber | Short-term relief for some; do not change the underlying course | Time-limited support, if advised |
| Psychological approaches | Cognitive behavioral strategies for pain, often within a combined program | Helpful for persistent pain affecting daily life | Considered when pain becomes long-standing |
| Injections and surgery | Targeted procedures for specific structural problems | Not recommended for nonspecific back pain; reserved for defined indications | Specialist decision only |
Two patterns stand out. First, the approaches with the strongest support are the least glamorous: keep moving, build strength, give it time. Second, manual therapy earns its place by making those approaches easier, not by replacing them. The Mayo Clinic lists physical therapy and, for some people, alternative approaches including spinal manipulation among reasonable options after self-care, while emphasizing that most back pain improves with home treatment.
What the following days and weeks usually look like after hands-on treatment
The first evening after a session is often the most surprising. Some people feel looser immediately and move more freely. Others notice a dull, workout-like ache around the treated area that lasts into the next day. Both responses are common, and the Mayo Clinic notes that soreness, tiredness or a mild headache after manipulation typically resolve within a day or two.
Over the first week, the goal is to use whatever relief you have. That means walking, doing the home exercises you were given, and returning to normal activities as tolerated rather than resting until the pain vanishes. The NHS is clear that staying active is one of the most important things you can do for back pain and that prolonged rest tends to prolong recovery.
Across the following weeks, progress is rarely a straight line. A good day followed by a stiff morning does not mean treatment has failed; it means you have a back. What matters is the trend: less pain on average, more movement, fewer activities you avoid. Clinicians usually review that trend after a handful of sessions and adjust the plan, more emphasis on exercise, a change in technique, or a decision to stop.
Timelines depend on how long the pain has been present. For an acute episode, the NHS advises that most back pain improves within a few weeks, and hands-on care is a bridge across that period. For pain that has persisted for months, the horizon is longer and the emphasis shifts further toward self-management, with manual therapy playing a smaller part.
If several sessions produce no change at all, that is useful information rather than a failure. It tells the team that a different approach, or a fresh look at the diagnosis, is warranted.
Is manual therapy safe? Risks, side effects and the rare complications
For most people with nonspecific back pain, hands-on care performed by a trained, licensed clinician is low-risk. The NIH describes spinal manipulation as generally safe in these circumstances, while acknowledging that adverse events are not always well reported in research.
The common side effects are minor and short-lived: local soreness, stiffness, fatigue and occasionally a headache, usually settling within a day or two. These are similar to what you might feel after an unfamiliar workout and do not indicate harm.
The rare complications are the ones worth understanding clearly. According to the Mayo Clinic, serious complications of spinal manipulation are rare but can include a herniated disk or worsening of an existing herniation, compression of nerves in the lower spine, including cauda equina syndrome, a compression of the nerve bundle at the base of the spinal cord that affects bladder, bowel and leg function, and, following neck manipulation, a specific type of stroke. These events are uncommon; they are also the reason screening before treatment matters so much.
Risk is not evenly distributed. It is higher with thrust techniques than with mobilization, higher in the neck than the low back, and higher when treatment is applied to someone with one of the conditions listed earlier, fragile bone, nerve compression, cancer involving the spine, or an elevated stroke risk. A clinician who asks about your medical history, medicines and any neurological symptoms before treatment is doing the single most protective thing available.
You can lower your own risk by being candid about your history, by declining manipulation if you are not comfortable with it, and by reporting any new numbness, weakness, bladder or bowel change, or neurological symptom promptly rather than waiting for the next appointment. Those situations are addressed in the final section.
What is the best treatment for back pain? Why the honest answer is a plan, not a technique
People searching this question want a single answer, and the evidence refuses to give one. What it offers instead is a hierarchy of what helps most often, for most people, with the least downside.
At the top sits staying active. The NHS and Mayo Clinic both place continued movement, walking, gentle stretching, returning to normal activity as soon as possible, ahead of any specific intervention for nonspecific back pain. Bed rest beyond a day or two tends to make things worse.
Next comes exercise that is structured and progressive. It does not much matter whether the label is core stability, yoga, Pilates or a walking program; what matters is that it is regular, that it builds tolerance over weeks, and that you are willing to keep doing it. Guidelines consistently rate exercise therapy as a first-line treatment for persistent back pain.
Manual therapy sits alongside these as an adjunct, useful when stiffness or pain is stopping you from doing the active work. Pain-relief medicines, most commonly the anti-inflammatory class, may be advised for short periods to make movement easier; the mechanism is dampening inflammation around irritated tissue, and the decision about whether and how to use them belongs to your prescribing clinician. Psychological approaches become more relevant as pain becomes long-standing and starts to shape daily life.
Imaging, injections and surgery are reserved for specific structural problems identified by a specialist. For nonspecific pain, the Mayo Clinic notes, scans rarely change management and can lead to unnecessary worry.
So the best treatment is the combination your team builds from these ingredients, adjusted to how you respond. Anyone promising that one method is the answer for everyone is selling certainty the science does not have.
Home exercises and daily habits that support manual therapy for back pain
What should you do all day with back pain? Mostly, the things you would do anyway, at a gentler pace. The NHS advises carrying on with normal activities, including work, as much as you can, because movement keeps the back supple and the mind less focused on the pain.
A few simple movements are commonly suggested by clinicians for uncomplicated low back pain and can be practiced between sessions. Check with your treating team that these suit you before starting:
- Knee-to-chest: lying on your back, draw one knee toward your chest and hold briefly, then switch.
- Pelvic tilts: lying with knees bent, gently flatten your lower back into the floor, then release.
- Cat-cow on hands and knees: slowly round the back, then let it sag, moving with your breath.
- Short, frequent walks, several a day beats one long one when the back is sore.
Everyday adjustments help too. Change position often rather than sitting or standing for long stretches. Heat, in the form of a warm bath or a heat pack, is a home remedy the NHS notes can ease muscle tension for many people; cold packs suit some in the first day or two after a flare. Sleeping on your side with a pillow between the knees, or on your back with a pillow under the knees, reduces strain for many.
Home remedies that circulate online, special mattresses, spinal braces worn all day, prolonged bed rest, extreme stretching, are not supported by the mainstream evidence and in some cases work against recovery by discouraging movement.
Think of home care as the part of the plan you own. Sessions with a clinician are brief; the hours between them are where recovery actually happens.
What people often get wrong about manual therapy
The myths around hands-on care are stubborn, and several of them steer people away from what actually helps.
The first is that something is out of place and needs to be put back. Vertebrae do not slip in and out of alignment in everyday back pain, and the pop of a manipulation is gas releasing from joint fluid, not a bone returning home. The relief some people feel is real, but the mechanism is more likely a change in stiffness, muscle tone and pain signaling than a repositioning.
The second is that a scan is needed before treatment can begin. For nonspecific back pain without red flags, the NHS and Mayo Clinic note that imaging rarely alters management. Many pain-free adults have disk bulges and degenerative changes on MRI; finding them does not explain the pain and can increase anxiety.
The third is that pain equals damage, so rest is the safest course. The evidence points the other way: staying active shortens recovery, and prolonged rest lengthens it.
The fourth is that if manual therapy helps, more of it is better. The research pattern is short-term benefit, best when combined with exercise, with diminishing returns from long open-ended courses. Ongoing reliance on being treated is a signal to shift toward self-management, not to book more.
The fifth is that manipulation is either miraculous or dangerous. It is neither. It is a technique with modest average benefit and rare but real risks, appropriate for some and not for others, which is exactly why assessment and consent matter.
And a final one: that manual therapy fixes the cause. For most nonspecific back pain, there is no single cause to fix. What can be changed is how you move, how strong you are, and how much the pain dictates your day.
Questions to ask your care team before starting hands-on treatment
A good clinician expects questions and will welcome them. These are the ones that tend to produce the most useful answers.
Ask what they found on examination and what they think is driving your pain. You are entitled to a plain-language explanation, and the answer for most people is a reassuring one: no sign of anything serious, a stiff and sensitive back that needs to move.
Ask which techniques they propose and why. Specifically, ask whether manipulation is planned and whether mobilization would be a reasonable alternative. You can consent to one and not the other.
Ask how many sessions are anticipated, how progress will be measured, and what would prompt a change of plan. A defined review point is a sign of good practice. So is a clear description of what you should be doing between visits.
Ask what the home exercise program looks like and how it will progress. If the answer is vague, the balance between passive and active care may be off.
Ask about risks in your particular case, especially if you have osteoporosis, take blood-thinning medicines, have had spinal surgery, have nerve symptoms in a limb, or have any history of stroke or vascular disease. Ask what symptoms after a session should prompt you to call.
Ask whether they will communicate with your doctor, and what would lead them to refer you back for medical review.
Finally, ask what they expect the end of treatment to look like. The honest answer is not a promise of a pain-free back; it is a description of you managing well on your own, with the skills and confidence to handle the next flare without needing anyone’s hands.
When to call your doctor
Most back and neck pain is uncomfortable rather than dangerous, and most of it settles. A small number of situations need prompt medical assessment, whether or not you are having manual therapy. The NHS lists the following as reasons to seek urgent care.
Contact emergency services or go to an emergency department immediately if back pain comes with numbness or tingling around the genitals or buttocks, difficulty passing urine, loss of bladder or bowel control, or new weakness in both legs. These can signal cauda equina syndrome, a compression of the nerve bundle at the base of the spine that needs same-day treatment. Seek emergency help too if pain follows a serious accident or fall, or if neck pain is accompanied by sudden severe headache, dizziness, visual disturbance, slurred speech, facial drooping or difficulty swallowing, particularly after neck manipulation.
Arrange an urgent appointment with your doctor if you have back pain with a high temperature, unexplained weight loss, a swelling or change in the shape of your back, pain that is constant and worse at night or when lying down, pain that started after a fall, or if you have a history of cancer, a weakened immune system or long-term steroid use.
Make a routine appointment if pain has not started to improve after a few weeks, if it is stopping you from working or sleeping, if it is spreading down a leg or arm with numbness or weakness, or if new symptoms appear after a treatment session and do not settle within a day or two.
Hands-on care is one tool among several, and every decision about whether it belongs in your plan, including whether to continue, pause or stop, sits with the team treating you. When in doubt, call.
Frequently asked questions
Does manual therapy work for back pain?
It can, modestly and mainly in the short term. Reviews summarized by the NIH find that spinal manipulation and mobilization produce small improvements in pain and function for nonspecific low back pain, similar to other recommended treatments such as exercise. The benefit is largest and most durable when hands-on care is combined with an active exercise program. Not everyone responds, and researchers cannot yet predict who will.
What is the difference between spinal mobilization vs manipulation?
Mobilization is slow, rhythmic, low-velocity movement of a joint that stays within your control. Manipulation is a single quick thrust that briefly takes the joint to the end of its range, sometimes with an audible pop. Both aim to restore movement to a stiff segment. Manipulation carries a small set of additional risks, especially in the neck, and there is no clear evidence it works better than mobilization for nonspecific pain.
Is manual therapy for neck pain safe?
Gentle mobilization of the neck by a trained clinician is generally low-risk. Neck manipulation, the thrust technique, has been linked in rare cases to injury of the vertebral arteries and stroke, which the Mayo Clinic lists as a rare but serious complication. Clinicians screen for vascular risk factors before treating. If you are uncomfortable with manipulation, you can ask for mobilization and exercise instead.
What are some hands-on physical therapy techniques used for back pain?
Common techniques include joint mobilization (slow oscillating pressure on a spinal segment), soft-tissue release on tight muscles around the spine and hips, muscle energy techniques where you push gently against resistance and then relax, and, when appropriate and agreed, spinal manipulation. Most sessions combine one or more of these with guided movement and a home exercise program to build on any relief.
What are some exercises I can do at home to relieve back pain?
Gentle movements often suggested for uncomplicated low back pain include knee-to-chest stretches, pelvic tilts, cat-cow on hands and knees, and short frequent walks. The NHS emphasizes staying active over resting. Progress gradually toward strengthening the trunk, hips and legs. Check with your treating team that a given movement suits your situation before starting, especially if you have leg symptoms.
What is the best treatment for back pain?
There is no single best treatment. Mainstream guidance places staying active and structured exercise at the center of care for nonspecific back pain, with manual therapy, short-term pain-relief medicines and psychological approaches as supporting options chosen by your treating team. Imaging, injections and surgery are reserved for specific structural problems. The right combination depends on how long the pain has lasted and how you respond.
What should I do all day with back pain?
Keep moving as normally as you can. The NHS advises continuing everyday activities, including work, while avoiding long stretches in one position. Change posture often, take short walks, use heat if it helps, and do the gentle exercises your clinician has suggested. Bed rest beyond a day or two tends to slow recovery. Pace activities rather than stopping them.
What are some home remedies for lower back pain?
Heat packs or a warm bath can ease muscle tension, and the NHS lists this among simple self-care measures. Some people prefer cold in the first day or two of a flare. Gentle movement, side-lying sleep with a pillow between the knees, and gradual return to activity all help. Braces worn all day, prolonged rest and extreme stretching are not supported by the evidence.
How many manual therapy sessions are usually needed for back pain?
There is no fixed number. Plans for uncomplicated back pain typically run as a limited course over several weeks, with progress reviewed after a few sessions rather than a long series booked in advance. The NHS notes most acute back pain improves within a few weeks, and hands-on care is meant to bridge that period. If several sessions bring no change, the plan should be revisited.
Do I need an MRI before starting manual therapy?
Usually not. For nonspecific back pain without red-flag symptoms, the NHS and Mayo Clinic note that imaging rarely changes treatment. Many people without pain have disk bulges and age-related changes on MRI, so findings can mislead more than they inform. Scans are reserved for situations where a clinician suspects a specific structural or serious cause based on your history and examination.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

What Swallowing Rehabilitation Involves: Exercises, Texture Changes and Safe Eating Positions
Swallowing rehabilitation, usually led by a speech-language pathologist, combines three things: targeted exercises that strengthen and retrain the tongue, throat and airway-protecting muscles; changes…

Driving After a Stroke: The Rules and the Assessment
In most places you should not drive for a period after a stroke, commonly at least one month for private car drivers and considerably…
How to Tape a Knee: Step-By-Step Methods for Support, Pain Relief and Sport
To tape a knee, clean and dry the skin and bend the knee slightly. For front-of-knee pain, anchor rigid tape on the outer edge…

Stroke Rehabilitation Timeline: From Hospital Bedside to Outpatient Therapy and Home Practice
A stroke rehabilitation timeline usually begins at the hospital bedside within about 24 to 48 hours, moves to an inpatient rehabilitation unit or home-based…

Manual Therapy vs Chiropractic Adjustment: How the Approaches and Evidence Differ
Manual therapy is a broad family of hands-on techniques, including joint mobilization, soft tissue work and manipulation, used mostly by physical therapists as part…

What Physiotherapy Involves, and What to Wear to Your First Session
Physiotherapy (called physical therapy in the United States) is a licensed health profession that restores movement and function after injury, surgery, illness, or long-term…