

Can You Work and Travel During Immunotherapy? Planning Life Around Infusion Cycles

Key Takeaways
- Most checkpoint-inhibitor infusions run from about 30 minutes to a few hours, but a realistic clinic visit is half a day once checks, preparation, and observation are included.
- Immune-related side effects such as colitis, pneumonitis, and thyroid changes can start in any cycle and sometimes months after treatment ends, so no week is entirely 'off'.
- Immunotherapy alone does not usually lower white blood cell counts, which is why chemotherapy-style infection restrictions are often relaxed, unless corticosteroids are being used for a reaction.
- Regular moderate activity and consistent sleep timing are more strongly associated with reduced cancer-related fatigue than extra rest is.
- On journeys longer than about three hours, cancer raises deep vein thrombosis risk, so walking, hydration, and calf exercises matter more than for other travelers.
- Diarrhea while traveling during immunotherapy should be treated as possible colitis and reported to your team, not assumed to be food-related.
Many people can work during immunotherapy, often with reduced hours or flexible days around infusion cycles, because most checkpoint-inhibitor infusions take under a few hours and side effects are frequently milder than with chemotherapy. Travel is often possible between cycles with your team's agreement, written treatment records, and a plan for urgent care, since immune-related side effects can appear at any time.
The calendar on the kitchen wall already has the infusion dates circled in blue. What it does not show is the team meeting on the Tuesday after, the daughter’s graduation two states away, or the question that keeps surfacing in the car on the way home from the clinic: can you work during immunotherapy, and can you still go anywhere?
It is a fair question, and a newer one than it looks. For decades, cancer treatment meant chemotherapy, and chemotherapy meant blood counts, nausea, and weeks written off. Immunotherapy changed the shape of that experience for many people, but it did not make it predictable. Some patients drive themselves to a Friday infusion and open their laptop Monday. Others are flattened by fatigue or develop a stubborn rash that needs steroid treatment and a pause.
This article walks through what actually happens in an infusion cycle, what the days after tend to look like, and how to plan work and travel around them without pretending the risks are smaller than they are.
Can you work during immunotherapy? The short, honest answer
For a meaningful share of people, yes. Immunotherapy is designed to help the body’s own immune system recognize and attack cancer cells rather than to poison fast-dividing cells directly, and that difference matters for daily life. The infusion visit is often short, there is usually no drop in blood counts in the way chemotherapy causes, and many people describe the first few cycles as closer to a bad cold than to the treatment they had braced for (NCI; NHS).
But “many” is not “all”, and the honest answer has three parts. First, the type of job matters more than the type of cancer. Desk-based or remote work with some flexibility is usually easier to sustain than shift work, heavy physical labor, or roles with fixed hours and no cover. Second, side effects are unpredictable in timing. Immune-related reactions can appear after the first cycle or months into treatment, and some require a break from infusions and a course of corticosteroids, a group of anti-inflammatory medicines that can themselves cause sleep disruption and mood changes (NCI). Third, fatigue is the symptom that most often reshapes a working week, and it rarely follows a neat curve (Mayo Clinic).
So the practical framing is this: plan to work, but plan the way you would for a season of unpredictable weather. Keep the core of your schedule, build in slack around infusion days, decide in advance who covers you if a side effect sends you to the clinic, and review the plan every cycle with your treating team. The decision about whether a particular job is safe to continue, especially if it involves driving, operating machinery, or exposure to infection, always sits with the clinicians who know your case.
How immunotherapy actually works, and why that changes the planning
The most widely used cancer immunotherapies are immune checkpoint inhibitors. A checkpoint is a natural brake on immune cells, a protein signal that tells T cells to stand down. Some tumors exploit that brake to hide. Checkpoint inhibitors are antibody medicines that block the brake, so the immune system can see the tumor again (NCI). Other forms exist, including CAR T-cell therapy, where a person’s own immune cells are modified in a lab and returned, and cytokine treatments, but the infusion-cycle rhythm most readers are planning around belongs to checkpoint inhibitors.
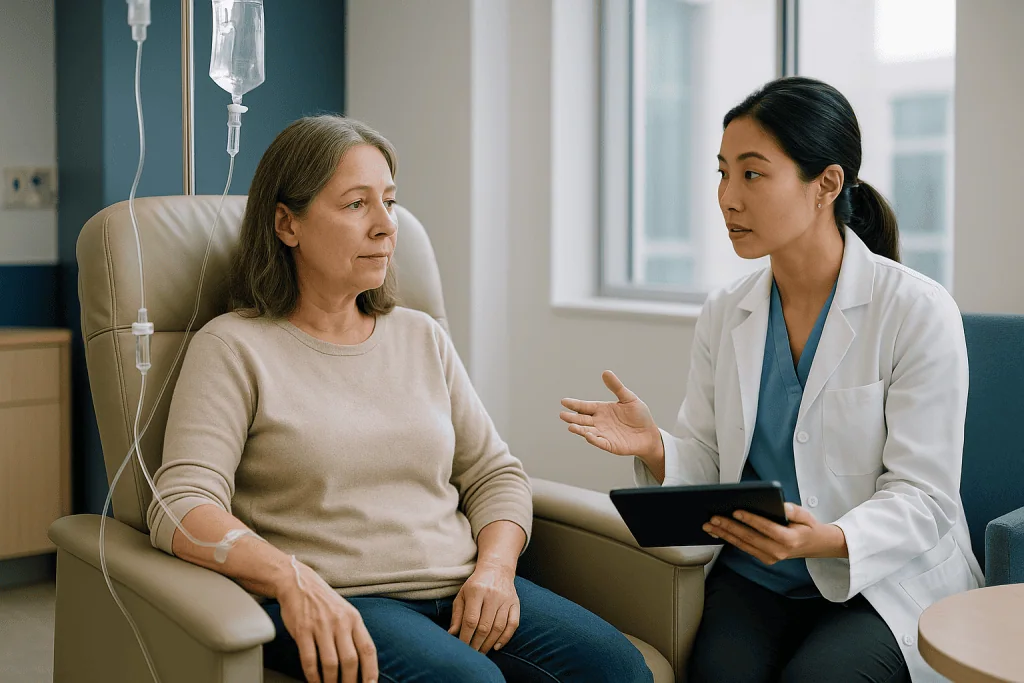
Why does the mechanism matter for your diary? Because the side effects follow the mechanism. Chemotherapy harms dividing cells, so hair, gut lining, and bone marrow suffer on a fairly predictable schedule. Releasing an immune brake does something different: it can let the immune system attack healthy tissue anywhere, which is why the recognized reactions include inflammation of the bowel (colitis), lungs (pneumonitis), liver (hepatitis), skin, and hormone-producing glands such as the thyroid (NCI; NHS). These are not tied to the day after infusion. They can arrive at any point during treatment and sometimes after it has stopped.
That has two consequences. The infusion day itself is often less disruptive than people expect. The weeks between infusions, however, are not “off” in the way a chemotherapy recovery week might feel like a countdown to normal. You are carrying a slightly louder immune system around with you, at work and on a plane, and the planning job is to make sure that if it misfires, you can reach care quickly.
Cleveland Clinic describes immunotherapy as given on a cycle: a period of treatment followed by a period of rest so the body can respond. Understanding that the rest period is about biology, not just recovery, helps when weighing whether a trip is a good idea.
How long does an immunotherapy infusion take? Infusion day, hour by hour
People who have sat through a six-hour chemotherapy chair are often surprised by an immunotherapy appointment. The medicine itself is typically given through a vein over roughly 30 minutes to a few hours, depending on the drug and whether it is combined with other treatment (Cleveland Clinic). The whole visit is longer than the drip, though, and it helps to picture the pieces.
First comes a check-in with a nurse or clinician: blood pressure, temperature, weight, and questions about new symptoms since the last cycle. Blood tests are usually drawn the same day or a day or two before, because thyroid, liver, and kidney markers are monitored for early signs of immune-related reactions (NCI). If a result is out of range, the infusion may be delayed while the team looks closer; this is a safety feature, not a setback, and it is the single most common reason a planned infusion date moves.
Then the drug is prepared, which can take a while, then the infusion runs, then a short observation period follows, especially in early cycles when reactions during the drip are more likely. Add waiting time, and a realistic block for a routine visit is half a day. Many people schedule infusions for a late morning slot and treat the afternoon as light or protected time.
Driving home is usually possible after a checkpoint-inhibitor infusion if no sedating medicine was given, but policies vary and your team will tell you what applies to you. Some people feel entirely normal that evening; others notice chills, mild aches, or a flu-like heaviness within the first day or two (NHS). Treatment cycles then repeat every few weeks, commonly somewhere between two and six depending on the specific medicine and schedule your clinicians have chosen (NCI; NHS). That interval is your planning unit for work and travel.
What the days and weeks after an infusion usually look like
There is no single immunotherapy week, but there are patterns clinicians see often enough to describe. Think of the cycle in three loose phases.

Days one to three. This is when infusion-related symptoms cluster if they occur: fatigue, chills, low-grade temperature, muscle aches, headache, or nausea (NHS; Cleveland Clinic). For many people these are mild or absent. If you can, keep these days free of travel and high-stakes commitments in the first two or three cycles until you learn your own pattern.
Days four to fourteen. Energy often stabilizes. This is the window most people use for fuller workdays, meetings, and shorter trips. Skin reactions such as dry, itchy patches or a rash are among the earliest immune-related effects to appear and are usually manageable with your team’s guidance (NCI).
The rest of the cycle. For many, this feels close to ordinary life. The caveat, repeated because it is the thing people underestimate, is that immune-related reactions do not respect this timetable. New diarrhea, breathlessness, or a change in how you feel generally can start in any week and in any cycle (NCI).
Over months, two things tend to happen. Some people settle into a rhythm and work almost normally. Others accumulate a grinding fatigue that is less about any single infusion and more about the cumulative load of treatment, appointments, and worry, which Mayo Clinic describes as one of the most common and persistent cancer-related symptoms. Hormone-gland reactions, particularly an underactive thyroid, can masquerade as this fatigue, which is one reason regular blood monitoring continues throughout (NCI). If your tiredness changes character, say so; it may be treatable rather than something to push through.
Immunotherapy side effects timeline: what shows up, and when
A reasonable rule of thumb from the cancer literature is that the skin tends to react earliest, the gut and liver often follow in the first few months, and hormone glands can be affected at almost any point, including after treatment ends. Timing varies widely by medicine, by combination, and by person, so treat these as a map of possibilities, not a schedule (NCI; NHS).
The common and usually manageable group includes fatigue, itching or rash, joint aches, mild diarrhea, loss of appetite, and flu-like symptoms around infusion days (Cleveland Clinic; NHS). These are the effects most people fold into a working life with some adjustment.
The immune-related group is less common but matters more for work and travel because it can escalate. Colitis presents as persistent or worsening diarrhea, sometimes with abdominal pain or blood. Pneumonitis presents as a new dry cough, breathlessness, or chest discomfort. Hepatitis is usually silent and picked up on blood tests, though yellowing skin or eyes and dark urine are late signs. Endocrine effects include thyroid changes, and rarely inflammation of the pituitary or adrenal glands, which can cause profound tiredness, headache, dizziness, or confusion. Rarer still are effects on the heart, nerves, kidneys, or eyes (NCI).
Why spell this out in an article about diaries? Because the standard management for a significant immune-related reaction is to pause immunotherapy and start corticosteroids, sometimes for several weeks, with a gradual reduction decided by your team (NCI). That is a different working month from the one you had planned, and a different travel risk. Knowing the early signs means you report them at the stage when a short course of treatment usually settles things, rather than from an unfamiliar emergency department far from your records. Your team will tell you which symptoms to report the same day and which can wait for the next visit; follow their list over any general one.
Who usually keeps working during immunotherapy, and who is usually asked to pause
Clinicians rarely issue a blanket “you can” or “you cannot”. They weigh the job against the person and the treatment. The combinations below describe common patterns rather than rules.
People who often continue working with adjustments include those in office-based, remote, or self-paced roles; those whose employer can offer flexible start times, reduced hours, or protected days around infusions; and those whose early cycles have produced only mild side effects. Immunotherapy alone does not usually suppress the bone marrow the way chemotherapy does, so the strict infection-avoidance rules familiar from chemotherapy are often less restrictive, though your own team’s advice overrides this (NHS).
People who are commonly asked to pause, reduce, or change duties include those whose work involves safety-critical tasks such as driving professionally, operating heavy machinery, or working at height, particularly if fatigue, dizziness, or joint pain is present; those with jobs that make it impossible to step away for an urgent review; those on combined treatment with chemotherapy, where blood-count effects reappear; and anyone currently being treated for an immune-related reaction with corticosteroids, which can affect sleep, blood sugar, mood, and infection risk (NCI).
A third group sits in between: shift workers, teachers, healthcare staff, and others with fixed hours and exposure to the public. For them the discussion is usually about timing and cover rather than a yes or no.
Travel follows the same logic. Short domestic trips between cycles are often reasonable; prolonged trips to remote places or to regions with limited emergency care are more likely to be discouraged, especially early in treatment while your pattern of side effects is unknown. Whatever the pattern, the decision belongs with the treating team, and it is worth asking for it in writing for an employer or insurer.
Immunotherapy fatigue and work: the symptom that decides most schedules
Ask people on checkpoint inhibitors what changed their working life and the answer is usually not the rash or the clinic visits. It is a tiredness that does not respond to sleep. Mayo Clinic describes cancer-related fatigue as persistent exhaustion, out of proportion to activity, that rest does not fully relieve; it is one of the most common symptoms across cancer treatments.
The mechanisms are several and they stack. The treatment itself provokes an inflammatory response, which the body experiences as fatigue in the same way it does with a viral infection. Disrupted sleep from anxiety, pain, or steroid treatment adds to it. Anemia, thyroid changes, and reduced physical activity can each contribute, which is why new or worsening fatigue should be reported rather than assumed (Mayo Clinic; NCI).
What helps, according to mainstream guidance, is less intuitive than resting more. Regular, moderate physical activity such as walking is consistently associated with less fatigue during cancer treatment, provided your team agrees it is safe. Keeping a consistent sleep and wake time, limiting long daytime naps, and spacing demanding tasks across the day rather than front-loading them are the behavioral strategies Mayo Clinic and the NHS highlight. Energy conservation, sometimes called pacing, means planning the week around your known lower points rather than fighting them.
For work, that translates into concrete asks: a later start on the two days after infusion, the hardest cognitive tasks scheduled for your best hours, permission to work from home on low days, and a standing agreement that a meeting can be moved without explanation. Some people find a short written energy log for two cycles reveals a pattern that makes negotiation with a manager much easier. If fatigue is severe or steadily worsening, tell your team; it may be a sign of a treatable hormone effect rather than a cost of treatment to be endured.
Which work and travel patterns fit infusion cycles? A comparison
The table below summarizes how common work and travel scenarios tend to line up with the rhythm of a checkpoint-inhibitor cycle. It is a planning aid, not a verdict; your team’s advice for your situation comes first.
| Scenario | Usually fits best | Main consideration | Typical adjustment |
|---|---|---|---|
| Office or remote work | Any phase, with flexibility | Fatigue on days 1–3 after infusion (NHS) | Protected half day for infusion; lighter days after |
| Shift or public-facing work | Mid-cycle | Fixed hours; infection exposure if on steroids (NCI) | Swap shifts around infusion days; agree on cover |
| Physical or safety-critical work | Case by case | Fatigue, dizziness, joint pain, concentration | Modified duties or temporary pause, team to decide |
| Day trip or overnight within reach of your center | Days 4 onward | Ability to return for review quickly | Carry treatment summary and contact numbers |
| Domestic trip of several days | Middle of the cycle | Access to emergency care; travel fatigue | Return before next infusion; identify local hospital |
| Long-haul flight or remote destination | Discuss before booking | Clot risk on journeys over about 3 hours (NHS DVT); distance from care | Team sign-off, insurance, written plan for side effects |
Two features of the table deserve emphasis. The middle of the cycle is the sweet spot for almost every scenario, and the further a plan takes you from a hospital that understands immunotherapy, the more preparation it needs. Many general emergency departments see immune-related reactions rarely; a short written summary of your treatment and its possible complications, prepared by your team, can change how quickly you are assessed.
Talking to your employer: adjustments, privacy, and pacing
You do not owe your workplace a diagnosis. In many countries, including the United States and the United Kingdom, employment law gives people with cancer a right to reasonable adjustments or accommodations, and to time off for treatment, but you can usually decide how much detail to share and with whom. A letter from your team stating that you are receiving treatment requiring periodic appointments, with likely patterns of fatigue, is often enough for human resources.
The conversation goes better when it is specific. Rather than “I may need some flexibility”, try “I will be away for roughly half a day every few weeks, I would like the following one to two days to be lower intensity, and I may need to move a meeting at short notice if I am unwell”. Managers can plan around a pattern; they struggle with vagueness.
Think about the shape of your week, not just the hours. Cognitive effects such as slowed thinking or difficulty concentrating, sometimes reported during cancer treatment, are easier to manage if demanding work is clustered in your best hours and routine work fills the rest (Mayo Clinic). If your role involves travel, decide now which trips are essential and which can be delegated for a few months.
Consider a staged approach. Some people keep full hours for the first cycle, with a clear agreement that they can drop to reduced hours without renegotiating if it proves too much. Others start reduced and build back up. Both are reasonable; the mistake is committing to a fixed plan before you know how your body responds.
Finally, keep a short record of appointments, symptoms, and days affected. It supports any later request for adjustments, and it is useful for your team too, who see you for minutes every few weeks and rely on your account of the time in between.
Flying during immunotherapy: what the evidence says about air travel
There is no medical rule that forbids flying while receiving checkpoint inhibitors, and many people do it between cycles. The relevant risks are mostly the same ones that apply to anyone with a serious illness traveling by air, with a few specific additions.
Blood clots come first. Cancer itself raises the risk of deep vein thrombosis, a clot in a deep vein usually in the leg, and sitting still on a journey longer than about three hours raises it further (NHS). The basics are well established: get up and walk the aisle regularly, do calf exercises in your seat, keep well hydrated, avoid alcohol and sedatives that keep you immobile, and wear properly fitted compression stockings if your team recommends them. Anyone with a previous clot, recent surgery, or reduced mobility should ask specifically whether additional precautions are advised; that decision is for the prescribing clinician, not a general article.
Cabin conditions are the second consideration. Aircraft cabins are pressurized to the equivalent of a moderate altitude, which lowers blood oxygen slightly. For most people this is unnoticeable, but anyone with lung involvement from cancer, prior pneumonitis, or new breathlessness should have that assessed before flying; a new cough or shortness of breath is one of the symptoms your team will want to hear about before, not after, you board (NCI).
Infection is the third. Immunotherapy alone does not usually leave people as vulnerable as chemotherapy does, but a current course of corticosteroids for a side effect does raise infection risk, and crowded airports are crowded airports. Hand hygiene, a mask if you choose, and avoiding travel while unwell are sensible.
Timing matters more than any of these. Flying in the middle of a cycle, after the first few cycles have shown your pattern, is the scenario most teams are comfortable discussing. Flying the day after an infusion, or while a side effect is still being assessed, is the scenario most often discouraged.
Traveling away from your treatment center: timing, records, and a plan B
A trip during immunotherapy succeeds or fails on preparation more than on distance. The conversation with your team should happen before anything is booked, and it usually covers five things.
Timing within the cycle. Aim to leave after the early post-infusion days and return before your next scheduled bloods and infusion. If a trip spans an infusion date, ask whether the schedule can shift; some teams can adjust by a few days, others cannot, and skipping or delaying treatment is never something to decide alone.
Documents. Carry a written treatment summary: your diagnosis, the name of the medicine class you receive, the date of your last infusion, a list of immune-related reactions to watch for, and a direct contact number for your team. Keep a digital copy as well. Clinicians who have never met you can act far faster with this in hand.
Access to care. Identify the nearest hospital with an emergency department at your destination before you go. If you develop severe diarrhea, breathlessness, or any red-flag symptom while away, you need assessment within hours, not a wait until you are home (NCI).
Insurance and contingency. Travel insurance that covers a pre-existing cancer diagnosis is essential for international trips; declaring your treatment accurately avoids a refused claim. Build in a plan for cutting the trip short.
Medicines you already take. Pack prescribed medicines in hand luggage, in original packaging, with enough for delays. Do not change anything about them for the trip without asking your team.
None of this is intended to discourage travel. Seeing people, resting somewhere different, and keeping a sense of an ordinary life are real benefits that many clinicians actively support. The point is to make sure the trip has an exit route if your immune system picks that week to misbehave.
Infection, sun, vaccines, and food: practical risk basics on the road
Because immunotherapy works differently from chemotherapy, some chemotherapy-era rules are stricter than needed and others are missing. Four areas come up repeatedly.
Infection. Checkpoint inhibitors on their own do not usually lower white blood cell counts, so the neutropenia precautions of chemotherapy, such as avoiding crowds entirely, are often unnecessary (NHS). The exception is anyone receiving corticosteroids or other immune-suppressing treatment for a side effect, which does increase infection risk. A fever during treatment should always be reported promptly, because it can signal either infection or an immune reaction, and the two are managed differently (NCI).
Sun. Skin is the organ most often affected by immune-related reactions, and some people become more sensitive to sunlight during treatment. High-factor sunscreen, a hat, and shade in the middle of the day are reasonable for any trip, and a new widespread or blistering rash is a reason to call rather than to wait (NCI).
Vaccines. Travel vaccines come in two types. Inactivated vaccines are generally considered acceptable during immunotherapy, though the timing should be agreed with your team. Live vaccines, which contain weakened virus, are usually avoided in people whose immune system is altered by treatment, and the advice is individual (NHS travel vaccinations guidance). Ask early, because some vaccines need to be given weeks before departure.
Food and water. The standard traveler’s precautions apply: safe water, well-cooked food, and care with raw produce in regions where this is recommended. The specific concern during immunotherapy is that diarrhea from a food-borne infection can look exactly like early colitis. If diarrhea starts while you are traveling, do not assume it is the food; contact your team, because immune-related colitis is treated by stopping the drug and starting anti-inflammatory treatment, and delaying that can make it worse (NCI).
What people often get wrong about immunotherapy, work, and travel
Myth: immunotherapy is “gentle”, so there is nothing to plan around. It is often easier to tolerate than chemotherapy, but immune-related reactions can be serious and occasionally life-threatening, and they are harder to predict (NCI). Easier on average does not mean easy for everyone.
Myth: side effects happen right after the infusion and then you are clear. Infusion-day symptoms do cluster early, but immune-related effects can start in any week of any cycle and sometimes months after the last dose. The “safe window” is a planning convenience, not a biological guarantee (NCI).
Myth: you must avoid crowds and raw food as you would on chemotherapy. Usually not, unless you are on corticosteroids or combined treatment. Over-restricting can cost you social contact and income for no benefit; ask your team what applies to you (NHS).
Myth: feeling well means the treatment is not working, and feeling terrible means it is. Side effects and response are not reliably linked in a way that should guide anyone’s behavior. Report symptoms because they need managing, not as a scorecard.
Myth: diarrhea on holiday is always the local food. During immunotherapy it may be colitis, which needs a different response. Treat it as a call-your-team symptom until proven otherwise (NCI).
Myth: steroids given for a side effect mean the cancer treatment has failed. A pause and a course of corticosteroids is the standard way to settle an immune reaction, and many people resume treatment afterward; whether and when is a decision for your team (NCI).
Myth: if you push through fatigue it will go away. Cancer-related fatigue tends to respond to pacing, regular moderate activity, and treating underlying causes such as thyroid changes or anemia, not to willpower (Mayo Clinic).
Myth: you cannot get travel insurance. You can, but you must declare the diagnosis and treatment accurately, and it is worth starting early.
Questions to ask your care team before you commit to work or travel plans
The most useful appointment is the one where you arrive with specific questions and leave with answers you can act on. These are the ones that tend to unlock planning.
- How long is my cycle, and which days in it are usually the lowest-energy days for people on this medicine?
- Which side effects should I report the same day, and which can wait for the next visit? Can I have that list in writing?
- Is it safe for me to drive after my infusion, and are there tasks at work I should avoid during treatment?
- If I need a letter for my employer or insurer, what will you include about appointments and likely patterns?
- Can my infusion dates move by a few days if a trip or work commitment falls on one, and what is the limit?
- Is there any reason specific to my cancer or my lungs that makes flying a concern right now?
- Do I need any extra precautions against blood clots on a long journey, given my history?
- Which travel vaccines are acceptable for me, and when should they be given?
- If I develop diarrhea or breathlessness while away, what exactly should I tell the local hospital, and should they call you?
- Are there destinations or trip lengths you would advise against at this stage of treatment?
- If I am started on corticosteroids for a side effect, how will that change my working week and my travel plans?
- Who do I contact out of hours, and what number should my family keep?
Write the answers down or ask for them in your patient portal. Plans drift over months of treatment, and the version you agreed in the first cycle will need updating after a side effect, a change in schedule, or simply a better understanding of how you respond. Treat it as a living document rather than a one-time permission slip, and revisit it before every significant commitment.
When to call your doctor: red-flag signs during immunotherapy
Most of the time, a call to your team’s helpline or an urgent appointment is the right first step. Some symptoms need emergency care immediately. Your team’s own list overrides anything written here, but the signs below are the ones mainstream guidance consistently flags for people receiving checkpoint inhibitors (NCI; NHS).
Seek emergency care without delay for chest pain, severe or sudden breathlessness, coughing up blood, a sudden severe headache, confusion, difficulty speaking, weakness or numbness on one side, a seizure, fainting, swelling of the face or throat, or a severe rash with blistering or peeling skin.
Contact your team the same day for a fever or chills; new or worsening cough or shortness of breath even if mild; diarrhea that is more frequent than usual, persists beyond a day, or contains blood or mucus; severe abdominal pain; yellowing of the skin or eyes, dark urine, or pale stools; a new widespread rash or severe itching; persistent nausea or vomiting; unusual thirst, frequent urination, or sudden fatigue; headaches with vision change or dizziness; eye pain or redness; new muscle weakness, numbness, or severe joint pain; swelling or pain in one calf; or any symptom that is frightening you. Explain that you are receiving immunotherapy; it changes how clinicians interpret what you describe.
If you are traveling, go to the nearest emergency department with your treatment summary and ask them to contact your team. Do not wait for your return flight.
Why the low threshold? Immune-related reactions are usually straightforward to manage when caught early and considerably harder when they have had days to develop. Reporting early is not overreacting; it is the single most effective thing you can do to keep working and traveling through treatment. Every decision about pausing, continuing, or changing your immunotherapy belongs with your treating team, and the fastest route to a good decision is a prompt phone call.
Frequently asked questions
Can you work during immunotherapy if you have a physical job?
Often yes with modified duties, but it depends on the specific job and your side effects. Fatigue, joint pain, dizziness, and reduced concentration can make safety-critical or heavy physical work risky, and corticosteroid treatment for a reaction adds further issues. Many people negotiate lighter tasks around infusion days. Ask your team for a written view on which duties are safe; the decision sits with them, not with you or your employer alone.
How long does an immunotherapy infusion take?
The drip itself typically takes from around 30 minutes to a few hours, depending on the medicine and whether it is combined with other treatment, according to Cleveland Clinic. The visit is longer because of pre-treatment checks, blood test review, drug preparation, and a short observation period. Plan for half a day in early cycles and ask your team how long your specific schedule usually runs.
Is flying during immunotherapy safe?
For many people, flying between cycles is reasonable once their team agrees. The main concerns are clot risk on longer journeys, which cancer already raises, lowered cabin oxygen if the lungs are affected, and distance from care should an immune-related reaction begin. Fly mid-cycle, move about regularly, stay hydrated, carry a treatment summary, and avoid flying while any new symptom is being assessed. Your team makes the final call.
What is the typical immunotherapy side effects timeline?
Flu-like symptoms and fatigue cluster in the first few days after an infusion, skin reactions tend to appear early in treatment, bowel and liver reactions more often follow in the first months, and hormone-gland effects can occur at almost any time, including after treatment stops, according to the National Cancer Institute. Timing varies widely, so these are patterns, not a schedule, and new symptoms should be reported whenever they start.
How do I manage immunotherapy fatigue and work at the same time?
Pace rather than push. Schedule demanding tasks in your best hours, keep consistent sleep and wake times, limit long naps, and build in regular moderate activity such as walking if your team agrees. Protect the one to three days after infusion. Keep a brief energy log for two cycles to show your manager a pattern. Report fatigue that worsens or changes character, since treatable causes such as thyroid changes are possible.
Do I need to avoid crowds and raw food on immunotherapy?
Usually not to the degree required during chemotherapy, because checkpoint inhibitors do not typically lower infection-fighting white cells. The exceptions are combined treatment that includes chemotherapy and periods on corticosteroids for a side effect, both of which raise infection risk. Standard food and water precautions for travel still apply. Check with your team, since advice is individual and may change during treatment.
Can my infusion dates be moved for a trip or a work commitment?
Sometimes, by a few days, but this depends on the medicine, the schedule, and where you are in treatment. Teams generally prefer to keep cycles consistent, and some protocols allow less flexibility than others. Ask before you book anything. Never skip or delay a scheduled infusion on your own; that decision belongs with your prescribing clinician.
What should I pack and carry when traveling during immunotherapy?
A written and digital treatment summary with your diagnosis, medicine class, last infusion date, a list of immune-related reactions to watch for, and your team’s contact numbers. Carry prescribed medicines in hand luggage with enough for delays. Take travel insurance that declares your diagnosis, and note the nearest hospital at your destination. These items let unfamiliar clinicians act quickly if something goes wrong.
Can I have travel vaccines while on immunotherapy?
Inactivated vaccines are generally considered acceptable, with timing agreed by your team. Live vaccines, which contain weakened virus, are usually avoided in people whose immune system is altered by treatment, and advice is individual. Because some travel vaccines must be given weeks before departure, raise the question early with your oncology team and the travel clinic, and never assume a vaccine is fine without asking.
What happens if I get a side effect while away from home?
Contact your team and go to the nearest emergency department for red-flag symptoms such as severe diarrhea, breathlessness, chest pain, confusion, or jaundice. Show your treatment summary and ask the local clinicians to call your team. Immune-related reactions are usually easier to manage when treated within hours rather than days, which is why delaying until you are home is discouraged.
References
- Immunotherapy: What It Is, How It Works and Side Effects, Cleveland Clinic
- Deep vein thrombosis (DVT), NHS
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Is a Second Opinion Worth It for Lymphocytic Leukemia? Questions a Hematologist Expects
A second opinion is often worthwhile for chronic lymphocytic leukemia (CLL), a slow-growing blood cancer in which experienced hematologists can reasonably disagree about when…

Follow-Up After Thyroid Cancer: What Blood Tests and Ultrasound Track Over Time
After treatment for differentiated thyroid cancer, follow-up usually combines a blood test for thyroglobulin, a protein made only by thyroid tissue, with a check…

Who Is a Candidate for Mohs Surgery? Skin Cancer Types, Locations and What Surgeons Consider
Candidates for Mohs surgery are usually people with basal cell or squamous cell skin cancer that sits in a high-risk or cosmetically sensitive area…
Does Surgery Come First or Chemotherapy? How Surgical Oncology Teams Sequence Cancer Treatment
Neither order is automatically better. Surgery first or chemotherapy first depends on the cancer type, its stage, how fast it tends to spread, and…

How Remission Is Confirmed After Lymphoma Treatment and Then Monitored Over Time
Remission after lymphoma treatment is usually confirmed with an end-of-treatment PET-CT scan read against a standard scale, plus a physical examination and blood tests,…
Proton Therapy Planning: The Simulation CT, Your Immobilization Device and Bladder Prep
A proton therapy simulation is the planning appointment held before treatment starts. You lie in the exact position you will use for every session,…