

How Accessory Breast Removal Works: Excision, Liposuction and the Armpit Incision Explained

Key Takeaways
- Accessory breast tissue is a leftover of the embryonic milk line running from armpit to groin, which is why the armpit, at the top of that line, is its most common home.
- Because it is true breast tissue with hormone receptors, it swells before periods and in pregnancy, can produce milk, and can develop the same benign and, rarely, malignant conditions as the chest breasts, so ultrasound comes before any surgical plan.
- Liposuction removes fat efficiently but leaves fibrous glandular tissue behind; most symptomatic mounds are mixed, which is why a combined liposuction-plus-excision approach through a short crease incision is the most common technique.
- The intercostobrachial nerve crosses the surgical field, so a numb strip on the inner upper arm is a recognized after-effect that usually improves over months as the nerve recovers.
- NHS guidance for liposuction-type procedures suggests one to two weeks off work, roughly four weeks before strenuous exercise, several weeks in a compression garment and up to six months for the final contour.
- Fully excised gland does not regrow, but remaining fat cells can enlarge with weight gain, so a stable weight is the most effective way a person can protect the result.
Accessory breast removal surgery takes out extra breast tissue, most often in the armpit, through a short incision hidden in the natural underarm crease. Surgeons remove fatty tissue with liposuction, firmer glandular tissue by direct excision, or combine both, usually as a day procedure under local anesthesia with sedation or general anesthesia. Swelling settles over weeks, and the treating team decides technique, timing and suitability.
She noticed it first in a fitting-room mirror: a soft fullness just in front of the armpit that pushed over the edge of a strapless dress, then ached for a few days before every period. Her doctor had called it “a bit of extra tissue” years earlier. A trainer had called it fat. Neither explanation quite fit the way it swelled and settled on a monthly schedule.
People who look into accessory breast removal surgery usually arrive with the same puzzle. The bump has a name, it has a reason for being there, and it behaves the way it does for a specific biological cause. Once you understand that cause, the surgical choices, excision, liposuction or a mix of the two, stop sounding like marketing and start sounding like engineering.
This explainer walks through what the tissue is, how the operation is actually done, what the armpit incision involves, and what the following weeks tend to look like, with the evidence stated plainly where it is strong and flagged honestly where it is thin.
What is accessory breast tissue, and why does it show up in the armpit?
Every human embryo forms two ridges of specialized skin cells, one on each side, running from the armpit down to the groin. Anatomists call them the mammary ridges or milk lines. In most people, everything along those lines melts away before birth except the two patches on the chest that become breasts. When a piece of the ridge fails to disappear, the leftover develops into accessory breast tissue: breast tissue in a place where breast tissue is not expected.
The armpit is the most frequent site because it sits at the top of the line, but leftovers can appear anywhere along its path, including under the normal breast or on the abdomen. The tissue may consist of a small extra nipple with nothing beneath it, a mound of glandular tissue (the milk-producing tissue of a breast) with no nipple, or both together. MedlinePlus notes that extra nipples are common and are often mistaken for moles or birthmarks, so many people never realize what they have.
The armpit variety usually goes unnoticed in childhood. It announces itself at puberty, during pregnancy, or after weight gain, because it carries the same hormone receptors as a normal breast and responds to estrogen and progesterone in the same way. That is why the swelling before a period, the tenderness, and occasionally milk production after childbirth are all part of the story people bring to a surgeon.
The condition occurs in both sexes. In men it tends to present as a fatty or firm mound near the front of the armpit rather than a cyclical swelling, and the surgical principles are the same.
Why people consider accessory breast removal surgery
Ask a surgeon what brings someone through the door and the answer is rarely a single thing. Some people describe a dull, dragging ache that flares in the second half of the menstrual cycle. Others talk about skin that chafes and sweats where the mound presses against the upper arm, leading to rashes that are hard to keep dry. Bras dig in at the wrong place. Sleeveless clothing becomes something to plan around. After childbirth, a few people are startled to find the armpit tissue engorging or leaking milk alongside the breasts.

Then there is the quieter reason: worry. A mound in the armpit is, to the untrained eye, a lump, and lumps in that region are unsettling. Part of what a consultation offers is the reassurance of a proper diagnosis before any talk of removal.
Surgeons tend to sort the reasons into two loose groups. Functional reasons cover pain, skin problems and interference with daily activities. Aesthetic reasons cover contour and confidence. The distinction matters less to the operating technique than to paperwork, because insurers in many systems treat the two differently, a point covered later.
What the evidence does not support is any sense of urgency. Accessory breast tissue is benign in the overwhelming majority of people, and choosing to live with it is entirely reasonable. Mayo Clinic’s guidance on breast lumps stresses that most lumps, wherever breast tissue exists, are not cancer, while still recommending that any new or changing lump be evaluated. The decision to operate is about quality of life, made with a treating team, not a race against anything.
Before the operation: imaging, diagnosis and the consultation
No responsible surgeon removes armpit tissue without first confirming what it is. Because accessory tissue is genuine breast tissue, it can develop the same conditions as the breasts on the chest: cysts, fibroadenomas (common benign lumps of glandular and fibrous tissue), infections and, rarely, cancer. Imaging exists to rule those out before a scalpel is anywhere near the area.
Ultrasound is typically the first study, because it distinguishes fluid-filled cysts from solid tissue and shows whether the mound is mostly fat, mostly gland, or a mixture. Depending on age and findings, a mammogram of the main breasts may be added, and occasionally an MRI when the picture is unclear. If anything looks atypical, a needle biopsy (removing a sliver of tissue with a fine needle for microscopic examination) settles the question before any cosmetic planning begins.
The consultation itself covers more than the mound. Expect questions about menstrual patterns, pregnancies and breastfeeding, weight history, smoking, bleeding tendencies, previous scars and how they healed, and current medicines. Medicines that affect clotting are relevant, but the team decides what, if anything, changes before surgery; nobody should pause a prescription on their own initiative.
Standardized photographs are taken with arms down and raised, because the mound often looks entirely different in each position. The surgeon will also pinch and lift the skin to judge how much will retract on its own once the bulk beneath it is gone, a judgement that drives the choice between a small hidden incision and a longer one that removes skin. Leave the consultation knowing which technique is proposed and why, in language you could repeat to a friend.
How accessory breast removal surgery works, step by step
The operation begins before anesthesia, with a marker. The surgeon outlines the mound while you stand, because tissue shifts when you lie down and the goal is a smooth contour in the upright position where the problem is visible.
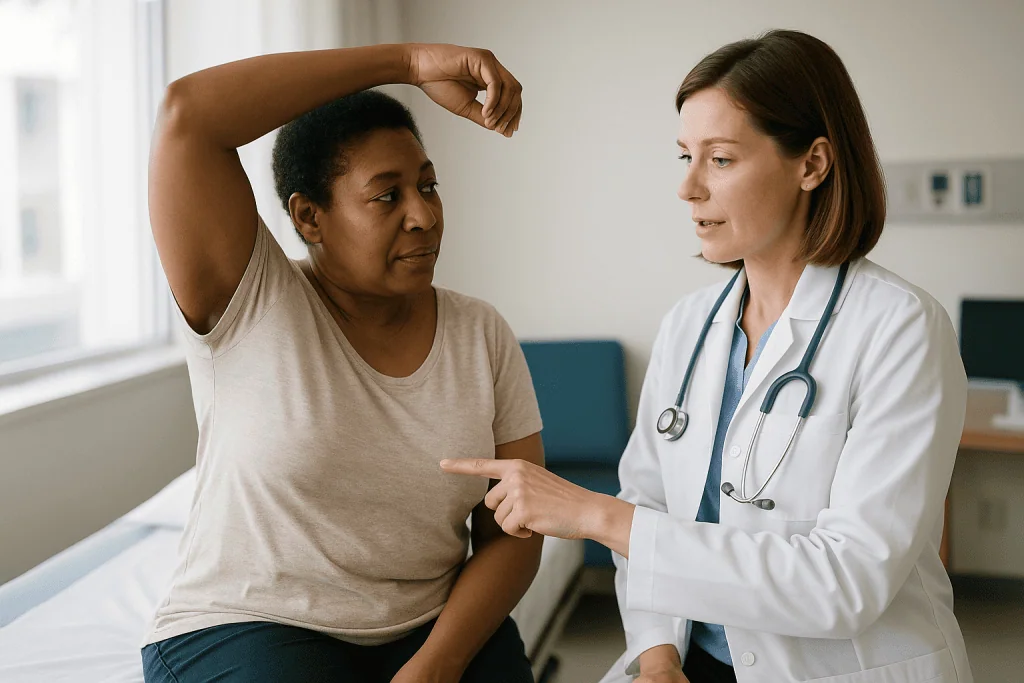
Anesthesia is either general or local with sedation. Mayo Clinic describes liposuction of small areas as commonly done in an outpatient setting, and accessory tissue removal usually follows that day-case pattern, though the team decides based on the extent of tissue and your health.
Most surgeons next infiltrate the area with tumescent fluid: a dilute solution containing local anesthetic and a blood-vessel-constricting agent, injected until the tissue becomes firm and swollen. The mechanism is simple. Constricted vessels bleed less, the fluid lifts the fatty layer away from deeper structures, and the local anesthetic leaves the area numb for hours afterward.
Through a puncture a few millimeters wide, a thin hollow tube called a cannula is passed back and forth to suction out fat. If the ultrasound showed a glandular core, the surgeon then makes a short incision along the armpit crease, lifts the skin, and cuts out the firm gland with scissors or an electrosurgical device that seals small vessels as it cuts. The gland is sent to a pathology laboratory for examination, standard practice for any removed breast tissue.
If pinching showed skin that will not shrink back, a crescent of skin is removed as well. The wound is closed in layers with dissolvable stitches, sometimes over a thin drain (a soft tube that carries away fluid for a day or two). A compression garment goes on before you wake.
Excision, liposuction or both: how the technique is chosen
The three approaches are not competitors so much as tools matched to what the ultrasound and the surgeon’s fingers find. Fat comes out readily through a cannula. Glandular tissue is fibrous, rubbery and attached; suction alone tends to leave it behind, where it can swell with the next hormonal shift. Skin that has stretched over years may not retract on its own, particularly in older patients or after weight loss.
| Technique | Usually suited to | Incision | Main trade-off |
|---|---|---|---|
| Liposuction alone | Mostly fatty mounds with good skin elasticity | One or two small punctures | Cannot remove firm glandular tissue; residual gland may re-swell |
| Direct excision | Predominantly glandular tissue, often with an extra nipple | Short incision in the armpit crease | Visible scar; contour step if fat around the edges is not blended |
| Combined liposuction and excision | Mixed fat and gland, the most common pattern | Puncture plus short crease incision | Longer operation; two healing sites |
| Excision with skin removal | Redundant, inelastic skin over the mound | Longer incision along the crease | Longest scar; tighter early feeling under the arm |
A recurring debate in the surgical literature is whether skin should be removed at the first operation or left to retract and revisited only if needed. The honest answer is that the evidence consists mostly of surgeon case series rather than randomized trials, so practice varies, and reasonable surgeons disagree. What matters for you is that the plan matches your tissue type and that the surgeon explains what happens if the skin does not settle as hoped.
The armpit incision explained: where it goes and why
Look at your own armpit with the arm raised and you will see a natural dome with fine skin folds running across it. That dome is where the incision lives. Placed along an existing fold, the scar lies in shadow whenever the arm hangs at the side and blends with the creases when the arm is lifted. The length depends on how much gland must come out and whether skin is being removed; a purely fatty mound may need only punctures, while a large gland with loose skin may need an incision spanning much of the crease.
Two anatomical facts shape the surgeon’s caution. The first is a sensory nerve, the intercostobrachial nerve, which crosses the armpit to supply feeling to the inner upper arm. Bruising or stretching it during surgery is a recognized cause of the numb patch some people notice afterward; sensation usually improves as the nerve recovers, though it can take months. The second is the cluster of lymph nodes that sits deeper in the armpit. Accessory tissue lies in the superficial layer above them, so a surgeon working in the correct plane should not disturb them, but this is the reason the dissection stays shallow and deliberate.
The armpit is also warm, moist and hair-bearing, which is why wound-care instructions here are more specific than for a scar on the abdomen. You will likely be told when showering is allowed, how to keep the fold dry, and to avoid deodorant on the incision until it has sealed.
Scar maturation follows the general pattern for skin surgery. NHS guidance on cosmetic procedures notes that scars fade over months, and some people, especially those with a history of raised or keloid scars, are advised about that risk in advance.
Who accessory breast removal surgery is usually for, and who is asked to wait
The typical candidate is an adult whose armpit tissue has been confirmed benign on imaging, who has symptoms or contour concerns significant enough to accept a scar and a recovery period, and whose general health allows anesthesia. Stable weight helps, because fat in the area shifts with weight changes and results are more predictable when the body is not mid-transition. Realistic expectations matter as much as any medical factor: the goal is a flatter, more comfortable armpit, not a perfect symmetry that few bodies have to begin with.
Several situations usually lead a team to recommend waiting. Pregnancy and breastfeeding top the list. Accessory tissue enlarges under pregnancy hormones and may produce milk, so operating during this period means removing tissue at its most swollen and vascular and risking milk leakage into the wound. Most surgeons prefer to wait until the tissue has settled after weaning; the team sets the interval.
Adolescents are generally asked to wait until development is complete, because tissue that is still growing is a moving target. An unexplained lump, or imaging that raises any question, means the diagnostic workup comes first and any cosmetic plan follows only when the result is clearly benign.
Smoking impairs wound healing by narrowing small blood vessels, and NHS advice for cosmetic surgery is to stop well beforehand; many teams will not schedule surgery until that has happened. Uncontrolled diabetes, bleeding disorders and active skin infection in the area are also reasons to postpone. None of these are permanent refusals. They are the team’s way of stacking the odds toward an uneventful recovery, and the timing decision stays with them.
How painful is axillary breast tissue removal?
The most common description from people who have been through it is soreness rather than sharp pain: a deep bruised feeling, worst when reaching overhead or lying on that side, most noticeable in the first few days. Mayo Clinic’s liposuction guidance sets expectations the same way, listing pain, swelling and bruising as normal after the procedure and noting that they subside over the following weeks.
Several things work in your favor. The tumescent fluid infiltrated during surgery keeps the area numb for hours after you wake, so the first evening is often more comfortable than people expect. The compression garment, though it looks unforgiving, reduces the swelling that would otherwise stretch tender tissue, which is why teams ask that it stay on. Ice packs over the garment in the first day or two are commonly suggested for the same reason.
Pain relief is planned by the surgical team before you leave, and it varies with the extent of surgery and your history. Many teams use non-opioid pain relievers as the foundation and reserve stronger medicines for breakthrough pain, but the choice, the amounts and how long they are used belong to the prescribing clinician, not to a magazine article.
Discomfort follows a predictable arc. Days one to three are the peak. By the end of the first week most people describe tightness and tenderness rather than pain. Odd sensations, such as tingling, itching or a numb strip along the inner arm, can persist for weeks as nerves recover. Pain that escalates instead of easing, or that arrives with rapid swelling, is not part of the normal arc and belongs in the red-flag list at the end of this article.
Axillary breast removal recovery: what the days and weeks usually look like
The first evening is quiet by design. Someone drives you home, the garment stays on, and if a drain was placed you are shown how to empty and record it. Most drains come out within a day or two, once the fluid output falls. Short walks around the house are encouraged from the start because movement keeps blood circulating in the legs, a basic clot-prevention measure that matters more after general anesthesia.
Through the first week, arm movement is kept gentle. Reaching, lifting and anything that stretches the armpit crease are limited so that the incision is not pulled while it seals. Showering is usually permitted once the team confirms the wound is closed. NHS guidance on liposuction suggests planning a week or two away from work, depending on how physical the job is, and that timeline suits combined procedures as well.
Weeks two to four bring the return of ordinary life. Bruising fades through the familiar yellow-green stages. The garment is typically worn for several weeks, as both Mayo Clinic and the NHS describe for liposuction, because swelling continues to drain during this period. Strenuous exercise, especially upper-body work, is generally held back for about four weeks per NHS advice, and your team will refine that based on how the incision looks at follow-up.
The final shape takes patience. Mayo Clinic notes that liposuction swelling subsides over a few weeks and the finished contour appears after several months, while the NHS puts full results at up to six months. Numbness on the inner arm can outlast all of this. Pathology results are usually discussed at an early follow-up visit, closing the diagnostic loop that began with the ultrasound.
Risks and complications in plain language
Every operation carries risk, and a good consultation names them without drama. For accessory tissue removal the list is short but worth knowing.
Bleeding into the wound after closure produces a hematoma, a collection of clotted blood that causes rapid, tight, painful swelling and sometimes needs draining. Seroma is the gentler cousin: a pocket of clear fluid that gathers in the space where tissue was removed, feels like a soft water balloon, and often resolves on its own or with needle aspiration. Drains and compression exist largely to reduce both.
Infection is uncommon in clean surgery but more of a concern in the armpit than on drier skin. The CDC describes surgical site infections as arising in the days after an operation, with redness, warmth, pain and drainage at the incision as the usual signals.
Numbness along the inner upper arm from irritation of the intercostobrachial nerve is common early and usually improves, though a small permanent patch is possible. Contour problems, such as a dent where too much was removed, a residual fullness where too little was, or asymmetry between sides, are the aesthetic risks, and revision is sometimes discussed. Scars can thicken or widen, particularly in people prone to keloids.
Rare but serious risks belong to any surgery under general anesthesia: reactions to anesthetic agents and blood clots in the leg veins, which the NHS notes can travel to the lungs. Injury to lymphatic channels causing arm swelling is theoretically possible but unusual when the dissection stays superficial. Your team weighs these against your particular situation, which is exactly why the decision rests with them.
Does accessory breast tissue go away, or come back after surgery?
Left alone, accessory breast tissue does not disappear. It is a permanent structure, not a swelling that resolves. What people experience as it “shrinking” is the ebb of hormonal stimulation: the mound may soften after menopause, deflate after breastfeeding ends, or look smaller after weight loss because the fatty component has reduced. The glandular core remains, quietly, and reactivates whenever hormones return, which is why the tissue that seemed to vanish after one pregnancy can reappear in the next.
After surgery the question shifts to recurrence. Glandular tissue that has been fully excised does not regrow; the body has no mechanism to rebuild breast tissue from nothing. Recurrence, when it happens, is almost always residual tissue that was never removed. This is the practical argument for excising the gland directly rather than relying on liposuction alone, since the cannula is efficient with fat and poor with fibrous gland. It is also why surgeons examine the cavity by feel before closing, hunting for firm remnants.
Fat behaves differently. Mayo Clinic explains that fat cells removed by liposuction are gone permanently, but the fat cells left behind can enlarge with weight gain, so a fatty armpit can refill if weight rises substantially. Maintaining a stable weight is therefore the single most useful thing a person can do to protect the result, and it is entirely within their control.
A separate point deserves emphasis. Removing accessory tissue does nothing to the breasts on the chest. Routine breast screening according to age-based guidance continues exactly as before, because the tissue that carries the overwhelming majority of breast health risk is still where it always was.
What people often get wrong about accessory breast tissue
The first myth is that it is simply fat. Sometimes it is, and liposuction alone works well in those cases. Often it is not, and the firm, cyclically tender component that bothers people most is glandular tissue that no amount of dieting will touch. An ultrasound settles this in minutes, and it is the reason a scan comes before any promise about technique.
The second myth follows from the first: that exercise, creams, massage or supplements can shrink it. There is no evidence that any of these reduce glandular tissue, and no plausible mechanism by which they could. Exercise can reduce surrounding fat, which sometimes makes the gland more prominent rather than less. Nothing rubbed onto skin reaches a structure beneath it.
The third is that accessory tissue is somehow exempt from breast disease. It is breast tissue, so it can develop cysts, benign lumps, infections and, rarely, cancer, just like the tissue on the chest. This is not a reason for alarm; it is the reason imaging comes first and the removed tissue goes to a pathologist afterward.
The fourth is that liposuction is scarless. It leaves small marks at the puncture sites, usually inconspicuous but real. The fifth is that removal will harm future breastfeeding. The main breasts are untouched, and the accessory tissue, which occasionally lactated and caused discomfort, is gone.
The last misconception is about who gets it. Accessory tissue occurs in men as well as women, and in men it is sometimes dismissed as a fat pad or a gym-related lump for years. The workup and surgical options are the same regardless of sex.
Questions to ask your care team
A consultation is a two-way examination. The surgeon studies your tissue; you study their reasoning. Arriving with specific questions turns a sales-like conversation into a clinical one, and the answers reveal how carefully the plan has been tailored to you rather than lifted from a template.
Start with diagnosis. What did the ultrasound show, and is the mound mostly fat, mostly gland, or mixed? Does anything about the imaging or my history call for a mammogram, MRI or biopsy before we plan anything? Will the removed tissue be sent to pathology, and when will I hear the result?
Move to technique. Which of excision, liposuction or a combination are you proposing, and what in my tissue drives that choice? Will skin be removed, and if not, what happens if it fails to retract? Exactly where will the incision sit, and roughly how long will it be? Do you expect to use a drain?
Then anesthesia and logistics. Will this be general anesthesia or local with sedation, and who administers it? Is this a day procedure? What should I do about my regular medicines, and who decides that?
Recovery questions are practical. How long will I wear the garment? When can I shower, drive, return to work, lift my children, and exercise? What numbness should I expect, and how long might it last?
Finish with the uncomfortable ones. What complications have you seen with this operation, and how were they handled? If tissue remains or the contour is uneven, what is your approach to revision? Who do I call at night or on a weekend if something worries me? If coverage is relevant, what documentation of symptoms does your office typically provide to an insurer?
When to call your doctor after accessory breast tissue surgery
Most recoveries are uneventful, and knowing the difference between ordinary healing and a problem lets you rest instead of worry. Soreness that eases day by day, bruising that fades through color changes, and a numb or tingling strip along the inner arm are all expected. The signs below are not, and each warrants a same-day call to the surgical team.
Swelling on one side that grows quickly, feels tense or rock-hard, or comes with pain that escalates rather than settles suggests a hematoma and should be assessed promptly. Fever, chills, spreading redness around the incision, increasing warmth, pus or a foul-smelling discharge point toward infection, which the CDC describes as typically appearing within days of surgery and is easiest to manage when caught early. A wound that opens, or stitches that pull apart, needs to be seen. A soft, sloshing fluid collection that keeps enlarging may be a seroma that requires draining.
Some signs bypass the surgeon’s office and go straight to emergency services. Pain, swelling or warmth in a calf can indicate a deep vein thrombosis, and the NHS lists sudden breathlessness, chest pain or coughing blood as signs that a clot may have traveled to the lungs. These are emergencies at any point in the weeks after an operation under anesthesia.
Before surgery, different red flags apply. A lump in the armpit or accessory tissue that is new, hard, fixed, growing steadily, or associated with skin dimpling, nipple discharge or unexplained weight loss should be evaluated by a doctor rather than watched. Mayo Clinic advises that any new or changing breast lump be checked. In every case, the assessment and the next step belong to your treating team; this list exists so that you know when to reach them.
Frequently asked questions
How much does accessory breast tissue removal cost?
No reliable figure can be given here, because the amount depends on the technique, the anesthesia type, the facility, the region and whether a health plan classifies the procedure as functional or cosmetic. The most useful step is to ask the surgical office for an itemized written estimate and to ask whether your symptoms may support a coverage request.
Will insurance cover removal of axillary breast tissue?
It depends on the plan and on how the problem is documented. Coverage is more often considered when there is a record of pain, recurrent skin irritation, or imaging findings that need removal, and less often when the reason is purely contour. Ask the surgeon’s office what documentation they can provide and check your plan’s criteria in advance.
How painful is axillary breast tissue removal?
Most people describe deep bruised soreness rather than sharp pain, worst in the first two or three days and aggravated by reaching overhead. Mayo Clinic lists pain, swelling and bruising as expected after liposuction, easing over the following weeks. The compression garment, ice and a pain plan set by the surgical team manage the early period.
Does accessory breast tissue go away on its own?
No. It is a permanent structure, though it may soften after menopause or shrink after breastfeeding ends or with weight loss because hormonal stimulation and fat content fall. The glandular core remains and can enlarge again with the next hormonal shift, which is why the tissue often reappears in a later pregnancy.
Is accessory breast tissue surgery done under general anesthesia?
It can be done under general anesthesia or under local anesthesia with sedation, usually as a day procedure. The choice depends on the extent of tissue, whether skin is being removed, your medical history and the surgeon’s practice. Mayo Clinic notes that smaller liposuction procedures are commonly performed in an outpatient setting.
Can axillary breast tissue be removed with liposuction alone?
Only when the mound is mostly fat with elastic skin. Liposuction cannot remove fibrous glandular tissue efficiently, so a purely suction-based approach on a gland-containing mound often leaves tissue that swells again with hormones. Ultrasound before surgery shows the fat-to-gland mix and guides whether direct excision is needed.
How long is axillary breast removal recovery before exercise?
NHS guidance for liposuction-type procedures suggests avoiding strenuous exercise for about four weeks, with lighter walking encouraged from the first days to keep circulation moving. Upper-body training that stretches the armpit crease is usually the last activity cleared. Your surgeon will adjust the timeline based on how the incision is healing at follow-up.
Will the armpit scar be visible?
The incision is placed along a natural fold in the dome of the armpit, so it sits in shadow with the arm down and blends with skin creases when the arm is raised. Length depends on how much gland and skin are removed. Scars fade over many months, and people prone to raised or keloid scars should raise that history at consultation.
Does removing accessory breast tissue affect breastfeeding later?
The breasts on the chest are untouched, so their ability to produce milk is unchanged. Accessory tissue itself occasionally lactates and causes painful engorgement after childbirth, so its removal eliminates that particular problem. Surgeons generally prefer to operate when someone is neither pregnant nor breastfeeding, so timing is worth discussing.
Can accessory breast tissue in the armpit be cancerous?
Rarely, yes, because it is genuine breast tissue and can develop the same conditions as the chest breasts, including cysts, benign lumps and, uncommonly, cancer. Most armpit mounds are benign. This is why imaging is performed before removal, removed tissue is sent to pathology, and any new or changing lump should be assessed by a doctor.
References
- MedlinePlus Medical Encyclopedia: Supernumerary nipples
- NHS: Liposuction
- NHS: Deep vein thrombosis (DVT)
- CDC: About Surgical Site Infections
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Breast Lift Scars and Daily Life After Mastopexy: Sleeping, Sports Bras and Sun Protection
Breast lift scars are permanent, but they usually change a great deal. Most fade from raised and pink to flat, pale lines over roughly…
Healing After Nipple Reconstruction: Protective Dressings, Bras to Avoid and the First Weeks
Nipple reconstruction recovery is usually gentler than earlier breast surgery. Most people wear a protective dressing or shield for the first weeks, choose soft…

Breast Fat Transfer vs Implants: Volume, Feel, Scars and Which Goals Each Option Suits
Fat transfer moves your own fat, taken by liposuction, into the breast for a modest, soft increase with only tiny needle-entry scars, but part…

Why Ultrasound or Mammography Comes Before Accessory Breast Surgery: Confirming the Tissue
Ultrasound, and sometimes mammography, comes before accessory breast surgery because a lump in the armpit or along the chest wall is not always breast…

Is Capsulectomy Needed With Breast Prosthesis Removal? How Surgeons Decide What Comes Out
Capsulectomy is not automatically required with breast prosthesis removal. Surgeons usually remove the capsule when it is thickened, calcified, ruptured silicone is present, or…

Local or General Anesthesia for Gynecomastia Surgery? What Shapes the Choice and Recovery
Gynecomastia surgery can be done under local anesthesia with or without sedation, or under general anesthesia. The choice depends mainly on how much glandular…