

How Herniated Disc Surgery Is Done: Finding the Disc Level and Freeing the Nerve
Key Takeaways
- Lumbar discectomy removes only the herniated fragment pressing on the nerve, leaving most of the disc and the spinal joint intact, with no hardware implanted.
- Surgeons confirm the disc level with live X-ray at least twice, before the incision and again against the bone, because vertebrae look alike from the outside.
- The operation typically takes one to two hours under general anesthesia, and many people walk the same day and go home the same day or next morning.
- Discectomy is aimed at radiating leg or arm pain from nerve compression; Mayo Clinic notes it is far less reliable for back pain alone.
- MedlinePlus gives a general range of about two to six weeks to return to work, with heavier lifting restricted longer and nerve numbness improving over months.
- Cleveland Clinic places the chance of the same disc herniating again at roughly 5% to 10%, which is why early bending and lifting limits exist.
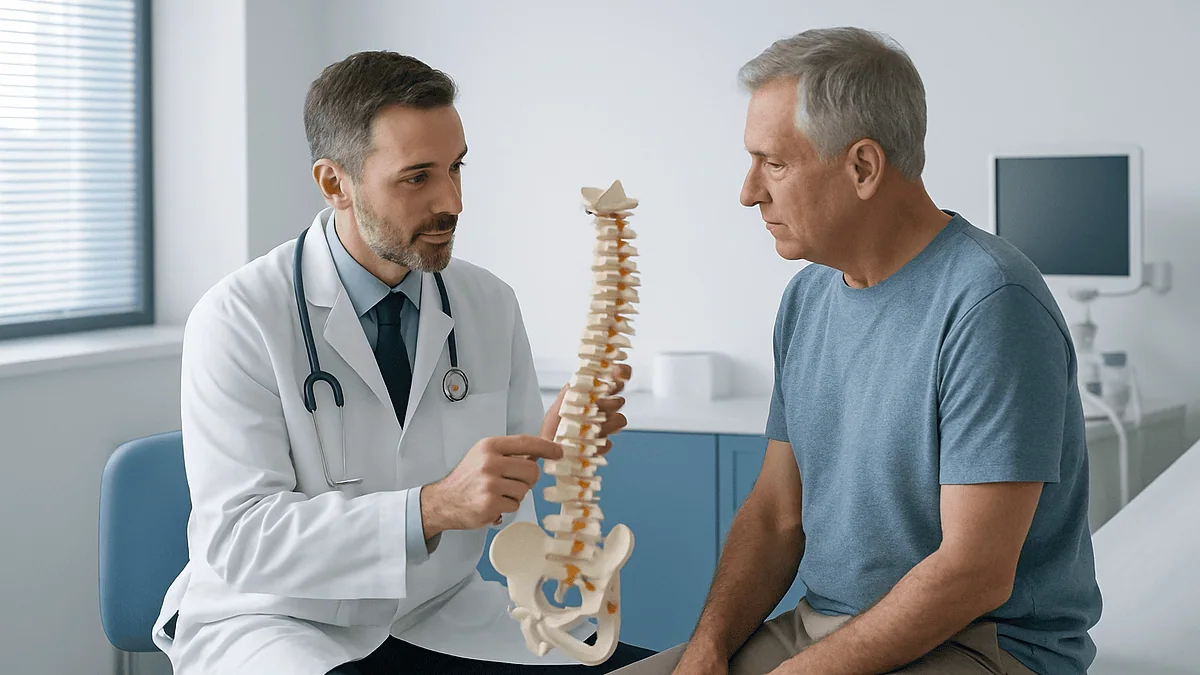
Herniated disc surgery, usually a lumbar microdiscectomy, is done under general anesthesia through a small incision in the back. The surgeon confirms the exact disc level with X-ray imaging, removes a small window of bone and ligament, gently moves the compressed nerve root aside, and takes out the disc fragment pressing on it. Most operations take one to two hours, and many people go home the same or next day.
The MRI report reads like a foreign language until one phrase lands: a disc fragment at L4-L5 pressing on the L5 nerve root. That explains the electric pain running down one leg, the foot that has started to drag on stairs, the nights spent standing in the kitchen because sitting is unbearable. Then a surgeon says the operation is straightforward, and the mind fills with questions that nobody quite asks out loud.
This explainer walks through how herniated disc surgery is done, step by step, in the order the surgical team actually thinks about it: confirming the correct disc level, opening a small path to the spine, and freeing the pinched nerve without harming it. Along the way it covers who is usually offered the operation, what the first weeks feel like, what can go wrong, and the myths that make the decision harder than it needs to be.
Every figure here is tied to mainstream medical sources, and every decision belongs to you and your treating team.
How herniated disc surgery is done: what the operation is actually trying to fix
Picture a spinal disc as a small jelly doughnut sitting between two vertebrae. The tough outer ring is the annulus; the soft center is the nucleus. A herniated disc means some of that soft center has pushed through a tear in the ring. On its own, that bulge is not the problem. The trouble starts when the escaped material presses on a nerve root, the branch leaving the spinal canal on its way to the leg or arm, producing the burning, shooting pain doctors call radiculopathy and most people call sciatica.
That single fact shapes the whole operation. The surgeon is not repairing the disc or putting it back where it was. The goal of a discectomy, the procedure name for removing disc material, is narrower and more precise: take away the piece that is compressing the nerve, disturb everything else as little as possible, and let the nerve recover. According to Mayo Clinic, the operation is most effective for leg or arm pain that radiates from a nerve, and far less predictable for back pain alone, because back pain usually has other causes the surgery does not touch.
Understanding how herniated disc surgery is done therefore starts with understanding what it is not. It is not a fusion, where two vertebrae are locked together with screws and bone graft. It is not a disc replacement. In its most common modern form, the lumbar microdiscectomy, it is a targeted decompression performed through an incision often shorter than a house key, using magnification so the surgeon can see structures a few millimeters wide.
The remainder of this article follows the operation in sequence, because the order matters. A beautifully executed decompression at the wrong level helps nobody, which is why the first real step happens before any tissue is divided.
Finding the disc level: how surgeons make sure they are at the right vertebra
From the outside, one lumbar vertebra looks much like its neighbor. The skin over L3-L4 and the skin over L5-S1 are a few centimeters apart, and in a person lying face down under sterile drapes there are no visible landmarks to count. Wrong-level spine surgery is rare, but it is recognized as one of the most serious avoidable errors in the specialty, and surgical teams treat localization as a formal safety step rather than a detail.

The process begins before the incision. With the patient positioned, the team takes an X-ray using fluoroscopy, a live X-ray that displays on a screen in the operating room. A thin needle or metal marker is placed on the skin, the image is checked, and the marker is moved until it sits over the target disc space. Surgeons count from a fixed reference, most often the sacrum, the triangular bone at the base of the spine, working upward: S1, L5, L4. That count is compared against the preoperative MRI so the anatomy on the table matches the anatomy in the report.
Some spines make this harder. A minority of people have a transitional vertebra, where the lowest lumbar bone is partly fused to the sacrum, so the same disc can be labeled differently depending on how a radiologist counted. In those cases the team may take a full-spine image or count from the top down to be certain.
Once the skin incision is made and the muscle is moved aside, localization is repeated. A small instrument is rested against the bone of the target level and another fluoroscopy image is taken. Only when that second check agrees with the first does the decompression begin. Many teams document the confirmation in the operative record, part of the surgical safety checklist that WHO recommends for every operation.
Lumbar discectomy procedure steps: opening a window and freeing the nerve
With the level confirmed, the work becomes a sequence of small, deliberate moves. Cleveland Clinic and Mayo Clinic describe the lumbar discectomy procedure steps in broadly the same order, and a typical operation takes about one to two hours, according to Cleveland Clinic.
- Incision and exposure. A cut of roughly an inch is made slightly off the midline of the lower back. The surgeon separates the paraspinal muscles from the bone rather than cutting through them, or slides a tubular retractor between the fibers to create a narrow channel.
- Laminotomy. The lamina is the roof of bone over the spinal canal. A small window is drilled or nibbled away, along with a portion of the ligamentum flavum, the yellow elastic ligament beneath it. This is the door into the canal.
- Identifying the nerve. Under an operating microscope or magnifying loupes, the surgeon sees the dura, the thin sac holding the spinal fluid and nerves, and beside it the nerve root heading toward the exit foramen, the bony tunnel it leaves through. The root is often swollen and stretched tight over the disc fragment.
- Retraction. A blunt instrument gently draws the nerve root a few millimeters toward the midline, exposing the disc bulge beneath it. This is the most delicate moment; surgeons keep retraction brief and light.
- Removing the fragment. A tiny grasping instrument called a pituitary rongeur removes the herniated material. If the fragment is still partly inside the disc, the surgeon opens the annulus and clears loose pieces from within, leaving the healthy disc in place.
- Checking and closing. A fine probe is passed along the nerve to confirm it now moves freely. The wound is washed, the muscle falls back into position, and the skin is closed with stitches or glue.
No hardware is left behind. Most of the disc, and all of the spinal joint, remains untouched, which is exactly why recovery is usually measured in weeks rather than months.
Who is usually offered herniated disc surgery, and who is asked to wait
Most people with a herniated disc never meet a surgeon. Mayo Clinic notes that nonsurgical treatment relieves symptoms in the majority of people within days to weeks, and the NHS advises that a slipped disc usually improves over about six weeks with staying active, gentle exercise and pain relief. The body reabsorbs a surprising amount of herniated material on its own, and the inflamed nerve settles as pressure falls.

Surgery enters the conversation in three broad situations, and each carries a different urgency.
The first is time. When leg or arm pain has persisted through at least six weeks of appropriate nonsurgical care and remains severe enough to limit daily life, Mayo Clinic lists discectomy as an option to discuss. The MRI must also show a herniation at the level and side that matches the symptoms; a bulge that does not explain the pain is not a surgical target.
The second is weakness. A foot that cannot lift, a thigh that gives way, or an arm losing grip strength signals that the nerve is not just irritated but failing. Progressive weakness often moves the discussion forward faster than pain alone, because motor recovery is less certain the longer compression continues.
The third is an emergency. Cauda equina syndrome, where a large central herniation compresses the bundle of nerves controlling the bladder, bowel and inner thighs, requires urgent surgical decompression. It is uncommon, but it is the reason the red-flag signs later in this article matter.
Who is usually asked to wait? People whose main complaint is back pain without leg symptoms, those still inside the first weeks of a flare that is trending better, and anyone whose imaging does not match their story. Certain medical conditions, smoking, or untreated infection may also prompt a pause. In every case the decision sits with the treating team, weighing symptoms, examination findings and imaging together.
Is discectomy major surgery?
The honest answer is that it depends on what you mean by major. If the measure is the size of the incision, the length of the operation and the length of the hospital stay, a lumbar microdiscectomy sits near the minor end of the spine surgery spectrum. MedlinePlus notes that many people go home the same day or after a single night, and Cleveland Clinic describes a procedure of roughly one to two hours performed through a small incision.
If the measure is what is at stake, the answer changes. The operation takes place millimeters from the dura and from nerve roots that carry sensation and movement for the leg. It requires general anesthesia in nearly every case, meaning a medication-induced sleep with an anesthesiologist managing breathing and circulation throughout. It carries the risks that every operation does, plus a few specific to the spine. Nobody working in an operating room calls it trivial.
A useful way to hold both truths is to compare it with operations people already understand. A microdiscectomy is closer in scale to a keyhole gallbladder removal than to a hip replacement or a spinal fusion. Recovery is usually counted in weeks. There are no implants to integrate, no bone that must knit together over months, and the spine’s stability is not altered.
Where the label matters practically is in preparation. Because it is a real operation under general anesthesia, expect the standard preoperative pathway: a health questionnaire, blood tests if indicated, a review of current medicines with the prescribing clinician, and instructions about fasting. Some people are asked to stop or adjust particular medicines beforehand; that decision always rests with the anesthesia and surgical teams, never with a magazine article.
So: minor in footprint, serious in precision. Treat it with the respect any operation deserves, without the dread that the word major can carry.
Microdiscectomy vs open vs endoscopic discectomy: how the approaches compare
The same goal, removing the fragment and freeing the nerve, can be reached by several routes. They differ mainly in how the surgeon sees and how the tissue between skin and spine is handled.
| Approach | How the surgeon sees | Typical incision | What is different for the patient |
|---|---|---|---|
| Traditional open discectomy | Direct vision, sometimes with loupes | Longer, often several centimeters | More muscle dissection; historically longer hospital stays |
| Microdiscectomy | Operating microscope | About an inch | Current standard in many centers; usually same-day or overnight stay |
| Tubular (minimally invasive) discectomy | Microscope or endoscope through a tube dilated between muscle fibers | Small, sized to the tube | Muscle spread rather than cut; similar goals to microdiscectomy |
| Endoscopic discectomy | Camera on a thin scope, image on a screen | Smallest, often under a centimeter | Sometimes done under sedation; not suitable for every herniation shape |
What the table cannot show is the most important point. Johns Hopkins, which describes minimally invasive lumbar discectomy in detail, and Mayo Clinic both frame these as variations on one operation rather than competing treatments. The decompression performed on the nerve is the same. Studies comparing them have generally found similar relief of leg pain, with the smaller approaches offering modest differences in early wound pain and recovery rather than a different outcome for the nerve itself.
The choice of approach usually reflects the anatomy of the herniation, whether it sits under the nerve, beside it or far out in the foramen, and the technique the surgeon has trained in most deeply. A surgeon experienced in one method will typically achieve a better result with it than with an unfamiliar one, whatever the incision length. That is worth remembering when marketing language suggests one keyhole is inherently superior to another.
How herniated disc surgery is done in the neck: a different route to the same nerve
Cervical herniations, those in the neck, produce pain, tingling or weakness in the shoulder, arm or hand rather than the leg. The nerve is freed in the same spirit, but the route is often very different, and this catches many people by surprise.
In the lumbar spine, the surgeon approaches from behind. In the neck, the most common approach is from the front. The reason is anatomy. The spinal cord itself sits directly behind the cervical discs, and retracting the cord the way a lumbar nerve root is retracted would be unsafe. Coming from the front lets the surgeon reach the disc without touching the cord at all.
Mayo Clinic describes this operation, anterior cervical discectomy, as follows. A small horizontal incision is made in a skin crease on the front of the neck. The surgeon moves the windpipe, food pipe and major blood vessels gently to one side; they are not cut. Fluoroscopy confirms the level, exactly as in the lower back. The disc is then removed through the front, the herniated piece is lifted away from the nerve root or cord, and the surgeon checks that the canal and foramen are clear.
Here comes the key difference. Because the entire disc is usually removed from the front, the space it occupied must be filled. Most anterior cervical discectomies are therefore combined with a fusion, a bone graft or spacer placed in the gap with a small plate to hold it, or with an artificial disc. The bone then heals across the space over months.
A posterior cervical approach, from the back of the neck, is possible for some side-positioned herniations and avoids fusion, but it is used less often. Cervical recovery timelines and restrictions differ from lumbar ones, particularly around neck movement while any fusion heals, so instructions from the treating team should take precedence over anything written about lumbar surgery here.
How painful is herniated disc surgery?
People asking this are usually asking two things at once: how bad is the pain now, and will surgery add to it. Both deserve straight answers.
Sciatica from a herniated disc is often described as among the more severe pains people experience, and many rate a bad flare toward the top of a 1 to 10 scale. There is no objective number that applies to everyone, and pain scales are personal tools rather than measurements. What the scale is good for is tracking your own trend: a pain that is easing week by week is behaving as the NHS says most slipped discs do, and a pain that is worsening or spreading is worth reporting.
After surgery the experience typically shifts. The incision site in the lower back is sore, in the way any fresh wound is sore, and muscles that were moved aside can ache for days. Mayo Clinic and Cleveland Clinic both describe this as expected postoperative pain managed with medicines prescribed by the team, which may include anti-inflammatory drugs and short courses of stronger analgesics chosen by the anesthesia and surgical clinicians.
The leg pain follows its own course. For many people the sharp radiating component eases early once the mechanical pressure is gone, while tingling or numbness lingers longer because an irritated nerve recovers slowly. Some people notice a temporary flare of nerve symptoms in the first days as the root, now free, reacts to having been handled. None of this can be promised in advance for any individual, and it is why surgeons talk about likely trajectories rather than guarantees.
Practical comfort measures matter more than they sound. Walking short distances several times a day, changing position regularly, using ice on the incision as advised, and avoiding long stretches of sitting all reduce muscle spasm in the first week. Pain that escalates rather than settles, or new weakness, is a reason to call, not to wait.
Microdiscectomy recovery time: what the first days and weeks usually look like
Recovery after lumbar microdiscectomy has a rhythm, and knowing it in advance takes much of the anxiety out of the early days. The ranges below are typical patterns described by MedlinePlus, Cleveland Clinic and Mayo Clinic, not promises for any one person.
The first day. Most people are up and walking within hours of waking from anesthesia. Nurses check that you can pass urine, that sensation and strength in the legs are as expected, and that pain is controlled with oral medicines. Discharge is often the same day or the next morning.
The first week. The main tasks are walking, short and frequent, and protecting the wound. Surgeons commonly advise limiting bending, lifting and twisting, sometimes summarized as no BLT, while the small opening in the annulus begins to seal. Sitting is usually allowed but in shorter stretches. Showering guidance depends on the type of wound closure; the discharge instructions will say.
Weeks two to six. Walking distance increases steadily. Many people with desk-based work return in this window; MedlinePlus gives a general range of about two to six weeks to return to work depending on the job’s physical demands. Driving usually resumes once you are no longer taking sedating medicines and can brake sharply without hesitation, a judgement your team will help with. A follow-up visit typically checks the wound and neurological recovery.
Weeks six to twelve. Lifting restrictions are progressively eased. Physical therapy, where prescribed, shifts from gentle mobility to core strengthening and movement retraining. Heavier manual work and impact sports are usually reintroduced toward the end of this period or later, on the team’s advice.
Nerve recovery runs on a slower clock than wound healing. Numbness and pins-and-needles can continue improving for many months, which is normal, and a numb patch that remains after everything else has settled is a recognized possibility rather than a sign of failure.
How long does it take to recover from L4-L5 herniated disc surgery?
L4-L5 and L5-S1 are the two levels where most lumbar herniations happen, so this specific question is really the general one. The good news is that the level itself does not greatly change the timeline. What changes it is the size of the herniation, how long the nerve was compressed before surgery, the physical demands of daily life, and general health.
An L4-L5 herniation most often compresses the L5 nerve root, which carries sensation to the top of the foot and controls lifting the foot and big toe. That is why a dragging foot, sometimes called foot drop, is the classic weakness at this level. When weakness has been present before surgery, recovery of strength can lag behind pain relief by weeks or months, because nerve fibers regrow slowly. Pain that has been present for a long time may also take longer to fade than pain of a few weeks’ duration.
Against that backdrop, the milestones described in the previous section apply. Walking on day one, light activity and often desk work within about two to six weeks per MedlinePlus, progressive lifting after six weeks or so, and heavier work later, all under the direction of the treating team. Cleveland Clinic and Mayo Clinic frame full recovery from microdiscectomy in terms of several weeks to a few months depending on activity goals.
Two things genuinely influence how those weeks go. The first is walking, which improves circulation, reduces stiffness and lowers the risk of blood clots after any operation. The second is respecting early restrictions, because the annulus opening is most vulnerable in the first weeks, and Cleveland Clinic places the chance of the same disc herniating again at roughly 5% to 10% over time.
Ask your surgeon for a written plan with specific dates for your own milestones. A generic timeline is a starting point; a personal one is what you actually recover to.
What can go wrong: risks explained without alarm
Every operation carries risk, and honest surgeons spend as much time on this conversation as on the benefits. Mayo Clinic and MedlinePlus list the recognized complications of discectomy, and understanding them makes informed consent real rather than a signature.
Dural tear. The dura, the thin membrane holding spinal fluid, sits directly beside the working area. A small tear can leak fluid. It is usually recognized during surgery and repaired with a stitch or sealant; afterwards it may mean a day or two of lying flat and, occasionally, a headache that settles. It is the most common technical complication of lumbar decompression.
Nerve injury. The root being freed can be bruised by retraction, causing temporary worsening of numbness or weakness. Permanent injury is uncommon but possible, which is why retraction is kept minimal and brief.
Infection. Wound infections are treated with antibiotics chosen by the team; deeper infections are rarer and may need further surgery. Smoking, diabetes and obesity raise the risk, and controlling them beforehand is part of preparation.
Bleeding and blood clots. Bleeding is usually minor. Clots in the leg veins are a risk after any operation, reduced by early walking and, where the team judges appropriate, compression devices or preventive medicines.
Recurrent herniation. The remaining disc can push out new material through the same weakened ring. Cleveland Clinic cites roughly 5% to 10% of people. Some are treated without surgery; some need a repeat operation.
Persistent symptoms. Sometimes the nerve was damaged by long compression and does not fully recover, or back pain from other sources continues. This is not surgical failure so much as the limit of what decompression can address.
Wrong-level surgery, injury to blood vessels in front of the spine, and anesthesia complications are rare but real, and the safety steps described earlier exist because of them.
What are the alternatives to herniated disc surgery?
Surgery is one branch on a wider tree, and understanding the other branches makes the surgical decision clearer.
The first alternative is structured time. The NHS and Mayo Clinic both describe a natural history in which most herniations improve over weeks as the fragment shrinks and inflammation settles. Staying active within pain limits, avoiding prolonged bed rest, and using pain-relieving medicines as directed by a clinician form the foundation. Anti-inflammatory drugs work by dampening the chemical irritation around the nerve; muscle relaxants and nerve-pain medicines are sometimes added for short periods. Which medicines, at what point, and for how long is a prescribing decision that belongs to your clinician.
Physical therapy is the second. Its aim is not to push the disc back in, which no exercise can do, but to restore movement, reduce protective muscle spasm, and build the trunk strength that supports the spine long term. Early work is gentle and often includes positions that ease leg symptoms.
Epidural steroid injection is the third. A clinician places anti-inflammatory medicine near the irritated nerve root under X-ray guidance. Mayo Clinic notes it can reduce pain for a period, buying time for natural recovery, but it does not remove the fragment and its benefit is variable and often temporary.
Other operations are a fourth category for specific situations. Fusion is not a treatment for a simple herniation but may be discussed when there is instability or repeated recurrence at the same level. Artificial disc replacement is used more in the neck than the lower back. Neither is a first step for an uncomplicated herniation.
The realistic framing is this: surgery tends to relieve leg pain faster than waiting, while many people who wait reach a similar place months later. Which trade-off suits you depends on how the pain affects your life, whether weakness is present, and how you weigh risk against time, a conversation to have with your team.
What people often get wrong about herniated disc surgery
Spine surgery attracts myths the way a magnet attracts iron filings. Some of the most common deserve a plain correction.
Myth: the surgeon removes the whole disc. In a lumbar discectomy only the herniated fragment and loose material are removed. The bulk of the disc stays, still doing its job as a cushion. Removing the entire disc is a cervical fusion concept, not a lumbar microdiscectomy one.
Myth: surgery fixes back pain. The operation targets nerve compression and the leg or arm pain that results. Mayo Clinic is explicit that it is less reliable for back pain alone. Someone whose main problem is an aching lower back is usually not a good candidate, however impressive the MRI.
Myth: a bigger operation is safer or more thorough. Open, microscopic, tubular and endoscopic approaches perform the same decompression. The surgeon’s experience with a technique matters more than the incision length.
Myth: you will be in bed for weeks. Walking begins on the day of surgery, and prolonged bed rest is actively discouraged because it stiffens muscles and raises clot risk.
Myth: once operated, the disc is permanently fixed. The annulus was torn before surgery and remains a weak point. Cleveland Clinic’s figure of roughly 5% to 10% recurrence reflects that reality, and it is why early restrictions exist.
Myth: if surgery is not done quickly, the nerve will be permanently damaged. Urgency applies to progressive weakness and to cauda equina syndrome. For pain alone, the NHS and Mayo Clinic both describe a window of weeks in which waiting is reasonable, and many people improve during it.
Myth: an MRI abnormality means surgery is needed. Disc bulges are common in people with no symptoms at all. Imaging is only meaningful when it explains the examination findings and the story the patient tells.
Questions to ask your care team before the operation
A good consultation is a two-way exchange, and surgeons generally welcome specific questions because they signal a patient who will engage with recovery. Bring a written list; memory under stress is unreliable. The questions below are prompts, not a script, and the answers should come from the people who have examined you and seen your imaging.
- Which disc level and which side is the herniation, and does it match my symptoms and your examination findings?
- Is my main problem nerve pain in the leg or arm, or back pain? What can surgery realistically change and what will it not change?
- Have I completed a reasonable trial of nonsurgical treatment, and what would happen if I waited another several weeks?
- Do I have any weakness now, and does that alter the urgency?
- Which approach will you use, microscopic, tubular or endoscopic, and why is it the right one for the shape and position of my herniation?
- How do you confirm the correct level in the operating room?
- What are the specific risks for someone with my medical history, and how often do you see a dural tear or infection in your own practice?
- Will I go home the same day? Who do I call at night if something worries me?
- What movements are restricted, for how long, and when does physical therapy start?
- When can I drive, return to my particular job, and resume the activities that matter to me?
- Which of my current medicines should be reviewed before surgery, and who will make those decisions?
- If pain returns months later, what are the likely explanations and what would the next steps be?
Notice that several questions ask the surgeon to explain their reasoning rather than simply state a plan. That is not a challenge; it is how you learn whether the plan fits your anatomy and your life. Write the answers down, and if anything remains unclear, a second appointment or a second opinion is a normal part of good care.
When to call your doctor
Most recoveries follow the steady arc described earlier. A small number take a turn that needs prompt attention, and knowing the difference is more useful than any timeline.
Seek emergency care immediately, before or after surgery, for any sign of cauda equina syndrome. The NHS lists these red flags: numbness or tingling around the genitals, anus or inner thighs, sometimes described as saddle numbness; new difficulty passing urine, loss of bladder control, or loss of bowel control; and weakness or numbness in both legs that is worsening. These signal compression of the nerve bundle at the base of the spine and are treated as a surgical emergency.
Call your surgical team the same day after the operation for any of the following, which Mayo Clinic and MedlinePlus flag as reasons to be seen:
- Fever, chills, or a wound that becomes increasingly red, warm, swollen or begins to leak fluid or pus.
- Clear, watery fluid draining from the incision, or a headache that is markedly worse when upright and eases lying flat, which can indicate a spinal fluid leak.
- New or worsening weakness in a leg or foot, or numbness that is spreading rather than shrinking.
- Leg pain that escalates sharply after an initial improvement.
- Calf pain, swelling or warmth in one leg, or sudden shortness of breath or chest pain, which can indicate a blood clot and warrant emergency evaluation.
- Pain that is not controlled by the medicines prescribed, or side effects from those medicines that concern you.
For the person still deciding whether to have surgery, the same principle applies. Progressive weakness, symptoms in both legs, or any bladder or bowel change should move the conversation from routine to urgent. Uncertainty about whether something counts is itself a reason to call; teams would far rather hear about a symptom that turns out to be nothing than miss one that mattered.
Frequently asked questions
How painful is herniated disk surgery?
Postoperative pain is usually incision and muscle soreness in the lower back that settles over days, managed with medicines chosen by your team. The radiating leg pain often eases early once pressure on the nerve is removed, though numbness or tingling can linger for weeks to months as the nerve recovers. Some people notice a brief flare of nerve symptoms in the first days. Pain that worsens rather than settles should be reported promptly.
Is herniated disc surgery a major surgery?
It is a real operation under general anesthesia performed millimeters from the spinal nerves, so it deserves respect, but in footprint a lumbar microdiscectomy is among the smaller spine procedures. The incision is about an inch, the operation takes roughly one to two hours according to Cleveland Clinic, and MedlinePlus notes many people go home the same day or after one night. No implants are placed and spinal stability is unchanged.
How painful is a herniated disc on a scale of 1 to 10?
There is no single number, because pain scales measure individual experience rather than tissue damage. Many people describe a severe sciatica flare as among the worst pains they have felt, often rating it high on the scale, while others have mainly numbness or weakness with modest pain. The scale is most useful for tracking your own trend over weeks; improvement is expected in most cases, and worsening or spreading pain is worth reporting.
How long does L4 L5 disc surgery recovery take?
The level itself changes little; the size of the herniation, how long the nerve was compressed, and the demands of your work matter more. Typical patterns from MedlinePlus and Cleveland Clinic include walking on the day of surgery, return to desk work in roughly two to six weeks, gradual lifting after about six weeks, and fuller recovery over a few months. Weakness such as foot drop present before surgery can take longer to improve than pain.
Will I be awake during herniated disc surgery?
Nearly all lumbar microdiscectomies are performed under general anesthesia, meaning you are fully asleep with an anesthesiologist managing your breathing and circulation throughout. Some endoscopic procedures can be done under sedation with local anesthetic, but this depends on the herniation’s position, the surgeon’s technique and your health. The anesthesia team makes this decision with you at the preoperative assessment, and you should raise any concerns about anesthesia there.
How does the surgeon know which disc to operate on?
The level is chosen from your symptoms, examination and MRI together, then confirmed in the operating room with fluoroscopy, a live X-ray. A marker is placed on the skin and adjusted until it sits over the target disc, counting from the sacrum upward. After the incision, an instrument is rested on the bone and a second image is taken. Only when both checks agree with the MRI does the decompression begin.
What is the difference between microdiscectomy and discectomy?
Discectomy is the general term for removing herniated disc material. Microdiscectomy is the modern version performed through a small incision using an operating microscope for magnification. Tubular and endoscopic discectomies use a narrow tube or camera instead. Johns Hopkins and Mayo Clinic describe these as variations on one operation; the decompression of the nerve is the same, and differences lie mainly in incision size and early wound soreness.
Can the disc herniate again after surgery?
Yes. The outer ring of the disc was torn before surgery and remains a weak point, so remaining disc material can push through again. Cleveland Clinic cites roughly 5% to 10% of people experiencing recurrent herniation at the same level. That is the main reason surgeons restrict bending, lifting and twisting in the early weeks. Some recurrences settle without surgery; others may need a repeat operation, a decision for the treating team.
Does herniated disc surgery help back pain?
Usually not as its primary effect. Discectomy relieves pressure on a nerve root, which is why Mayo Clinic describes it as most effective for radiating leg or arm pain. Back pain alone commonly arises from muscles, joints or the disc itself, sources the operation does not address. Someone whose main complaint is an aching lower back without leg symptoms is generally not considered a good candidate, regardless of what the MRI shows.
When can I drive after herniated disc surgery?
Most teams advise waiting until you are no longer taking sedating pain medicines, can sit comfortably for the journey, and can perform an emergency stop without hesitation. For many people that falls within the first one to two weeks, but it varies with pain, the side operated on, and your vehicle. Your surgeon will give specific guidance at discharge or follow-up, and some insurers have their own requirements worth checking.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Living in a Scoliosis Brace: School, Sport, Sleep and Skin Care Day to Day
Living with a scoliosis brace means wearing a rigid, custom-molded shell for a set number of hours each day while the spine is still…

What Spinal Stenosis Surgery Relieves and What It May Not: Leg Pain vs Back Pain
Spinal stenosis surgery, usually a decompression that widens the narrowed canal, is most reliable at easing leg symptoms caused by pinched nerves: the aching,…

Nucleoplasty Recovery: Why Back Pain Can Rise Briefly and When Bending and Lifting Resume
Nucleoplasty recovery usually involves going home the same day, a brief rise in back pain over the first days as the needle path and…

Lifting, Bending and Sitting After Herniated Disc Surgery: Habits That Protect the Repair
After herniated disc surgery, most surgical teams ask patients to avoid lifting anything heavier than a light grocery bag, roughly 5 to 10 pounds,…

When Spinal Fusion Does Not Fuse: Pseudarthrosis Explained and What Revision Involves
A failed spinal fusion, called pseudarthrosis or nonunion, means the bone graft placed between vertebrae did not grow into one solid piece within the…

Who Is a Candidate for Artificial Disc Replacement? Single-Level Disease and Healthy Facets
The typical artificial disc replacement candidate has neck or low back pain traced to a single worn disc, with facet joints and surrounding bone…