

Laparoscopy or Open Surgery for an Ovarian Cyst? What the Keyhole Approach Changes

Key Takeaways
- Most ovarian cysts need no surgery at all; the NHS and Mayo Clinic describe functional cysts typically resolving on their own within a few months.
- Laparoscopy and open surgery remove the same cyst; what differs is the route in, with keyhole incisions of roughly 0.5–1 cm versus a single cut commonly 10–15 cm long.
- The NHS describes same-day or next-day discharge after most laparoscopies and a stay of several days after laparotomy, with recovery often cited at around 6–8 weeks for open surgery.
- Open surgery is usually chosen for very large cysts, cysts with features suspicious for cancer, or complex and emergency cases, and a laparotomy does not by itself mean cancer is present.
- Removing a cyst while preserving the ovary (cystectomy) is the usual aim in premenopausal women, and a single remaining ovary generally maintains cycles, hormones and fertility.
- Sudden severe pelvic pain with vomiting, fever, fainting or cold clammy skin can signal ovarian torsion or rupture and needs urgent medical help, whether or not you have had surgery.
For most ovarian cysts that need surgery, laparoscopy (keyhole surgery through small incisions) is the usual first choice because it typically means a shorter hospital stay and a faster recovery than open surgery. Open surgery, or laparotomy, is generally reserved for very large cysts, cysts with features that raise concern for cancer, or situations where the surgeon needs wider access. The treating team decides based on imaging, blood tests and your overall health.
The ultrasound report sits folded in her bag, read so many times the crease has gone soft. A cyst, 6 centimeters, on the left ovary. The gynecologist used the word laparoscopy, then, almost in passing, mentioned that a bigger cut was sometimes needed. Now she is at the kitchen table searching laparoscopy vs open surgery ovarian cyst at eleven at night, trying to work out which of those two sentences applies to her.
That late-night question is one of the most common ones gynecologists field, and it deserves a clearer answer than a shrug. The two operations remove the same thing. What they change is how the surgeon gets there, how long you stay in hospital, how your abdomen feels for the next few weeks, and, in a minority of cases, how safely a suspicious cyst can be handled.
This explainer walks through both approaches the way a careful clinician would at a consultation with time to spare: what happens, who tends to be offered which, what the recovery actually looks like, and where the popular wisdom gets it wrong.
Why the laparoscopy vs open surgery ovarian cyst question comes up at all
Most ovarian cysts never reach an operating room. An ovarian cyst is a fluid-filled sac that forms on or inside an ovary, and the commonest kind, the functional cyst, is simply part of the monthly cycle misfiring slightly. The NHS notes that most of these are harmless and disappear within a few months without any treatment, and the Mayo Clinic describes functional cysts typically resolving over two to three menstrual cycles.
So the surgical conversation only starts when a cyst refuses to follow that script. It may be persisting on repeat scans, growing, causing pain, or showing features on ultrasound that do not look like a simple bubble of fluid. In a woman past menopause, when functional cysts are no longer expected, even a modest cyst earns closer scrutiny.
Once surgery is on the table, the question splits in two. The first is what to remove: the cyst alone, or the whole ovary. The second is how to reach it: through a few small incisions with a camera, or through a single longer incision that opens the abdomen. People tend to focus on the first question, understandably. Yet it is the second, the route in, that shapes most of what you will physically experience in the weeks afterward.
The honest framing is this: laparoscopy and open surgery are not competing philosophies. They are two tools in the same kit, and a good team chooses between them for reasons that have more to do with the cyst than with preference. Understanding those reasons takes most of the fear out of the decision, because it stops being a mystery and becomes a set of questions with answers.
What actually happens during keyhole surgery for an ovarian cyst
Laparoscopy is surgery performed through small cuts, usually under general anesthesia, using a thin telescope with a camera on the end. The surgeon makes an incision near the navel, typically about a centimeter long, and introduces carbon dioxide gas to lift the abdominal wall away from the organs. That gas creates a working space; without it, the camera would be pressed against a wall of bowel.
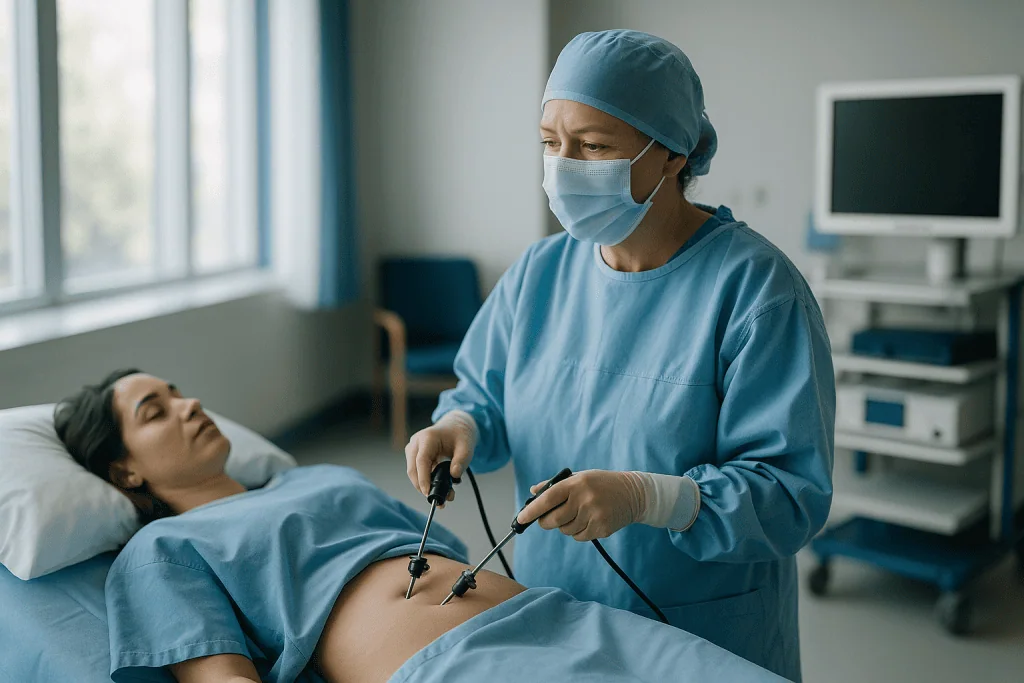
Through that first port the laparoscope goes in, and the pelvis appears on a screen magnified several times. Two or three further incisions, each roughly half a centimeter to a centimeter, are placed lower on the abdomen for the instruments. These are long, slender tools: graspers, scissors, devices that seal blood vessels with heat or energy.
With the ovary in view, the surgeon makes an opening in the ovarian capsule and peels the cyst away from the healthy tissue, much like separating the skin from a peach without bruising the flesh. The cyst is placed in a retrieval bag inside the abdomen and drawn out through one of the ports. If it is large, it may be drained inside the bag first so it fits through the small opening. That bag matters, and we return to why later.
The gas is released, the small incisions are closed with dissolvable stitches or glue, and the whole procedure for a straightforward cyst commonly takes around an hour, though complex cases run longer. MedlinePlus and the NHS both describe this as the standard way to remove most ovarian cysts, with many people going home the same day or the following morning.
What open surgery (laparotomy) for an ovarian cyst involves
Laparotomy is surgery through a single, longer incision in the abdominal wall, large enough for the surgeon to see and work with their hands directly. For ovarian surgery the cut is often horizontal just above the pubic hairline, the same line used for many cesarean births, and typically runs 10 to 15 centimeters. When a cyst is very large or when cancer is a real possibility, a vertical incision from below the navel may be chosen instead, because it can be extended upward if needed.
Inside, the steps mirror laparoscopy: identify the ovary, open the capsule, separate the cyst, control any bleeding, and either preserve or remove the ovary. The difference is scale and access. A surgeon’s hands can feel the texture of tissue, lift a heavy cyst without rupturing it, and inspect the whole abdomen, including the lining, the omentum (the fatty apron over the bowel) and lymph nodes, in a way that is harder through ports.
That direct access is the entire point. The NHS explains that laparotomy is used when a cyst is particularly large or when there is concern that it could be cancerous, because the surgeon may need to remove it intact and take further tissue samples at the same operation. If a cyst looks suspicious, keeping it whole prevents spillage of its contents into the abdomen, which matters for both diagnosis and treatment planning.
The trade-off is recovery. Cutting through the full thickness of the abdominal wall, including muscle and its fibrous covering, demands more healing time. The NHS describes a hospital stay of a few days after laparotomy, compared with a same-day or next-day discharge after most laparoscopies, and a longer road back to lifting, driving and work.
Cystectomy or oophorectomy: what is being removed?
Before the route in matters, the team decides what comes out. An ovarian cystectomy removes the cyst while leaving the ovary in place. An oophorectomy removes the whole ovary, sometimes with the fallopian tube beside it (salpingo-oophorectomy). Either can be done laparoscopically or through an open incision; the approach and the extent are separate decisions.

Cystectomy is generally preferred in women who have not reached menopause, especially those who want children in the future, because preserving ovarian tissue preserves eggs and hormone production. The Mayo Clinic lists it as the usual option for cysts that are benign in appearance. The ovary is remarkably forgiving: even after a cyst wall is stripped away, the remaining tissue typically continues to ovulate and release hormones.
Oophorectomy enters the conversation in a few situations. If the cyst has replaced almost all recognizable ovarian tissue, there may be little left worth saving. If a woman is past menopause, the ovary is no longer producing eggs or meaningful amounts of estrogen, and removing it eliminates the chance of future cysts on that side. And if there is any suspicion of cancer, removing the ovary intact, rather than cutting into it, is standard practice because it avoids spilling cells and gives the pathologist the whole organ to examine.
One nuance that surprises people: a single ovary is enough. Women with one ovary generally still cycle, still ovulate and can still conceive, because the remaining ovary tends to compensate. Losing one ovary is not the same as losing fertility or entering menopause, though it is a reasonable topic to raise with your team if you are concerned about either.
Who is usually offered laparoscopy, and who is asked to wait
The typical laparoscopy candidate has a cyst that looks benign on ultrasound, is causing symptoms or has persisted beyond the window in which it should have resolved, and is not so enormous that it fills the abdomen. The Cleveland Clinic and NHS both describe keyhole surgery as the standard route for cysts of this kind, and that includes common types such as dermoid cysts (containing skin, hair or fatty tissue), endometriomas (cysts of endometriosis, often called chocolate cysts) and simple cystadenomas.
Equally important is who is asked not to have surgery at all, at least not yet. A premenopausal woman with a simple, thin-walled, fluid-only cyst and no symptoms is usually offered watchful waiting: a repeat scan in a few weeks or months to see whether it has gone. The Mayo Clinic describes this wait-and-see approach as appropriate when the cyst is small and looks like a functional cyst. Operating on something that will vanish on its own exposes a person to anesthesia and incisions for no gain.
Someone who is pregnant with a cyst is often monitored rather than operated on unless the cyst is causing problems, because many pregnancy-related cysts resolve on their own. People with significant heart or lung disease may need extra assessment before laparoscopy, since the carbon dioxide gas and head-down position used during the procedure place additional demands on breathing and circulation.
Previous abdominal surgery does not rule out keyhole surgery, but it can mean scar tissue (adhesions) that makes the initial entry trickier. Surgeons have techniques for this, including entering at a different point, and most of the time laparoscopy still proceeds. The treating team weighs all of it together; there is no single number or finding that decides the matter on its own.
When surgeons lean toward an open approach
Three situations push a team toward laparotomy for an ovarian cyst, and each is about safety rather than habit.
The first is suspicion of cancer. Ultrasound features such as solid areas, thick internal walls, irregular growths on the surface or fluid in the abdomen, combined with blood test results and age, feed into a risk estimate. When that estimate is high, guidelines favor removing the cyst and ovary without rupturing them, inspecting the whole abdomen and taking washings and biopsies. The NHS states plainly that a laparotomy is usually recommended if the cyst could be cancerous. That does not mean a laparotomy means you have cancer; it means the team is being careful.
The second is sheer size. A cyst that reaches the navel or above leaves very little room for the gas space laparoscopy depends on, and a large cyst is harder to remove intact through a port. Some surgeons will drain a huge but clearly benign cyst inside a bag and proceed laparoscopically; others judge that open removal is safer. Both are defensible, and your surgeon should be able to explain why one fits your case.
The third is complexity. Dense adhesions from prior surgery or severe endometriosis, suspected spread of infection, or an emergency such as heavy internal bleeding can make an open approach the quicker and safer route to control.
A fourth, less visible factor is what the team is set up to do. Advanced laparoscopic work requires equipment and experience, and an honest surgeon will say if a case sits outside their usual practice. It is entirely reasonable to ask how the recommendation was reached and what the alternative would be.
Laparoscopy vs open surgery for an ovarian cyst: side by side
Putting the two approaches next to each other makes the pattern clear. The figures below are typical ranges described by the NHS and Mayo Clinic, not promises; individual recovery varies with the cyst, the extent of surgery and your general health.
| Feature | Laparoscopy (keyhole) | Laparotomy (open) |
|---|---|---|
| Incisions | Two to four cuts, each roughly 0.5–1 cm | One cut, commonly 10–15 cm |
| How the surgeon sees | Magnified camera image on a screen | Direct view and touch |
| Usual hospital stay | Same day or one night | Several days |
| Typical return to light activity | Days to about two weeks | Several weeks, often cited as 6–8 |
| Pain pattern | Incision soreness plus shoulder-tip pain from residual gas | Deeper wound pain, worse with coughing or sitting up |
| Scarring | Small, often fading to faint marks | One longer scar, usually low on the abdomen |
| Usually chosen for | Benign-appearing cysts of moderate size | Very large cysts, suspected cancer, complex or emergency cases |
| Main limitation | Harder to remove huge cysts intact; needs gas space | Longer recovery, higher wound complication rate |
Two things the table cannot show. First, a laparoscopy can become a laparotomy during the operation if the surgeon finds something unexpected, which is why consent forms usually mention this possibility. Second, the shorter recovery of keyhole surgery is real but not magical: the internal healing of the ovary takes similar time either way. What laparoscopy spares you is the abdominal wall injury, and that is where most of the pain and downtime come from.
Does the keyhole approach change the risks?
Every operation carries risk, and the honest answer is that laparoscopy shifts the risk profile rather than erasing it. MedlinePlus lists the general risks of pelvic laparoscopy as bleeding, infection, injury to nearby organs such as the bowel, bladder or blood vessels, and reactions to anesthesia. Open surgery shares all of these.
Where open surgery carries more risk is in the wound itself. A longer incision through muscle means a higher chance of wound infection, of a hematoma (a collection of blood under the skin) and, over the longer term, of an incisional hernia, where tissue bulges through a weak point in the healed scar. Longer immobility in hospital also raises the chance of blood clots in the leg veins, which is why early walking and compression stockings are routine.
Laparoscopy has a few risks of its own. The initial blind entry of the first port is the moment of greatest potential for injury to bowel or a major blood vessel, which is rare but recognized. The carbon dioxide gas can cause shoulder-tip pain for a day or two as it irritates the diaphragm. In rare cases gas can track into tissue under the skin. And if a cyst ruptures during removal, its contents spill into the abdomen; for a dermoid cyst this can cause chemical irritation of the lining, which is one reason retrieval bags are used.
For a suspicious cyst, the risk calculus flips. Spilling a possibly cancerous cyst can worsen the situation, so the small-incision advantage is outweighed by the need for intact removal. This is not laparoscopy being dangerous; it is the right tool being chosen for the specific job. Your consent discussion should cover which risks are most relevant to your particular cyst.
What the hours and days after surgery usually look like
You wake in a recovery area with a throat that feels scratchy from the breathing tube and an abdomen that feels bloated and tender. After laparoscopy, the most unexpected sensation is often an ache in one or both shoulders. That is referred pain from residual gas pressing on the diaphragm, and it typically eases within a day or two as the gas is absorbed. Walking, warmth and changing position help more than lying still.
Nurses will encourage you to sit up, sip fluids and walk to the bathroom within hours. This is not impatience; movement reduces the chance of clots and helps the bowel wake up. Many people having a laparoscopic cystectomy go home the same day once they can pass urine, eat something light and manage their pain with oral medicine. The NHS describes this same-day or next-day discharge as typical.
After laparotomy, the early days feel different. Coughing, laughing and getting out of bed pull on the incision, and most people need stronger pain control for the first day or two, sometimes through a pump they control themselves. A catheter in the bladder may stay overnight. The bowel is often sluggish for a few days, so meals start small. The NHS describes a stay of a few days before discharge.
Either way, the dressings are usually light. Small laparoscopy incisions are often covered with simple adhesive strips that can get wet in the shower after a day or so, following the team’s instructions. Light vaginal bleeding or spotting for a few days is common after any pelvic surgery. Your team will give specific guidance on wound care, bathing and what pain is expected versus what should prompt a call.
Ovarian cystectomy recovery time: the weeks that follow
Recovery has a rhythm, and knowing it stops you from mistaking normal for wrong. In the first week after laparoscopy, most people are moving around the house, tiring easily and sore at the incisions. By the second week, many have returned to desk work, short walks and light errands. The NHS describes recovery from laparoscopy to treat a condition as ranging from a few days to a few weeks, depending on what was done, with heavier activity and strenuous exercise resuming later.
After laparotomy, the timeline stretches. Fatigue is pronounced for the first two to three weeks, and the abdominal muscles protest when you lift anything heavier than a kettle. Guidance commonly cites around six to eight weeks before full return to lifting, vigorous exercise and physically demanding work, in line with what the NHS describes for open abdominal surgery. Driving usually waits until you can brake hard without flinching and are no longer taking sedating pain medicine; your insurer and surgeon both have a view on that.
Some things follow the same clock regardless of approach. The ovary itself heals internally over weeks, and your next period may come early, late or heavier than usual as the ovary settles. Sexual activity is generally paused until bleeding has stopped and the incisions are comfortable, and your team will give a specific time. If stitches were placed inside the vagina or the cervix was manipulated, that advice may be longer.
Scars soften and fade over months, not weeks. Keyhole marks often end up as faint lines; a laparotomy scar flattens and lightens over a year. A follow-up appointment, often around six weeks, reviews the pathology report and confirms healing. If something in your recovery feels off before then, you do not have to wait for that appointment to ask.
Fertility, hormones and your ovaries after cyst surgery
For many people this is the real question hiding behind the surgical one. Will I still be able to have children? Will this bring on menopause? The answers are reassuring in most cases, with honest caveats.
A cystectomy that preserves the ovary leaves behind tissue that continues to produce eggs and hormones. Some ovarian reserve, the pool of remaining eggs, is inevitably lost when a cyst wall is stripped away, because a thin rim of healthy tissue often comes with it. This loss is generally small for a simple cyst. It can be larger for endometriomas, which tend to be stuck firmly to the ovary, and surgeons try to limit damage by using gentle techniques and minimizing the use of heat near healthy tissue. The approach, keyhole or open, matters less to the ovary than the surgeon’s care in handling it.
Removing one ovary does not trigger menopause. The remaining ovary continues to cycle, and the body’s hormone output is maintained. Fertility with one ovary is possible for most women, though if the remaining ovary is also affected by disease or if you are in your late thirties or beyond, your team may suggest discussing fertility preservation or planning before surgery. That is a conversation worth having early rather than after the fact.
Removing both ovaries, which is uncommon for benign cysts in premenopausal women, does cause immediate surgical menopause. If that is ever a possibility in your case, it should be discussed explicitly before you sign consent, including what hormone management might look like afterward and who would prescribe it. The Johns Hopkins and Mayo Clinic resources on ovarian cysts both stress that the extent of surgery is tailored to age, fertility wishes and what the cyst looks like.
What people often get wrong about ovarian cyst removal surgery
Keyhole surgery is minor surgery. It is not. The incisions are small, but what happens inside is the same operation as the open version, under the same general anesthesia. Treating the first week as if you had a tooth filled is the commonest route to feeling unexpectedly wiped out.
Open surgery means the surgeon thinks it is cancer. Not necessarily. Laparotomy is also chosen for very large cysts, dense scar tissue and emergencies. It can also be a precaution when imaging is ambiguous. Most cysts removed by any method turn out to be benign, and the NHS and Mayo Clinic both emphasize that the great majority of ovarian cysts are not cancerous.
A cyst that is removed cannot come back. The cyst itself does not return, but the ovary that made it remains capable of making another. Functional cysts in particular can recur as long as you ovulate. That is why surgeons remove the cyst, not the tendency.
Draining a cyst is as good as removing it. Simply aspirating the fluid through a needle leaves the cyst wall in place, and the wall is what refills and what the pathologist needs to see. Drainage alone is not standard treatment for a persistent cyst.
Birth control pills shrink existing cysts. The Mayo Clinic is clear that hormonal contraception may reduce the formation of new functional cysts but does not make an existing cyst smaller. Whether it is useful for you is a question for your prescriber, not something to start or stop on your own.
Surgery always means losing the ovary. For benign-appearing cysts in premenopausal women, preserving the ovary is the usual aim, whatever the approach.
Alternatives to surgery: watchful waiting, follow-up scans and hormonal contraception
Surgery is one option among several, and for many cysts it is not the first. The main alternative is watchful waiting: a planned repeat ultrasound, often after six to eight weeks or a couple of menstrual cycles, to see whether the cyst has shrunk or gone. The Mayo Clinic recommends this approach for simple, small, fluid-filled cysts in women who still menstruate, because most such cysts resolve on their own. Waiting is active management, not neglect; it has a scan date attached and a plan for what happens if the cyst persists.
For women past menopause, follow-up is more structured. A small, simple cyst with a normal blood test may still be watched with repeat scans, since many are benign, but the threshold for recommending removal is lower because functional cysts are no longer expected at this life stage. The NHS describes this age-based difference in its guidance on ovarian cyst treatment.
Hormonal contraception is sometimes discussed, not as a treatment for an existing cyst but as a way of reducing new functional cysts in people who form them repeatedly. It works by suppressing ovulation, so the follicle that would have become a cyst never develops. Whether this suits you depends on your health history, your contraceptive needs and your prescriber’s judgment; it is never a substitute for investigating a cyst that looks unusual.
Pain relief with ordinary over-the-counter medicines, heat and rest can manage the discomfort of a cyst that is being watched. What these alternatives cannot do is provide tissue for a pathologist, so when the question is what a cyst actually is, rather than whether it will go away, only removal answers it. Your team will be weighing exactly that trade-off.
Questions to ask your care team
A consultation goes better with questions written down, and a good team welcomes them. These are the ones that tend to unlock the most useful conversation.
- What type of cyst do you think this is, and how confident are you from the scan and blood tests?
- Is surgery necessary now, or is there a safe option to repeat the ultrasound first? What would change your mind?
- Which approach are you recommending, laparoscopy or open surgery, and what about my cyst led you there?
- How likely is it that a laparoscopy would need to be converted to an open operation during surgery, and what would prompt that?
- Are you planning to remove just the cyst or the whole ovary? What would make you change plan once you can see inside?
- How will you protect the healthy ovarian tissue, and how might this affect my fertility or hormones?
- What is the plan if the cyst turns out to be something unexpected on the pathology report?
- How long should I expect to stay in hospital, and when can I realistically return to work, driving and exercise?
- What pain and what bleeding are normal afterward, and what should make me call?
- Who do I contact after hours if something worries me?
You might also ask whether a second opinion is reasonable, particularly if the recommendation is open surgery or removal of an ovary and you feel unsure. Surgeons generally take no offence at this; many will arrange it. The aim is not to second-guess your team but to walk into the operating room understanding why each decision was made.
When to call your doctor
Most recovery is uneventful, and most cysts being watched stay quiet. A few signs, before or after surgery, need prompt attention rather than a wait for the next appointment.
If you have a cyst that is being monitored, the NHS advises seeking urgent medical help for sudden, severe pelvic or abdominal pain, especially if it comes with nausea or vomiting, fever, dizziness or fainting, rapid breathing, or cold clammy skin. These can signal ovarian torsion, where the ovary twists on its blood supply, or a cyst that has ruptured with internal bleeding. Both are emergencies where hours matter. Heavy vaginal bleeding alongside pain also warrants urgent assessment.
After surgery, call your care team or seek urgent care for any of the following: a fever or chills; pain that is getting worse rather than better after the first couple of days, or that is not controlled by the medicine you were given; redness, spreading warmth, swelling or pus at an incision; a wound that opens; vomiting that stops you keeping fluids down; a swollen, hard or very bloated abdomen; difficulty passing urine or burning when you do; heavy vaginal bleeding soaking through a pad an hour; or a painful, swollen or red calf.
Shortness of breath, chest pain or coughing up blood after any operation can indicate a blood clot that has travelled to the lungs and need emergency services immediately.
None of this is meant to alarm. It is a short list precisely because serious problems are uncommon, and knowing it means you can relax about the ordinary aches. Your treating team remains the right place for every decision about your care; this article is a map, not a substitute for the people who have examined you.
Frequently asked questions
Is laparoscopy always better than open surgery for an ovarian cyst?
No. Laparoscopy is the usual first choice for benign-appearing cysts because it means smaller incisions, a shorter hospital stay and a faster recovery. Open surgery becomes the safer option when a cyst is very large, when imaging and blood tests raise concern for cancer, or when scar tissue or an emergency makes keyhole access difficult. The better operation is the one that fits your particular cyst.
How long is ovarian cystectomy recovery time with keyhole surgery?
Many people are moving around within a day or two and back to light work within about two weeks after laparoscopic cystectomy, with the NHS describing recovery from treatment laparoscopy as ranging from days to a few weeks depending on the extent of surgery. Strenuous exercise and heavy lifting usually wait longer. Your surgeon will give a timeline based on what was actually done inside.
What does laparotomy for ovarian cyst recovery look like?
Expect a hospital stay of a few days, more noticeable wound pain when coughing or sitting up, and marked tiredness for the first two to three weeks. Guidance commonly cites around six to eight weeks before returning to lifting and vigorous activity, consistent with NHS descriptions of open abdominal surgery. Walking early, managing pain adequately and following wound-care instructions all help the process along.
Does keyhole surgery for an ovarian cyst mean the cyst was not serious?
Usually it reflects that the cyst looked benign on imaging and was a manageable size, but the approach is not a diagnosis. Every removed cyst is sent to a pathologist, and the report, typically reviewed at follow-up, is what confirms what it was. Occasionally a laparoscopy reveals something unexpected and the surgeon converts to an open operation during the procedure.
Will ovarian cyst removal surgery affect my fertility?
For most people having a cystectomy, fertility is preserved because the ovary stays in place and continues to release eggs. A small amount of ovarian tissue is lost with the cyst wall, more so with endometriomas. Even if one whole ovary is removed, the remaining ovary generally compensates and conception remains possible. Discuss fertility goals with your team before surgery so the plan reflects them.
Can an ovarian cyst come back after surgery?
The specific cyst that was removed does not return, but the ovary remains capable of forming new ones, particularly functional cysts linked to ovulation. Endometriomas can also recur because the underlying endometriosis persists. Follow-up scans and, in some cases, hormonal treatment prescribed by your clinician may be discussed to reduce new cyst formation, though no approach eliminates the possibility entirely.
Why do surgeons use a bag to remove the cyst during laparoscopy?
The retrieval bag contains the cyst so it can be drained and pulled through a small incision without its contents spilling into the abdomen. Spillage matters because dermoid cysts can cause chemical irritation of the abdominal lining, and because a cyst that unexpectedly turns out to be cancerous should not scatter cells. The bag also keeps the whole cyst wall intact for the pathologist.
What is shoulder pain after laparoscopy and how long does it last?
It is referred pain from the carbon dioxide gas used to inflate the abdomen irritating the diaphragm, which shares nerve pathways with the shoulder. It usually eases within a day or two as the gas is absorbed. Walking, changing position, warmth and the pain relief recommended by your team help. It is expected and harmless, though worsening pain with fever or vomiting is not and should be reported.
Can a cyst be drained instead of removed?
Simple aspiration, drawing off the fluid with a needle, is not standard treatment for a persistent ovarian cyst. It leaves the cyst wall behind, which tends to refill, and provides no tissue for the pathologist to examine. Removal of the cyst wall, by laparoscopy or open surgery, both treats the cyst and establishes what it is. Your team may explain why drainage alone is rarely recommended.
Do birth control pills make an existing ovarian cyst go away?
No. The Mayo Clinic notes that hormonal contraception does not shrink an existing cyst, though it may reduce the formation of new functional cysts by suppressing ovulation. Whether it is appropriate for you depends on your health history and contraceptive needs and is a decision for your prescriber. It is never a reason to skip investigating a cyst that looks unusual on ultrasound.
References
- NHS: Ovarian cyst, Treatment
- NHS: Laparoscopy (keyhole surgery)
- MedlinePlus Medical Encyclopedia: Pelvic laparoscopy
- Cleveland Clinic: Ovarian Cysts
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Inside the Operating Room: How a Robotic Hysterectomy Is Performed Through Small Incisions
A robotic hysterectomy removes the uterus through several small abdominal incisions, each roughly fingertip-width. Under general anesthesia the abdomen is inflated with carbon dioxide,…
Can You Get Pregnant After Menopause? Natural Odds, Perimenopause and IVF Options
Once menopause is complete, meaning 12 consecutive months without a period, pregnancy with your own eggs is no longer realistically possible because the ovaries…
Early Pregnancy Symptoms: The First Signals, Week by Week
Early pregnancy symptoms usually begin around weeks 4 to 6, counted from the first day of your last period. A missed period is the…

Who Is a Candidate for Endometriosis Surgery? Pain, Fertility Plans and Imaging Findings
Endometriosis surgery is usually considered for people whose pelvic pain has not eased with hormonal or anti-inflammatory treatment, who are trying to conceive and…

Endometriosis After Surgery: Why Lesions Can Return and How Repeat Treatment Is Planned
Endometriosis can return after surgery because the operation removes visible lesions but not the hormonal environment that drives them. Pooled studies report symptoms or…

When to Start Mammograms and How Often to Have Them
Most women at average risk can begin screening mammograms at age 40 and repeat them every one to two years, depending on the guideline…