

Nerve Block vs General Anesthesia for Surgery: How Anesthesiologists Choose

Key Takeaways
- A nerve block numbs a single region while you breathe for yourself; general anesthesia produces full unconsciousness and usually requires airway support.
- Single-injection nerve blocks typically provide numbness for many hours and often into the next day, which is why they are favored for shoulder and knee surgery with severe early pain.
- The NHS describes serious complications of general anesthesia, including awareness and severe allergic reaction, as very rare, with risk rising mainly with age, illness, and emergency surgery.
- Many operations deliberately combine both: general anesthesia for the procedure itself and a block for pain control that continues into recovery.
- Blood thinners, infection at the needle site, and existing nerve disease in the limb are the main reasons a block may be postponed or replaced.
- After a general anesthetic the NHS advises against driving, alcohol, operating machinery, or signing legal documents for 24 hours, even if you feel alert.
A nerve block numbs one region of the body while you stay awake or lightly sedated; general anesthesia makes you fully unconscious and usually requires airway support. Anesthesiologists choose based on the operation's site and length, your heart and lung health, bleeding risk, your preferences, and how much pain is expected afterward. Many surgeries combine both, using a block for pain control alongside general anesthesia.
The pre-op nurse has just left, and the question that has been circling since the surgery date was set finally lands: do you want to be asleep for this, or awake? For a knee replacement, a shoulder repair, a hernia, even hand surgery, the answer is rarely as simple as picking one door. The nerve block vs general anesthesia conversation is a real one, and it happens thousands of times a day in pre-assessment clinics.
What surprises most people is how little of the decision is about bravery. It is about anatomy, physiology, and arithmetic: where the surgeon needs to work, how long it will take, how your lungs and heart will cope, and what the first night afterward should feel like. Anesthesiologists run through that list quickly because they have done it so often. This article slows it down so you can follow the reasoning, ask sharper questions, and understand why the plan your team suggests looks the way it does.
What is a nerve block, and what actually happens?
A nerve block is an injection of local anesthetic, a medicine that temporarily stops nerves from sending pain signals, placed close to the nerve or bundle of nerves that supplies the part of the body being operated on. Think of it as switching off one branch of the wiring rather than shutting down the whole house.
In practice the process is quieter than most people imagine. You lie or sit in a pre-op bay or the operating room. A monitor tracks your heart rhythm, blood pressure, and oxygen. The anesthesiologist cleans the skin, usually offers light sedation so you feel calm, and then uses an ultrasound probe to watch the nerve, the needle, and nearby blood vessels in real time on a screen. Local anesthetic is spread around the nerve, and within minutes the area begins to feel warm, heavy, and then numb.
Blocks are named for where they go. An interscalene block in the neck numbs the shoulder. A femoral or adductor canal block in the thigh covers much of the knee. A brachial plexus block above or below the collarbone numbs the arm and hand. For longer pain relief, a thin catheter can be left beside the nerve so medicine can keep flowing after surgery.
According to Cleveland Clinic, the numbness from a single-injection block typically lasts many hours and often into the next day, depending on the medicine and the site. During that window you cannot move the limb normally, which is expected, not a complication. The block does not treat the surgical problem itself; it manages the pain of fixing it.
What happens during general anesthesia?
General anesthesia is a medically induced, reversible state of unconsciousness. You do not hear, feel, or remember the operation, and your protective reflexes such as swallowing and coughing are suppressed, so the anesthesiologist takes over the job of keeping your airway open and your breathing steady.
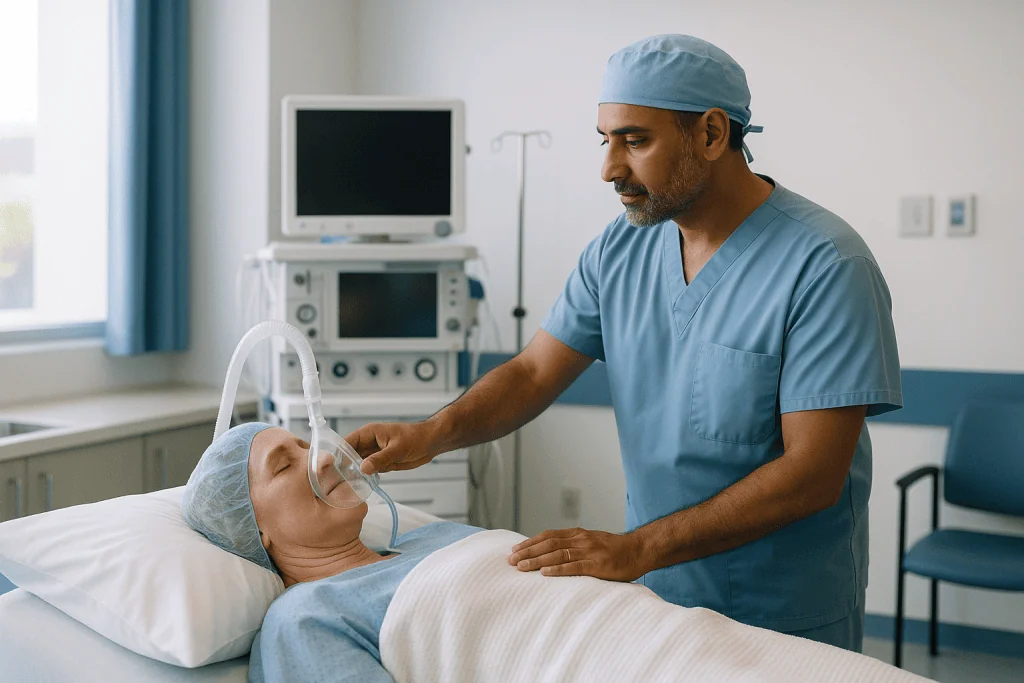
It begins in one of two ways. Most adults receive medicine through an intravenous (IV) line, a thin tube placed in a vein, and lose consciousness in well under a minute. Children, and some adults who prefer it, may breathe an anesthetic gas through a mask instead. Once you are asleep, a breathing tube or a soft laryngeal mask is usually placed to protect the airway and deliver oxygen and anesthetic gas.
Throughout the operation the anesthesiologist adjusts the depth of anesthesia moment by moment, watching heart rate, blood pressure, oxygen saturation, exhaled carbon dioxide, and often brain-activity monitoring. Pain medicines and, when needed, muscle relaxants are given so the surgeon can work. Mayo Clinic describes general anesthesia as a combination of medicines rather than a single drug, chosen for the operation and the patient.
When the surgeon finishes, the anesthetic is stopped, the gas washes out through the lungs, and you wake in the recovery room. The NHS notes that a sore throat, drowsiness, shivering, and nausea are common in the first hours and usually settle without specific treatment. Memory of the recovery room is often patchy, which is why hospitals ask that an adult take you home and stay with you overnight after day surgery.
Nerve block vs general anesthesia: the core differences at a glance
Laid side by side, the two approaches differ less in how safe they are and more in what they ask of the body. The table below summarizes the practical contrasts your anesthesiologist weighs, drawing on NHS, Mayo Clinic, and Cleveland Clinic patient guidance.
| Feature | Nerve block (regional) | General anesthesia |
|---|---|---|
| Consciousness | Awake or lightly sedated | Fully unconscious |
| Breathing | Your own, unassisted | Usually supported with a tube or mask |
| Area affected | One limb or region | Whole body |
| Pain relief after surgery | Continues for hours after the operation | Ends on waking; separate pain medicine needed |
| Common after-effects | Numb, heavy limb; bruising at the needle site | Nausea, sore throat, drowsiness, shivering |
| Suits best | Limb, shoulder, hand, foot, some hernia and eye surgery | Abdominal, chest, brain, long or complex operations |
| Can be combined? | Yes, frequently with general anesthesia or sedation | Yes, often with a block for pain control |
One row deserves emphasis: the pain-relief column. A block keeps working while you are in recovery and often through the first night, which can mean fewer opioid pain medicines in those early hours. General anesthesia removes awareness during the procedure but offers nothing once you are awake, so pain must be managed by other means.
The other row to notice is breathing. Whenever a patient can keep breathing for themselves, anesthesiologists generally prefer it, particularly in people with lung disease, sleep apnea, or difficult airways.
Regional anesthesia vs general anesthesia: why the vocabulary gets confusing
Nerve blocks belong to a larger family called regional anesthesia, meaning any technique that numbs a region of the body while leaving you conscious. The family has three main members, and patients often hear the names used interchangeably.

- Peripheral nerve blocks target a specific nerve or bundle in the neck, arm, trunk, or leg. These are what most people mean by “a block.”
- Spinal anesthesia is a single injection into the fluid around the spinal cord in the lower back, numbing the body from roughly the waist down. It is common for cesarean births, hip and knee replacements, and some urological surgery.
- Epidural anesthesia places a catheter in the space just outside the spinal fluid so medicine can be given continuously, for hours or days, as in labor or after major abdominal surgery.
Sedation sits beside all of these. Mayo Clinic explains that sedation ranges from minimal, where you are relaxed but conversational, to deep, where you drift off and may not remember the procedure, yet still breathe for yourself. When your anesthesiologist says “a block with sedation,” they mean the limb is numb and you are comfortably drowsy, not under general anesthesia.
Why does this matter? Because the regional anesthesia vs general anesthesia choice is not binary. A hand surgery might be done with a block alone. A shoulder repair might use a block plus general anesthesia. A hip replacement might use a spinal plus sedation. Asking “which type of regional, and how much sedation?” gets you a far more useful answer than “awake or asleep?”
How anesthesiologists choose between a nerve block and general anesthesia
Behind every anesthetic plan sits a short checklist that experienced anesthesiologists run almost automatically. Johns Hopkins Medicine describes the anesthesiologist’s role as matching the technique to the operation and to the individual; here is what that matching involves.
Where is the surgery? Blocks work when a limb or a defined region can be numbed completely. Operations inside the chest, skull, or upper abdomen need muscle relaxation and airway control that only general anesthesia provides.
How long will it take? A single-injection block covers a defined window. For an operation expected to run long, the team may add general anesthesia or a catheter so the numbness does not wear off mid-procedure.
What position will you be in? Lying face down or on your side for hours is hard to tolerate awake, and some positions make it difficult to secure the airway in an emergency. Those favor general anesthesia.
What is your medical history? Severe lung disease, sleep apnea, a difficult airway, or a history of problems with general anesthesia push toward regional techniques. Bleeding disorders, blood-thinning medicines, infection at the injection site, or pre-existing nerve damage in the limb push away from blocks.
What will the first night look like? Operations known for severe early pain, such as shoulder and knee surgery, are where blocks earn their keep.
What do you want? Some people find the idea of hearing the operating room unbearable; others want to avoid unconsciousness at almost any cost. Your preference is a legitimate variable, weighed alongside the others, and the final plan is agreed between you and the treating team.
Who is usually offered a nerve block, and who is usually asked to wait?
Nerve blocks are offered most often for operations on the arm, hand, shoulder, knee, ankle, and foot, and for some hernia, breast, and chest-wall procedures where a block can cover the incision. People with heart or lung disease, obstructive sleep apnea, or a known difficult airway are frequently steered toward regional techniques because they keep breathing for themselves and avoid the deeper physiological swings of general anesthesia.
There are also groups for whom a block is usually postponed or set aside, at least for now.
- People taking blood-thinning medicines whose timing has not been coordinated with the surgical team. Bleeding around a nerve can cause pressure damage, so anticoagulants are managed carefully before deep blocks. Never stop or change these medicines on your own; the prescribing clinician decides.
- People with infection over the planned needle site, which risks carrying bacteria deeper.
- People with existing nerve injury or neurological disease in the limb, where a new block could cloud the picture or add risk.
- People with a documented allergy to local anesthetics, which is rare but real.
- Anyone unable to stay still or cooperate, including young children and adults with severe anxiety or confusion, for whom general anesthesia is often the kinder choice.
“Asked to wait” sometimes means literally that. If you arrive with an unexpected chest infection, a poorly controlled blood sugar, or blood pressure far above your usual, the NHS notes that elective surgery of any kind may be deferred until you are well. That is not a judgment; it is risk management, and it applies equally to blocks and general anesthesia.
Is a nerve block safer than general anesthesia? What the evidence shows
It is the question nearly everyone asks, and the honest answer is: for most healthy people, both are very safe, and the differences in major complications are small. The evidence is more nuanced than the common belief that “awake is always safer.”
Start with the baseline. The NHS describes serious complications of general anesthesia, including severe allergic reaction, awareness during surgery, and death, as very rare, with the risk rising mainly with age, existing illness, smoking, excess weight, and emergency rather than planned surgery. Those same factors raise the risk of any anesthetic and of the surgery itself.
Regional techniques avoid airway instrumentation and the deepest effects on blood pressure and breathing, which is why they are favored in people with lung disease or difficult airways. Mayo Clinic notes that regional anesthesia can reduce certain after-effects such as nausea and grogginess. Blocks also provide pain relief that extends past the operation, which can reduce the need for opioid medicines in the first hours.
Where the evidence is less decisive is on hard outcomes. Large comparisons of regional versus general anesthesia for hip and knee surgery have found differences in early recovery markers, but no consistent, large advantage in long-term survival or major complications for the average patient. In plain terms, the choice between a block and general anesthesia rarely changes whether you do well; it changes how the first day feels.
Blocks carry their own uncommon risks, covered in the next section. The safest option is therefore not a fixed answer. It is the one that fits your anatomy, your medical history, and your operation, which is exactly why the decision is individualized by the treating team rather than taken from a chart.
Nerve block side effects and risks explained in plain language
Most nerve block side effects are expected consequences of the technique working. A limb that feels heavy, floppy, tingly, or entirely absent is the block doing its job. Bruising or tenderness at the needle site is common and fades within days. Cleveland Clinic lists soreness, bleeding at the site, and temporary weakness among the usual after-effects.
Some effects depend on location. An interscalene block for the shoulder often numbs the nerve that drives the diaphragm on that side, producing a feeling of mild breathlessness; it is temporary, but it is why people with significant lung disease are assessed carefully before this block. The same block can cause a droopy eyelid and a hoarse voice for a few hours.
Less common risks include:
- Prolonged numbness or weakness lasting days to weeks. Most cases resolve fully; permanent nerve injury is rare, as Cleveland Clinic and the NHS both note.
- Local anesthetic toxicity, where too much medicine reaches the bloodstream. Ultrasound guidance, careful dosing by the anesthesiologist, and continuous monitoring exist precisely to prevent this.
- Infection or bleeding around the nerve, both rare, and the reason blood thinners and skin infections are reviewed beforehand.
- Block failure, where numbness is incomplete and the plan switches to sedation or general anesthesia during the operation.
One practical hazard deserves special mention: a numb limb cannot protect itself. People have burned a hand on a hot pan or dropped a heavy object on a numb foot. Until full sensation returns, the limb should be treated as if it belongs to someone else, kept supported, and never tested against heat or load.
General anesthesia side effects: what is common and what is rare
Waking from general anesthesia is rarely glamorous, and knowing what is ordinary makes the recovery room far less alarming. The NHS lists the most common after-effects as feeling sick or vomiting, shivering and feeling cold, confusion or memory loss for a short period, bladder difficulty, dizziness, bruising at the IV site, a sore throat from the breathing tube, and aches in the jaw or muscles. These usually ease within hours, occasionally over a day or two.
Nausea is the complaint patients most dislike. Risk is higher in women, non-smokers, people with a history of motion sickness or previous post-operative nausea, and after certain operations. Anesthesiologists routinely give preventive anti-nausea medicines when risk is high, and this is one area where adding a nerve block, which reduces the need for opioid pain medicines, can help.
Rarer problems include damage to teeth or lips during airway placement, breathing difficulties, and a severe allergic reaction, which the NHS describes as uncommon. Awareness during surgery, meaning waking while paralyzed, is a real but very rare event; monitoring and modern anesthetic practice are designed to prevent it, and most reported episodes are brief and without pain.
Older adults sometimes experience post-operative confusion or a longer-lasting dip in memory and concentration. Mayo Clinic notes this is more likely in people with existing cognitive problems, heart or lung disease, or a history of stroke. It is not unique to general anesthesia; the stress of surgery, pain, sleep disruption, and hospital environment all contribute. If a relative seems unusually confused after an operation, tell the team promptly; it is treatable and usually temporary.
Why many surgeries use both a nerve block and general anesthesia
If you have been told you will have “a block and a general,” you have not been given a muddled plan. You have been given a layered one, and it is one of the most common strategies in modern anesthesia.
The logic is division of labor. General anesthesia handles the operation itself: unconsciousness, stillness, airway security, and tolerance of awkward positions over a long procedure. The nerve block handles pain, both during surgery, where it means less opioid and less anesthetic gas are needed to keep you comfortable, and after it, where it carries you through the hours when pain is typically at its worst.
Shoulder surgery is the classic example. Operations on the rotator cuff are often performed sitting up, a position that is uncomfortable to maintain awake and that adds complexity to airway management, so general anesthesia makes sense. Yet shoulder pain after these repairs is notoriously severe in the first night, which is exactly what an interscalene block addresses. Knee replacement follows a similar pattern, pairing a spinal or general anesthetic with blocks around the knee.
The practical gain for patients shows up in the recovery room. With a working block, people tend to wake calmer, need less rescue pain medicine, and experience less nausea, which Mayo Clinic links to lower opioid exposure. For day-case surgery that can mean meeting discharge criteria sooner.
There is a trade-off. Combining techniques means accepting the small, separate risks of each. Your anesthesiologist weighs that against the expected pain of the specific operation and your own history, which is why the same procedure may be planned differently for two people in neighboring beds.
What the hours and days after surgery usually look like
Recovery has a rhythm, and it differs noticeably between the two approaches.
After a block alone or with sedation, you usually arrive in recovery alert, able to drink, and in little or no pain. The limb stays numb and heavy. Cleveland Clinic notes that single-injection blocks typically last many hours and frequently into the following day, varying with the medicine and the site. As sensation returns you may feel pins and needles first, then aching; the team will usually ask you to start your prescribed pain medicine before the block fully wears off, so that you are not caught by a sudden surge of pain at two in the morning. Follow the schedule your clinician gives you rather than improvising.
After general anesthesia, the first hour is drowsy. The NHS advises that for 24 hours after a general anesthetic you should not drive, operate machinery, drink alcohol, sign legal documents, or be alone, because judgment and coordination remain impaired even when you feel fine. Nausea and a sore throat are common that evening; most people feel much more themselves by the next day, though tiredness can linger for several days after a longer operation.
In the days that follow, both groups converge. Pain is managed with the plan agreed before surgery, swelling peaks around the second or third day for most limb operations, and physical therapy or gentle movement begins according to the surgeon’s instructions. A limb that had a block may feel slightly odd, with patches of altered sensation, for a few days; most of this fades. Persistent weakness or numbness beyond the expected window should be reported, as covered later.
What people often get wrong about nerve block vs general anesthesia
A handful of myths shape the way people approach this choice, and most of them dissolve under a little evidence.
“Awake means I will see and feel everything.” Almost everyone having surgery under a block receives sedation that leaves them relaxed and often with little memory of the room. Sterile drapes block the view. If you want to be more alert, or more deeply sedated, say so; the depth is adjustable.
“General anesthesia is dangerous for everyone.” The NHS describes serious complications as very rare in healthy people. Risk rises with age and illness, not with the mere fact of being asleep, and those same factors raise the risk of regional techniques too.
“A nerve block means I will not need pain medicine.” It means you may need less, and later. Every block wears off, and the team plans for that moment.
“Blocks cause permanent nerve damage.” Temporary tingling or weakness is relatively common; lasting injury is rare, according to Cleveland Clinic and the NHS. Ultrasound guidance has made needle placement far more precise than in past decades.
“Being awake is braver, or better.” Neither approach is a test of character. The right one is the one that fits your operation and your body.
“I can eat before a block since I will not be asleep.” Fasting rules usually still apply, because a block may need to be converted to general anesthesia if it is incomplete or the operation changes. The NHS fasting guidance for general anesthesia, typically no food for about six hours and clear fluids until about two hours beforehand, is often applied to regional cases for exactly this reason. Follow the instructions your own team gives you.
Questions to ask your care team before surgery
Pre-assessment appointments move quickly, and good questions get better answers. Bring these, and write down the responses.
- Which anesthetic approach are you recommending for my operation, and what makes it the best fit for me specifically?
- If a nerve block is planned, which nerves will it cover, and how long is the numbness expected to last for this type of block?
- Will I be awake, lightly sedated, or deeply sedated during the procedure? Can I choose, or adjust, on the day?
- What is the plan if the block is incomplete or the surgery takes longer than expected?
- Which of my regular medicines, especially blood thinners, diabetes medicines, and blood pressure medicines, should I take on the morning of surgery, and which should I pause? Who makes that call?
- What are the specific risks of this technique for someone with my medical history?
- How will pain be managed once the block wears off, and when should I take the first dose of what you prescribe?
- What should the numb limb feel like tomorrow, and what would be abnormal?
- How long should I expect to stay in the hospital or recovery area?
- Who do I call overnight or at the weekend if something worries me?
Two things make these conversations more productive. First, give a complete history: smoking, alcohol, sleep apnea, previous reactions to anesthesia, and anything a relative experienced under anesthesia. Second, be honest about your preferences. If you dread awareness, or if you have had severe nausea after a previous general anesthetic, those facts change the plan. The anesthesiologist cannot weigh what they do not know, and the final decision is one you reach together.
When to call your doctor after a nerve block or general anesthesia
Most recoveries from either technique are uneventful, but a short list of warning signs should prompt a call to your surgical team, the number on your discharge paperwork, or emergency services if severe.
Seek emergency care immediately for difficulty breathing, chest pain, a racing or irregular heartbeat, severe dizziness or fainting, a seizure, confusion that is worsening rather than clearing, or signs of a severe allergic reaction such as facial swelling, widespread hives, or wheezing. A calf that is swollen, hot, and painful, or sudden breathlessness after limb surgery, can indicate a blood clot and also needs urgent assessment.
Call your surgical or anesthesia team the same day if:
- Numbness, weakness, or tingling in the blocked limb persists well beyond the window your anesthesiologist described, or gets worse after initially improving.
- You develop new weakness or numbness in an area the block was not meant to cover.
- The injection site becomes increasingly red, swollen, hot, or starts leaking fluid.
- You have a fever, severe headache, or stiff neck after a spinal or epidural.
- Pain is uncontrolled despite taking medicine exactly as prescribed.
- Vomiting continues for more than a day, or you cannot keep fluids down.
- You are unable to pass urine many hours after surgery.
A general rule from NHS guidance applies: if you are unsure whether something is normal, ask. Teams would far rather field a phone call about a tingling thumb than hear about a developing problem days later. Keep your discharge sheet and the out-of-hours number somewhere easy to find, and make sure the adult staying with you knows where it is.
Frequently asked questions
What is a nerve block, in simple terms?
A nerve block is an injection of local anesthetic placed next to the nerve or group of nerves that supplies the part of the body being operated on, so pain signals from that area cannot reach the brain. You stay awake or lightly sedated. Anesthesiologists usually guide the needle with ultrasound, and the resulting numbness often lasts many hours after surgery, according to Cleveland Clinic.
Is a nerve block safer than general anesthesia?
For most healthy people, both are very safe and the difference in serious complications is small. Blocks avoid airway instrumentation and may reduce nausea and early opioid use, which helps people with lung disease or sleep apnea. General anesthesia carries very rare serious risks, per the NHS, while blocks carry their own rare risks such as nerve irritation. The safer option depends on your history and operation.
What are the most common nerve block side effects?
The most common effects are a heavy, numb, or weak limb for many hours, plus bruising or tenderness at the needle site. Shoulder blocks can cause temporary breathlessness, a hoarse voice, or a droopy eyelid. Prolonged tingling can occur and usually resolves; permanent nerve damage is rare, according to Cleveland Clinic and the NHS. A numb limb must be protected from heat and injury.
What is the difference between regional anesthesia and general anesthesia?
Regional anesthesia numbs one part of the body while you remain conscious, and includes peripheral nerve blocks, spinal injections, and epidurals. General anesthesia makes you fully unconscious and usually requires a breathing tube or mask. Regional techniques are often paired with sedation so you feel drowsy but still breathe for yourself, which is different from being under general anesthesia.
Will I be awake and feel things during surgery with a nerve block?
You will not feel pain in the blocked area, though you may notice pressure or movement. Most people receive sedation that leaves them relaxed and often with little memory of the operating room, and sterile drapes block the view. If you prefer to be more alert or more deeply sedated, tell your anesthesiologist; the depth can be adjusted during the procedure.
How long does a nerve block last after surgery?
It varies with the medicine used and the site, but Cleveland Clinic notes that a single-injection block typically lasts many hours and often into the following day. A catheter left beside the nerve can extend relief for longer. Your team will usually advise starting prescribed pain medicine before the block fully wears off, following the schedule your clinician gives you.
Can I have general anesthesia and a nerve block at the same time?
Yes, and this combination is common, especially for shoulder and knee surgery. General anesthesia keeps you unconscious and still during the operation, while the block provides pain relief that continues into the recovery room and often through the first night. The combination can reduce the amount of opioid medicine needed, which Mayo Clinic links to less post-operative nausea.
Why would an anesthesiologist refuse a nerve block?
The usual reasons are blood-thinning medicines that have not been timed appropriately, infection over the injection site, existing nerve damage or neurological disease in the limb, a known allergy to local anesthetics, or an inability to stay still. Sometimes the operation itself, such as surgery inside the chest or abdomen, simply needs general anesthesia. The decision rests with the treating team.
Do I still need to fast before surgery if I am only having a nerve block?
Usually yes. A block can be incomplete or the operation can change, and the team may need to convert to general anesthesia, which requires an empty stomach. NHS guidance for general anesthesia is typically no food for about six hours and clear fluids until about two hours before, and many centers apply this to regional cases. Follow your own team’s written instructions.
What should I expect in the 24 hours after general anesthesia?
Expect drowsiness, possibly nausea, a sore throat, shivering, and patchy memory of the recovery room. The NHS advises that for 24 hours you should not drive, drink alcohol, operate machinery, sign legal documents, or be alone, because judgment and coordination remain impaired. Most people feel considerably better by the next day, though tiredness can linger after longer operations.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
How a Nerve Block Is Given: Imaging Guidance, the Injection and What You Feel
A nerve block procedure numbs a specific nerve or group of nerves by injecting local anesthetic, sometimes with a steroid, right beside them. Most…

Joint Injection Aftercare: Resting the Joint, Managing Soreness and When Relief Begins
Joint injection aftercare is usually simple: rest the joint from strenuous activity for a day or two, keep the small dressing clean and dry…

How Neuromodulation Works: What Electrical and Magnetic Stimulation Do to Nerve Signals
Neuromodulation works by delivering carefully controlled electrical currents or magnetic pulses to specific nerves, the spinal cord or brain regions, altering how those cells…

Who May Be a Candidate for Neuromodulation? Conditions, Prior Treatments and Testing
A candidate for neuromodulation is typically someone with a chronic, clearly diagnosed condition, such as persistent nerve-related pain, overactive bladder, or a movement disorder,…

Preparing for an Interventional Pain Procedure: Blood Thinners, Fasting and Imaging Review
Preparing for an interventional pain procedure usually means three things: telling the team about every blood thinner you take so they can decide, with…

Chronic Pain Treatment in Older Adults: Balancing Mobility, Other Conditions and Safety
Chronic pain treatment in older adults usually combines movement-based therapy, pacing, sleep and mood support, and carefully chosen medicines, with injections or procedures considered…