

Sarcoidosis and the Heart: When Lung Sarcoidosis Patients Need a Cardiology Assessment

Key Takeaways
- Clinically obvious heart involvement affects about 5 percent of people with sarcoidosis, but autopsy and imaging studies suggest around a quarter have silent granulomas or scar in the heart muscle.
- The Heart Rhythm Society consensus advises that every sarcoidosis patient be asked about palpitations, fainting and breathlessness and have a 12-lead ECG, with further tests only when something is abnormal.
- Granulomas favor the septum and the atrioventricular node, which is why heart block is one of the most common first signs and why adults under 60 with unexplained advanced heart block are screened for sarcoidosis.
- Cardiac MRI shows scar as patchy late gadolinium enhancement, while FDG-PET shows active inflammation but needs a strict high-fat, low-carbohydrate fast beforehand to avoid false-positive results.
- A pacemaker is standard for advanced heart block regardless of cause, and an ICD is recommended after a sustained dangerous rhythm or when pumping remains severely reduced despite anti-inflammatory treatment.
- Evidence for corticosteroids and steroid-sparing drugs in cardiac sarcoidosis comes from observational studies rather than randomized trials, so clinicians describe conduction recovery as possible, not expected.
People with lung sarcoidosis usually need a cardiology assessment when they have palpitations, fainting or near-fainting, unexplained breathlessness, or an abnormal ECG or echocardiogram. Expert consensus from the Heart Rhythm Society also advises asking every sarcoidosis patient about heart symptoms and checking an ECG, because heart involvement is often silent. The treating team decides whether further imaging, such as cardiac MRI or PET, is needed.
The follow-up appointment is almost over. His lung scans look steadier than last year, his cough has faded, and he is halfway out of the chair when he mentions, almost as an afterthought, that his heart sometimes does a strange little skip on the stairs. The nurse’s pen stops. That pause is the subject of this article: sarcoidosis heart involvement, cardiologist assessment, and who among the many people living with lung sarcoidosis genuinely needs one.
Sarcoidosis is best known as a lung disease, and for most people it stays that way. Yet the same clusters of inflammatory cells that settle in the lungs can settle in the heart muscle, where even a small patch can disturb the electrical wiring that keeps the heartbeat steady.
The frustrating part is that the heart often gives no warning. So the real question is not whether to worry, but which checks are sensible, which symptoms change the plan, and what happens after a referral is made.
How does sarcoidosis affect the heart?
Sarcoidosis is a condition in which the immune system forms tiny clumps of inflammatory cells, called granulomas, in one or more organs. A granuloma is essentially a microscopic knot of immune cells that has walled itself off; in the lungs these knots appear on a chest X-ray or CT scan as scattered nodules and swollen lymph glands. According to the National Heart, Lung, and Blood Institute, the lungs are involved in roughly nine out of ten people with the disease, which is why most patients first meet a respiratory specialist rather than a cardiologist.
The heart is a different kind of neighborhood. It is a muscle, but it is also an electrical organ, and its wiring runs through a narrow corridor of specialized tissue between the upper and lower chambers. A granuloma the size of a grain of rice in the lung is lost among millions of air sacs. The same granuloma sitting in that electrical corridor can slow or block the signal that tells the lower chambers to contract.
Three things can go wrong, sometimes together. Inflammation can swell the muscle wall and irritate it, which breeds abnormal rhythms. Granulomas can interrupt conduction, producing heart block or bundle branch block. And as inflammation burns out, it leaves scar, which stiffens the wall and weakens pumping; scar also creates the detours around which dangerous fast rhythms can circle.
The pattern is patchy rather than uniform. One part of the septum, the wall dividing the two pumping chambers, may be thinned to a thread while the rest of the heart looks normal on a routine scan. That patchiness explains why a single test rarely settles the question and why cardiologists often use several in sequence.
How common is cardiac sarcoidosis in people with lung sarcoidosis?
Two numbers appear in almost every discussion of this topic, and they sit uncomfortably far apart. The Heart Rhythm Society’s expert consensus statement, the most widely used guidance on arrhythmias in cardiac sarcoidosis, notes that clinically obvious heart involvement is found in about 5 percent of people with sarcoidosis. Autopsy studies and modern imaging, however, suggest that around a quarter of patients have some granulomas or scar in the heart muscle, most of it never causing symptoms during life.
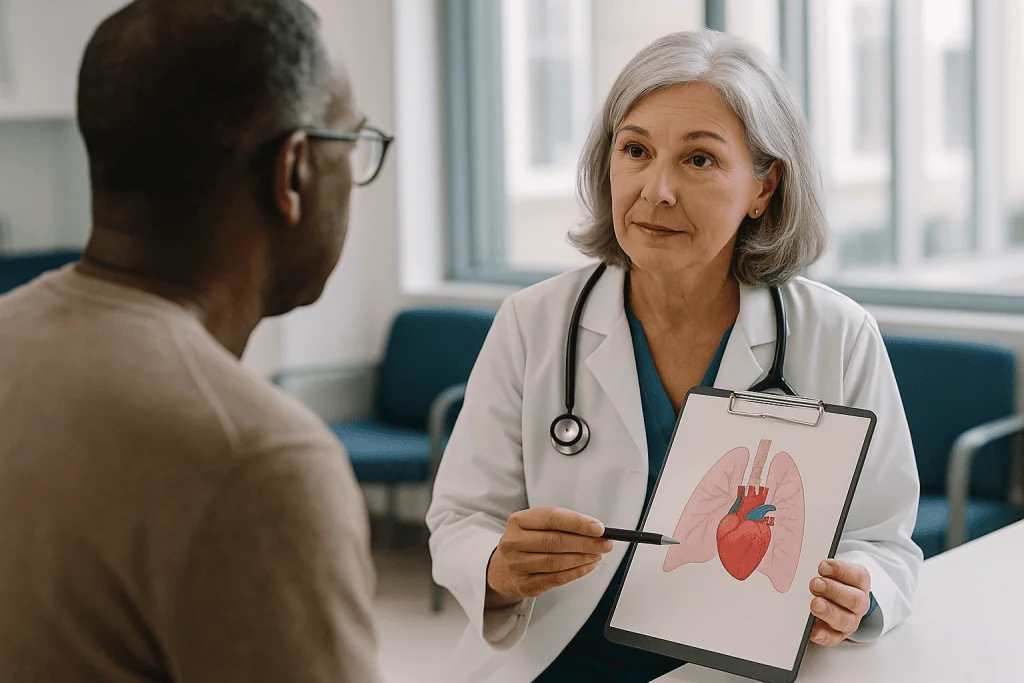
Both figures are true, and the gap between them is the whole clinical problem. Visible heart disease is uncommon; hidden heart disease is not rare. A screening approach that waits for symptoms would miss most of the people in that silent middle group, while an approach that scanned everyone with every available tool would expose many to tests, radiation and anxiety they do not need.
Geography and ancestry also shape the picture. Cardiac involvement has historically been reported more often in Japanese cohorts than in European or North American ones, a difference described in the Heart Rhythm Society document. Whether that reflects genetics, diagnostic habits or both is not fully settled, so clinicians treat it as context rather than as a rule for any individual.
One more point matters. Cardiac sarcoidosis can occur on its own, with no lung disease at all, a form known as isolated cardiac sarcoidosis. It is often discovered only when a younger adult presents with unexplained heart block or a fast rhythm from the lower chambers. The consensus statement specifically advises that people under 60 with unexplained advanced heart block be evaluated for sarcoidosis, a reminder that the heart is sometimes the first organ to speak.
Sarcoidosis heart involvement: when should a cardiologist get involved?
The honest answer is that a cardiologist should be a phone call away for every sarcoidosis patient, but only some need to walk through the clinic door. The Heart Rhythm Society consensus recommends that everyone with sarcoidosis outside the heart be asked about cardiac symptoms and have a 12-lead ECG, the simple tracing of the heart’s electrical activity recorded from stickers on the chest and limbs. Those two steps, a conversation and a tracing, form the floor of good care.
Referral usually follows when any of the following appears, as summarized by the consensus statement and by Mayo Clinic’s patient guidance:
- Palpitations, meaning an awareness of a fast, pounding or irregular heartbeat, especially if episodes are sustained or come with lightheadedness.
- Fainting or near-fainting, which in someone with sarcoidosis is treated as a cardiac symptom until proven otherwise.
- Breathlessness, swelling of the ankles or a drop in exercise tolerance that the lung disease does not fully explain.
- An ECG showing heart block, a bundle branch block, abnormal electrical activity or new changes compared with an earlier tracing.
- An echocardiogram showing a weakened pump, wall thinning or an unusual wall motion pattern.
Cardiac sarcoidosis symptoms overlap heavily with those of lung sarcoidosis, and that overlap is precisely why clinicians lower their threshold. A respiratory physician who hears about a skipped beat on the stairs is not overreacting by ordering a monitor; they are following the guidance.
None of this means a referral is a verdict. Most people sent to cardiology on the strength of a symptom or a minor ECG finding turn out to have normal imaging. The purpose of the visit is to sort the common and benign from the uncommon and important, and only a cardiologist with access to the right tests can do that sorting well.
Why sarcoidosis heart block deserves special attention
Heart block is the finding that most often tips a lung sarcoidosis patient into cardiology. The term means that the electrical signal generated in the upper chambers is delayed or fails to reach the lower chambers, so the heart beats slowly, irregularly or, in the most complete form, on a sluggish backup rhythm. On an ECG it shows up as a stretched or broken link between the small wave from the atria and the larger spike from the ventricles.

Sarcoidosis has an unlucky preference for the exact tissue that carries this signal. The granulomas tend to settle in the upper part of the septum and around the atrioventricular node, the junction box between upper and lower chambers. The Heart Rhythm Society statement describes atrioventricular block as one of the most frequent manifestations of cardiac sarcoidosis, and the Cleveland Clinic’s patient material lists it alongside abnormal rhythms and heart failure as the three main ways the disease declares itself.
What makes sarcoid heart block distinctive is the age of the people it affects. Conduction disease in a 75-year-old is usually ordinary wear on the wiring. The same finding in a 38-year-old is unusual enough that guidelines ask clinicians to look for a cause, and sarcoidosis sits near the top of that list. Hence the consensus recommendation to screen adults under 60 with unexplained second-degree Mobitz type II or complete heart block.
There is a hopeful wrinkle. Because active inflammation rather than permanent scar sometimes causes the block, treatment aimed at the immune system can occasionally allow conduction to recover, something that never happens with age-related fibrosis. The evidence here comes from observational series rather than randomized trials, so clinicians describe it as possible rather than expected. Even so, it changes the conversation: a pacemaker may still be needed for safety, but the inflammation itself is also a target.
What does a cardiologist actually check for sarcoidosis heart involvement?
The first visit is usually less dramatic than people fear. It begins with questions, and the cardiologist will want detail: what the palpitations feel like, how long they last, whether they come with lightheadedness, whether there has ever been a true blackout, and whether anyone in the family died suddenly or young. They will also want the full sarcoidosis story, including which organs are involved and what treatment has already been given.
Then come the standard tests, in roughly this order:
- A resting 12-lead ECG, repeated even if one was done recently, because conduction changes can appear between visits.
- An echocardiogram, an ultrasound of the heart that measures how strongly each chamber squeezes, how thick the walls are and whether any region moves oddly. Thinning of the basal septum or a small bulge in the wall are patterns that raise suspicion.
- Ambulatory rhythm monitoring, a portable recorder worn for 24 hours to two weeks, which catches intermittent heart block or runs of fast rhythm that a single ECG would miss.
- Blood tests, mainly to check kidney and liver function before imaging and to look at inflammatory markers, although no blood test can diagnose cardiac sarcoidosis.
If these are entirely normal and symptoms are mild, the Heart Rhythm Society statement does not require advanced imaging; many cardiologists then arrange a periodic recheck rather than a scan. If anything is abnormal, or if symptoms are compelling despite normal basic tests, the next step is cardiac MRI or PET, covered in the following section.
The craft lies in sequencing. A good cardiologist does not order every test on day one. They choose the next test that would most change what they do, and they explain why. Patients who understand that logic tend to find the process far less frightening.
Cardiac sarcoidosis MRI and PET scans: what the pictures show
Two imaging tools have transformed this field, and they answer slightly different questions. Cardiac MRI uses magnetic fields rather than radiation to build detailed pictures of the heart muscle. After an injection of gadolinium contrast, areas of scar hold on to the dye longer than healthy muscle and glow bright on delayed images, a pattern called late gadolinium enhancement. In sarcoidosis that enhancement is typically patchy, often in the septum or the outer wall, and in places where a blocked artery would not explain it.
MRI is excellent at showing scar and at measuring pumping strength precisely. It is less good at telling whether the inflammation is still active, and that is where PET steps in. A cardiac FDG-PET scan tracks a radioactive sugar molecule; inflammatory cells are hungry for glucose, so active granulomas light up. Because ordinary heart muscle also burns glucose, patients are asked to follow a high-fat, very-low-carbohydrate diet and then fast before the scan, which switches the healthy muscle to burning fat and leaves only inflamed areas bright. Skipping that preparation can make a normal heart look diseased, so centers give detailed instructions.
The Heart Rhythm Society consensus treats a positive MRI or PET as a cornerstone of the clinical diagnosis when biopsy of the heart is not possible, as is usually the case. Heart biopsy samples such a small region of a patchy disease that it frequently misses the granulomas, which is why imaging has largely taken its place.
Neither scan is perfect. Scar on MRI can come from other causes, and PET uptake can be seen in other inflammatory conditions. The result is always read alongside the ECG, echocardiogram, symptoms and the known pattern of sarcoidosis elsewhere in the body. A scan is a strong clue, not a verdict on its own.
Sarcoidosis heart screening tests compared
Patients often ask why they need so many tests when one scan seems to show everything. The table below sets out what each test is for, what it does well and where it falls short, drawing on the Heart Rhythm Society consensus and Cleveland Clinic’s description of the diagnostic pathway.
| Test | What it measures | Strengths | Limitations |
|---|---|---|---|
| 12-lead ECG | Electrical timing and conduction at rest | Quick, painless, widely available; recommended for all sarcoidosis patients | Misses intermittent problems; a normal tracing does not exclude disease |
| Echocardiogram | Pump strength, wall thickness, wall motion | No radiation; measures ejection fraction, the percentage of blood pumped out per beat | Cannot see inflammation; early patchy disease may look normal |
| Ambulatory monitor | Rhythm over days to weeks | Catches brief heart block or fast rhythms that cause symptoms | Only useful if an event happens while wearing it |
| Cardiac MRI | Scar pattern and precise chamber function | Detailed anatomy; scar location helps guide diagnosis and risk discussions | Needs contrast and a long still period; some devices or kidney problems limit use |
| FDG-PET | Active inflammation | Shows whether disease is active and can be repeated to judge treatment response | Radiation exposure; strict diet preparation needed; uptake not specific to sarcoidosis |
The order matters more than the list. ECG and echocardiogram come first for almost everyone. Monitoring is added when symptoms are intermittent. MRI or PET follows when something earlier is abnormal, or when a strong symptom such as fainting demands a definitive look even though the basic tests were clean. Some centers use both MRI and PET together because the pair answers two questions at once: is there scar, and is the inflammation still active?
Who is usually referred, and who is usually asked to wait
Not every sarcoidosis patient is sent to cardiology, and that is deliberate rather than neglectful. The Heart Rhythm Society consensus, the National Heart, Lung, and Blood Institute and the NHS all describe a tiered approach, and it helps to know which tier you are in.
People who are usually referred promptly include anyone with cardiac symptoms, meaning palpitations, fainting, near-fainting or breathlessness out of proportion to the lung disease. Anyone whose screening ECG shows heart block, a bundle branch block or frequent extra beats from the lower chambers is also referred. So is anyone whose echocardiogram shows reduced pumping, wall thinning or a bulge. Younger adults with unexplained advanced heart block are referred even if they have never been diagnosed with sarcoidosis, because the heart may be where the disease first appears.
People who are usually asked to wait, with periodic rechecks rather than a specialist visit, are those with lung or skin sarcoidosis, no cardiac symptoms, a normal ECG and, where one has been done, a normal echocardiogram. For this group the consensus does not call for routine MRI or PET. Watchful follow-up typically means asking about symptoms at each respiratory visit and repeating the ECG at intervals the team chooses.
Waiting is not the same as being forgotten. The watchful group should know which symptoms would move them into the referral group, and they should feel free to raise a new symptom between visits rather than saving it for the next appointment.
There are gray zones. Someone with extensive disease in several organs, or someone about to start a medicine that itself affects heart rhythm, may be referred earlier than the rules alone would suggest. Those judgments belong to the treating team, who weigh the whole picture rather than a single test.
How is cardiac sarcoidosis treated?
Treatment has two aims that run in parallel: calm the inflammation, and protect the heart from the electrical and pumping problems that inflammation and scar produce. The first aim is largely medical, the second often involves devices, and both decisions are made by the cardiology and respiratory teams together.
Corticosteroids are the longest-established anti-inflammatory treatment. They work by broadly suppressing the immune signals that recruit cells into granulomas, and they are typically used when imaging shows active inflammation, especially in the setting of heart block, dangerous rhythms or a weakened pump. The Heart Rhythm Society consensus notes that this practice rests on observational studies rather than large randomized trials; the evidence suggests benefit for conduction recovery and possibly for pumping function, but the certainty is moderate at best, and the document is candid about that.
Because long courses of steroids carry well-known side effects on bone, blood sugar, weight and mood, teams often add or switch to steroid-sparing immunosuppressants, medicines that dampen the immune system through different pathways and allow the steroid to be reduced. Which agent, in what sequence and for how long are individualized decisions, and this article deliberately does not describe regimens; those belong to the prescribing clinician.
Alongside immune treatment, standard heart failure medicines may be used if the pump is weakened, and anti-arrhythmic medicines may be used for fast rhythms, with the same caution that applies to any heart patient. Follow-up imaging, usually PET, is often repeated after some months to see whether inflammation has settled, and the plan is adjusted accordingly.
If you are reading this while taking sarcoidosis medicines for your lungs, the message is simple: do not change anything on the strength of an article. Bring your questions to the team, who can see your scans and know your history.
Pacemakers and defibrillators: when devices come into the conversation
Devices are where cardiac sarcoidosis differs most from ordinary heart disease, and where the Heart Rhythm Society consensus gives its most specific guidance. A pacemaker is a small generator placed under the skin below the collarbone with leads threaded into the heart; it delivers a timed electrical pulse whenever the heart’s own signal is too slow or fails. An implantable cardioverter-defibrillator, or ICD, does everything a pacemaker does and can also deliver a shock to stop a life-threatening fast rhythm.
For heart block that is advanced or symptomatic, a pacemaker is the standard response regardless of cause, and the consensus does not advise waiting to see whether immune treatment restores conduction before protecting the patient. The interesting question in sarcoidosis is whether that device should be a pacemaker alone or an ICD, because scar in the heart muscle raises the risk of fast rhythms from the lower chambers even when the pump looks reasonable.
The consensus recommends an ICD for people with cardiac sarcoidosis who have already had a sustained dangerous rhythm or a cardiac arrest, and for those whose ejection fraction remains severely reduced despite treatment of inflammation. It describes an ICD as reasonable in several other situations, including when a pacemaker is already indicated, when there is unexplained fainting, or when an electrophysiology study, a catheter-based test that deliberately tries to trigger abnormal rhythms, provokes a sustained one.
These are weighty decisions with real trade-offs. ICDs can deliver inappropriate shocks, leads can fail, and the device itself needs lifelong follow-up. The team weighs those harms against the risk of a sudden event, using the scar pattern, the rhythm history and the person’s own values. Nobody should feel rushed through that conversation, and asking for a second discussion is entirely reasonable.
What the following weeks and months usually look like
Once a referral is made, the pace depends on what triggered it. Fainting or a high-grade heart block on the ECG is treated as urgent, and assessment may happen within days or even during a hospital stay. Palpitations with a normal ECG are usually seen in a routine outpatient slot, with the first visit often spent arranging tests rather than announcing conclusions.
A typical sequence runs like this. The first appointment covers history, examination, ECG and echocardiogram, sometimes on the same day. A monitor is fitted and worn for anything from one day to two weeks. If advanced imaging is needed, cardiac MRI or PET follows, each requiring its own preparation and a separate visit. Results are then discussed, often at a joint meeting between cardiology and respiratory specialists before being explained to the patient. From first visit to a settled plan, several weeks is common, and longer where scans must be scheduled around other treatment; these are ranges drawn from how the pathway is described in the Heart Rhythm Society document and in Cleveland Clinic’s patient guidance, not promises for any individual.
If immune treatment is started, the usual rhythm is a period of months on therapy followed by repeat imaging to judge response, then adjustment. If a device is implanted, there is a short recovery during which arm movement on that side is restricted, followed by regular device checks, many of which can now be done remotely from home.
For the watchful group who were not referred, the timeline is slower and gentler: a symptom question at each lung clinic visit and a repeat ECG at intervals the team sets. The NHS notes that sarcoidosis often settles over months to a few years, and heart surveillance tends to follow the overall arc of the disease, becoming lighter as the lungs quieten.
What people often get wrong about sarcoidosis and the heart
Myths cluster around this topic because the disease is uncommon and the heart is frightening. Five deserve correcting.
The first is that if the lungs are quiet, the heart must be too. Cardiac involvement does not track neatly with lung activity; people with mild or improving lung disease can have active inflammation in the heart, and isolated cardiac sarcoidosis exists with no lung disease at all. Lung stability is reassuring, but it is not a heart test.
The second is that a normal ECG rules out heart involvement. It does not. The ECG is recommended for everyone precisely because it is cheap and catches the most dangerous conduction problems, yet the Heart Rhythm Society consensus is clear that a normal tracing cannot exclude disease, which is why symptoms and the echocardiogram are weighed alongside it.
The third is that any palpitation means cardiac sarcoidosis. Most palpitations in sarcoidosis patients, as in everyone else, come from harmless extra beats, caffeine, anxiety, poor sleep or the medicines used to treat the lungs. They warrant a check, not alarm.
The fourth is that a bright spot on a PET scan is a diagnosis. Without the strict dietary preparation, healthy heart muscle takes up the tracer and can mimic disease, and uptake also occurs in other inflammatory conditions. Scans are read in context, never alone.
The fifth is that treating the inflammation makes a device unnecessary. Immune treatment may allow conduction to recover in some people, but the consensus still advises pacing for advanced heart block and considering an ICD where scar or rhythm history raises risk. Medicines and devices are partners, not alternatives, and the balance between them is set by the treating team.
Questions to ask your care team
A cardiology referral can feel like being handed to strangers mid-story. Arriving with questions turns the visit into a conversation. The following are drawn from what patients most commonly want to know, and from the decision points the Heart Rhythm Society consensus highlights.
- What exactly prompted this referral: a symptom, an ECG finding or an echo result, and how concerning is that finding on its own?
- Which tests do you plan first, and what would each result change about my care?
- If I need a cardiac MRI or PET scan, what preparation is involved, and who will explain the diet instructions before PET?
- How will the cardiology and respiratory teams share information, and who is my main point of contact if a new symptom appears?
- If the tests are normal, how often should I be rechecked, and which symptoms should bring me back sooner?
- If inflammation is found, what are the treatment options, what are the main side effects, and how will you judge whether treatment is working?
- Is a pacemaker or ICD being considered, and if so, what are the specific reasons in my case and the trade-offs of each option?
- Do any of my current sarcoidosis medicines affect heart rhythm, and should anything be reviewed because of this referral?
- Are there activities, including exercise or driving, that you would like me to limit while the assessment is under way?
- Who should I call, and at what number, if I faint or have sustained palpitations outside clinic hours?
Write the answers down or bring someone to listen with you. The point of these questions is not to challenge the team but to understand the plan well enough to follow it, and to know which door to knock on when something changes.
When to call your doctor
Most of the time, sarcoidosis and the heart is a story of careful checking rather than emergencies. Some situations, though, should never wait for the next scheduled appointment, and the guidance from the National Heart, Lung, and Blood Institute, Mayo Clinic and the Heart Rhythm Society is consistent on which ones.
Call emergency services, rather than your clinic, if you faint or black out, especially during exertion or without warning; if you have chest pain or pressure that does not settle within minutes; if your heart races persistently and you feel faint, confused or short of breath with it; or if you develop sudden severe breathlessness. Someone who collapses and does not respond needs immediate CPR and a defibrillator, and bystanders should call for help first.
Contact your doctor the same day if you notice new or worsening palpitations lasting more than a few minutes, repeated episodes of lightheadedness or near-fainting, a heart rate that feels unusually slow or irregular, new swelling of the ankles or abdomen, or breathlessness when lying flat that forces you to prop yourself up on pillows. New breathlessness out of proportion to your lung disease deserves the same prompt call.
If you already have a pacemaker or ICD, contact your device clinic if you receive a shock, feel the device vibrate or beep, or notice redness, swelling or discharge at the implant site. A single shock with full recovery is usually handled by an urgent clinic review; two or more shocks in a day, or a shock followed by continuing symptoms, is an emergency.
When in doubt, call. The teams who look after sarcoidosis patients would far rather hear about a symptom that turns out to be nothing than learn about one that was saved for next time.
Frequently asked questions
What are the most common cardiac sarcoidosis symptoms?
Palpitations, fainting or near-fainting, and breathlessness or ankle swelling that the lung disease does not explain are the most common cardiac sarcoidosis symptoms. Many people have none at all, which is why guidelines recommend an ECG for everyone with sarcoidosis rather than relying on symptoms. Any blackout in a sarcoidosis patient is treated as a heart symptom until a cardiologist has looked.
Does everyone with lung sarcoidosis need to see a cardiologist?
No. Expert consensus recommends that everyone with sarcoidosis be asked about heart symptoms and have an ECG, but a cardiology referral is usually made only when symptoms, the ECG or an echocardiogram are abnormal. People with no cardiac symptoms and normal basic tests are typically monitored through their respiratory clinic with periodic rechecks rather than seen by a specialist.
Why does sarcoidosis heart block happen in younger adults?
Sarcoidosis heart block happens because granulomas settle in the conduction tissue of the septum, interrupting the signal between upper and lower chambers. Age-related conduction disease is common after 70 but unusual in younger adults, so unexplained advanced heart block in someone under 60 prompts a search for a cause, and the Heart Rhythm Society consensus names sarcoidosis as one to look for.
What does a cardiac sarcoidosis MRI show?
A cardiac sarcoidosis MRI shows areas of scar that hold on to gadolinium contrast and glow bright on delayed images, usually in a patchy pattern in the septum or outer wall that does not match a blocked artery. It also measures pumping strength precisely. MRI is less able to show whether inflammation is active, which is why a PET scan is sometimes added.
Can a normal ECG rule out heart involvement in sarcoidosis?
No. A normal ECG is reassuring and catches the most dangerous conduction problems, but it cannot exclude cardiac sarcoidosis because the disease is patchy and often silent on a resting tracing. That is why clinicians weigh symptoms and the echocardiogram alongside it, and why a monitor or advanced imaging is used when the story does not fit the tracing.
What is the purpose of sarcoidosis heart screening if most people are fine?
Sarcoidosis heart screening exists to find the minority with conduction disease, dangerous rhythms or a weakening pump before a serious event, since these problems can be silent. The approach is deliberately light, a conversation and an ECG for everyone, with imaging reserved for those with abnormalities, so that most people are reassured without unnecessary scans or radiation.
Why do I need a special diet before a cardiac PET scan?
Healthy heart muscle normally burns glucose, so without preparation it would take up the sugar-based tracer and look inflamed. A high-fat, very-low-carbohydrate diet followed by fasting switches the normal muscle to burning fat, leaving only inflamed areas bright. Skipping the preparation can produce a false-positive scan, which is why centers give detailed instructions and sometimes repeat the test.
Can treating the inflammation reverse sarcoidosis heart block?
Sometimes, but it is not guaranteed. Observational studies summarized in the Heart Rhythm Society consensus suggest conduction can recover in some people when active inflammation is treated, something that never happens with age-related scar. Because the evidence is not from randomized trials and recovery is unpredictable, pacing is still advised for advanced heart block while inflammation is addressed.
Will I need an ICD if I have cardiac sarcoidosis?
Not necessarily. An ICD is recommended for people who have had a sustained dangerous rhythm or whose pumping remains severely reduced despite treatment, and it is considered reasonable in several other situations such as unexplained fainting or when a pacemaker is already needed. Many people with mild findings do not need one. The decision rests with the treating team after weighing risks and benefits.
Can cardiac sarcoidosis occur without lung disease?
Yes. Isolated cardiac sarcoidosis affects the heart alone and is often discovered when a younger adult presents with unexplained heart block or a fast rhythm from the lower chambers. Because there is no lung disease to point the way, diagnosis relies on cardiac MRI, PET and sometimes biopsy of other tissues, and it is one reason cardiologists screen for sarcoidosis in unexplained conduction disease.
References
- Sarcoidosis – National Heart, Lung, and Blood Institute (NIH)
- Sarcoidosis – NHS
- Sarcoidosis – MedlinePlus
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Aortic Aneurysm Repair Recovery: Hospital Nights, Wound Healing and Weeks Back to Routine
Recovery after aortic aneurysm repair depends mainly on the technique. After endovascular repair (EVAR) through the groin, people often leave hospital within a few…
How Dangerous Is a 4 Cm Aortic Aneurysm? Sizes, Surveillance and Screening
A 4 cm aortic aneurysm is classed as small. In the largest surveillance trials, aneurysms between 4.0 and 5.5 cm ruptured at roughly 1%…

Before Coronary CT Angiography: Caffeine, Fasting and Kidney Function Checks
To prepare for coronary CT angiography, most people are asked to avoid caffeine for roughly 12 hours, stop eating about 4 hours beforehand while…

How Is Deep Vein Thrombosis Treated in Pregnancy and After Surgery? Adapting the Plan
Deep vein thrombosis in pregnancy and after surgery is treated with anticoagulant medicines that stop the clot growing while the body slowly dissolves it.…

Pulmonary Embolism Recovery: Restarting Activity Gradually and What the First Months Involve
Pulmonary embolism recovery time varies widely. Most people feel noticeably better within a few weeks, but full recovery of stamina commonly takes several months,…

Metabolic Health: The Five Markers That Define It and How Few Adults Meet Them
Metabolic health is usually defined by five markers measured without medication: a waist circumference below 40 inches for men and 35 for women, fasting…