

What Cornea and External Disease Specialists Treat: Infections, Pterygium and Dystrophies

Key Takeaways
- A cornea and external disease specialist is an ophthalmologist with additional fellowship training in the cornea, conjunctiva, tear film and eyelid margins, and is referred to for complex, progressive or surgical problems.
- The cornea has no blood vessels, which is why donor tissue for transplants does not routinely need blood or tissue matching, according to the NHS and Mayo Clinic.
- Contact lens habits, especially sleeping in lenses or exposing them to water, are among the leading avoidable risk factors for infectious keratitis, per Mayo Clinic.
- Fuchs dystrophy is a failure of the cornea's inner pump layer, typically producing morning blur that clears through the day, with symptoms most often appearing in the 50s and 60s (Mayo Clinic).
- Corneal cross-linking for keratoconus aims to stabilize the cornea and slow progression; it does not reverse an existing cone, and vision correction still comes from lenses.
- Full recovery of vision after a full-thickness corneal transplant can take up to 18 months, whereas endothelial-only grafts commonly improve over weeks to months (NHS).
A cornea and external disease specialist is an ophthalmologist with extra fellowship training in the clear front window of the eye and the surface tissues around it. They diagnose and manage corneal infections (keratitis), pterygium, inherited dystrophies such as Fuchs, keratoconus, severe dry eye and ocular surface injury, and they perform corneal surgery, including transplants and cross-linking, in partnership with your regular eye care team.
The referral letter said three words she had never seen together: cornea, external, disease. She read it twice in the parking lot. Her optometrist had noticed something at a routine check, a faint haze at the back of the cornea, and wanted a second set of eyes on it. Not an emergency, he said. Just the right person for this particular tissue.
That is how most people meet a cornea and external disease specialist. Not through a dramatic injury, but through a quiet handoff: a contact lens ulcer that is not healing on schedule, a fleshy growth creeping in from the corner of the eye, a family history of cloudy corneas, or dry eye that has stopped responding to the usual advice.
This explainer walks through what this subspecialty covers, what actually happens in the clinic, which conditions land on their desk, and what the days after a diagnosis or a procedure tend to look like. Every decision along the way stays with your treating team; the goal here is to make the conversation easier.
What does a cornea and external disease specialist actually do?
Think of the eye as a camera. The retina is the film at the back, and a cornea and external disease specialist looks after the lens cap and the case: the cornea itself, the conjunctiva (the thin membrane over the white of the eye), the tear film, and the eyelid margins that keep the surface wet and clean. In medicine this whole territory is called the ocular surface.
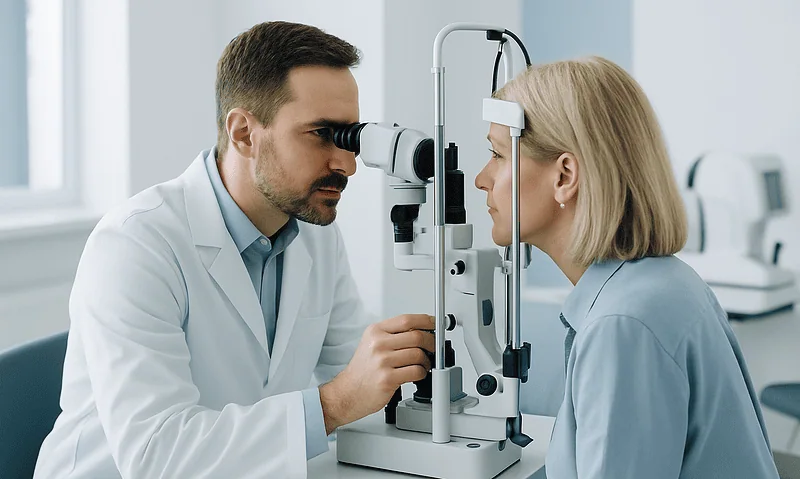
Their day splits roughly into three kinds of work. The first is detective work: examining the cornea under a slit lamp, a microscope with a narrow beam of light that lets the doctor see each layer in cross-section, then adding tools such as corneal topography (a computer map of the cornea’s shape) or specular microscopy (a photograph of the cells lining its inner surface). The second is medical management: choosing the right class of eye drop for an infection, an inflammatory flare or a chronically dry surface, and adjusting the plan as the tissue responds. The third is surgery, which ranges from removing a pterygium in under an hour to replacing a full-thickness cornea with donor tissue.
What makes the subspecialty distinct is the size of its canvas. The cornea is about half a millimeter thick in the center, according to MedlinePlus, and its transparency depends on a precise arrangement of collagen fibers and a single layer of pump cells on its inner face. A scar the width of a pencil dot can drop vision several lines on the chart. The specialist’s job is to protect that clarity, restore it where possible, and be honest about where the limits lie.
What is a cornea specialist called, and how does a corneal specialist differ from an ophthalmologist?
The formal title is usually cornea and external disease specialist, though you will also hear corneal specialist, cornea surgeon, or anterior segment surgeon (the anterior segment is the front third of the eye). All describe the same person: a fully qualified ophthalmologist, a medical doctor trained in eye disease and surgery, who has completed an additional fellowship, typically one to two years, focused on the cornea and ocular surface.

So the question of corneal specialist versus ophthalmologist is a bit like asking about a cardiologist versus an internist. Every cornea specialist is an ophthalmologist; not every ophthalmologist is a cornea specialist. A general ophthalmologist can diagnose and treat many corneal problems, including straightforward infections, abrasions and mild dry eye. The subspecialist is brought in when the problem is unusual, stubborn, sight-threatening, or surgical.
Optometrists sit in this picture too. They are often the first to spot a corneal change during a routine exam and can manage a good deal of surface disease. Referral tends to happen when the diagnosis is uncertain, when a condition is progressing, or when surgery is on the table.
People often search for the best corneal specialist in their city. It is worth knowing that no medical body ranks individual doctors, and any list that claims to is marketing rather than evidence. Reasonable things to check instead are board certification in ophthalmology, completion of a cornea fellowship, whether the practice has the imaging equipment described above, and whether the specialist works closely with an eye bank if transplantation might be needed. Your referring clinician can usually name colleagues they trust.
How the cornea works: five layers and a pump
The cornea has no blood vessels. It draws oxygen from the air and nutrients from tears and the fluid behind it, which is why a contact lens that blocks oxygen for too long can cause trouble. That absence of blood also gives it a rare kind of immune privilege, one reason donor corneas can be transplanted without the tissue matching required for a kidney or heart, as the NHS notes.
From front to back, the layers are:
- Epithelium – a thin skin of cells that renews itself every week or so and heals small scratches quickly. Most abrasions and many infections start here.
- Bowman’s layer – a tough sheet under the epithelium that does not regenerate; damage here can leave a permanent mark.
- Stroma – about 90 percent of the cornea’s thickness (MedlinePlus), made of collagen fibers arranged so regularly that light passes straight through. Scars, thinning and many dystrophies live here.
- Descemet’s membrane – a thin elastic basement layer.
- Endothelium – a single layer of cells that never divides after birth. Its job is to pump fluid out of the stroma so the cornea stays compact and clear.
That last layer explains a lot of what a cornea specialist sees. Everyone is born with a fixed supply of endothelial cells, and the count falls slowly with age. If disease or surgery pushes it below a critical threshold, fluid seeps in, the cornea swells, and vision fogs, especially first thing in the morning. Fuchs dystrophy, the most common reason for a transplant in many countries, is essentially a failure of this pump.
What are the common conditions that affect the cornea?
The list of conditions that affect the cornea is long, but a handful account for most referrals. Grouping them by mechanism makes the landscape easier to read.

| Group | Examples | What goes wrong | Typical first management |
|---|---|---|---|
| Infection | Bacterial, fungal, viral (herpes simplex, herpes zoster) and amoebic keratitis | Microbes invade the epithelium or stroma, causing an ulcer and inflammation | Targeted anti-infective drops chosen for the organism; close follow-up |
| Growths | Pterygium, pinguecula | Sun- and wind-driven overgrowth of conjunctiva onto or beside the cornea | Lubricants and UV protection; surgery if vision or comfort is affected |
| Dystrophies | Fuchs endothelial dystrophy, lattice, granular, map-dot-fingerprint | Inherited changes in one layer that cloud the cornea or weaken its surface | Monitoring; drops for surface symptoms; transplant in advanced cases |
| Shape disorders | Keratoconus, post-surgical ectasia | Progressive thinning and bulging into a cone, distorting focus | Specialty contact lenses; corneal cross-linking to slow progression |
| Surface disease | Dry eye, blepharitis, allergic and autoimmune conjunctivitis | Unstable tear film and chronic inflammation damage the epithelium | Lid hygiene, lubricants, anti-inflammatory drops as prescribed |
| Injury | Abrasions, chemical burns, foreign bodies, scars | Mechanical or chemical damage to one or more layers | Irrigation, protective measures, scar management, sometimes surgery |
Two threads run through the table. First, many corneal problems announce themselves the same way: redness, light sensitivity, blur, watering and a gritty or sharp pain, which is why an examination rather than a symptom list is what settles the diagnosis. Second, the cornea has a limited menu of ways to fail: it gets infected, it scars, it swells, it thins, or its surface dries out. Nearly every treatment aims at one of those five failures.
Corneal infections: why keratitis is treated as urgent
Keratitis is the medical term for inflammation of the cornea, and infectious keratitis means a microbe is responsible. It is the diagnosis cornea specialists worry about most in an otherwise healthy person, because a corneal ulcer can deepen from surface to full thickness in days and leave a permanent scar over the pupil.
Bacteria are the most frequent culprits, and contact lenses the most frequent doorway. Mayo Clinic lists lens wear, especially sleeping in lenses, swimming or showering in them, and cleaning them with tap water, among the main risk factors. Fungal keratitis often follows injury with plant material, a thorn or a branch. The herpes simplex virus, the same one behind cold sores, can hide in the nerve that supplies the cornea and flare repeatedly, each episode risking scar and reduced sensation. A free-living amoeba, Acanthamoeba, is rare but notorious for slow, painful infections in lens wearers exposed to water.
In clinic, the specialist may gently scrape the ulcer to send cells for culture, then start drops chosen for the most likely organism and adjust once results return. The classes involved are antibacterial, antifungal or antiviral, and the course typically runs from days to several weeks depending on the organism and depth, according to Mayo Clinic; your prescriber sets the exact schedule and will often want to see you again within a day or two. Corticosteroid drops, which calm inflammation, are sometimes added later to limit scarring, but only once the infection is clearly under control, because they can worsen fungal and some viral disease.
Deep or central ulcers that heal with a dense scar may eventually be discussed for transplantation, once the eye has been quiet for months.
Pterygium: the growth people call surfer's eye
A pterygium (pronounced tuh-RIJ-ee-um) is a wedge of fleshy, pink tissue that grows from the conjunctiva onto the cornea, almost always from the side nearest the nose. The nickname surfer’s eye is apt: it is strongly linked to years of ultraviolet light, wind and dust, and is more common closer to the equator and in people who work or play outdoors. A pinguecula is its milder cousin, a yellowish bump on the white of the eye that never crosses onto the cornea.
Most pterygia are slow and, for long stretches, silent. Some redden and feel gritty in wind or air conditioning. The concern for a cornea specialist is twofold. As the growth advances it can pull on the cornea and induce astigmatism, a distortion of focus, long before it reaches the pupil. If it does reach the visual axis, it blocks light directly.
Early management is conservative: wraparound sunglasses and a brimmed hat to cut UV exposure, lubricating drops for irritation, and short courses of anti-inflammatory drops if it flares, as prescribed. Surgery enters the conversation when vision is affected, when astigmatism is rising on serial measurements, when the eye is persistently inflamed, or when appearance is a genuine burden to the person.
The operation itself is usually done under local anesthesia in well under an hour. The growth is peeled from the cornea, and the bare area is covered with a small graft of the person’s own conjunctiva, taken from under the upper lid, and secured with sutures or tissue glue. Covering the defect this way is the standard approach because pterygia can regrow, and recurrence is the main long-term risk your surgeon will discuss. A light-sensitive, scratchy eye for one to two weeks is typical while the surface heals.
Corneal dystrophies and thinning disorders: Fuchs, keratoconus and their relatives
A corneal dystrophy is an inherited condition in which abnormal material builds up in one layer of the cornea, or in which a layer gradually fails. Dozens are described; most are rare and many are found incidentally. Two related conditions dominate the clinic.
Fuchs endothelial dystrophy is a slow loss of the pump cells on the cornea’s inner surface. Mayo Clinic describes symptoms typically appearing in people in their 50s and 60s, with women affected more often than men, and notes it often runs in families. The hallmark is blurred, hazy vision on waking that clears over the morning, because fluid accumulates overnight when the closed lid stops evaporation. Later, tiny painful blisters can form on the surface. Early Fuchs is monitored; the specialist may photograph the endothelium yearly and measure corneal thickness. When swelling becomes constant, a transplant of only the inner layer, called endothelial keratoplasty, is the usual option discussed.
Keratoconus is not strictly a dystrophy but sits in the same corner of the clinic. The stroma weakens and the cornea bulges forward into a cone, causing worsening astigmatism and blur that glasses cannot fully correct. Cleveland Clinic notes it usually begins in the late teens or twenties and may progress for years before stabilizing. Rubbing the eyes vigorously is a recognized aggravating habit. Management runs from rigid or scleral contact lenses, which create a smooth optical surface over the cone, to corneal cross-linking, an outpatient procedure that uses riboflavin drops and ultraviolet light to stiffen collagen and slow progression. Cross-linking aims to stabilize, not to reverse the cone, and it is offered when measurements show the disease is still changing.
Other dystrophies, such as lattice or granular, deposit material in the stroma and may be smoothed with a laser or, rarely, need a transplant.
External disease: dry eye, blepharitis and the inflamed surface
The external in the specialty’s name covers everything that touches the cornea from outside: tears, lids, conjunctiva. Diseases here rarely threaten sight quickly, but they generate more clinic visits than any other category and can make life miserable.
Dry eye disease is the headline. Mayo Clinic describes two broad mechanisms: not making enough watery tears, or making tears that evaporate too quickly because the oily layer produced by the meibomian glands along the lid margin is deficient. The second type is far more common and is closely tied to blepharitis, a chronic inflammation of the lid edges. Screen time, low-humidity environments, certain medications, hormonal change and autoimmune conditions such as Sjögren’s syndrome all feed into it. The paradox many people notice, a dry eye that waters constantly, happens because an irritated surface triggers reflex tearing that lacks the oil to stay put.
A cornea specialist looks past the symptom to the surface: staining the cornea with a dye to reveal damaged cells, timing how quickly the tear film breaks up, and examining the glands. Management is layered rather than single-shot. Warm compresses and lid cleaning address the glands. Preservative-free lubricants replace what is missing. Where inflammation drives the problem, prescription anti-inflammatory drop classes may be added, with effect often judged over weeks to months rather than days, as Mayo Clinic notes. Tiny plugs in the tear drainage ducts can hold moisture on the eye longer.
Allergic conjunctivitis, contact-lens-related inflammation, and autoimmune surface disease such as ocular pemphigoid also fall here. The through-line is inflammation of a tissue that must stay smooth and wet to work, and the treatment logic is to restore that environment before the cornea pays the price.
What are the corneal disease treatment options?
People asking about corneal disease treatment options usually imagine surgery. In practice the ladder has many rungs, and most patients never climb past the lower ones.
Environment and habits come first because they are free of side effects: UV-blocking sunglasses for pterygium, strict contact lens hygiene and no sleeping in lenses to prevent infection, stopping eye rubbing in keratoconus, humidifiers and screen breaks for dry eye.
Eye drops by class do the heavy lifting in medical management. Anti-infectives target bacteria, fungi, viruses or amoebae. Corticosteroid and other anti-inflammatory classes calm the immune response that scars tissue. Lubricants stabilize the tear film. Hypertonic saline drops draw excess fluid out of a swollen cornea in early Fuchs. Each has a mechanism, a timeline and trade-offs, and the prescribing clinician weighs them; steroids, for example, can raise eye pressure and encourage some infections, so they are used with monitoring.
Contact lenses as treatment is a concept that surprises people. Scleral lenses vault over an irregular cornea and bathe it in fluid, sharpening vision in keratoconus and protecting a fragile surface in severe dry eye. Bandage soft lenses shield a healing abrasion.
Office and laser procedures include cross-linking for progressive keratoconus, punctal plugs for dry eye, superficial laser polishing of surface scars, and removal of foreign bodies.
Surgery covers pterygium excision with graft, amniotic membrane grafts to help a stubborn surface heal, and the family of transplants described next. Even here, choice matters: replacing only the diseased layer is now often preferred to full-thickness replacement when the rest of the cornea is healthy, because recovery is faster and the risk of rejection is lower, according to the NHS.
Which rung is right depends on the layer involved, how fast the disease is moving, and how much it is limiting the person’s life. That judgment is the specialist’s, made with you.
Corneal transplant: what actually happens on the day
A corneal transplant, or keratoplasty, replaces damaged corneal tissue with tissue from a deceased donor supplied through an eye bank, where it is screened for infection and quality. Because the cornea has no blood vessels, blood or tissue matching is not routinely required, as both the NHS and Mayo Clinic explain, and waiting times are usually governed by tissue availability and scheduling rather than by finding a match.
There are three main versions, and your surgeon chooses based on which layers are diseased:
- Penetrating keratoplasty (PK) replaces the full thickness. A circular disc of the central cornea is removed with a trephine, a round cutting instrument, and the donor disc is sewn in place with sutures finer than a human hair.
- Deep anterior lamellar keratoplasty (DALK) replaces the front layers and keeps the person’s own healthy endothelium, useful in keratoconus and stromal scars, and lowering rejection risk.
- Endothelial keratoplasty (DSAEK or DMEK) replaces only the inner pump layer through a small incision, with the donor tissue held in place by an air or gas bubble rather than stitches. This is the usual approach for Fuchs dystrophy.
Surgery is commonly done under local anesthesia with sedation, or under general anesthesia, and typically lasts under an hour for the endothelial types and somewhat longer for full-thickness grafts, according to the NHS. Most people go home the same day with a shield over the eye. After endothelial keratoplasty you may be asked to lie flat for a period so the bubble presses the graft into position.
Risks the surgeon will discuss include rejection, infection, raised eye pressure, graft detachment (for endothelial grafts), astigmatism, and the possibility that the graft eventually fails and needs repeating. Alternatives depend on the condition: specialty lenses, cross-linking, or continued observation.
Who is usually referred to a cornea and external disease specialist, and who is asked to wait?
Referral patterns are fairly consistent across health systems. A cornea and external disease specialist is usually brought in when:
- a corneal infection is large, central, deep, not improving within the expected window, or in a contact lens wearer where an unusual organism is suspected;
- a pterygium is growing onto the cornea, distorting vision measurements, or repeatedly inflamed;
- keratoconus is diagnosed or suspected, particularly in a young person where progression is likeliest and cross-linking may be time-sensitive;
- Fuchs dystrophy is causing daily blur, or cataract surgery is planned and the endothelium needs assessment first;
- dry eye or surface disease has failed standard measures, or an autoimmune cause is suspected;
- the eye has had a chemical injury, a significant scar, or a previous graft.
Equally useful is knowing who is generally asked to wait, because waiting is often the right medical answer rather than a delay. A person with a small pterygium that does not touch the cornea and causes no symptoms will typically be monitored with photographs. Early Fuchs with clear vision by mid-morning is observed, often for years; surgery is reserved for when swelling becomes constant, because a transplant brings its own risks. A dense central scar from an old infection is not usually grafted until the eye has been free of active inflammation for many months, since operating on an inflamed eye raises rejection risk.
Timing also runs the other way. Cross-linking is generally offered only while measurements show keratoconus is still progressing; a stable cornea in someone’s forties is more likely to be managed with lenses alone, as Cleveland Clinic notes. And transplantation is usually deferred in someone with uncontrolled surface disease or eyelid problems until those are treated, because a graft placed on a hostile surface tends to fail.
None of this is a fixed rulebook. It is the reasoning your specialist will lay out, and you are entitled to hear it in full.
What the following days and weeks usually look like
Recovery depends almost entirely on which procedure, if any, you have had, so the timelines below are typical ranges drawn from published patient information rather than promises.
After an infection is treated, the ulcer usually closes over days to weeks, but redness and light sensitivity can linger, and a scar may take months to soften. Vision is judged only once the surface is fully healed. Expect frequent early visits, then spacing out as the eye quiets.
After pterygium surgery, the eye is typically red, watery and scratchy for one to two weeks, with a patch or shield for the first day. Sutures, if used, may dissolve or be removed at a follow-up. Anti-inflammatory drops are commonly continued for several weeks as prescribed. The white of the eye can look pink for a few months while the graft settles.
After cross-linking, the surface cells are usually removed to let the vitamin drops penetrate, so the first three to five days can be quite uncomfortable, with a bandage lens in place. Vision is often blurrier than before for several weeks and may take months to settle. The purpose is stability, and the specialist will compare corneal maps at intervals to confirm progression has slowed.
After a transplant, the range is wide. The NHS notes that vision after endothelial keratoplasty often improves over weeks to a few months, while a full-thickness graft can take up to 18 months for vision to stabilize, with sutures often left in for a year or more and adjusted along the way to reduce astigmatism. Long-term anti-rejection drops are commonly used, and follow-up continues indefinitely because rejection can occur years later.
Across all of these, three habits matter: use every prescribed drop on the schedule given, do not rub or press on the eye, and protect it with a shield at night if told to. Driving, swimming, contact lens wear and return to work are cleared by your team, not by the calendar.
What people often get wrong about corneal disease
A red, gritty eye is just pink eye. Common conjunctivitis is usually mild and self-limiting. Infectious keratitis can look similar on the first morning, yet it can scar the cornea within days. The differences, pain out of proportion, light sensitivity, blurred vision, a visible white spot, and contact lens wear, are why an examination matters more than a guess.
A pterygium is a cataract, or a tumor. It is neither. A cataract clouds the lens inside the eye; a pterygium grows on the surface. Pterygia are benign, though very rarely a surface growth needs a biopsy to confirm what it is, which is one reason a specialist looks rather than assumes.
Corneal transplants need a matched donor and a long wait. The cornea’s lack of blood vessels means tissue matching is not routinely required, per the NHS and Mayo Clinic, and scheduling is driven by tissue supply rather than by compatibility testing.
A transplant means new vision the next day. Full-thickness grafts can take a year or more to give their best vision, and glasses or a contact lens are frequently still needed afterward. Endothelial grafts are faster, but still measured in weeks to months.
Cross-linking fixes keratoconus. It aims to stop progression. Vision correction still comes from lenses, and a cone that already exists does not disappear.
Dry eye is trivial. Untreated surface inflammation damages corneal cells, blurs vision, and can compromise the outcome of any later surgery. It deserves the same seriousness as any chronic condition.
Water is fine for contact lenses. Tap, shower and swimming-pool water can carry organisms, including Acanthamoeba, that cause severe keratitis. Mayo Clinic lists water exposure among the leading avoidable risk factors for lens-related infection.
Questions to ask your care team
A cornea consultation moves fast and uses words most people have never heard. Writing questions down beforehand, and bringing someone to listen, makes a real difference. The following are the ones patients most often wish they had asked.
- Which layer of my cornea is affected, and is the condition likely to progress or stay stable?
- What is the working diagnosis, and how confident are you? Are there tests still pending, such as cultures or corneal mapping?
- What happens if we monitor rather than treat right now? What would change your recommendation?
- For each drop you are prescribing, what is it for, how will we know it is working, and what side effects should prompt a call?
- Am I safe to keep wearing contact lenses, and if not, for how long?
- If surgery is discussed: which type, why that one for me, what are the alternatives, and what are the specific risks in my case?
- What will my vision realistically be like in the first weeks, and when can I expect to know the final result?
- How many follow-up visits should I plan for, and who do I contact out of hours?
- Are there activities I should stop or protective steps I should take, such as sunglasses, night shields or avoiding eye rubbing?
- Does this condition run in families, and should relatives be examined?
- Will this affect other eye care I may need later, such as cataract surgery?
You are also entitled to ask about the specialist’s training and how often they perform a given procedure. Good clinicians welcome the question. If an answer is unclear, ask for it to be repeated in plain words; the plainer the explanation, the better the decision you will make together.
When to call your doctor
Corneal problems are one of the few areas of eye care where a day’s delay can change the outcome, so the threshold for calling should be low. Contact your eye care team the same day, or go to an emergency department if you cannot reach them, for any of the following:
- eye pain that is moderate to severe, or worsening rather than easing, particularly if you wear contact lenses;
- a sudden drop in vision, new blur, or a dark or foggy patch that does not clear with blinking;
- marked sensitivity to light, or a red eye with a white or gray spot visible on the cornea;
- a chemical splash or a high-speed foreign body; rinse with clean water for at least 15 minutes and seek care immediately;
- after any corneal surgery or transplant: increasing redness, pain, light sensitivity or reduced vision, since these are the classic warning signs of graft rejection or infection, and Mayo Clinic notes rejection is often manageable when treated early;
- a thick discharge, a swollen lid, or fever alongside an inflamed eye;
- a herpes cold sore near the eye, or a shingles rash on the forehead or nose, both of which can involve the cornea.
If you have been told you have keratoconus, Fuchs dystrophy or a pterygium and notice a clear change in your vision between scheduled visits, that is also a reason to call rather than wait. Take out contact lenses and keep them, along with the case, in case your team wants to culture them.
Whatever the situation, the specialist decides what happens next, whether that is reassurance, an adjusted prescription, or an urgent appointment. Your part is simply to report changes early and honestly.
Frequently asked questions
What is a cornea specialist called?
The usual title is cornea and external disease specialist, sometimes shortened to corneal specialist or cornea surgeon. It describes an ophthalmologist, a medical doctor trained in eye disease and surgery, who has completed an additional fellowship focused on the cornea and the ocular surface. You may also hear anterior segment surgeon, which covers the front third of the eye more broadly.
What are the common conditions that affect the cornea?
The most frequent are infections (bacterial, viral, fungal or amoebic keratitis), pterygium, inherited dystrophies such as Fuchs, keratoconus, dry eye and other ocular surface disease, and injuries including abrasions and chemical burns. Most present with some mix of redness, pain, light sensitivity and blur, which is why a slit-lamp examination rather than symptoms alone settles the diagnosis.
How is a corneal specialist different from a regular ophthalmologist?
Every corneal specialist is an ophthalmologist, but not every ophthalmologist has subspecialty training in the cornea. A general ophthalmologist manages many routine corneal problems; the specialist is involved when a condition is unusual, sight-threatening, progressive or surgical, such as deep infections, keratoconus, advanced Fuchs dystrophy or transplantation. Optometrists often spot the problem first and refer onward.
What are the treatment options for corneal disease?
Options range from habit changes and UV protection, through eye drops by class (anti-infective, anti-inflammatory, lubricant), to specialty contact lenses, office procedures such as cross-linking or punctal plugs, and surgery including pterygium removal and corneal transplant. Which is appropriate depends on the layer involved, how fast the disease is changing and how much it limits daily life; the treating team makes that judgment with you.
How do I find a good corneal specialist near me?
No medical body ranks individual doctors, so lists of the best specialists in a city are marketing rather than evidence. Reasonable markers are board certification in ophthalmology, a completed cornea fellowship, access to corneal imaging such as topography and specular microscopy, and links with an eye bank if transplantation may be needed. Your optometrist or general ophthalmologist can usually recommend colleagues they trust.
Is a pterygium dangerous?
A pterygium is a benign growth and rarely threatens sight quickly. The concerns are that it can distort the cornea’s shape and cause astigmatism, become chronically inflamed, or, if large, grow across the pupil. Small, quiet pterygia are usually monitored with sun protection and lubricants; surgery is discussed when vision or comfort is affected.
Does a corneal transplant need a matched donor?
Not routinely. The cornea has no blood vessels, giving it a degree of immune privilege, so blood or tissue matching is generally not required, as the NHS and Mayo Clinic explain. Donor tissue comes from an eye bank after screening for infection and quality. Rejection can still occur, which is why anti-rejection drops and long-term follow-up are standard.
How long does it take to recover from a corneal transplant?
It depends on the type. Endothelial-only grafts often show improving vision over weeks to a few months, while full-thickness grafts can take up to 18 months for vision to stabilize, with sutures frequently left in for a year or more, according to the NHS. Glasses or a contact lens are commonly still needed afterward, and follow-up continues for life.
Can keratoconus be treated without surgery?
Often, yes. Many people manage keratoconus for years with rigid or scleral contact lenses, which create a smooth optical surface over the irregular cornea. Corneal cross-linking, an outpatient procedure, is offered to slow progression when measurements show the cornea is still changing. Transplant is reserved for advanced cases where lenses no longer give useful vision or scarring is present.
Why does my dry eye keep watering?
An irritated, unstable tear film triggers reflex tears, but those tears lack the oily layer produced by the eyelid glands, so they evaporate or spill over quickly. Mayo Clinic describes this evaporative type as the more common form of dry eye. Treating the lids and the underlying inflammation, rather than just adding drops, is usually the specialist’s focus.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
What Chalazion Removal Involves: Numbing, the Incision Inside the Eyelid and the Patch
A chalazion removal procedure is a short outpatient operation for a blocked oil gland in the eyelid. The lid is numbed with a local…

How Corneal Repair Is Done: Sutures, Tissue Glue, Membrane Grafts and Transplant Options
Corneal repair is matched to the depth and cause of the damage. Small scratches are usually left to heal under protection; cuts and perforations…

Ophthalmic Lasers Explained: Retina, Glaucoma and Corneal Lasers and What Each One Does
Eye lasers fall into three broad groups. Retinal lasers seal leaking or abnormal blood vessels and barricade retinal tears. Glaucoma lasers improve fluid drainage…

Ocular Surface Disease Explained: How Tear Film, Eyelids and Cornea Fail Together
Ocular surface disease is an umbrella term for conditions in which the tear film, eyelids and cornea stop working as a unit, most often…

Eye Surgery in Older Adults With Heart Disease or Diabetes: How the Plan Is Adjusted
Eye surgery in older adults with heart disease or diabetes is usually still possible, but the plan changes. Most procedures, especially cataract surgery, are…

Why You Must Pause Contact Lenses Before a Myopia Laser Assessment (and for How Long)
Contact lenses press on the cornea and temporarily change its shape, so measurements taken too soon after removing them can be inaccurate and could…