

What the Robot Actually Changes in a Robotic Hysterectomy: Precision, Incisions and Recovery

Key Takeaways
- The robot never moves on its own: every instrument motion in a robotic hysterectomy is made by the surgeon at a console, and the instruments freeze when the surgeon's hands stop.
- In most total robotic hysterectomies the uterus leaves the body through the vagina, not through the fingertip-sized abdominal incisions.
- Cochrane's pooled trials show a large recovery advantage for keyhole surgery over open surgery, but no clear difference in complications between robotic and hand-held laparoscopy.
- Robotic operations run longer than conventional laparoscopy, partly because docking the arms adds set-up time, though times fall as surgical teams gain experience.
- Shoulder-tip pain after keyhole surgery comes from carbon dioxide gas irritating the diaphragm and typically eases over a few days with walking.
- Small skin scars do not mean a small internal recovery: the vaginal cuff takes roughly 4–6 weeks to heal, which is why lifting and sex restrictions outlast the incisions.
In a robotic hysterectomy the robot does not operate on its own. The surgeon sits at a console a few feet from the patient and controls slim, wristed instruments passed through small abdominal incisions, guided by a magnified three-dimensional camera. The system steadies hand movements and adds range of motion; the uterus is usually removed through the vagina. Current evidence shows recovery broadly similar to conventional keyhole surgery, with longer operating times.
The consultation is nearly over when she asks the question she has been holding back. “So who is actually doing the operation?” The gynecologist smiles, because almost everyone asks it. The word robotic conjures a machine working while the humans watch. Understanding what the robot does in robotic hysterectomy, and what it does not do, turns out to be the single most reassuring piece of information most patients receive before the day.
Hysterectomy, the surgical removal of the uterus, is one of the most common operations performed on women in the United States, second only to cesarean birth according to Cleveland Clinic. It can be done through one long abdominal cut, through the vagina alone, through several keyhole incisions with hand-held instruments, or through those same keyhole incisions with instruments mounted on robotic arms.
That last option gets the marketing. It deserves a plainer, more honest explanation: what changes for the surgeon, what changes for your body, and what stays exactly the same.
What the robot does in robotic hysterectomy: a surgeon at a console, not an autopilot
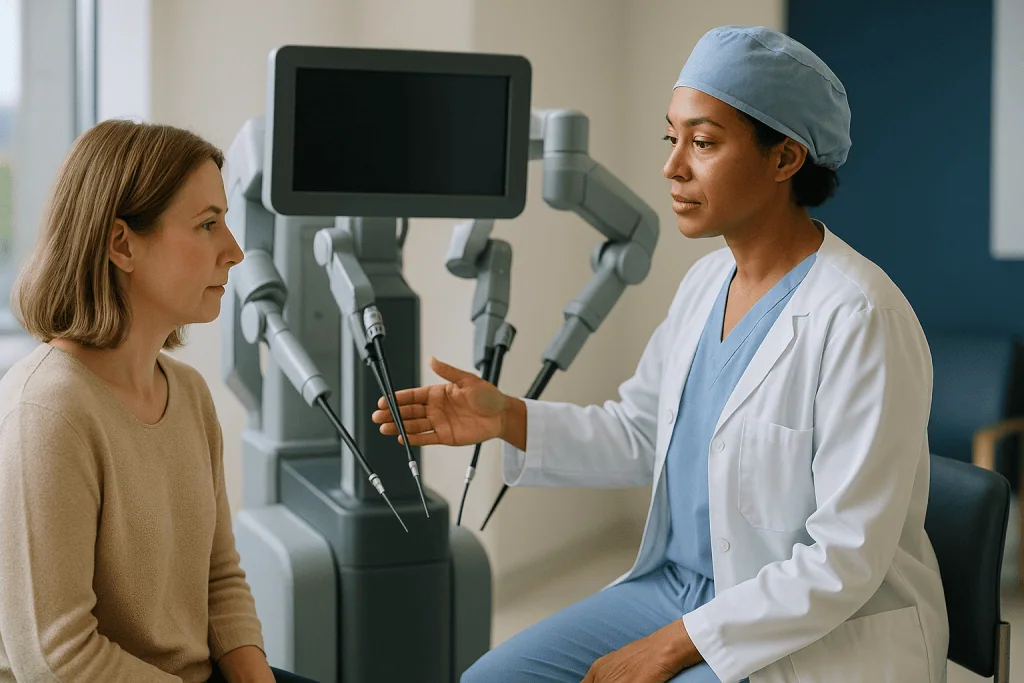
Start with the room. The patient lies on the operating table under general anesthesia. Beside the table stands a cart with three or four articulated arms. A few feet away, sometimes in the corner of the same room, the surgeon sits at a console with a viewer, two hand controllers and foot pedals. A second surgeon or trained assistant stays scrubbed at the bedside, swapping instruments and managing the small incisions.
Every movement of the instruments inside the abdomen is made by the surgeon’s hands in real time. The console translates finger and wrist motions into identical, scaled-down motions at the instrument tips. Let go of the controllers and the instruments freeze in place. There is no program, no automated cutting, no decision the machine makes on its own. Mayo Clinic describes the system as a tool that lets the surgeon perform the same operation as laparoscopic surgery, with added dexterity and a stereoscopic view.
So what does the robot actually contribute? Three things, in plain terms. First, the instruments have a wrist at the tip that rotates further than a human wrist, so suturing deep in the pelvis is done with the tip angled rather than the whole hand. Second, the software filters out small hand tremor. Third, the camera gives a magnified, three-dimensional picture instead of the flat two-dimensional screen of standard laparoscopy, which is surgery performed through keyhole incisions with long, hand-held instruments.
None of this replaces judgment. Which tissue to cut, where the ureter runs, when to convert to an open incision: those calls remain entirely human. The most accurate phrase is computer-assisted laparoscopic surgery. The word robot is memorable, but it describes the tool, not the operator.
How does a robotic hysterectomy actually work, step by step?
The sequence is remarkably close to a conventional laparoscopic hysterectomy, with a docking step added. After anesthesia, a catheter drains the bladder and the patient is positioned with the head lower than the feet, a tilt called Trendelenburg position, which lets the bowel slide upward out of the pelvis so the surgeon can see the uterus clearly.
Next comes insufflation: carbon dioxide gas is pumped into the abdomen through a fine needle to lift the abdominal wall away from the organs and create a working space. Four or five small incisions are then made, typically each less than an inch long, and hollow tubes called ports are placed through them. The robotic arms are wheeled in and clicked onto the ports. This docking usually takes a few minutes and is one reason robotic operations run longer than the hand-held equivalent, a difference documented in randomized trials summarized by the Cochrane review on surgical approaches to hysterectomy.
With the camera and instruments inside, the surgeon moves to the console. The operation follows the anatomy in order: the round ligaments that anchor the uterus are sealed and divided; the blood vessels to the ovaries are either preserved or divided, depending on whether the ovaries are being removed; the bladder is gently peeled off the front of the uterus; the uterine arteries, the main blood supply, are sealed; and finally the connection between the cervix and the top of the vagina is cut. That last step is called a colpotomy.
If the cervix is left behind, the procedure is a supracervical hysterectomy. If cervix and uterus both go, it is a total hysterectomy. The open top of the vagina, known as the vaginal cuff, is closed with stitches, which is where the wristed instruments earn their reputation. The arms are undocked, gas is released, and the tiny incisions are closed with dissolving stitches or skin glue.
How does the uterus come out during a robotic hysterectomy?
This question surprises people once they picture the geometry. Five incisions the width of a fingertip cannot pass a uterus. The answer, in most robotic and laparoscopic total hysterectomies, is that the uterus leaves the body through the vagina.
Once the colpotomy is complete, the uterus is free inside the pelvis. The bedside assistant guides it down through the opening at the top of the vagina and out, the same route used in a purely vaginal hysterectomy. A uterus that has not been enlarged by fibroids is roughly the size of a pear and passes without difficulty. The vaginal cuff is then closed from above with the robotic instruments.
Sometimes the uterus is too large for that route, or the cervix is being kept so there is no vaginal opening to use. Surgeons then have a few options. One is to widen a single abdominal incision slightly and lift the specimen out inside a sturdy bag. Another is morcellation, which means cutting the tissue into smaller pieces so it can be removed through a small incision. In recent years many surgical bodies have restricted or discouraged morcellation performed loose inside the abdomen when a cancer cannot be excluded, because fragments of an unsuspected cancer could be spread. Where morcellation is still used, it is often done inside a containment bag. Your surgeon should tell you in advance which removal method is planned and why.
Removing the uterus does not leave an empty cavity. The bowel and bladder settle into the space the uterus occupied, and the vagina keeps its length in a total hysterectomy because the closure is at its top, not along its walls. Johns Hopkins notes that the ovaries, if kept, continue producing hormones as before, since their blood supply is separate from the uterus.
What does precision mean when the robot is involved?
Precision is the word every brochure uses, so it pays to unpack it into mechanisms.

The first is wristed articulation. A standard laparoscopic instrument is a straight rod; it can move in, out, tilt and rotate around the port, but the tip cannot bend. Robotic instruments carry a tiny jointed wrist at the end, so a needle can be driven at almost any angle inside a confined pelvis. Surgeons describe this as the difference between writing with a pencil taped to a broomstick and writing with a pencil.
The second is motion scaling. The console can be set so that a movement of several centimeters at the surgeon’s hand becomes a movement of a few millimeters at the instrument tip. Combined with tremor filtering, this steadies fine work such as placing stitches close to the ureter, the narrow tube carrying urine from kidney to bladder, which runs within a centimeter or so of the uterine artery.
The third is vision. The camera delivers a magnified, three-dimensional image with depth perception, which matters when judging how deep a cut sits relative to the bladder wall. Mayo Clinic lists this view, along with the range of motion, as the practical reasons some surgeons prefer the platform for complex pelvic anatomy.
What precision does not mean is a measurably better outcome for every patient. Randomized comparisons of robotic and conventional laparoscopic hysterectomy for benign disease, summarized by Cochrane in 2015 and again in 2019, found low-certainty evidence and no clear difference in complication rates, with robotic operations taking longer. The mechanical advantages are real for the surgeon; whether they translate to fewer complications for a given patient depends heavily on the complexity of the case and the experience of the team. Honest teams say so.
Robotic vs laparoscopic hysterectomy: what does the evidence actually show?
Four surgical routes exist, and the fairest way to see where robotics sits is side by side. Figures below are typical ranges from NHS, Mayo Clinic and the Cochrane review on surgical approach to hysterectomy for benign disease; individual timelines vary, and your team’s numbers are the ones that count.
| Approach | Incisions | Typical hospital stay | Typical return to usual activities | What the evidence emphasizes |
|---|---|---|---|---|
| Abdominal (open) | One cut, roughly 5–7 inches, horizontal or vertical | Up to about 5 days (NHS) | About 6–8 weeks (NHS) | Longest recovery; still needed for very large uteri or some cancers |
| Vaginal | None on the skin; through the vagina | Often 1–4 days (NHS) | Shorter than abdominal, often around 4–6 weeks (NHS) | Cochrane recommends it where feasible; fewest complications overall |
| Laparoscopic | Several keyhole incisions, each under an inch | Often same day to 2 days | Faster than abdominal (Cochrane) | Quicker recovery than open; slightly higher urinary tract injury rate than open in trials |
| Robotic-assisted | Four to five keyhole incisions | Same day or next day (Mayo Clinic) | Around 3–4 weeks for many (Mayo Clinic) | Comparable to laparoscopy in complications; longer operating time; low-certainty evidence |
Two conclusions follow. The gap between open and keyhole surgery of either kind is large and well documented: less pain, shorter stays, faster return to work. The gap between hand-held and robotic keyhole surgery is small and uncertain. Cochrane’s authors concluded that vaginal hysterectomy should be performed whenever possible, with laparoscopic approaches next where vaginal is not feasible, and that robotic surgery had not been shown to improve outcomes over conventional laparoscopy.
That is not an argument against the robot. Some surgeons complete complex cases through keyholes with the platform that they would otherwise convert to an open incision, and the patient gains the whole keyhole advantage. It is an argument for asking which approach your particular surgeon does most, and why they favor it for your anatomy.
Who is a robotic hysterectomy usually for, and who is usually asked to wait?
The reasons for a hysterectomy come first; the route comes second. According to MedlinePlus, the common reasons include fibroids causing heavy bleeding or pressure, endometriosis that has not settled with other treatment, uterine prolapse, chronic pelvic pain, adenomyosis, abnormal bleeding unresponsive to medicines or less invasive procedures, and cancers of the uterus, cervix or ovaries. For most benign conditions, hysterectomy is offered after other options have been discussed, because it is irreversible and ends the possibility of pregnancy.
Once hysterectomy is agreed, a robotic approach tends to be considered when a keyhole route is wanted and the pelvis is expected to be difficult: extensive endometriosis with scarring, a moderately enlarged uterus, multiple previous abdominal operations with adhesions, a higher body weight where long hand-held instruments are harder to control, or certain early cancers where lymph nodes must be sampled. In these situations the wrist and the three-dimensional view are most useful.
Some patients are steered elsewhere. A uterus that is very large may be safer to remove through an open incision. Prolapse is often best treated vaginally, the route Cochrane favors when it is feasible. Advanced cancers may need open surgery for a complete assessment.
Others are asked to wait rather than choose a different route. Anesthesia teams commonly postpone elective surgery for uncontrolled blood pressure, poorly controlled diabetes, an active infection, a recent heart event, or unresolved anemia from heavy bleeding, because correcting these first lowers the risk of the operation itself. Smokers are usually encouraged to stop for several weeks beforehand; NHS advice highlights slower healing and higher chest and wound complication rates in smokers. Anyone who may still want a pregnancy is asked to pause and review uterus-sparing alternatives with the team. These are not rejections. They are the team stacking the odds in your favor before the day arrives.
How many hours does a robotic hysterectomy take?
Two clocks run on the day of surgery, and mixing them up causes a lot of anxious waiting-room arithmetic.
The first is skin-to-skin operating time. NHS guidance states that a hysterectomy operation itself usually takes about an hour, a figure that applies most closely to straightforward abdominal or vaginal procedures. Randomized trials pooled by Cochrane found that laparoscopic approaches took longer than open surgery, and that robotic-assisted procedures took longer again than hand-held laparoscopy, typically by tens of minutes. Extra time goes into placing ports, docking the arms, and, in complex cases, the meticulous dissection the platform is chosen for. Removing the ovaries and fallopian tubes at the same time, sampling lymph nodes, or dividing dense endometriosis adhesions each add to it.
The second clock is the one your family watches. It starts when you leave them and ends when the surgeon calls, and it includes anesthesia induction, positioning, catheter placement, the operation, waking, and transfer to recovery. Several hours from goodbye to phone call is normal even when the operative time is modest. Ask your team for their own typical range for your planned procedure; it will be more accurate than any general figure.
Does a longer operation matter to you? Longer anesthesia and longer time in the steep head-down position carry their own small considerations, discussed in the section on downsides. Against that, an operation completed through keyholes rather than converted to an open incision saves weeks of recovery. Surgeons weigh those trade-offs case by case, which is why the same diagnosis can lead to different approach recommendations for different patients.
One practical note: the surgeon’s experience with the platform influences operating time more than the platform itself. Trials consistently show times fall as teams accumulate cases.
How bad is the pain after a robotic hysterectomy?
People expect the incisions to be the problem. Usually they are not. Most describe the first two days as sore rather than severe, with three distinct kinds of discomfort.
The incisions themselves ache and feel bruised, particularly the one near the navel where the uterus was pulled toward the camera. Deep pelvic cramping, similar to strong period pain, comes from the raw surface where the uterus sat and from the vaginal cuff stitches. The third and least expected is shoulder-tip pain. Carbon dioxide left under the diaphragm irritates a nerve that shares its pathway with the shoulder, so a sharp ache appears under one shoulder blade, most noticeably when standing. NHS describes this as common after keyhole surgery and notes that it eases over a few days as the gas is absorbed. Walking and changing position help it disperse.
Pain is managed in layers. Local anesthetic is often injected around the ports before you wake. In the ward or recovery area, teams typically use a combination of non-opioid pain relievers on a schedule, with stronger medicines held back for breakthrough pain. The prescribing clinician decides what is appropriate for you, and any change to what you already take belongs to that conversation, not to a magazine. Trials pooled by Cochrane show that keyhole approaches, robotic included, produce less postoperative pain and shorter recovery than open surgery; robotic and conventional laparoscopy were not clearly different from each other on pain.
Most patients report a clear step-down in discomfort by day three or four, and many stop scheduled pain relief within the first week. Pain that climbs rather than falls, or pain concentrated in one area with fever, is a different matter and is covered in the red-flag section below.
Robotic hysterectomy recovery time: what the first days and weeks usually look like
Recovery has a shape, and knowing it prevents the common mistake of doing too much in week two.
Day of surgery and day one: you wake with a catheter that is usually removed within hours. Nurses will want you walking to the bathroom the same day, because early movement lowers the risk of blood clots in the legs and helps the gas disperse. Mayo Clinic notes that after a robotic hysterectomy most patients go home the same day or the next morning, provided they can pass urine, manage pain with oral medicines and walk safely.
Week one: expect fatigue that feels out of proportion to the small incisions, light vaginal bleeding or brownish discharge, some bloating, and a tender abdomen. Short walks several times a day, gradually lengthening, are the main prescription. Showers are usually fine once the dressings allow; baths and swimming wait until incisions and the vaginal cuff have sealed.
Weeks two to four: energy returns in steps. Desk-based work is often possible somewhere in this window, although NHS notes that many people need 4–8 weeks off, depending on the job and the route of surgery. Driving resumes when you can comfortably wear a seatbelt, twist to check mirrors and perform an emergency stop without hesitation; NHS puts this somewhere between 3 and 8 weeks for most, and your insurer may have its own rule.
Weeks four to eight: the vaginal cuff is the last tissue to heal. NHS advises waiting until discharge has stopped and the surgeon has confirmed healing before vaginal sex or inserting anything into the vagina, typically 4–6 weeks. Heavy lifting, including toddlers and full grocery bags, waits for a similar period to protect the cuff and the small port hernia risk. Mayo Clinic describes full recovery after robotic hysterectomy at around 3–4 weeks for many, compared with 6–8 weeks after open surgery, but these are typical ranges, not promises, and your team will set the pace.
What are the downsides of a robotic hysterectomy?
Every hysterectomy carries the risks NHS lists for the operation regardless of route: bleeding, infection of the wound or urinary tract, blood clots in the legs or lungs, injury to the bladder, bowel or ureter, reactions to anesthesia, and, when the ovaries are removed, immediate menopause. Keyhole approaches reduce wound problems and speed recovery, but Cochrane’s pooled trials found urinary tract injuries, mainly bladder and ureter, somewhat more frequent with laparoscopic surgery than with open surgery. That risk appears similar between robotic and hand-held laparoscopy.
Robotic surgery then adds a short list of its own considerations.
- Loss of touch. The surgeon cannot feel tissue resistance through the console and relies on visual cues instead. Experienced operators adapt, but it is a genuine change in how the operation is sensed.
- Longer time under anesthesia and in a steep head-down tilt. Prolonged Trendelenburg position raises pressure in the head and eyes and can cause facial swelling; teams monitor for this and limit duration, and serious problems are rare, but it is a reason very long cases are planned carefully in people with certain eye or heart conditions.
- Conversion. If bleeding, adhesions or unexpected findings make the keyhole approach unsafe, the surgeon converts to an open incision. This is a safety decision, not a failure, but it means an open-surgery recovery.
- Nerve or pressure injuries from positioning, prevented with padding and careful arm placement.
- Port-site hernia, where bowel pushes through a healed incision, uncommon but more likely at the larger ports.
- Uncertain added benefit. The evidence base comparing robotic with conventional laparoscopy remains low-certainty, so the platform should be seen as an option, not an upgrade.
None of these should decide the matter alone. They are the items a good surgeon raises unprompted during consent, alongside the alternatives, so that you weigh them against the specific reasons the platform is being suggested for your case.
What people often get wrong about what the robot does in robotic hysterectomy
Myth: the robot performs the surgery. The surgeon performs every movement; the system transmits and refines them. If the surgeon stops, everything stops.
Myth: the robot is more accurate, so complications are lower. The mechanical precision is real, but trials summarized by Cochrane have not demonstrated fewer complications compared with conventional keyhole surgery for benign conditions. The large, proven gain is keyhole over open, whichever keyhole method is used.
Myth: the uterus is removed through the small incisions. It almost always comes out through the vagina. Alternative removal methods are used only when that route is not available or the uterus is too large.
Myth: a hysterectomy always means menopause. Removing the uterus stops periods and pregnancy. Menopause follows only if both ovaries are removed. Johns Hopkins and NHS both note that retained ovaries keep producing hormones, although NHS mentions that some people with ovaries kept reach menopause a little earlier than they otherwise might.
Myth: a robotic operation is a smaller operation. It is the same organ removed with the same internal cuts and the same internal healing time for the vaginal cuff. The skin recovers fast; the pelvis follows its own timetable, which is why lifting and sex restrictions last weeks despite fingertip-sized scars.
Myth: everyone should ask for the robot. The Cochrane review’s headline recommendation is vaginal hysterectomy where feasible, then laparoscopic. Robotic assistance is one form of laparoscopic surgery, most valuable in complex pelvises and in the hands of a team that uses it regularly.
Myth: hysterectomy ends sexual function. Cleveland Clinic notes that for many, relief from pain and bleeding improves intimacy, while a minority notice changes in sensation, particularly if the cervix or ovaries are removed. It is worth raising in advance rather than discovering afterward.
Incisions, scars and ports: what changes on the skin
Ask a surgeon to draw the incisions and you get a shallow arc across the abdomen: one at or just above the navel for the camera, two or three spaced across the lower abdomen roughly level with the hip bones, and often one on the side for the bedside assistant. Each is typically less than an inch. The camera port is usually the largest, and for that reason the one most likely to feel tender and the one where a hernia, though uncommon, is most likely to develop later.
Compare this with the alternatives. An abdominal hysterectomy leaves a single 5–7 inch scar, usually horizontal along the bikini line, sometimes vertical when the uterus is very large or cancer is suspected, according to NHS. A vaginal hysterectomy leaves no visible scar at all. Conventional laparoscopy leaves a similar scatter of small marks to the robotic version, sometimes one fewer.
Closure is done with dissolving stitches beneath the skin, skin glue or small adhesive strips, so there is often nothing to remove. Bruising around the ports is common in the first week and fades. Over months the marks flatten and pale; people with a tendency to raised or keloid scars should mention it beforehand so the team can plan placement and aftercare.
Caring for the incisions is undramatic: keep them clean and dry, pat rather than rub after showering, avoid soaking until they have sealed, and resist picking at glue or strips, which come away on their own. Watch for the signs of wound infection covered below.
The skin, in the end, is the least of it. The incision most people never see, the vaginal cuff, is the one that governs the recovery rules and deserves the same patience you would give a visible wound.
Questions to ask your care team
A good consultation is a conversation, and the questions below tend to draw out the information that matters most. Bring them written down; anesthesia-day nerves erase memory.
- Why hysterectomy rather than the alternatives for my condition, and what would happen if I waited?
- Which route are you recommending, and why that one for my anatomy and history? Would a vaginal or conventional laparoscopic approach be feasible?
- How often do you perform robotic hysterectomies, and how often do you convert to an open incision?
- Will you remove the cervix, the fallopian tubes or the ovaries, and what are the reasons for each decision?
- How will the uterus be removed from my body, and will any form of morcellation be used?
- What is your typical operating time for a case like mine, and how long should my family expect to wait?
- Will I go home the same day or stay overnight, and what has to happen before discharge?
- How will my pain be managed, and how does that fit with the medicines I already take?
- What are the specific risks in my case, and which would prompt you to change plan during surgery?
- If my ovaries are removed, how will we handle the resulting menopause, and who follows that up?
- When can I drive, return to my kind of work, lift my children, exercise and resume sex?
- Who do I call out of hours if something worries me, and what should prompt an emergency visit?
- Will the removed tissue be examined by a pathologist, and how will I receive those results?
Notice what is not on the list: any request for a particular machine or a promise about outcomes. The useful questions are about your surgeon’s reasoning and experience. A team confident in its recommendation will welcome every one of them.
When to call your doctor
Most recoveries are uneventful, and the discomforts described earlier fade steadily. A short list of signs should prompt a same-day call to your surgical team or, where marked with urgency, emergency care. NHS and Mayo Clinic list similar warning signs after hysterectomy.
- Fever, chills or a general sense of being unwell that develops after the first day or two, which can signal infection at the wound, in the urinary tract or in the pelvis.
- Vaginal bleeding heavier than a light period, bleeding that soaks through a pad in an hour, or bleeding that restarts heavily after settling. A sudden gush of watery fluid can indicate a problem with the vaginal cuff and needs prompt review.
- Redness spreading from an incision, thick or foul-smelling discharge, or an incision that opens.
- Pain that increases rather than decreases, or severe pain concentrated in one area of the abdomen.
- Difficulty passing urine, burning when you do, or leakage of urine from the vagina, which can point to a bladder or ureter injury.
- Persistent vomiting, inability to keep fluids down, or a swollen abdomen with no bowel movement.
- A swollen, warm or painful calf, which may be a blood clot.
Seek emergency care immediately for sudden breathlessness, chest pain, coughing up blood, collapse or fainting, or confusion; these can indicate a clot that has traveled to the lungs or significant internal bleeding. Do not drive yourself.
The threshold for calling is lower than people think. Surgical teams would far rather reassure ten people over the phone than miss the one who needed to come in. Keep the out-of-hours number your team gives you somewhere visible, and if you are unsure whether something counts, that uncertainty is itself a reason to call.
Frequently asked questions
How is the uterus removed robotically if the incisions are so small?
It usually comes out through the vagina. After the surgeon detaches the uterus and cuts it free from the top of the vagina, the bedside assistant guides it down and out along that natural route, and the opening is stitched closed from above. If the uterus is too large or the cervix is being kept, the team may enlarge one incision slightly and remove it in a bag, or use contained morcellation. Ask which method is planned for you.
How many hours does a robotic hysterectomy take?
NHS states a hysterectomy operation itself typically takes about an hour, and randomized trials summarized by Cochrane show robotic approaches take longer than open or conventional laparoscopic surgery, often by tens of minutes, because of port placement, docking and complex dissection. Total time away from family, including anesthesia and recovery, is usually several hours. Your surgeon’s own typical range for your planned procedure is the most reliable figure.
How bad is the pain after a robotic hysterectomy?
Most people describe the first few days as sore rather than severe, with tender incisions, period-like pelvic cramping and shoulder-tip pain from residual gas. NHS notes the gas pain settles over a few days. Pooled trials show keyhole approaches cause less pain than open surgery, with no clear difference between robotic and hand-held laparoscopy. Pain relief is prescribed in layers by your team, and pain that worsens rather than eases should be reported.
What is a typical robotic hysterectomy recovery time?
Mayo Clinic describes discharge the same day or the next morning and full recovery for many people at around 3–4 weeks, compared with 6–8 weeks after an open abdominal hysterectomy according to NHS. Internal healing sets the pace: the vaginal cuff typically takes 4–6 weeks, so NHS advises waiting that long before vaginal sex or heavy lifting. These are typical ranges, not promises, and your team will guide your specific timeline.
What are the main robotic hysterectomy downsides compared with other approaches?
Robotic surgery shares the general risks of any hysterectomy: bleeding, infection, clots, and injury to the bladder, bowel or ureter. Specific to the platform are longer operating and anesthesia time, a prolonged head-down position, the surgeon’s loss of tactile feedback, the possibility of converting to an open incision, and low-certainty evidence that it improves outcomes over conventional laparoscopy. These points belong in the consent discussion with your surgeon.
Is robotic vs laparoscopic hysterectomy a real difference for the patient?
For the surgeon, yes: wristed instruments, tremor filtering and a three-dimensional view change how the operation feels to perform. For the patient, the measurable differences are small. Cochrane’s review found no clear difference in complications or recovery between robotic and hand-held laparoscopy for benign conditions, with robotic surgery taking longer. The bigger question is whether a keyhole route of either kind is feasible for you rather than open surgery.
Will a robotic hysterectomy put me into menopause?
Only if both ovaries are removed at the same time. Removing the uterus alone stops periods and pregnancy but leaves ovarian hormone production intact, as Johns Hopkins and NHS explain. NHS adds that some people whose ovaries are kept may reach menopause slightly earlier than expected. Whether to remove ovaries depends on your age, family history and the reason for surgery, and is a decision for you and your treating team.
Does the surgeon have to be in the same room as the robot?
In standard practice, yes. The console typically sits in the operating room a few feet from the table, and a second surgeon or trained assistant remains scrubbed at the bedside throughout to change instruments, manage the ports and respond immediately if the plan changes. The system is designed for the operating surgeon to be present and able to step to the bedside and convert to conventional or open surgery at any moment.
Can I choose a robotic hysterectomy if my surgeon recommends a vaginal one?
You can always ask, and a good surgeon will explain their reasoning. Cochrane’s review recommends vaginal hysterectomy where feasible because it has the fewest complications and no abdominal incisions, with laparoscopic approaches next. Robotic assistance is one form of laparoscopy, most useful in complex pelvic anatomy. The route that fits your anatomy and your surgeon’s regular practice generally matters more than the presence of a particular machine.
When should I worry after a robotic hysterectomy?
Call your surgical team the same day for fever or chills, heavy or restarting vaginal bleeding, a sudden gush of fluid, spreading redness or discharge at an incision, pain that increases rather than decreases, trouble passing urine or urine leaking from the vagina, persistent vomiting, or a swollen painful calf. Seek emergency care immediately for chest pain, sudden breathlessness, coughing blood, fainting or confusion, which can indicate a clot or significant bleeding.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

What Size of Ovarian Cyst Is Dangerous? Centimetres, Millimetres and What They Mean
There is no single size at which an ovarian cyst becomes dangerous. Most cysts are small, fluid-filled and disappear on their own within a…

Pelvic Ultrasound vs Hormone Tests in PCOS: Why Diagnosis Needs More Than One Finding
Neither a pelvic ultrasound nor a blood test can diagnose PCOS on its own. Clinicians use the Rotterdam approach, which requires at least two…

Endometriosis Treatment in Steps: Hormonal Medicine, Pain Care and When Surgery Is Added
Endometriosis treatment options are usually built in steps. Most people start with pain care, often anti-inflammatory medicines, and hormonal medicine that lowers estrogen's effect…

How Fast Ovarian Cysts Grow: Typical Timelines, Warning Signs and When to Treat
Most ovarian cysts are functional cysts that form during a normal menstrual cycle, reach roughly 2 to 5 centimeters, and shrink or disappear within…

Cystectomy vs Oophorectomy: Removing the Cyst or the Ovary and How Surgeons Decide
A cystectomy removes only the cyst and leaves the ovary in place; an oophorectomy removes the whole ovary, sometimes with the fallopian tube. Surgeons…

Blood Pregnancy Test vs Urine Test: Which Is More Accurate and When
Both tests detect the pregnancy hormone hCG. A blood test can pick it up slightly earlier, as soon as about 10 days after conception,…