

Does Every Case of Pink Eye Need Antibiotic Drops? Conjunctivitis Myths, Corrected

Key Takeaways
- A systematic review in JAMA estimated that around 80 percent of acute infectious conjunctivitis is viral, a type antibiotics cannot treat.
- According to the CDC, viral pink eye usually clears in 7 to 14 days on its own, and mild bacterial pink eye often improves within 2 to 5 days without drops.
- Antibiotic drops shorten bacterial conjunctivitis only modestly, by days, and are mainly reserved for thick pus, contact lens wearers, newborns, and people with weakened immunity.
- Intense itching is the single most useful clue pointing toward allergic rather than infectious pink eye, and antibiotics play no role there either.
- Pink eye spreads through hands and surfaces, not eye contact, so hand washing and separate towels do more to protect a household than any drop.
- Eye pain, light sensitivity, or blurred vision that does not clear with blinking means the cornea may be involved and the eye needs prompt examination.
No. Most pink eye does not need antibiotic drops. Roughly four in five cases of infectious conjunctivitis are viral, and antibiotics have no effect on viruses; viral pink eye usually settles within one to two weeks on its own. Even mild bacterial pink eye often improves without treatment. Clinicians generally reserve antibiotic drops for clearly bacterial cases with thick pus, contact lens wearers, newborns, and people with weakened immunity.
It is 6:40 on a school morning and a seven-year-old is standing at the bathroom sink, one eyelid glued shut with a yellow crust, the other eye already going watery and pink. The parent has three thoughts in quick succession: is this pink eye, can she go to school, and does pink eye need antibiotics or are we about to spend the morning in a waiting room for nothing?
That last question is the one this article is really about. Pink eye, the everyday name for conjunctivitis, is one of the most common reasons people book a same-day appointment, and antibiotic drops remain one of the most common things they walk out with. The evidence says those two facts should not line up as neatly as they do.
What follows is a plain account of what actually happens in an inflamed eye, how clinicians weigh up bacteria against viruses and allergies, when drops genuinely earn their place, and which warning signs should never wait.
Does pink eye need antibiotics? The short, honest answer
Conjunctivitis means inflammation of the conjunctiva, the thin, clear membrane that covers the white of the eye and lines the inside of the eyelids. Almost anything that irritates that membrane turns it pink: a virus, bacteria, pollen, a splash of chlorine, or a stray eyelash. Antibiotics act on exactly one item in that list.
The numbers matter here. A systematic review published in JAMA and indexed on PubMed estimated that roughly 80 percent of acute infectious conjunctivitis is viral, with adenoviruses responsible for the large majority of those viral cases. Viruses do not have the cell walls or protein-building machinery that antibiotics attack, so a bottle of antibiotic drops does nothing to a viral eye except add another thing to put in it.
Bacterial pink eye is the second most common infectious type, and even there the case for drops is narrower than most people assume. The CDC notes that mild bacterial conjunctivitis often improves within two to five days without any treatment, though it can take up to two weeks to clear fully. Antibiotic drops can shorten that course and reduce the chance of passing the infection on, which is why they still have a real role, but the benefit is modest in an otherwise healthy person.
So the honest answer to whether pink eye needs antibiotics is: sometimes, in specific situations, and far less often than the prescription rate suggests. The rest of this article explains how clinicians decide which situation you are in, and why the reflex to reach for drops persists even when the evidence points the other way.
What actually happens when the white of your eye turns pink
The conjunctiva is laced with tiny blood vessels that are normally too small to see. When something irritates or infects the membrane, those vessels widen to bring in immune cells, and the extra blood is what shows through as pink or red. That is the whole visual story; the color itself does not tell you the cause.
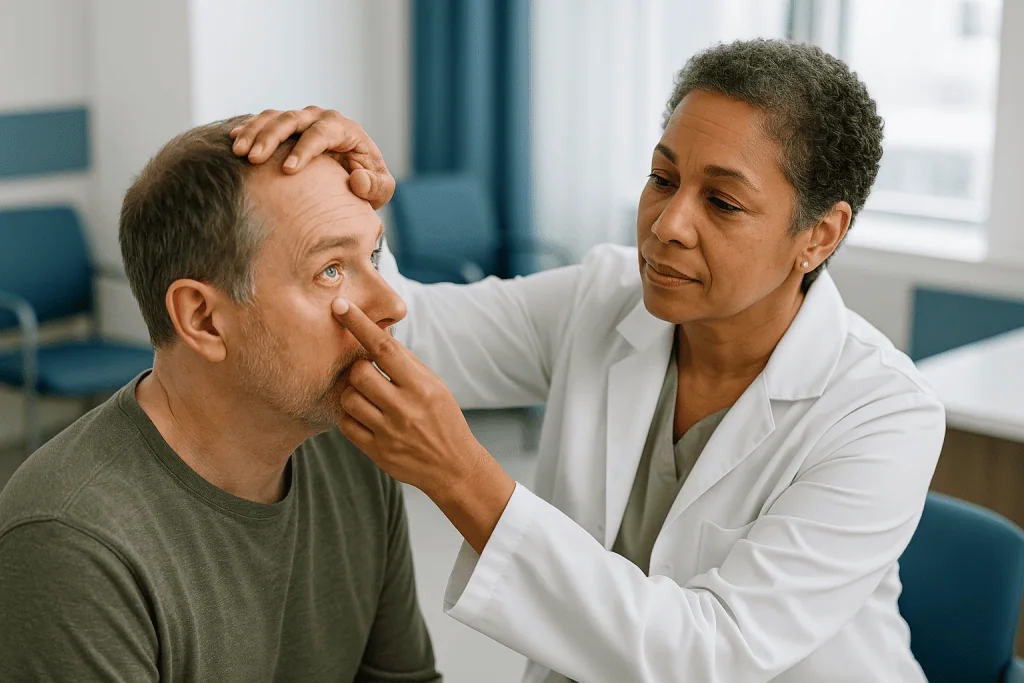
The discharge tells you a little more. A viral infection tends to trigger a watery, tear-like flow because the irritated conjunctiva simply weeps. A bacterial infection recruits white blood cells that die at the site and mix with mucus, producing the thicker, yellow or green discharge that can dry into the morning crust that seals eyelids shut. An allergic reaction releases histamine, a chemical messenger that makes vessels leak and nerves itch, which is why the hallmark of allergic conjunctivitis is intense itching rather than pus.
Some viral infections also swell a small lymph node just in front of the ear on the affected side, the preauricular node. Clinicians feel for it because bacteria rarely cause that swelling, and it nudges the likely diagnosis toward a virus.
One reassuring piece of anatomy: the conjunctiva stops at the edge of the cornea, the clear dome over the colored part of the eye that does the focusing. Ordinary conjunctivitis leaves the cornea alone, which is why vision usually stays sharp once you blink away the discharge. When blurring persists after blinking, or light starts to hurt, the cornea itself may be involved, and that changes the picture entirely. The Mayo Clinic and CDC both list those signs among the reasons to be seen promptly rather than wait it out.
How can you tell if pink eye is bacterial or viral?
Here is something worth saying plainly: you often cannot tell by looking, and neither can a clinician with complete confidence. The JAMA systematic review is candid that signs and symptoms overlap substantially between causes and that clinical diagnosis is imperfect. What clinicians do is weigh a pattern of clues, not tick a single box.
The clues that lean toward a virus include a watery rather than sticky discharge, a recent cold or sore throat, infection that starts in one eye and then spreads to the other a few days later, and that tender node in front of the ear. Adenoviral outbreaks also tend to travel through households and classrooms in waves.
The clues that lean toward bacteria include thick yellow or green discharge that keeps returning through the day after you wipe it away, eyelids matted shut on waking, and, statistically, being a young child; the JAMA review notes bacterial conjunctivitis is more common in children while viral causes dominate in adults.
The clues that lean toward allergy include itching as the main complaint, both eyes affected from the start, a seasonal pattern, and companion symptoms such as sneezing or a runny nose.
A rapid in-office test for adenovirus exists and can help settle the question in some settings, though it is not universally available. Cultures, where a swab is sent to a laboratory, are generally reserved for severe, unusual, or recurrent cases, or for newborns.
The practical point is that a clinician is not scanning for one decisive sign. They are asking whether the overall picture, plus your age, contact lens use, and general health, justifies drops, or whether the safer path is to watch, support, and reassess.
Will pink eye clear without antibiotics? What the evidence shows
For viral pink eye the answer is yes, with time as the only real treatment. The CDC describes viral conjunctivitis as usually clearing within 7 to 14 days without medication, with some cases taking two to three weeks. There is no antiviral drop for adenovirus, the usual culprit, so antibiotics are not just unhelpful but beside the point.

For bacterial pink eye the answer is usually also yes, though a little more slowly. The CDC notes that mild bacterial cases often improve within two to five days without treatment and may take up to two weeks to resolve completely. The JAMA systematic review reached a similar conclusion: bacterial conjunctivitis is generally self-limited, meaning the body’s own immune response clears it, and most untreated cases resolve within one to two weeks.
What antibiotics add is speed and a shorter window of contagiousness. Pooled trial data summarized in that review show antibiotic drops modestly increase the chance of being better a few days earlier compared with placebo drops. That is a genuine benefit, not a trivial one for a working parent or a child missing school, but it is a matter of days rather than a transformation.
This is why some clinicians offer what UK primary care calls a delayed or back-up prescription: watch for a few days, and only start drops if the eye is not improving or gets worse. The NHS notes that most cases do not need treatment and that a pharmacist can advise on symptom relief. Whether that watch-and-wait approach fits you depends on your circumstances, and that call sits with the person examining your eye.
Why antibiotics do nothing for viral pink eye
Antibiotics work by exploiting the differences between bacterial cells and human cells. Some break down the rigid wall that bacteria build around themselves; others jam the bacterial machinery for making proteins or copying DNA. Human cells lack those exact targets, which is what makes the drugs relatively safe for us.
Viruses are not cells at all. An adenovirus is a packet of genetic instructions inside a protein shell that slips into a conjunctival cell and hijacks that cell’s own equipment to copy itself. There is no bacterial wall to breach and no bacterial ribosome to block. Dropping an antibiotic onto a virally infected eye is like sending a locksmith to fix a software problem.
The JAMA systematic review attributes 65 to 90 percent of viral conjunctivitis to adenoviruses, a family that also causes colds and sore throats, which is why pink eye so often shows up a few days after someone in the house has been sniffling. There is no approved antiviral drop for adenovirus. Treatment is supportive: cool compresses, lubricating drops, and patience while the immune system does its work.
Herpes simplex virus is the important exception. It can infect the conjunctiva and, more worryingly, the cornea, and it does respond to antiviral medicines. Clinicians take particular care to consider herpes because steroid eye drops, which are sometimes used to calm severe inflammation, can make a herpes infection dramatically worse. That is one reason self-treating a red eye with leftover drops of unknown type is a poor idea, and why a persistent, painful, or light-sensitive red eye needs an examination rather than a guess.
Who is usually offered antibiotic drops, and who is usually asked to wait
Guidance from the CDC, the Mayo Clinic, and the JAMA systematic review converges on a fairly short list of situations where antibiotic drops are routinely considered rather than debated.
- Pink eye with obvious thick pus, where a bacterial cause is likely and the burden of discharge is significant.
- Anyone who wears contact lenses, because the bacteria involved can be more aggressive and the cornea is at higher risk.
- People with a weakened immune system, whether from illness or from medicines that suppress immunity.
- Newborns, for whom conjunctivitis in the first month of life is treated as a potential emergency.
- Cases where a specific, more dangerous bacterium is suspected, such as those linked to sexually transmitted infections, which can cause a severe, rapidly worsening form of the illness.
On the other side of the ledger sit the majority: an otherwise healthy adult or child with watery or mildly sticky discharge, a recent cold, no contact lenses, normal vision, and no pain. For this group, clinicians are increasingly comfortable recommending supportive care and a review if things are not settling within about a week, or a back-up prescription to be started only if the eye worsens.
Two things belong in the middle. Young children with sticky discharge are more likely than adults to have a bacterial cause, and some clinicians lean toward treating them earlier, especially when daycare policies require it. And anyone whose pink eye is not improving after a week or two, regardless of how it started, warrants a fresh look, because persistence sometimes means the original guess was wrong.
None of this is a rulebook you can apply to yourself. It is the reasoning a clinician uses after examining the eye, and the decision to start, delay, or skip drops belongs to that examination.
Bacterial vs viral vs allergic pink eye: how they compare
The table below pulls together the patterns clinicians look for and the timelines the CDC and the JAMA review describe. Treat it as a map of tendencies, not a diagnostic tool; real eyes are messier than columns, and overlap is common.
| Feature | Viral | Bacterial | Allergic |
|---|---|---|---|
| Typical cause | Adenovirus most often | Common skin and respiratory bacteria | Pollen, dust, pet dander |
| Discharge | Watery, clear | Thick, yellow or green, crusts overnight | Stringy, white, mucus-like |
| Main sensation | Gritty, burning | Sticky, irritated | Itching, often intense |
| Eyes affected | One first, often spreading to both | One or both | Both, from the start |
| Usual course | 7 to 14 days, sometimes 2 to 3 weeks (CDC) | Often improving in 2 to 5 days, up to 2 weeks (CDC) | As long as exposure continues |
| Contagious | Yes, highly | Yes | No |
| Do antibiotic drops help? | No | Modestly; shorten course in selected cases | No |
A few rows deserve a second glance. Itching is the single most useful discriminator in the table: when someone says the eye is maddeningly itchy rather than sore or sticky, allergy moves to the top of the list and antibiotics drop off it. The contagious row also cuts across the antibiotic question: viral pink eye spreads easily and antibiotics cannot change that, so hand washing and not sharing towels are the real infection-control measures for most people.
Finally, the discharge row is the one most often misread. Green or yellow discharge raises the odds of bacteria but does not settle them, because a heavy viral infection can also produce cloudy discharge, particularly on waking.
Do you just let pink eye run its course? Self-care that genuinely helps
Letting pink eye run its course does not mean ignoring it. The measures below are the ones the Mayo Clinic, the NHS, and the CDC consistently recommend, and they are the entire treatment plan for most viral and allergic cases.
Compresses first. A clean cloth soaked in cool water and laid over closed eyes for a few minutes eases the burning of viral or allergic conjunctivitis. A warm compress loosens the crusts of bacterial discharge so lids open without pulling. Use a fresh cloth for each eye and each session, and wash it in hot water afterward, because a cloth that touched an infected eye is an efficient way to seed the other one.
Gentle cleaning matters more than people expect. Wipe from the inner corner outward with a damp cotton pad, once, then discard it. Dried discharge on the lashes is a reservoir of infectious material, and clearing it several times a day reduces both irritation and spread.
Lubricating drops, the class often sold as artificial tears, soothe grittiness and rinse away irritants. They do not treat infection, but they make the waiting more comfortable. Redness-relief drops that work by constricting blood vessels are a different category; the Mayo Clinic advises against relying on them for conjunctivitis, as they can worsen irritation and rebound redness. For allergic conjunctivitis, antihistamine or mast-cell-stabilizing drops target the histamine mechanism directly and are a question for your pharmacist or clinician, not something to guess at.
Then the unglamorous basics. Stop wearing contact lenses until the eye has fully recovered and a clinician says it is safe. Throw away eye makeup used during the infection. Wash hands for at least 20 seconds after touching the face, and change pillowcases and towels frequently. The CDC treats these steps as the core of containing pink eye, and they work regardless of whether the cause is a virus or a bacterium.
What the following days and weeks usually look like
Pink eye has a rough shape, and knowing it helps you recognize when things are on track and when they are not. The ranges below come from the CDC and the JAMA systematic review; individual courses vary, and none of this is a promise.
The first two or three days are usually the most alarming. Redness peaks, discharge is at its heaviest, and if the cause is viral the second eye often joins in during this window. Morning crusting can be dramatic. For a bacterial infection this is also when antibiotic drops, if prescribed, are expected to start showing an effect; the CDC notes that improvement within a few days is typical once treatment begins.
Days four to seven are the turning point for most bacterial cases, treated or not, with discharge thinning and lids no longer sticking. Viral cases may plateau here rather than improve, which is normal and not a sign that antibiotics were missed.
By the end of week two the large majority of both types have resolved. A minority of adenoviral infections drag into a third week, and a small number leave faint inflammatory spots on the cornea that cause blurring or glare for a while afterward. That blurring, and any pain or light sensitivity, is the reason to go back rather than assume it will pass.
If you were prescribed drops and the eye is not improving after the expected few days, or is getting worse, the right move is to contact the prescriber for a reassessment, not to stop the drops on your own or to switch to something left over in the medicine cabinet. Persistence sometimes means a different cause, a resistant bacterium, or something that was never conjunctivitis to begin with.
How long is pink eye contagious, and do you have to stay home?
Infectious pink eye is contagious for as long as the eye is producing tears or discharge. The CDC frames it that simply: viral and bacterial conjunctivitis can spread while symptoms are present, which for viral cases means potentially the full one to two weeks. Antibiotic drops can shorten the contagious period for bacterial infection but do nothing for the far more common viral type.
Spread happens through hands, not through eye contact, despite the persistent playground belief that looking at someone with pink eye will give it to you. Someone rubs an infected eye, touches a doorknob or a shared tablet, and the next person touches that surface and then their own face. Adenoviruses in particular survive on surfaces for extended periods, which is why household and classroom clusters are so common.
Whether you or your child must stay home is less about medicine than about local rules. The NHS advises that people with conjunctivitis do not need to stay away from work or school unless they feel generally unwell. In the United States, the CDC notes that many schools and daycare centers have their own policies, some of which require a child to be seen by a clinician or to have started treatment before returning. It is worth knowing your school’s rule before the crusty morning arrives, because a policy that demands drops can end up driving a prescription that the eye itself does not need.
The measures that actually reduce transmission are the same regardless of setting: frequent hand washing, not sharing towels, pillows, or eye makeup, wiping discharge with disposable tissues, and keeping hands away from the face. A child who can manage those reasonably well is not a materially greater risk than the classmate with a cold sitting next to them.
Contact lens wearers, newborns, and other situations that change the plan
Most of this article describes the ordinary case. A handful of situations rewrite the rules, and they are worth spelling out because the wrong reassurance in these groups can be harmful.
Contact lens wearers come first. Lenses can carry bacteria onto the eye and create tiny scratches on the cornea that let those bacteria in. What looks like simple pink eye in a lens wearer can be the early stage of bacterial keratitis, an infection of the cornea itself that threatens sight. The Mayo Clinic and CDC both advise lens wearers with a red eye to remove their lenses immediately and be examined, and to discard the lenses and case rather than reuse them. This is the group where clinicians most consistently reach for antibiotic drops, and where waiting is not usually advised.
Newborns are the second group. Conjunctivitis in the first month of life can be caused by bacteria acquired during birth, including those responsible for gonorrhea and chlamydia, which can damage the eye quickly. MedlinePlus and the Mayo Clinic describe this as needing urgent medical assessment, sometimes with laboratory testing and treatment that goes beyond drops. A blocked tear duct is a far more common and benign cause of a sticky eye in infants, but distinguishing the two is a clinician’s job, not a parent’s.
People with weakened immunity, those who have had recent eye surgery, and adults with sudden, severe, copious pus may also have conjunctivitis that behaves differently and progresses faster. In each of these situations the threshold for examination and for treatment is lower, and the general advice to watch and wait does not apply. If you belong to one of these groups, that fact belongs at the top of your conversation with the care team.
What people often get wrong about pink eye and antibiotics
Myths about conjunctivitis are unusually sticky, partly because the condition is common enough that everyone has a story. Here are the ones clinicians hear most, corrected against the evidence.
Every pink eye needs drops. It does not. The JAMA systematic review puts most infectious cases in the viral column, where antibiotics have no target, and the CDC notes mild bacterial cases often improve on their own.
Green discharge means bacteria. It raises the odds but does not decide the question. Heavy viral infections can produce cloudy discharge too, and clinicians weigh it alongside itching, the pattern of spread, recent colds, and age.
Leftover drops from the last episode are fine. They are not. Opened bottles can become contaminated, the previous prescription may have been for a different problem, and some drops, particularly steroids, can seriously worsen certain infections. The Mayo Clinic advises against using old or someone else’s eye medicines.
Once the eye looks better you can stop the drops. If a clinician has prescribed a course, changing or stopping it is a decision to make with them, not on the basis of appearance alone.
Breast milk, urine, or honey in the eye will clear it. There is no reliable evidence from any mainstream medical source that these help, and introducing non-sterile fluids into an infected eye carries its own risks.
Antibiotic drops stop it spreading to the other eye. For viral conjunctivitis, which is the type most likely to jump eyes, they do not. Hand hygiene does.
You can catch pink eye by looking at someone who has it. Transmission is through hands and surfaces, as the CDC describes, not through line of sight.
Red eye always means pink eye. Uveitis, acute glaucoma, corneal ulcers, and other conditions also cause redness, which is exactly why pain, light sensitivity, and blurred vision are treated as red flags rather than as bad pink eye.
Why fewer antibiotic prescriptions for pink eye is good medicine
It can feel like a downgrade to leave an appointment without a prescription. The evidence suggests the opposite: for most people with pink eye, not being handed antibiotic drops is the better-quality outcome.
The first reason is resistance. The WHO identifies antimicrobial resistance as one of the leading global public health threats, and every unnecessary course, including topical courses, contributes to the pressure that selects for resistant bacteria. Eye drops are not exempt; resistant strains of the bacteria that cause conjunctivitis have been documented, and they make the genuinely bacterial cases harder to treat for everyone.
The second reason is direct harm. Antibiotic drops can sting, blur vision briefly, and occasionally trigger allergic reactions that make the eye redder and itchier than the original infection did. Preservatives in some formulations irritate the surface of the eye. For a viral infection that was always going to resolve in ten days, that is risk without benefit.
The third reason is diagnostic. Starting drops on a hunch can delay recognition that the problem was never bacterial conjunctivitis. A herpes infection, an allergic reaction, or an early corneal problem may be papered over for a week while the real cause advances.
There is also the plainer matter of medicine matching the problem. The JAMA review’s finding that antibiotics offer only a modest, days-long advantage in bacterial cases, and none in viral ones, means a blanket prescribing habit treats hundreds of people to help a few by a small margin. Guideline bodies on both sides of the Atlantic have moved toward supportive care and delayed prescribing for exactly this reason.
None of this makes antibiotics the villain. They are precisely the right tool for the situations described earlier. The goal is to use them where they work, not to use them everywhere a pink eye appears.
Questions to ask your care team
A good consultation about pink eye is short, but it should leave you understanding the reasoning, not just the outcome. These questions tend to draw out that reasoning without taking much time.
- Based on what you see, do you think this is more likely viral, bacterial, or allergic, and what points you that way?
- Is there anything about my situation, such as contact lenses, my immune system, or recent surgery, that changes how you would normally handle this?
- If you are recommending antibiotic drops, what specifically do you expect them to do, and how soon should I notice a difference?
- If you are recommending we wait, what should I watch for that would mean coming back sooner?
- Would a delayed or back-up prescription make sense for me, to be started only if things worsen?
- When is it safe to go back to wearing contact lenses, and should I throw away my current pair and case?
- Does my child need to stay home from school or daycare, and is there a note the school will need?
- Are there any drops I already have at home that I should definitely not use for this?
- How should I handle towels, pillowcases, and hand washing to protect the rest of the household?
- If this is allergic, what is likely triggering it, and what class of drop would target that mechanism?
You are not expected to decide any of this yourself. The questions are there so the decision your care team makes is one you understand and can follow through on, including knowing exactly which changes in the eye should bring you back to the door.
When to call your doctor: red-flag signs that should not wait
Most pink eye is a nuisance rather than a threat. The signs below are the exceptions, drawn from the CDC and the Mayo Clinic, and they mean the eye should be examined promptly rather than watched at home.
- Pain in the eye, as opposed to grittiness or mild irritation.
- Sensitivity to light that makes you want to squint or shield the eye.
- Blurred vision that does not clear when you blink away the discharge.
- Intense redness, or redness that is rapidly worsening.
- Symptoms that are getting worse rather than better, or that have not begun to improve after a week or two.
- A red eye in someone who wears contact lenses.
- Any conjunctivitis in a newborn, within the first month of life.
- A red eye in someone with a weakened immune system, whether from illness or from medicines.
- Fever with a red eye, or swelling and redness of the eyelid skin that is spreading, which can signal infection beyond the conjunctiva.
- A history of recent eye surgery or injury to the eye.
If you were prescribed drops and the eye is not improving in the timeframe your clinician described, or you develop a new reaction such as increased swelling or itching after starting them, contact the prescriber before making any change. Seek emergency care without delay for sudden severe pain, sudden loss of vision, or a red eye following a chemical splash or an object striking the eye.
None of these signs is a diagnosis. They are the triggers for an examination by someone who can look at the cornea and the inside of the eye, and every decision that follows, about drops, tests, or referral, belongs to that treating team.
Frequently asked questions
Do you just let pink eye run its course?
For most people, yes, with supportive care rather than neglect. Viral pink eye has no targeted treatment and settles within one to two weeks according to the CDC, and mild bacterial cases often improve on their own. Cool or warm compresses, gentle lid cleaning, lubricating drops, and strict hand hygiene are the plan. Exceptions include contact lens wearers, newborns, people with weakened immunity, and anyone with pain, light sensitivity, or blurred vision, who should be examined.
Should I go to the doctor for pink eye?
Not always, but certain situations make it wise. See a clinician if you wear contact lenses, have thick pus that keeps returning, have a weakened immune system, or the affected person is a newborn. Pain, light sensitivity, blurred vision that does not clear with blinking, or worsening symptoms after several days also warrant an examination. A mild, watery, itchy or gritty eye in an otherwise healthy person can usually be managed at home while you watch for those signs.
Will pink eye go away on its own?
Usually. The CDC describes viral conjunctivitis as clearing in 7 to 14 days without medication, occasionally stretching to three weeks, and bacterial conjunctivitis as often improving within 2 to 5 days untreated, with full resolution in up to two weeks. Allergic conjunctivitis lasts as long as the trigger is around. If an eye is not improving after a week or two, or is getting worse, that persistence is itself a reason to be seen.
How can you tell if pink eye is bacterial or viral?
Often you cannot be certain from appearance alone, and clinicians weigh several clues together. Watery discharge, a recent cold, spread from one eye to the other, and a tender lump in front of the ear lean toward a virus. Thick yellow or green discharge and lids stuck shut on waking lean toward bacteria, especially in young children. A rapid adenovirus test exists in some settings, but the overall pattern, plus your age and lens use, usually guides the decision.
Can antibiotic eye drops make viral pink eye go away faster?
No. Antibiotics attack structures that bacteria have and viruses lack, such as cell walls and bacterial protein-making machinery. Adenovirus, which the JAMA systematic review identifies as the cause of most viral conjunctivitis, has none of those targets, so the drops cannot shorten the infection or stop it spreading to the other eye. They can, however, cause stinging or allergic irritation. Supportive care and time are the treatment for viral pink eye.
How long is pink eye contagious?
As long as the eye is producing tears or discharge, according to the CDC. For viral conjunctivitis that can mean the full one to two weeks of the illness. Antibiotic drops can shorten the contagious period for bacterial cases but have no effect on viral ones. Spread is through hands and contaminated surfaces rather than eye contact, so frequent hand washing, not sharing towels or pillows, and keeping hands away from the face are what actually protect other people.
Does my child have to stay home from school with pink eye?
It depends on the school’s policy more than on the medicine. The NHS advises that children do not need to stay away unless they feel generally unwell. In the United States, the CDC notes many schools and daycare centers set their own rules, some requiring a clinician’s visit or started treatment before return. Ask your school in advance so a policy, rather than the eye itself, does not end up driving an unnecessary prescription.
Is it safe to use leftover eye drops from a previous infection?
No. Opened bottles can become contaminated with bacteria, the earlier prescription may have been for a different problem, and some drops, particularly steroid drops, can dramatically worsen certain infections such as herpes of the eye. The Mayo Clinic advises against using old or another person’s eye medicines. If you think drops are needed, the eye should be examined and a fresh, specific decision made by the clinician.
What if I wear contact lenses and get pink eye?
Remove the lenses right away and arrange to be examined rather than waiting it out. Lens wearers are at higher risk of bacterial keratitis, an infection of the cornea that can threaten sight and can start out looking like ordinary conjunctivitis. The CDC and Mayo Clinic advise discarding the lenses and case rather than reusing them, and not returning to lenses until the eye has fully recovered and a clinician confirms it is safe.
When should pink eye be treated as an emergency?
Seek urgent care for sudden severe eye pain, sudden loss or marked blurring of vision, a red eye after a chemical splash or an object striking the eye, or any conjunctivitis in a newborn. Spreading redness and swelling of the eyelid skin with fever can signal infection beyond the conjunctiva and also needs prompt assessment. These are triggers for examination, not diagnoses; the treating team decides what comes next.
References
- CDC: About Conjunctivitis (Pink Eye)
- NHS: Conjunctivitis
- MedlinePlus: Conjunctivitis or pink eye
- WHO: Antimicrobial resistance fact sheet
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Cataracts in Younger Adults: Steroid Use, Injury and Diabetes as Drivers of Early Treatment
Cataracts at a young age most often trace back to a specific cause rather than to aging: long-term corticosteroid use, diabetes, or an eye…

LASIK vs PRK: Same Laser, Different Surface, and How Recovery and Candidacy Diverge
LASIK and PRK use the same excimer laser to reshape the cornea and treat similar prescriptions. LASIK works beneath a thin hinged flap, so…

Strabismus Surgery Recovery: Red Eyes, Temporary Double Vision and Returning to School or Work
Strabismus surgery recovery is usually measured in days for comfort and weeks for appearance. Most people go home the same day; the operated eye…

Why Astigmatism Blurs and Stretches Vision at Every Distance and How Care Is Planned
Astigmatism blurs vision at every distance because the cornea or lens is curved more steeply in one direction than the other, so light focuses…
What Robotic Ophthalmology Changes in the Operating Room: Steadier Hands, Same Surgeon
Robotic eye surgery uses a surgeon-controlled mechanical arm to hold and move instruments inside the eye with less tremor and finer motion than an…

ReLEx SMILE Recovery: When Screens, Workouts and Swimming Come Back
Most people return to desk work and light screen use within one to two days of SMILE eye surgery, while vision keeps sharpening and…