

Follow-Up After Thyroid Cancer: What Blood Tests and Ultrasound Track Over Time
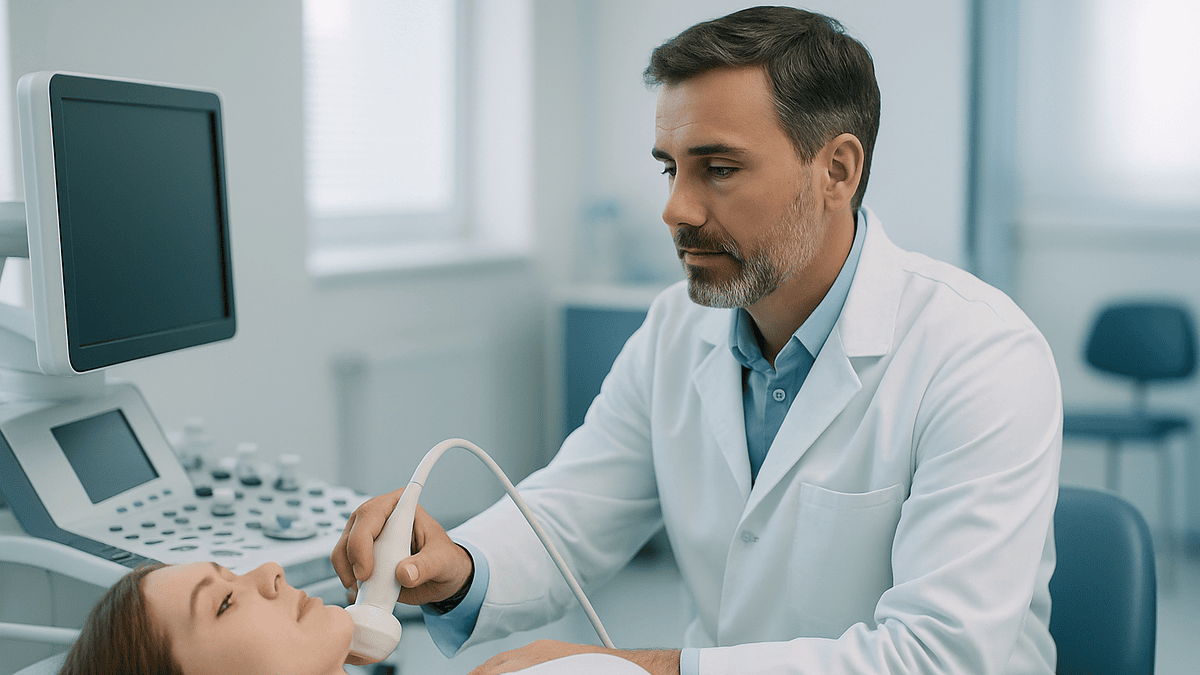
Key Takeaways
- Thyroglobulin only works as a tumor marker after the thyroid has been removed, because normal thyroid tissue produces it too.
- Thyroglobulin antibodies can make the marker read falsely low, so a falling antibody trend over time is itself used as a reassuring sign.
- TSH reflects how hormone replacement is set, not whether cancer is present, and the target is deliberately individualized to your risk group.
- Most recurrences of papillary cancer are found in neck lymph nodes by ultrasound and bloodwork before they cause any symptoms.
- Medullary thyroid cancer is tracked with calcitonin and CEA rather than thyroglobulin, because its cells come from a different lineage.
- Guideline-based follow-up re-draws your risk label at every visit, so surveillance often becomes less intensive after an excellent early response.
After treatment for differentiated thyroid cancer, follow-up usually rests on three blood tests, thyroglobulin, thyroglobulin antibodies and TSH, paired with a neck ultrasound. Thyroglobulin acts as a tumor marker once the thyroid is removed, TSH shows whether hormone replacement is set at the level your team intends, and ultrasound checks the thyroid bed and lymph nodes. Frequency depends on your risk group and how results trend over time.
The envelope arrives, or the patient portal pings, and there it is: a thyroglobulin result of 0.3. Last time it was undetectable. Six months before that, undetectable too. For most people two years past a thyroidectomy, that single decimal point can swallow an afternoon.
Thyroid cancer follow up blood tests are unusual in oncology. Very few cancers leave behind a marker this specific, and very few allow a clinician to watch a number drift up or down for years before anything shows on a scan. That is a genuine advantage, but it also means the numbers carry more emotional weight than they can bear on their own.
This explainer walks through what each test actually measures, why an ultrasound is the natural partner to the bloodwork, how the schedule loosens for many people over time, and which results deserve a phone call rather than a sleepless night. Every decision described here belongs to your treating team; the goal is that you understand the conversation.
Why thyroid cancer follow up blood tests matter more than any single scan
Most thyroid cancers are papillary or follicular, together called differentiated thyroid cancer because the cells still behave, in part, like normal thyroid tissue. Cleveland Clinic puts papillary cancer alone at up to roughly 80% of all thyroid cancers. That shared ancestry is the whole basis of follow-up: differentiated cancer cells keep making thyroglobulin, a protein produced only by thyroid tissue, and they keep responding to thyroid-stimulating hormone.
Once the thyroid gland has been surgically removed, and especially if remaining fragments were treated with radioactive iodine, the body should have almost no source of thyroglobulin left. So a blood test that would be meaningless in a person with an intact thyroid becomes a sensitive smoke detector. A rising trend can flag persistent or returning disease months before anything is large enough to feel or image.
Blood tests also do something imaging cannot. They are repeatable without radiation, they cost nothing in recovery time, and they give a trajectory rather than a snapshot. A scan tells you what is there today; a series of thyroglobulin values tells you which direction things are moving.
The pairing with neck ultrasound is deliberate. Ultrasound sees structure, meaning the thyroid bed and the lymph nodes of the neck, while blood tests see biochemistry. Each covers a blind spot in the other. A person can have a clearly abnormal lymph node with a thyroglobulin that stays low, and another can have a slowly climbing marker with a perfectly clean neck. Guideline-based follow-up, as described by the NHS and Mayo Clinic, uses both together and lets the combination, not either alone, guide the next step.
How follow-up actually works: the loop of test, ultrasound and reassessment
Follow-up is not a fixed timetable handed over at discharge. It is a loop, and understanding the loop makes the appointments far less mysterious.
It starts with an initial risk estimate. Your team looks at the pathology report, including tumor size, whether cancer had grown beyond the gland, whether lymph nodes were involved, the specific subtype, and any spread found on imaging. From this they place you in a broad category, commonly described as low, intermediate or high risk of the cancer persisting or returning. That first estimate sets how intensive the early monitoring will be.
Then the loop begins. Blood tests and an ultrasound are done, and the results are compared against what was expected for someone in your category. Many clinicians describe the outcome using four plain labels, sometimes called response to therapy:
- Excellent response: no detectable disease on imaging and thyroglobulin at or near undetectable, with negative antibodies.
- Indeterminate response: findings that are neither clearly clean nor clearly abnormal, such as low but detectable thyroglobulin or a tiny non-specific node.
- Biochemical incomplete response: thyroglobulin higher than expected, or rising, with nothing visible on imaging.
- Structural incomplete response: something visible, in the neck or elsewhere, that is thought to be cancer.
Here is the part people rarely hear: the label is re-drawn at every visit. Someone who started as intermediate risk and has shown an excellent response for a couple of years is now, in practical terms, low risk, and the schedule and hormone targets often relax accordingly. The reverse is also true. This dynamic approach is why your team may sound relaxed at one visit and order extra imaging at the next; they are responding to the trend, not the original diagnosis.
Thyroglobulin levels after thyroidectomy: what the number really means
Thyroglobulin is the storage protein inside which the thyroid builds its hormones. MedlinePlus describes the blood test for it as a tumor marker used mainly after treatment for thyroid cancer, not as a way to diagnose it. That distinction matters, because before surgery everyone has thyroglobulin in their blood and the level tells you almost nothing about cancer.
After a total thyroidectomy, the expected level is very low, and after radioactive iodine has cleared the last normal fragments, it is often undetectable on modern high-sensitivity assays. A value that is low and stable is the reassuring pattern. A value that is low but detectable is common and is usually interpreted as indeterminate rather than alarming; small remnants of normal thyroid tissue can produce it for years. The pattern clinicians watch for is a sustained rise across several tests.
Two practical points shape how the number is read. First, thyroglobulin production increases when TSH is high, so a level drawn while you are on suppressive hormone therapy (an unstimulated value) is not directly comparable with one drawn after your team deliberately raised TSH, either by pausing hormone tablets under supervision or by using an injected form of TSH (a stimulated value). Second, different laboratories use different assays, and results can differ between them. Using the same lab each time is not fussiness; it is what makes the trend trustworthy.
After a lobectomy, where half the gland remains, thyroglobulin is far less useful because the remaining lobe keeps producing it normally. In that situation ultrasound and clinical examination carry more of the load, and your team may still check the level occasionally to make sure it is not climbing unexpectedly.
Thyroglobulin antibodies: the result that can blur the picture
Some people’s immune systems make antibodies against thyroglobulin. This is especially common in those who also have autoimmune thyroiditis, the Hashimoto pattern of inflammation that often coexists with papillary cancer. The antibodies themselves are not dangerous, but they cause a technical problem: they bind thyroglobulin in the sample and can make the measured level read falsely low. A reassuring undetectable result in someone with strong antibodies may not mean what it appears to mean.
For that reason, laboratories measure thyroglobulin antibodies alongside thyroglobulin every time. If antibodies are negative, the thyroglobulin value can be trusted. If they are positive, your team shifts its weight in two directions.
The first shift is toward the antibody trend itself. Once the thyroid and any residual tissue are gone, the immune system has less thyroglobulin to react to, so antibody levels commonly fall over the following years. A steadily declining antibody titer is generally taken as a good sign; a persistently rising one, without another explanation, can prompt a closer look with imaging, because it suggests the immune system is still meeting thyroglobulin somewhere. This is the idea behind using antibodies as a surrogate marker, and it is an interpretation of pattern rather than a precise measurement.
The second shift is toward ultrasound. When the blood marker is unreliable, structural imaging becomes the primary surveillance tool, and some teams image more regularly than they would for an antibody-negative person with the same pathology.
What antibodies do not do is change your prognosis on their own. Their presence complicates monitoring; it does not, by itself, mean cancer is more likely to return. If your results carry an antibody flag, ask your team to walk you through how they are compensating for it.
TSH levels after thyroid cancer: why the pituitary signal is tracked
Thyroid-stimulating hormone, TSH, is the pituitary gland’s message telling thyroid tissue to grow and produce hormone. Without a thyroid, you take levothyroxine, a synthetic version of the main thyroid hormone, to replace what the gland made. Your TSH result shows how the pituitary is reading that replacement: high TSH means it senses too little hormone, low TSH means it senses plenty.
Here is where thyroid cancer differs from ordinary hypothyroidism. Because differentiated cancer cells can respond to TSH, teams sometimes aim to keep TSH deliberately lower than normal in the early years, so that any lingering cells receive less encouragement to grow. This is called TSH suppression. How low, and for how long, depends on your risk category and your response to therapy, and it is one of the decisions most likely to change as your results accumulate.
Suppression is not free. Long periods of low TSH can accelerate bone loss and raise the chance of heart rhythm problems such as atrial fibrillation, risks that matter more with age and with pre-existing heart or bone conditions. That trade-off is why guideline-based practice, reflected in Mayo Clinic and NHS patient information, describes hormone targets that are individualized rather than universal, and why someone with an excellent response is often moved toward a normal TSH range over time.
Two things are worth knowing. TSH responds slowly; after any change in hormone therapy it typically takes several weeks to settle, so a check drawn too soon can mislead. And pregnancy, planned or confirmed, changes hormone requirements substantially, so tell your team early. Never adjust your own tablets based on a result you read online; the target is set by your prescriber, and it is set for a reason.
Calcium, parathyroid hormone and the other labs your team may check
Thyroid cancer follow up blood tests are not only about the cancer. A few other results matter, and one of them is urgent in the first days after surgery.
The four parathyroid glands sit against the back of the thyroid and regulate blood calcium. Surgery can bruise or, less often, permanently damage them, causing hypoparathyroidism, a state of too little parathyroid hormone and therefore low calcium. Symptoms include tingling around the mouth and fingertips and muscle cramps. Calcium and parathyroid hormone are checked closely early on, and for people whose glands do not recover, calcium and vitamin D monitoring continues indefinitely. Johns Hopkins lists this among the recognized effects of thyroid surgery that follow-up is designed to catch.
Medullary thyroid cancer plays by different rules. It arises from C cells, which do not make thyroglobulin, so that marker is useless. Instead teams track calcitonin, the hormone C cells produce, and carcinoembryonic antigen (CEA), a protein some tumors release. How fast these values double over time is often more informative than any single result. Genetic testing for inherited forms is also part of the medullary pathway, because it affects family members.
Anaplastic thyroid cancer, which is rare and aggressive, is monitored mainly with imaging and clinical assessment rather than a blood marker.
For the smaller group whose disease is treated with targeted oral therapies for advanced cancer, routine labs such as liver, kidney and blood pressure monitoring become part of the visit.
One question comes up constantly: what labs would indicate thyroid cancer in the first place? Honestly, none reliably do. TSH is usually normal at diagnosis, and thyroglobulin is not a screening test. Thyroid cancer is found through examination, ultrasound and needle biopsy, not through a blood panel, which is why a normal set of labs before diagnosis is not a missed signal.
Neck ultrasound after thyroid cancer: what the sonographer is looking for
Ultrasound uses sound waves to build a live picture of soft tissue, with no radiation and no injection. For the neck it is unusually good, because the structures of interest lie close to the skin. Mayo Clinic describes it as a routine part of monitoring after thyroid cancer treatment.
The examination has two targets. The first is the thyroid bed, the space where the gland used to be, where a small nodule could represent leftover thyroid tissue, scar, or recurrence. The second is the lymph node chains, both the central compartment immediately around the airway and the lateral compartments along the sides of the neck. Papillary cancer in particular tends to travel to these nodes, and they are where most recurrences are found.
Normal lymph nodes are oval, with a bright fatty center called a hilum. The features that make a sonographer pause are different: a node that has become rounded, has lost its hilum, shows tiny bright calcifications, contains cystic areas, or has disorganized blood flow. No single feature is definitive. Many small nodes that look slightly unusual turn out to be reactive, meaning the immune system has simply been busy.
What happens next depends on size and behavior. Small indeterminate nodes are usually watched rather than biopsied, because sampling them is difficult and treating them offers little benefit. A node that is growing or clearly suspicious may be sampled with a fine needle, and the fluid can be tested for thyroglobulin as well as examined under a microscope.
Ultrasound is operator dependent. The same team, or at least the same imaging service, comparing directly against previous images gives you the most reliable read on whether something has changed. If you move or switch providers, ask for your prior images to travel with you.
Which tests apply to you? A summary by thyroid cancer type and treatment
People often compare notes in support groups and come away unsettled, because their neighbor’s schedule looks nothing like theirs. Usually the difference is not quality of care; it is cancer type and the extent of surgery. This table summarizes the general pattern described across NHS, Mayo Clinic and National Cancer Institute patient information. Your own plan may differ, and that is expected.
| Situation | Main blood tests | Main imaging | What the team is mostly watching |
|---|---|---|---|
| Papillary or follicular cancer after total thyroidectomy, with or without radioactive iodine | Thyroglobulin, thyroglobulin antibodies, TSH; calcium early on | Neck ultrasound | Thyroglobulin trend; lymph node changes; hormone target |
| Papillary or follicular cancer after lobectomy (half the gland removed) | TSH; thyroglobulin has limited value because the remaining lobe produces it | Neck ultrasound of the remaining lobe and nodes | New nodules in the remaining lobe; nodes; whether hormone replacement is needed at all |
| Medullary thyroid cancer | Calcitonin and CEA; calcium; genetic testing at diagnosis | Neck ultrasound; further imaging guided by marker levels | How quickly calcitonin and CEA rise, if they rise |
| Anaplastic thyroid cancer | General labs; no specific tumor marker | CT or other cross-sectional imaging | Structural change and symptoms |
| Any type with thyroglobulin antibodies present | Antibody trend used as a surrogate marker | Ultrasound carries more weight | Whether antibodies fall over time |
Two clarifications. Whole-body radioactive iodine scans are not a routine part of ongoing surveillance for most low-risk people who have shown an excellent response; they are used selectively. And PET scanning is generally reserved for the puzzling scenario of a rising marker with a clean ultrasound, when the team needs to find where the signal is coming from. If you are offered either, it reflects a specific question your team wants answered, not a routine step everyone gets.
Who gets closer surveillance, and who is usually asked to wait and watch
The single biggest determinant of how often you are tested is the risk category from your pathology and your early results, not how anxious you or your clinician happen to be.
Closer surveillance is typical for people whose cancer had grown through the thyroid capsule into surrounding tissue, who had numerous or large lymph nodes involved, who had spread beyond the neck, whose pathology showed a more aggressive subtype, or whose early thyroglobulin did not fall as expected. For this group, visits are more frequent, hormone targets are usually lower, and additional imaging is used more readily.
A different group is asked, in effect, to wait. Someone with a small cancer confined to the gland, no involved nodes, clean margins and an undetectable thyroglobulin at the first check has a very different outlook, and the National Cancer Institute describes most thyroid cancers as found early and highly treatable. For them, intensive testing offers little; it mostly generates indeterminate results that create worry without changing management. Guideline-based practice moves this group toward less frequent visits and a normal hormone range sooner.
Waiting also applies to findings, not just people. A tiny node with borderline features, or a low detectable thyroglobulin that is not rising, is very often observed rather than acted upon. This can feel like inaction. In reality it is a decision grounded in evidence that many such findings never progress and that chasing them with repeat surgery carries real risks to the voice and parathyroid glands.
At the far end of waiting sits active surveillance, offered by some teams for the smallest papillary cancers, where the tumor is monitored with ultrasound instead of being removed at all. Whether that path is appropriate is a highly individual judgment, and it belongs firmly with the treating team.
What the first months and years after treatment usually look like
Timelines below are typical ranges drawn from NHS and Mayo Clinic patient guidance. Your own may run faster or slower, and that is not a warning sign in itself.
The first days and weeks. Attention is on the wound, the voice and calcium. If levothyroxine was started, it needs time to reach a steady state; TSH is usually rechecked several weeks after starting or after any change, because testing sooner gives a misleading picture. If radioactive iodine is planned, it generally happens within the first few months and is followed by a scan to show where the iodine was taken up.
The first year. This is when the response-to-therapy label is first drawn. A thyroglobulin, antibody and TSH panel, together with a neck ultrasound, is typically performed within the first six to twelve months after treatment. Many people describe this visit as the emotional turning point: the first time the plan is based on how their body actually responded rather than on predictions.
Years one to five. The NHS describes check-ups continuing at regular intervals, commonly every six to twelve months at first, becoming less frequent if results remain reassuring. Ultrasound is not necessarily repeated at every visit for people with an excellent response; blood tests often carry the surveillance between scans.
Beyond five years. For many people the rhythm settles to an annual review of blood tests and hormone replacement. Differentiated thyroid cancer can occasionally return many years later, which is why some form of follow-up, even if only a yearly blood draw and hormone review, usually continues long term. For most, those visits increasingly resemble ordinary thyroid hormone management rather than cancer care.
If your schedule has not been explained to you in these terms, asking for a written outline is entirely reasonable.
Thyroid cancer recurrence symptoms: what people notice, and what they usually don't
The honest answer to the question of what recurrence feels like is that, most of the time, it does not feel like anything. The entire surveillance structure exists because blood tests and ultrasound generally pick up returning disease well before it produces symptoms. That is reassuring, and it also reframes the daily habit of neck-checking in the mirror: it is understandable, but it is not your primary safety net.
When recurrence in the neck does become noticeable, it tends to be as a new firm lump in the front or side of the neck that persists and slowly enlarges. Less often, a growing node or mass presses on nearby structures and causes hoarseness that does not resolve, a sense of food catching when swallowing, or a persistent cough with no other explanation. Spread beyond the neck, which is uncommon in papillary cancer, may show as bone pain that does not settle, or as breathing symptoms if the lungs are involved. Mayo Clinic and Cleveland Clinic both describe these as features that warrant assessment rather than proof of anything.
Context matters enormously. The neck contains dozens of lymph nodes that enlarge with colds, dental infections and skin irritation. A tender node that appeared with a sore throat and shrank within a couple of weeks has an obvious explanation. Voice change in the weeks after surgery is often nerve irritation that recovers. The features worth reporting are persistence and progression, not appearance alone.
This is not a checklist for self-diagnosis; it is a guide to what deserves a phone call. Bring anything new to your team and let them decide whether it needs an earlier ultrasound. Waiting for the next scheduled appointment is usually fine, but it should be their judgment, not yours, when a symptom is genuinely new.
Do I need to see an oncologist for thyroid cancer, or is an endocrinologist enough?
In many health systems the answer surprises people: a medical oncologist is often not the lead clinician for differentiated thyroid cancer. The core treatments, surgery and radioactive iodine, are delivered by surgeons and nuclear medicine specialists, and the long-term work of interpreting thyroglobulin and managing hormone therapy sits naturally with an endocrinologist, a physician who specializes in hormone systems. Johns Hopkins and the NHS both describe thyroid cancer care as multidisciplinary, meaning a team that includes the surgeon, endocrinologist, radiologist, pathologist, nuclear medicine physician and often a specialist nurse.
A medical oncologist typically becomes central when disease is advanced, no longer responds to radioactive iodine, or requires targeted drug therapy. For anaplastic cancer, oncology involvement is usual from the start. If your case is straightforward and you have never met an oncologist, that is not a gap in care; it reflects how this particular cancer is managed.
What you do need is one clinician who clearly owns the follow-up. Results that are copied to several specialists but interpreted by none of them are a real risk, especially years down the line when visits are infrequent. Ask directly who is responsible for reviewing your thyroglobulin trend and who you should contact between appointments.
A related question people search is how often thyroid cancer spreads. Guideline sources describe it this way: papillary cancer quite commonly involves lymph nodes in the neck at diagnosis, and this does not, on its own, carry the grim implications that node involvement has in some other cancers. Spread to distant sites such as lungs or bones is much less common. The National Cancer Institute notes that most thyroid cancers are detected at an early stage. Your own pathology report gives a far more useful answer than any general statistic, so ask your team to translate it for you.
What people often get wrong about thyroid cancer follow up blood tests
Support forums are full of good intentions and a handful of persistent misunderstandings. These are the ones clinicians correct most often.
Any detectable thyroglobulin means the cancer is back. Not so. Low, stable, detectable levels are common and frequently reflect a small remnant of normal thyroid tissue. The signal that matters is a sustained rise over several measurements, interpreted alongside antibodies and imaging.
A normal TSH means everything is fine. TSH tells you about hormone replacement, not about cancer. Someone can have a perfectly placed TSH and a rising thyroglobulin, or the reverse. The tests answer different questions.
Taking levothyroxine is the follow-up. Hormone replacement is essential, but it does not monitor anything. Skipping blood tests because you feel well and take your tablet daily removes the surveillance layer entirely.
More scans are safer. Beyond what your risk category warrants, extra imaging mostly finds indeterminate specks that trigger anxiety and occasionally unnecessary procedures. Guideline-based practice reduces imaging for people with an excellent response precisely because the evidence favors it.
Supplements are irrelevant to the results. High-dose biotin, common in hair and nail products, can interfere with some laboratory immunoassays, including thyroid tests, and produce misleading values. Iodine-rich supplements such as kelp can interfere with radioactive iodine imaging. Tell your team what you take, and ask whether to pause anything before testing. Do not stop a prescribed medicine on your own.
A different lab is just as good. Thyroglobulin assays vary between manufacturers. A jump that coincides with a lab switch may be an artifact. Consistency protects the trend.
The fear should match the number. A decimal-point change is data, not destiny. Your team reads it in context; that context is what you are paying attention for.
Questions to ask your care team
The most useful appointments are the ones where you leave understanding not just the result but the plan behind it. Write questions down beforehand; the consultation room has a way of emptying the mind. These are the ones patients and clinicians tend to find most productive.
- Which risk category was I placed in at diagnosis, and has my response to treatment changed it?
- What thyroglobulin level would you expect for someone in my situation, and what pattern would prompt further imaging?
- Do I have thyroglobulin antibodies, and if so, how are you compensating for them in reading my results?
- What TSH range are you aiming for now, why that range, and when might it be relaxed?
- How often will I have blood tests and ultrasound over the next two years, and what would make that schedule change?
- Will I have my tests at the same laboratory and imaging service each time, and if not, how will you account for differences?
- Were my parathyroid glands affected, and do I need ongoing calcium or vitamin D monitoring?
- Who is the single person responsible for reviewing my results, and how do I reach that person between appointments?
- Are there supplements or medicines I should tell you about before tests, or pause under your guidance?
- If I am planning a pregnancy, what should change and when should I tell you?
- What symptoms should prompt me to contact you before my next scheduled visit?
- Do I need to see a medical oncologist at any point, and who decides that?
You are not obliged to ask all of these, and your team may answer several before you raise them. The point is to convert a set of numbers into a shared understanding of what is being watched, and why. A team that welcomes these questions is doing exactly what good follow-up requires.
When to call your doctor
Most of thyroid cancer follow-up happens on a calendar, and most concerns can wait for the next scheduled visit. A short list of situations should not.
Seek emergency care if you develop difficulty breathing, noisy or high-pitched breathing, a rapidly swelling neck, or severe muscle spasms, seizures or confusion. In the days after surgery, severe cramping with tingling around the mouth and in the hands and feet can indicate dangerously low calcium and needs same-day assessment.
Call your care team promptly, meaning within a day or two rather than waiting weeks, for:
- A new lump in the neck that persists beyond a couple of weeks or is clearly enlarging
- Hoarseness or voice change that develops well after surgery and does not improve
- Food or liquid catching when you swallow, or unexplained persistent cough
- Bone pain that does not settle, or new unexplained breathlessness
- Palpitations, a racing or irregular heartbeat, chest discomfort, unexplained weight loss, tremor or marked anxiety, which can signal too much thyroid hormone
- Marked fatigue, feeling cold, constipation or weight gain, which can signal too little
- A confirmed or suspected pregnancy, since hormone needs change quickly
- Any new medicine or supplement started by another clinician, so interactions with hormone therapy and tests can be checked
- A result that arrives without explanation and worries you; a call is better than a week of guessing
None of these signs is a diagnosis. Several have entirely benign explanations far more often than not. The reason to call is that your team can only interpret what it knows about, and thyroid cancer follow-up works best when small changes are assessed early. Every decision about further testing, imaging or treatment rests with the clinicians who know your history; your role is to keep them informed.
Frequently asked questions
What labs would indicate thyroid cancer before diagnosis?
No routine blood test reliably indicates thyroid cancer. TSH is usually normal at diagnosis, and MedlinePlus describes thyroglobulin as a marker for monitoring after treatment rather than a screening tool. Thyroid cancer is identified through physical examination, neck ultrasound and fine-needle biopsy of a suspicious nodule. A normal blood panel before diagnosis is therefore not a missed warning, and blood tests become useful mainly once the gland has been removed.
How are thyroglobulin levels after thyroidectomy interpreted?
The expected level after total thyroidectomy is very low or undetectable, particularly after radioactive iodine. A low but stable detectable value is common and often reflects a small remnant of normal tissue. Clinicians focus on the trend across several tests rather than one result, read alongside thyroglobulin antibodies and ultrasound. Results should ideally come from the same laboratory each time, because different assays can give different numbers for the same sample.
Do I need to see an oncologist for thyroid cancer follow-up?
Often not, at least for differentiated thyroid cancer managed with surgery and radioactive iodine. Follow-up is commonly led by an endocrinologist working within a multidisciplinary team, as the NHS and Johns Hopkins describe. A medical oncologist becomes central when disease is advanced, stops responding to radioactive iodine, or needs targeted drug therapy, and is involved from the start in anaplastic cancer. What matters most is that one named clinician owns your results.
How often does thyroid cancer spread?
Papillary thyroid cancer quite commonly involves lymph nodes in the neck at diagnosis, and this does not carry the same implications it has in many other cancers. Spread to distant sites such as lungs or bones is much less common, and the National Cancer Institute notes that most thyroid cancers are found at an early stage. Your own pathology report and imaging give a far more meaningful answer than general statistics, so ask your team to explain them.
What are the signs and symptoms of papillary thyroid cancer recurrence?
Most recurrences cause no symptoms and are detected by blood tests and ultrasound first. When symptoms do occur, the typical one is a persistent, slowly enlarging firm lump in the neck. Less often people notice lasting hoarseness, a catching sensation when swallowing, or an unexplained cough. Bone pain or breathlessness that does not settle can reflect spread beyond the neck. Persistence and progression matter more than a single new finding; report anything new to your team.
What should TSH levels be after thyroid cancer?
There is no single correct number. Your team sets a TSH target based on your risk category and how you have responded to treatment. In the early years after higher-risk disease, TSH may be kept deliberately below the normal range to reduce stimulation of any remaining cells; for people with a low-risk cancer and an excellent response, a normal range is often the goal sooner. The target is reviewed over time and should only be changed by your prescriber.
Can follow-up blood tests still help if I only had half my thyroid removed?
Partly. After a lobectomy the remaining lobe keeps producing thyroglobulin, so that marker loses much of its value as a cancer signal, although some teams still check it to make sure it is not rising unexpectedly. TSH is monitored to see whether hormone replacement is needed at all. Surveillance in this situation relies more on neck ultrasound of the remaining lobe and lymph nodes, together with clinical examination.
What does it mean if my thyroglobulin antibodies are positive?
It means your immune system makes antibodies that can interfere with the thyroglobulin test, making the result read falsely low. It does not by itself mean cancer is more likely to return. Your team will place more weight on neck ultrasound and will watch the antibody level over time; a gradual fall is generally reassuring, while a sustained rise without another explanation may prompt closer imaging. Ask how your results are being adjusted for this.
How often is neck ultrasound after thyroid cancer needed?
It depends on your risk category and response to treatment. An ultrasound is typically performed within the first six to twelve months after treatment, and the NHS describes check-ups continuing at regular intervals, commonly every six to twelve months at first, becoming less frequent if results stay reassuring. People with an excellent response often do not need imaging at every visit, with blood tests carrying surveillance in between. Your team decides the interval.
Can biotin or other supplements affect my thyroid cancer blood tests?
Yes. High-dose biotin, found in many hair and nail supplements, can interfere with some immunoassays used for thyroid tests and produce misleading results. Iodine-rich supplements such as kelp can affect radioactive iodine imaging. Tell your team everything you take and ask whether anything should be paused before a test. Never stop or change a prescribed medicine, including thyroid hormone, without guidance from your prescriber.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Basal Cell Carcinoma in Older Adults: How Treatment Is Tailored to Health and Skin
Basal cell carcinoma treatment in older adults is tailored to the tumor's size, location, subtype and growth rate, and to the person's overall health,…

Rash and Diarrhea on Targeted Therapy: Why They Happen and When to Contact the Team
Rash and diarrhea are common side effects of targeted cancer therapy because the molecular switches these drugs block, such as EGFR, also keep skin…
Who May Be a Candidate for SBRT for Early-Stage Lung Cancer When Surgery Is Not Planned
SBRT for early-stage lung cancer is usually considered for people with a small non-small cell lung cancer that has not spread to lymph nodes…

Why a PSMA PET Scan Comes Before Lutetium-177 PSMA Therapy and What It Has to Show
A PSMA PET scan comes before lutetium-177 PSMA therapy because the treatment only works on cancer cells that display the PSMA protein, and the…

Eating After Pancreatic Cancer Surgery: Enzyme Replacement, Blood Sugar and Small Meals
After pancreatic cancer surgery, many people need enzyme replacement because the remaining pancreas cannot release enough digestive enzymes; the capsules are taken with food…

Infection Prevention During Lymphocytic Leukemia Treatment: Vaccines, Habits, Warning Signs
CLL infection prevention during treatment rests on four layers: non-live vaccines timed around therapy (ideally before B-cell-depleting drugs, then again once the immune system…