

How a Permanent Pacemaker Is Implanted Under Local Anesthesia, and What the Leads Do
Key Takeaways
- The implant is done through an incision a few centimeters long below the collarbone under local anesthetic with sedation, and the NHS puts the typical procedure time at about an hour.
- Leads sense the heart's own beats first and pace only when a beat is missing, so a pacemaker never takes over a heart that is already beating adequately.
- Active-fixation leads use a tiny screw and passive leads use soft tines, but scar tissue growing over the following weeks is what anchors them for good, which is why arm movement is limited early on.
- Slow rhythms with a reversible cause, such as rate-slowing medicines, thyroid deficiency or the days after a heart attack, are usually treated or observed before anyone considers a device.
- The NIH StatPearls review puts overall complication rates in the low single digits, with pocket bleeding, lung puncture, lead dislodgement and infection the ones to know about.
- Generator batteries typically last 5 to 15 years according to Mayo Clinic, and replacement usually swaps only the generator through the original incision, leaving the leads in place.
A permanent pacemaker is implanted through a small incision below the collarbone under local anesthesia, usually with light sedation. Thin insulated wires called leads are guided through a vein into the heart under X-ray, tested, and connected to a matchbox-sized generator placed in a pocket under the skin. The leads sense the heart's own rhythm and deliver tiny electrical pulses only when the heartbeat is too slow.
The consult ends with a sentence that lands harder than the diagnosis itself: “You’ll be awake for it.” The heart’s natural wiring has been slowing, the monitor has caught pauses of several seconds, and now someone is describing a device the size of a matchbox that will sit under the skin for the rest of your life. Most people leave that appointment with two questions they did not think to ask in the room. What actually happens on the table, and what are those wires doing inside the heart?
Understanding how a permanent pacemaker is implanted takes the mystery out of both. The procedure belongs to the family of keyhole cardiac work: no ribs are opened, the heart keeps beating throughout, and the person on the table can usually hold a conversation. The leads, insulated wires no wider than cooked spaghetti, do the quiet work of listening and, only when needed, nudging.
This explainer walks through each stage in plain language, including what the following weeks tend to look like and which symptoms deserve a same-day phone call.
How a permanent pacemaker is implanted, step by step
Picture a bright room that looks more like a radiology suite than an operating theater. You lie on a narrow table beneath a large X-ray camera, connected to a heart monitor, a blood pressure cuff and an intravenous line. A nurse cleans the skin below one collarbone, usually on the side opposite your dominant hand, and drapes the area so only a small window of chest is visible. Most people receive a dose of antibiotic through the drip before the first cut, a standard step aimed at lowering infection risk.
The doctor numbs the skin and the tissue beneath it with local anesthetic, then makes an incision a few centimeters long. Under that incision runs a vein heading toward the heart, most often the cephalic, axillary or subclavian vein. A fine needle enters the vein, a guidewire follows, and a short plastic tube called a sheath is slid over the wire to create a working channel.
Through that channel the leads are advanced. Fluoroscopy, which is simply real-time X-ray, shows them curving through the great veins into the right side of the heart. Once each lead is positioned and tested, a pocket is opened between the skin and the chest muscle. The generator, the sealed battery-and-computer unit, is plugged into the leads and tucked into the pocket. The incision is closed with dissolvable stitches, skin glue or both.
From first injection to dressing, the NHS describes the whole process as typically taking about an hour, longer when three leads are needed. A chest X-ray afterwards confirms lead position and checks that the lung has not been nicked. Many people go home the same day or after one night, according to the same NHS guidance.
Why is it done under local anesthesia rather than general?
General anesthesia means being fully unconscious with breathing supported by a machine. Pacemaker implantation rarely needs that, because nothing about it requires stillness beyond what a relaxed, sedated adult can manage, and because the heart never stops. The team actually wants you breathing on your own, able to follow a request to take a deep breath or cough while lead stability is checked.

Local anesthetic blocks nerve signals from a small patch of chest. Alongside it, most centers give a sedative through the intravenous line. This is sometimes called conscious sedation: you are drowsy, calm and often unable to recall much afterwards, but you respond to your name. Mayo Clinic describes the approach as being awake with medicine to relax you and numb the area. Which sedative, how much and for how long are decisions for the anesthesiologist or cardiologist, based on your age, breathing history and anxiety level.
The practical benefits are real. Avoiding a breathing tube means fewer airway complications, particularly in older adults, who make up most pacemaker recipients. Recovery from sedation takes hours rather than a day, one reason same-day discharge is common. And you can tell the team if something hurts, which matters when a lead is being anchored in heart muscle.
General anesthesia is still chosen in some situations: young children, people who cannot lie flat or still, those whose anxiety does not settle with sedation, and complex cases such as lead extraction or surgical placement of leads on the outer surface of the heart. If being awake worries you, raise it at the pre-assessment visit rather than on the day; the plan can be adjusted.
What do pacemaker leads do inside the heart?
A healthy heartbeat begins in the sinus node, a cluster of specialized cells in the right upper chamber that fires about 60 to 100 times a minute at rest, the range MedlinePlus lists as normal. The impulse spreads across both atria, pauses briefly at the atrioventricular node, then races down to the ventricles. When the sinus node fires too slowly or the connection through the AV node fails, the pumping chambers may wait several seconds between beats. That is the gap a pacemaker fills.
Each lead has two jobs, and it does the first far more often than the second. The first is sensing: the electrode at the tip rests against heart muscle and reads the small voltage of each natural beat, feeding it back to the generator. The second is pacing: if the generator has heard nothing within a programmed interval, it sends a brief pulse down the lead, far too small to feel yet enough to make that chamber contract.
Modern devices pace on demand. Cleveland Clinic and the American Heart Association both stress that a pacemaker does not take over a heart that is beating adequately; it waits. In a dual-chamber system, one lead in the atrium and one in the ventricle let the generator preserve the natural sequence, so the atria fill the ventricles before they squeeze. Many generators also carry a motion sensor that raises the pacing rate when you climb stairs, mimicking what a healthy sinus node would do.
The lead body itself is a coiled conductor wrapped in silicone or polyurethane insulation, built to flex with every heartbeat for a decade or more. Mayo Clinic notes that generator batteries typically last 5 to 15 years; the leads usually stay in place when the generator is replaced.
How a permanent pacemaker is implanted: fixing and testing the leads
Getting a lead into the heart is the easy part. Making it stay, inside a chamber that contracts with every beat, is where the craft lies.
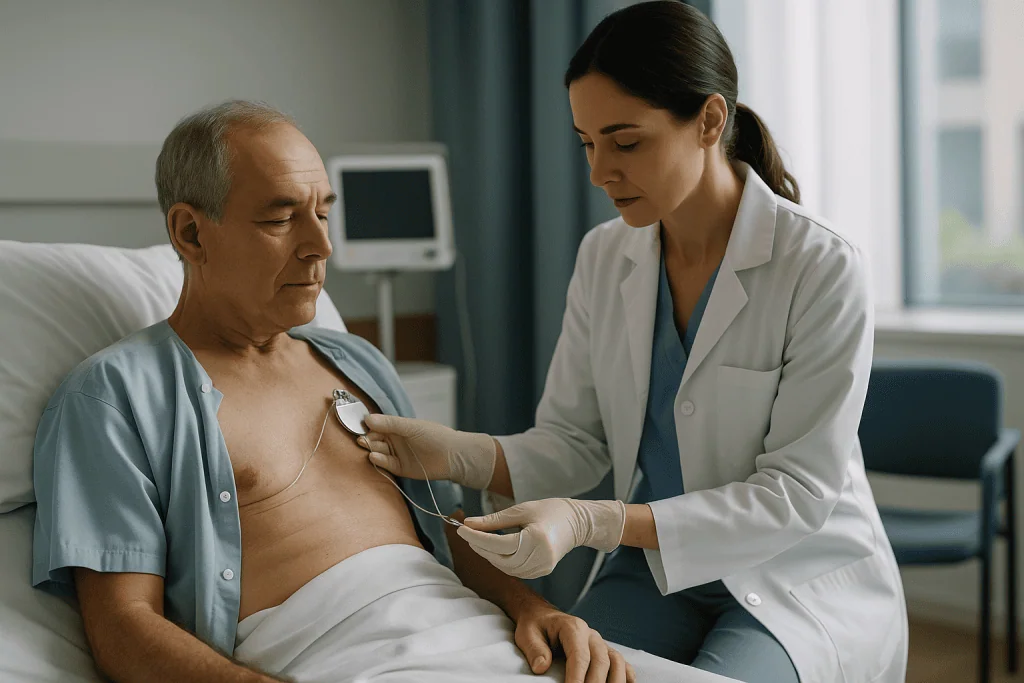
Two anchoring designs are in common use. Active-fixation leads carry a tiny corkscrew helix at the tip that the doctor extends by rotating the lead, screwing it a millimeter or two into the muscle. Passive-fixation leads instead have soft plastic tines, like the barbs of a miniature anchor, that catch in the muscle’s natural ridges. Active fixation allows placement almost anywhere; passive relies on textured regions such as the tip of the right ventricle or the right atrial appendage, the small pouch off the upper chamber.
Once a lead is seated, the team connects it to an external analyzer and takes three measurements. Sensing amplitude asks how clearly the electrode hears the heart’s own signal. Pacing threshold asks the minimum energy needed to make the chamber contract; lower is better because it spares the battery. Impedance, the electrical resistance along the lead, confirms the circuit is intact and the tip is in good contact. Poor numbers mean repositioning, which is why the procedure can run beyond the hour the NHS quotes as typical.
You may be asked to breathe deeply, cough or turn slightly while the doctor watches the tip on fluoroscopy to be sure it holds. The lead is then tied to the chest muscle with a sleeve and stitch near the vein entry. Over the following weeks, scar tissue grows around the tip and along the lead, anchoring it far more firmly than any helix or tines. That biological healing is the real reason your team limits arm movement early on.
For biventricular systems, a third lead travels through the coronary sinus, a vein on the back of the heart, to reach the left ventricle from the outside.
Who is a permanent pacemaker usually for, and who is asked to wait?
The core indication is symptomatic bradycardia: a heart rate slow enough to cause fainting, near-fainting, breathlessness, exhaustion or confusion. The usual culprits are sick sinus syndrome, in which the natural pacemaker cells wear out, and high-grade atrioventricular block, in which impulses from the atria fail to reach the ventricles. Both become more common with age, though neither is confined to older adults.
Other recognized reasons include very slow rates in atrial fibrillation, certain fainting disorders driven by reflex slowing of the heart and, for biventricular devices, heart failure with a specific electrical delay on the ECG. Cardiac society guidelines, including those the American Heart Association summarizes for patients, set out these categories, and your cardiologist maps your ECG and monitor findings onto them.
Just as instructive is who is asked to wait. A slow rate with a reversible cause is not usually treated with a device until that cause has been addressed. Medicines that slow conduction, including beta-blockers and some calcium-channel blockers, are common examples; the team may adjust them and re-check rather than implant. Thyroid deficiency, electrolyte disturbances, untreated sleep apnea, Lyme infection and the days immediately after a heart attack can all produce block that recovers on its own. Athletes and young adults frequently have resting rates in the 40s with no symptoms, and that alone is not an indication.
Active infection anywhere in the body is a reason to postpone, because bacteria in the bloodstream can settle on the new device. So is an uncontrolled bleeding tendency. None of this is refusal; it is sequencing. Whether and when to implant rests with your treating team, who weigh symptoms, monitor evidence and everything else happening in your body.
Single-chamber, dual-chamber, biventricular or leadless: how the systems compare
“Pacemaker” covers several quite different systems. The number and position of the leads is what separates them, and it shapes both the procedure and the follow-up.
| System | Leads and where they sit | Typically considered for | Notes on the implant |
|---|---|---|---|
| Single-chamber | One lead, usually in the right ventricle | Slow rates in permanent atrial fibrillation; selected sinus node disease | Shortest transvenous procedure; one vein puncture |
| Dual-chamber | Two leads: right atrium and right ventricle | AV block with a working sinus node; sick sinus syndrome | Preserves atrial-ventricular timing; the most common adult system |
| Biventricular (CRT) | Three leads: right atrium, right ventricle and, via the coronary sinus, the left ventricle | Heart failure with electrical delay between the ventricles | Longer procedure; coronary sinus anatomy can make the third lead harder to place |
| Leadless | No leads; a capsule anchored inside the right ventricle via a leg vein | Selected people needing ventricular pacing, especially with poor upper-vein access or high infection risk | No chest incision or pocket; delivered through a catheter from the groin |
The table simplifies. Some newer approaches place the ventricular lead in the heart’s own conduction bundle rather than the muscle, aiming to recruit the natural wiring, and some leadless designs now sense the atrium. Whether these suit you depends on your anatomy, your rhythm problem and your team’s experience with each.
What the table cannot show is time and trade-offs. The NHS describes standard transvenous implantation as taking about an hour in most cases, with three-lead systems at the upper end. A leadless implant skips the pocket and its wound-care worries but adds a large-vein puncture in the groin, which brings instructions about lying flat afterwards. Each option is a trade, and the treating team’s job is to explain which trade fits you.
Is a pacemaker major surgery?
The honest answer is that it sits in an in-between category, and the label depends on what you compare it with.
Against open-heart surgery, it is minor by any measure. The chest is not opened, no heart-lung machine is used, blood loss is usually minimal, and MedlinePlus describes the standard approach as a minimally invasive procedure done through a small cut. Most people are sitting up and eating within hours. The NHS notes that many go home the same day or the next morning.
Against having a mole removed, though, it is clearly more than minor. A foreign object is being placed permanently in your body. Wires are being anchored inside a beating heart under X-ray. There is a recognized, if small, risk of puncturing the lung or the heart wall. And the commitment is lifelong: device checks, eventual generator replacement, and a set of everyday precautions. Cardiologists tend to say “procedure” rather than “operation,” which is accurate but can undersell that seriousness.
Some situations genuinely turn the implant into bigger surgery. When the veins to the heart are blocked or absent, or in small children who would outgrow transvenous leads, surgeons may attach epicardial leads to the outside of the heart through a chest incision under general anesthesia. Lead extraction, removing old leads that have scarred into the veins, is likewise a specialized, higher-risk undertaking that only some centers perform.
A useful way to hold it: the implant itself is a short, well-rehearsed, locally anesthetized procedure, but the reason you need one, a heart whose electrical system is failing, is the serious part. Treat the day lightly and the aftercare seriously.
How painful is a pacemaker implant?
Ask people who have been through it and most describe pressure and pulling rather than pain. The sharpest moment is usually the local anesthetic itself, a sting and burn that fades within a minute as the tissue numbs. Sedation softens the memory further.
During the procedure you may feel the doctor working in the pocket, a tugging as the leads are secured, and occasionally a brief ache when a lead tip engages the heart muscle. Because you are conscious, you can say so, and more local anesthetic can be added. Some people notice their heart being paced during testing, a fluttering or a sense of the rhythm changing. It is not painful, just odd.
The days afterwards bring the discomfort most people remember. The pocket is bruised and tender, especially in slim people with little padding over the muscle. Raising the arm, reaching behind the back or lying on that side pulls on the incision. The NHS says you may feel some pain or discomfort during the first 48 hours and that pain-relieving medicine is usually enough; which product and how to take it is a conversation for your team, particularly if you take anticoagulants.
Pain should follow a downward slope. Mild tenderness for a couple of weeks is expected. What is not expected is pain that increases after the first few days, a pocket that becomes hot, red or visibly swollen, or a throbbing that keeps you awake. Those patterns can signal a hematoma, a collection of blood under the skin, or an infection, and they belong in the “call your doctor” category rather than “wait and see.”
Pacemaker surgery recovery time: the first days and weeks
Recovery unfolds in roughly four phases. The timings below are typical ranges drawn from NHS and Mayo Clinic guidance, not promises for any one person.
The first hours are about monitoring. You return to a bed with the heart monitor still attached, a pressure dressing over the pocket, and instructions to keep that arm low and quiet. A chest X-ray checks lead position and rules out a lung puncture. Before discharge, a technician holds a programmer wand over the device and confirms the leads are sensing and pacing as expected.
The first week is about the wound. Keep it dry until the team says otherwise, watch for the warning signs described later, and lift nothing heavier than a kettle with that arm. The NHS advises against driving a car for at least a week under UK rules; regulations differ elsewhere, so ask what applies to you. Many people return to desk work within days, though tiredness from sedation and the disrupted sleep beforehand often lingers.
Weeks two to six are about the leads settling. Scar tissue is anchoring the tips, so the NHS advises avoiding strenuous activity for around four to six weeks and keeping the elbow below shoulder height in the early part of that period. Walking, light chores and gentle stationary cycling are usually fine. The first outpatient check typically falls in this window, and it is when many teams fine-tune the pacing settings.
Beyond six weeks, most people resume their previous activities, including swimming, golf and gardening, once the team confirms the leads are stable. Device checks then continue at intervals your clinic sets, increasingly through a bedside monitor that transmits data overnight. Mayo Clinic puts battery life at 5 to 15 years, after which the generator, but usually not the leads, is replaced in a shorter procedure through the same incision.
What to avoid with a pacemaker, and what is perfectly safe
Most of household life is untouched. Microwaves, televisions, computers, electric blankets, hair dryers and remote controls pose no problem to modern shielded devices, as the American Heart Association and NHS both confirm. The genuine cautions cluster around three things: strong magnets, sustained close contact with certain electrical fields, and physical blows to the pocket.
Cell phones are safe to use, but the NHS advises holding them to the ear on the opposite side and keeping them at least 15 cm (about 6 inches) from the device, which rules out the shirt pocket on that side. Headphones with magnets, some smartwatch bands and magnetic phone cases deserve the same distance. Induction cooktops, large speakers, arc welding equipment and a running engine with the hood open are worth stepping back from; passing by is fine, leaning over them for minutes is not.
Store security gates and airport metal detectors can be walked through at normal pace. Do not linger inside the arch, and carry your device identification card so you can request a hand search rather than a handheld wand held over the chest.
Medical settings are the other place to speak up. MRI scanning was once off-limits; Mayo Clinic notes that many current systems are MRI-conditional, meaning scans are possible under settings agreed between the cardiology and radiology teams. Diathermy used in physical therapy, TENS units, radiotherapy and some dental and surgical equipment can interfere, so every clinician treating you should know the device is there.
Physically, avoid contact sports that could strike the chest wall over the pocket until the team clears you, and do not fire a rifle from that shoulder. Everything else, from sex to skiing, is a question of general fitness rather than of the device.
What are the risks, and how common are they?
Any honest explainer names the risks, and the good news is that they are uncommon and mostly early. The NIH StatPearls review of pacemaker insertion puts the overall complication rate in the low single digits, with individual problems each occurring in roughly 1 in 100 or fewer cases. These are the ones worth understanding.
Pocket hematoma is a collection of blood under the skin that makes the site swell and bruise. It is more likely in people taking anticoagulants, medicines that slow clotting to prevent stroke or vein clots. Whether those are paused, continued or adjusted around the procedure is a decision for the prescribing clinician; do not change them yourself. Pneumothorax, a puncture of the lung lining while the vein is accessed, lets air into the chest and causes sharp pain or breathlessness; small ones seal on their own, larger ones need a drain. Lead dislodgement, the tip slipping from its perch in the first weeks, may require a second procedure to reposition it.
Infection of the pocket or leads is uncommon but the most consequential, because an infected system usually has to come out. Cardiac perforation, a lead passing through the heart wall, is rare and is why teams watch for fluid around the heart afterwards. Rarer still are clots in the vein carrying the leads, which cause arm swelling, and stimulation of the diaphragm, felt as rhythmic hiccups.
Over years, leads can fracture or lose insulation, a lead crossing the tricuspid valve can worsen its leakiness, and the generator will need replacing. Remote monitoring is designed to catch most of these before symptoms appear. Alternatives are limited once symptomatic block or sinus disease is established, but observation, treating a reversible cause or a leadless device are all options your team may weigh with you.
What people often get wrong about pacemakers
“The pacemaker keeps my heart beating.” Not quite. It stops the heart from beating too slowly. If your own rhythm is adequate, the device does nothing but listen, sometimes for weeks at a stretch. Some people with complete block do rely on it for most beats, and your team can tell you what percentage of the time yours is pacing, but that is a fact about your heart, not a side effect of the device.
“I’ll feel it shock me.” That confuses a pacemaker with an implantable cardioverter-defibrillator, a related device that can deliver a high-energy shock to stop dangerous fast rhythms. Pacing pulses are tiny and imperceptible to almost everyone.
“It fixes my heart.” A pacemaker manages an electrical fault. It does not repair damaged muscle, clear arteries or control blood pressure. Those still need their own care.
“I can’t use a microwave or go through airport security.” Both are fine, as the earlier section explains. The real restrictions concern strong magnets and leaning over powerful motors.
“When the battery dies, they redo the whole thing.” Generator replacement is usually a shorter procedure through the old incision that swaps the box and leaves the leads in place, as Mayo Clinic and the NHS describe. Leads are replaced only when they have failed.
“You have to be put to sleep.” Local anesthetic with sedation is the default; general anesthesia is the exception.
“Having a pacemaker means I’m near the end.” The device treats a specific electrical problem. What happens afterwards depends on the underlying heart condition and general health, not on the presence of the device, and the treating team is the right source for what that means in your case.
Questions to ask your care team before the implant
Pre-assessment appointments are short, and the useful questions are the ones written down beforehand. These are worth taking with you.
- Which type of system are you recommending for me, and why that one rather than the alternatives?
- How many leads will be placed, where, and will any sit in the conduction system rather than the muscle?
- Will I be sedated, and what should I tell you now about past reactions to anesthesia or trouble lying flat?
- What is the plan for my anticoagulant or antiplatelet medicine around the procedure, and who makes that call?
- How dependent on pacing do you expect me to be, and what would happen if the device stopped working?
- Is the device MRI-conditional, and how would a future scan be arranged?
- What restrictions on arm movement, lifting and driving apply to me, and for how long?
- Will I have remote monitoring, and how will I hear about anything it detects?
- Which symptoms should prompt a call to the clinic, and which a call to emergency services?
- What is the fallback if a lead cannot be placed where intended on the day?
Bring someone with you if you can. Sedation makes it hard to remember answers, and a second pair of ears on discharge day is worth more than any leaflet. Ask, too, for the name of the arrhythmia nurse or device clinic and a direct number. Over the years that contact will matter more than the name of the person who performed the implant.
One last question rarely asked but always worth it: what does your team consider a good result for someone in my situation? The answer tells you how they will judge the follow-up, and how you should too.
When to call your doctor
Most recoveries are uneventful, but a small number of problems announce themselves early, and they are far easier to treat when caught in hours rather than days. Keep the clinic’s number by the phone and use it without apology.
Call your doctor or device clinic the same day if you notice:
- Redness spreading from the incision, warmth over the pocket, oozing, or a wound edge that opens.
- Fever or chills in the weeks after the implant, even without an obvious wound problem.
- Swelling over the pocket that is growing, tense or increasingly painful.
- Swelling, heaviness or discoloration of the arm or hand on the device side, which can signal a vein clot.
- Persistent hiccups or rhythmic twitching of the chest or abdominal wall in time with your pulse.
- A return of the symptoms that led to the pacemaker: dizziness, near-fainting, unusual fatigue, or a pulse that feels slower than the lower rate you were told the device is set to.
- The device outline becoming more prominent, or the skin over it thinning or changing color.
Call emergency services rather than the clinic for sudden chest pain, severe or worsening shortness of breath, coughing up blood, fainting or collapse, or a fast, pounding heartbeat that does not settle. Chest pain and breathlessness in the first days can indicate a collapsed lung or fluid around the heart, both of which Mayo Clinic and the NIH StatPearls review list among recognized early complications, and both of which need same-day imaging.
None of these signs means something has definitely gone wrong. They mean the treating team should look. Trust that instinct over any reluctance to bother anyone.
Frequently asked questions
What is the life expectancy after having a pacemaker put in?
It depends on the heart condition that led to the pacemaker and on your overall health, not on the device itself. A pacemaker treats slow rhythms and the fainting and fatigue they cause; it does not repair heart muscle or arteries. Someone whose only problem is an electrical fault has a different outlook from someone with heart failure, and your cardiologist is the right person to discuss what applies to you.
Are you awake when a permanent pacemaker is implanted?
Usually yes, but drowsy. Local anesthetic numbs the skin below the collarbone and a sedative given through a drip keeps you relaxed, so most people remember little. You can speak to the team and report discomfort throughout. General anesthesia is reserved for children, people who cannot lie still, or complex cases, and the choice is made with you at the pre-assessment visit.
How long does the pacemaker implantation procedure take?
The NHS describes the procedure as typically taking about an hour, with three-lead biventricular systems running longer. Preparation, a chest X-ray and a device check afterwards mean planning for most of a day in the hospital. Many people go home the same evening or the next morning, though anyone living alone or with other health conditions may be kept overnight.
Is a pacemaker considered major surgery?
It is minimally invasive rather than major in the open-heart sense. There is no chest opening or heart-lung machine, and MedlinePlus describes it as a procedure done through a small incision. It is still real surgery with a permanent implant, small but genuine risks and lifelong follow-up. Surgical placement of leads on the outside of the heart, needed in some children and people with blocked veins, is a larger operation.
How long do pacemaker batteries last, and what does replacement involve?
Mayo Clinic puts typical battery life at 5 to 15 years, depending on how often the device paces and the settings used. Routine checks track remaining charge months in advance, so replacement is planned rather than urgent. The replacement swaps the generator through the original incision under local anesthetic; the existing leads are tested and, if healthy, simply reconnected to the new unit.
Can I have an MRI scan with a pacemaker?
Often yes, with conditions. Mayo Clinic notes that many current systems are MRI-conditional, meaning scans can be done when the device is programmed to a safe mode and specific scanner settings are used. Older systems or abandoned leads may still rule it out. Always tell the radiology team you have a pacemaker so they can check your device card and coordinate with cardiology.
Will I feel my pacemaker working?
Almost never. Pacing pulses are tiny and imperceptible to nearly everyone; the device that delivers noticeable shocks is an implantable defibrillator, not a pacemaker. Some people notice a fluttering during testing or a stronger pulse if the pacing rate rises with exercise. A rhythmic twitch in the chest or persistent hiccups is unusual and should be reported, as it can mean a lead is stimulating nearby muscle.
Can I use a cell phone with a pacemaker?
Yes. The NHS advises holding the phone to the ear opposite the device and keeping it at least 15 cm (about 6 inches) away, which means not carrying it in a shirt pocket over the pacemaker. The same distance applies to magnetic phone cases, some headphones and smartwatch bands. Ordinary calls, texting and using apps at arm’s length pose no problem.
What is a leadless pacemaker and who is it for?
A leadless pacemaker is a capsule-sized device delivered through a vein in the groin and anchored directly inside the right ventricle, with no wires and no chest pocket. It is considered for selected people who need single-chamber ventricular pacing, particularly those with blocked upper veins or a higher infection risk. It is not suitable for everyone who needs atrial pacing, and your team will explain whether it fits your rhythm problem.
How soon can I drive and go back to work after a pacemaker?
The NHS advises against driving a car for at least a week under UK rules, and rules differ by country and license type, so ask what applies to you. Desk work is often possible within days once the sedation has worn off. Jobs involving heavy lifting or arm work above the shoulder usually wait until the four-to-six-week point the NHS gives for avoiding strenuous activity, after the team confirms the leads are stable.
References
- NHS: Pacemaker implantation
- MedlinePlus: Heart pacemaker
- NIH StatPearls: Pacemaker Insertion
- Cleveland Clinic: Permanent Pacemaker
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Cardiothoracic Surgery in Older Adults: How Age and Other Conditions Are Weighed
Age alone rarely decides whether an older adult can have cardiothoracic surgery. Surgical teams weigh frailty, kidney and lung function, diabetes, memory, mobility and…

Why Does Congenital Heart Disease Need Lifelong Cardiology Follow-Up After Repair?
Repairing a congenital heart defect changes the heart's anatomy, but it rarely makes the heart identical to one that formed normally. Over decades, patches…

How Heart Bypass Surgery Reroutes Blood Around Blocked Arteries, Step by Step
Heart bypass surgery, also called coronary artery bypass grafting (CABG), treats blocked coronary arteries by sewing a healthy blood vessel taken from the chest…

Heart Monitoring During Cancer Treatment: When Oncology Refers to Cardiovascular Toxicology
Heart monitoring during chemotherapy means checking the heart's pumping strength and stress markers before, during, and after treatments known to affect it. Oncologists typically…

When Cardiac Rehab Ends: Keeping the Exercise, Nutrition and Medication Habits Going
After cardiac rehab ends, most people are encouraged to continue the same pattern they practiced in the program: regular moderate aerobic activity on most…

Blood Sugar Spikes: What They Do to Energy, Hunger and Arteries, and How to Blunt Them
Blood sugar spikes are sharp rises in glucose after eating, usually peaking within an hour and settling within two to three hours in healthy…