

Thyroid Cancer Treatment for Women Planning Pregnancy: How Timing Is Discussed
Key Takeaways
- Only one part of standard thyroid cancer treatment, radioactive iodine, carries a formal pregnancy waiting period: at least 6 months per the NHS and 6 to 12 months per the American Thyroid Association guideline.
- Women treated with surgery alone have no guideline-mandated waiting period; the practical checks are recovery from the operation and a stable thyroid function test.
- Levothyroxine requirements rise by roughly 20 to 30 percent in early pregnancy according to the American Thyroid Association pregnancy guideline, which is why the prescriber wants to hear about a positive test straight away.
- The fetus depends entirely on the mother's thyroid hormone until about mid-pregnancy, so keeping replacement in range in the first trimester is where the monitoring effort is concentrated.
- The 2015 American Thyroid Association review found no increase in infertility, miscarriage or birth defects in pregnancies conceived after the recommended interval following radioactive iodine.
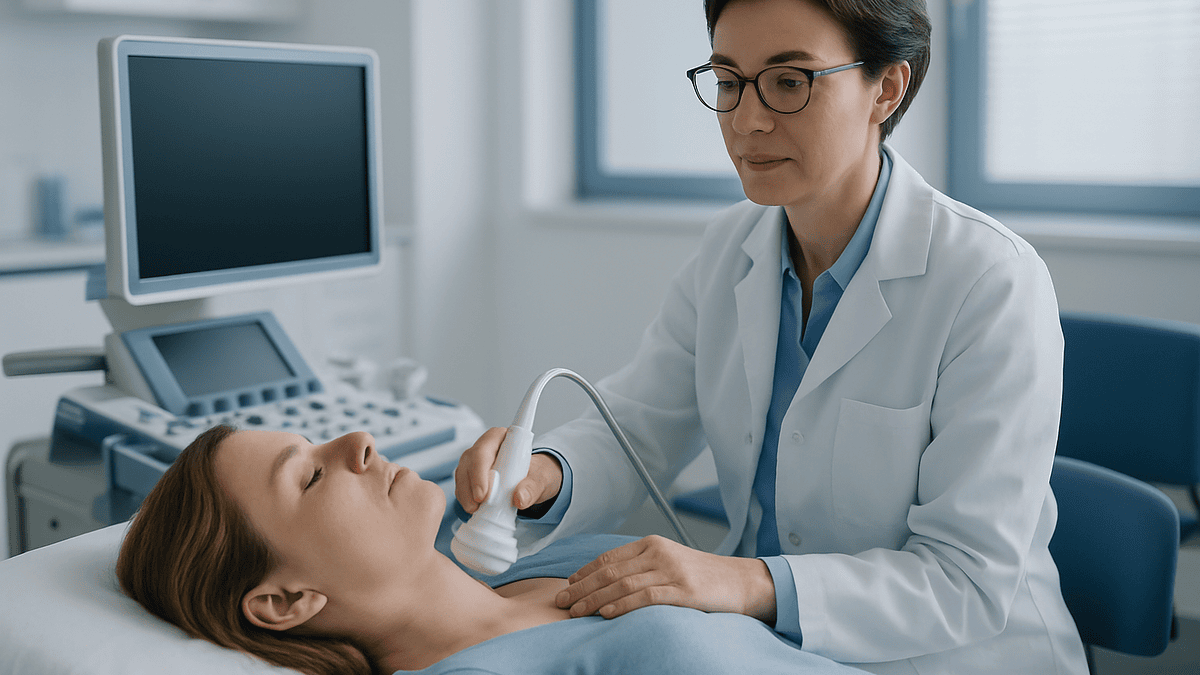
- Differentiated thyroid cancer diagnosed during pregnancy can usually be monitored by ultrasound with surgery deferred until after delivery, or performed in the second trimester if the nodule grows or spreads.
Women who have had thyroid cancer treatment can usually plan a pregnancy once the care team confirms two things: enough time has passed since any radioactive iodine (guidelines advise waiting at least 6 months, and often up to 12) and thyroid hormone levels are stable on replacement. Surgery alone rarely requires a long delay. The timing decision always rests with the treating team, based on the individual case.
She had already picked a name. Not out loud, not to anyone, but the diagnosis arrived three weeks after she and her partner had quietly decided to stop preventing a pregnancy. Now the conversation in the consulting room was about surgery dates, scans and whether she would need radioactive iodine, and the question she most wanted to ask felt almost embarrassing to say: when can we try?
It is one of the most common questions in a thyroid clinic, and one of the least embarrassing. Thyroid cancer is diagnosed more often in women than men, and many of those women are in their twenties, thirties or forties. Thyroid cancer treatment pregnancy planning is therefore not a niche topic; it is part of standard care, with guideline-level answers that are more reassuring than most people expect.
This explainer walks through how the timing is actually discussed: what each treatment step involves, which steps set a waiting period and which do not, and what the evidence says about fertility and future pregnancies.
How thyroid cancer treatment pregnancy planning is usually discussed
The first thing worth knowing is that the timing conversation is not a single verdict delivered at the end of treatment. It is a thread that runs through every appointment, and it usually starts before surgery. Endocrinologists and surgeons expect to be asked, and the guidelines they follow have a specific section on it.
The 2015 American Thyroid Association guideline on differentiated thyroid cancer (the umbrella term for papillary and follicular types, which together make up the large majority of cases) sets out the main timing rule: pregnancy should be deferred for 6 to 12 months after radioactive iodine treatment. The NHS gives the same advice in plainer terms, asking women to avoid pregnancy for at least 6 months after this treatment. Beyond that single rule, most of the discussion is about stability rather than a countdown.
What does stability mean in practice? Three things, broadly. The thyroid hormone replacement has settled at a level the team is happy with. Any follow-up scans or blood tests that would be awkward or impossible during pregnancy have been completed. And the person feels physically ready, which after a neck operation and a period of hormone adjustment can take longer than the calendar suggests.
The medical team will also want to know the plan in reverse. A woman who hopes to conceive within the next year may have her treatment sequence arranged differently from someone who is not planning a pregnancy for several years. That might mean scheduling a diagnostic scan sooner, or being deliberate about when hormone levels are checked. None of this changes the cancer treatment itself; it changes the order and pace of the steps around it.
The rest of this article breaks those steps down, because the waiting period, where one exists, comes from the specific treatment rather than from the diagnosis.
What actually happens in treatment: surgery, radioactive iodine and hormone replacement
Most people picture cancer treatment as chemotherapy. For differentiated thyroid cancer, chemotherapy is rarely part of the picture. According to Mayo Clinic and the NHS, the usual sequence has three possible parts, and not everyone needs all three.

The first is surgery. A lobectomy removes half the thyroid; a total thyroidectomy removes the whole gland. The choice depends on the size of the tumor, whether it has spread to nearby lymph nodes, and other features on imaging. The operation is done under general anesthetic through a small incision at the front of the neck.
The second, for some but not all, is radioactive iodine. Thyroid cells are unusual in that they absorb iodine from the bloodstream to make hormone. Radioactive iodine exploits that: it is taken as a capsule or liquid, travels to any remaining thyroid tissue, and the radiation destroys those cells from the inside while largely sparing the rest of the body. The NHS explains that it is used after total thyroidectomy in people judged to be at higher risk of the cancer returning, and that patients spend a few days in a hospital room with radiation precautions.
The third is thyroid hormone replacement. Once the gland is gone, the body cannot make thyroxine, the hormone that sets the pace of metabolism, heart rate and much else. A daily tablet of levothyroxine, a synthetic copy of thyroxine, takes over that job for life. In many cases the prescriber also aims for a level slightly higher than the body would naturally produce, to keep thyroid-stimulating hormone (TSH, the pituitary signal that tells thyroid cells to grow) low. Mayo Clinic describes this as reducing the drive on any leftover cancer cells.
Of these three, only radioactive iodine carries a formal pregnancy waiting period. That single fact answers a large share of the timing question.
Pregnancy after radioactive iodine: why this step sets the calendar
Radioactive iodine works because the body cannot tell radioactive iodine from ordinary iodine. That same property is why it must never be given during pregnancy: the developing thyroid of a fetus would absorb it too. Every guideline, including the NHS and the American Thyroid Association, requires a negative pregnancy test immediately before treatment.
The waiting period afterwards has a different logic. By the time a woman leaves hospital, most of the radiation has already been excreted in urine and sweat or has decayed; the physical half-life of the isotope used is about eight days. The 6 to 12 month recommendation in the 2015 American Thyroid Association guideline rests on two other concerns. One is that the ovaries receive a small radiation dose, and some women have temporary changes to their periods in the months afterwards; allowing those cycles to settle is sensible. The other, and arguably the more important, is that the months after radioactive iodine are when the care team confirms the treatment did what it was meant to do and settles hormone replacement, and it is far easier to do that outside of pregnancy.
The NHS phrases the advice as avoiding pregnancy for at least 6 months, with a shorter minimum of 4 months for men who wish to father a child. Where a team advises closer to 12 months, it is usually because a follow-up scan or a repeat course is possible and they want that window kept clear.
People sometimes ask whether reliable contraception is really needed during those months. It is. The point of the interval is precisely that a pregnancy should not begin before the team has finished the checks that only make sense before conception.
The evidence on what happens after the waiting period is discussed later in this article, and it is reassuring.
Who is usually cleared to try sooner, and who is usually asked to wait
Timing is individual, but a few patterns hold across most clinics and are worth setting out in neutral terms.

Women whose treatment was surgery alone, without radioactive iodine, are generally in the shortest waiting category. The NHS notes that a lobectomy often leaves enough thyroid tissue that no hormone tablets are needed, and Mayo Clinic describes low-risk cases where the remaining half of the gland does the whole job. In that setting the practical constraints are wound healing, a return to normal energy, and a blood test confirming thyroid function is stable. There is no guideline-mandated interval.
Women who had a total thyroidectomy without radioactive iodine sit in a similar place, with one addition: the levothyroxine level needs to be steady before conception, for reasons covered in the next two sections. Getting there typically takes a few dose adjustments spaced weeks apart, so the team may suggest confirming a stable result before trying.
Women who had radioactive iodine are the group asked to wait, for the 6 to 12 months already described. Within that group, someone with a single low-activity course and a clean follow-up may be given the shorter end; someone whose follow-up is not yet complete, or who may need further treatment, is more likely to hear the longer figure.
A smaller number of women are on active surveillance rather than treatment. Mayo Clinic describes this option for very small papillary cancers that show no sign of spread: regular ultrasound instead of immediate surgery. Pregnancy is not automatically a reason to leave surveillance, but it is a reason to discuss it, because monitoring continues through pregnancy and the team will want a plan if the nodule changes.
Medullary and anaplastic thyroid cancers are rarer, behave differently and are treated on separate pathways; timing questions there are always case-by-case with the specialist team.
Thyroidectomy and pregnancy: what changes once the gland is gone
A woman without a thyroid can carry a healthy pregnancy. That statement is worth making plainly, because a surprising number of people assume otherwise. What changes is that the hormone supply now comes from a tablet rather than a gland, and pregnancy places new demands on that supply.
In a pregnancy with an intact thyroid, the gland quietly increases its output. Pregnancy hormones raise the amount of a carrier protein in the blood that binds thyroxine, so more total hormone is needed to keep the free, active portion steady. Early on, the pregnancy hormone hCG also mildly stimulates the thyroid directly. A healthy gland absorbs these shifts without anyone noticing.
A tablet cannot adjust itself. The NIH’s National Institute of Diabetes and Digestive and Kidney Diseases explains that women taking levothyroxine usually need more of it during pregnancy, and the 2017 American Thyroid Association guideline on thyroid disease in pregnancy summarizes studies showing that the requirement rises by roughly 20 to 30 percent, often within the first weeks. This is why prescribers ask to be told the moment a pregnancy test is positive: the adjustment and the blood test to check it are handled by the clinician, and the earlier the better.
Why does it matter so much in the first trimester? The fetus does not make its own thyroid hormone until roughly the middle of pregnancy. Until then it relies entirely on the mother’s supply, and thyroid hormone is essential for early brain development. Both the NIH and the American Thyroid Association guideline note that untreated or under-treated hypothyroidism in pregnancy is associated with complications, which is exactly why the monitoring is built in.
The other post-thyroidectomy consideration is calcium. The four tiny parathyroid glands sit behind the thyroid and regulate blood calcium; surgery can bruise or, less commonly, permanently affect them. Anyone who needed calcium or vitamin D supplements after surgery should raise that with the team when planning, since calcium needs also shift in pregnancy.
Levothyroxine before pregnancy: why levels are checked, then checked again
The number the team watches most closely is TSH. When thyroid hormone in the blood is low, the pituitary gland raises TSH to ask for more; when hormone is high, TSH falls. It is a sensitive gauge, and it is why a single blood test can tell a prescriber whether the replacement is roughly right.
Before conception, the goal is a TSH that is stable and in the range the cancer team has chosen. That range may be lower than the usual population range, because of the TSH suppression strategy described earlier. The 2017 American Thyroid Association pregnancy guideline addresses this directly: a woman treated for thyroid cancer should generally continue with the same TSH goal in pregnancy that her cancer team had set beforehand, adjusted by the prescriber as pregnancy progresses. In other words, the cancer plan and the pregnancy plan are meant to be the same plan.
Once pregnant, the same guideline recommends checking thyroid function about every 4 weeks through the first half of pregnancy, then at least once around mid-pregnancy and again later. That schedule catches the rising requirement early. It is worth saying that levothyroxine has been used in pregnancy for decades and is the standard treatment for hypothyroidism in pregnant women; it replaces a hormone the body would normally make, and the NIH describes it as safe in pregnancy when properly monitored.
A few practical habits matter more than most people realize. Levothyroxine is absorbed in the gut, and iron, calcium and some antacids interfere with that absorption if taken at the same time. Prenatal vitamins contain iron and calcium. The NIH advises separating the two by several hours, and the prescriber or pharmacist can suggest a routine. Nausea in early pregnancy can also make a daily tablet hard to keep down; if that happens, it is a reason to call, not to skip.
None of this requires the patient to interpret numbers herself. It requires a blood test, a phone call and a prescriber who knows a pregnancy is planned.
Thyroid cancer treatment pregnancy planning at a glance: a timing summary
The details above can be condensed into a single view. The table below is a summary of what mainstream guidance says about each treatment step, not a schedule for any individual; the treating team sets the actual timing.
| Treatment step | Typical pregnancy timing consideration | Source of the guidance |
|---|---|---|
| Lobectomy (half the thyroid removed) | No guideline-mandated interval; recovery from surgery and a stable thyroid function test are the practical checks | NHS; Mayo Clinic |
| Total thyroidectomy without radioactive iodine | No mandated interval; hormone replacement should be stable before conception, then adjusted by the prescriber in early pregnancy | NIH (NIDDK); American Thyroid Association 2017 |
| Radioactive iodine | Avoid pregnancy for at least 6 months; guidelines advise 6 to 12 months; negative pregnancy test required before treatment | NHS; American Thyroid Association 2015 |
| Breastfeeding before radioactive iodine | Stop breastfeeding several weeks to a few months beforehand, as breast tissue concentrates iodine | American Thyroid Association 2015 |
| Active surveillance (no immediate treatment) | Pregnancy is possible; ultrasound monitoring continues and a plan is agreed in case of change | Mayo Clinic; American Thyroid Association 2017 |
| During pregnancy, on levothyroxine | Thyroid function checked about every 4 weeks in the first half of pregnancy, with dose changes made by the prescriber | American Thyroid Association 2017 |
Two things stand out. First, only one row carries a fixed waiting period, and it applies to a specific treatment rather than to the diagnosis. Second, the steps that do not involve waiting still involve preparation, mostly in the form of blood tests. A woman who leaves the clinic with a clear answer to “what does stable look like for me, and when will we check it” has most of what she needs.
What the weeks and months after treatment usually look like
Timelines are easier to accept when the reason behind each stretch is clear. Here is the typical shape, drawn from NHS and Mayo Clinic descriptions, with the caveat that individual plans vary.
After surgery, the first two to three weeks are about the neck: a healing incision, some stiffness, a voice that may be hoarse for a while if the nerve to the voice box was irritated. Calcium may be checked in the first days. Levothyroxine, if needed, usually starts straight away. A first thyroid function test follows after roughly six weeks, because that is about how long it takes for a change in tablet strength to fully show in the blood.
If radioactive iodine is planned, it usually comes a few weeks to a few months after surgery. The NHS describes a low-iodine diet for about two weeks beforehand, so that thyroid cells are hungry for the treatment iodine, and preparation that either pauses levothyroxine or uses an injected form of TSH to raise the signal. Treatment itself involves a short hospital stay, typically a few days, followed by simple precautions at home for a period the team specifies.
The months after radioactive iodine are the confirmation phase. A whole-body scan a few days after treatment shows where the iodine went. Blood tests measure thyroglobulin, a protein made only by thyroid cells, which after total removal should fall to very low levels; it becomes the main long-term marker. A neck ultrasound and a further thyroglobulin check often follow at around six to twelve months. This is the window the pregnancy waiting period protects.
By the end of the first year, most women with low-risk disease have moved to routine follow-up: periodic blood tests and ultrasound, and an established replacement routine. From a pregnancy-planning point of view, that is the point at which the team can usually say, with the follow-up in hand, that there is no treatment-related reason to wait longer.
Does radioactive iodine affect fertility or a future baby? What the evidence shows
This is the question underneath all the others, and the honest answer is more reassuring than the anxiety around it suggests, with a couple of genuine caveats.
On fertility, the 2015 American Thyroid Association guideline reviewed the available studies and concluded that radioactive iodine does not appear to reduce a woman’s ability to conceive later. A minority of women have temporary changes to their periods, including missed cycles, in the months after treatment; these generally resolve. The same review noted a possible association with a slightly earlier average age of menopause after higher cumulative activity, which is one reason teams avoid unnecessary repeat courses and a reason a woman in her late thirties who wants children may have that factored into her treatment discussion.
On the baby, the guideline found no evidence of an increase in birth defects, miscarriage or other adverse outcomes in pregnancies conceived after the recommended waiting period. The waiting period exists to allow the ovaries to recover from a small radiation exposure and to complete follow-up, not because a later pregnancy carries a known risk.
The evidence has limits worth naming. Most of the studies are observational, meaning they compare outcomes in women who did and did not have treatment rather than randomly assigning it, and numbers for higher-activity treatment are smaller. Guideline writers grade this evidence as moderate rather than strong. Saying so is not a hedge; it is what the evidence actually shows.
For women who have not yet had radioactive iodine and are concerned about future fertility, there is one more point to raise early: whether the treatment is needed at all. The 2015 guideline moved firmly away from routine radioactive iodine for low-risk disease. A team recommending it should be able to explain the specific risk features that make it worthwhile in a particular case.
Thyroid cancer during pregnancy: when the diagnosis comes after conception
Sometimes the order is reversed. A lump is noticed at a routine antenatal check, or an ultrasound for something else picks up a nodule, and the diagnosis arrives with a due date already on the calendar. This is unsettling, but it is a situation the guidelines specifically address.
The 2017 American Thyroid Association guideline on thyroid disease in pregnancy gives clear direction for differentiated thyroid cancer found during pregnancy. In most cases, surgery can safely wait until after delivery. The cancer is typically slow-growing, and the guideline’s review found that pregnancy itself does not appear to worsen the outlook for women with this type. The preferred approach is ultrasound monitoring through the pregnancy.
There are exceptions. If the nodule grows substantially over the pregnancy, or if there are signs of spread to lymph nodes, the guideline states that surgery can be performed in the second trimester, when the risks of anesthesia to the pregnancy are lowest and the uterus is not yet large enough to complicate positioning. Decisions here involve the surgeon, the endocrinologist and the obstetric team together.
Radioactive iodine is never given during pregnancy, and diagnostic scans that use radioactive iodine are also avoided. Ultrasound, which uses sound waves, is the imaging tool of choice. A biopsy of the nodule with a fine needle can be done safely in pregnancy if needed to confirm the diagnosis.
Some women in this situation are started on levothyroxine even before surgery, to keep TSH in a lower range and reduce the growth signal to the nodule. Whether that is appropriate is a prescriber’s decision, based on the individual picture.
What most women in this position want to hear is that a wait until after delivery is a medically reasoned choice, not a compromise forced by the pregnancy. For the common types of thyroid cancer, that is what the guideline evidence supports.
Breastfeeding, surveillance scans and the other timing questions that come up
Once the main sequence is understood, a cluster of smaller timing questions tends to follow. They deserve straight answers.
Breastfeeding and radioactive iodine do not mix, and not only for the obvious reason. Breast tissue actively concentrates iodine during lactation, so a woman who has recently been breastfeeding would deliver radiation to her own breast tissue as well as risk passing it to the infant. The 2015 American Thyroid Association guideline advises stopping breastfeeding for a period of several weeks to a few months before treatment, so that the breast tissue returns to its non-lactating state; the exact interval is set by the treating team. Breastfeeding a future baby after a past course of radioactive iodine is not affected.
Follow-up scans are the other frequent question. Neck ultrasound and thyroglobulin blood tests are entirely compatible with pregnancy and continue on schedule. A diagnostic whole-body scan using a tracer amount of radioactive iodine is not, and a team that would normally do one at a particular follow-up point may bring it forward, delay it until after delivery, or rely on ultrasound and blood tests instead. This is one of the concrete reasons to tell the team early that a pregnancy is planned.
Thyroglobulin levels themselves can be slightly harder to interpret in pregnancy, because the blood volume expands and, in women with any remaining normal thyroid tissue, the pregnancy hormone hCG can stimulate it. Endocrinologists are used to reading results in that context.
Lastly, some women ask about the interval between pregnancies, or about a second pregnancy after treatment. Nothing in the guidelines imposes a thyroid-specific interval once the initial post-treatment period has passed and replacement is stable. The usual obstetric advice on spacing applies, and the levothyroxine adjustment cycle simply repeats with each pregnancy.
What people often get wrong about thyroid cancer and pregnancy
Myths gather quickly around any topic that combines cancer and fertility. Several of them are worth correcting with evidence rather than reassurance.
The first is that a thyroid cancer diagnosis means the end of pregnancy plans. It does not. The NHS, Mayo Clinic and the American Thyroid Association all describe pregnancy after treatment as routine, with one specific waiting period after radioactive iodine and no waiting period at all for many women treated with surgery alone.
The second is that levothyroxine is a drug that must be stopped when trying to conceive. The opposite is true. Levothyroxine replaces a hormone the body can no longer make, and the NIH is explicit that it is needed throughout pregnancy, usually in larger amounts. Stopping it would deprive both mother and fetus of the hormone. Any change is the prescriber’s decision.
The third is that radioactive iodine leaves a woman permanently radioactive or damages her eggs for good. The isotope decays with a physical half-life of about eight days, and the 2015 American Thyroid Association guideline found no lasting effect on fertility or on outcomes of later pregnancies. Temporary menstrual changes in the months afterwards are real, but they are temporary.
The fourth is that pregnancy makes thyroid cancer grow or come back. The 2017 pregnancy guideline reviewed this question and did not find that pregnancy worsens the course of differentiated thyroid cancer, provided replacement therapy is kept in range.
The fifth, more subtle, is that a woman needs to reach a particular “recovered” feeling before she is allowed to plan. Readiness matters, and nobody should feel hurried. But the medical criteria are concrete: time since radioactive iodine, stable hormone levels, completed follow-up. Those are things a blood test and a calendar can confirm, and a team can say clearly when they are met.
Questions to ask your care team about timing and pregnancy
Consultations are short and questions evaporate under pressure. Writing them down beforehand helps, and so does bringing a partner or friend to take notes. These are the questions that most directly shape the timing discussion.
- Based on my results, is radioactive iodine likely to be part of my treatment, and what features of my case make that recommendation?
- If I do have radioactive iodine, what waiting period will you advise for me, and what follow-up tests need to be completed within it?
- Do I need thyroid hormone replacement after my surgery, and what TSH range are you aiming for in my case?
- How many blood tests, roughly, do you expect before my replacement is stable enough to plan a pregnancy?
- When I have a positive pregnancy test, whom should I contact first, and how quickly will my replacement be reviewed?
- Will any of my follow-up scans need to be moved because I am planning a pregnancy?
- Was my calcium affected by surgery, and does that change anything for pregnancy?
- If I am currently breastfeeding, how does that affect the timing of any further treatment?
- Would my treatment plan look different if I were not planning a pregnancy soon? If so, what are the trade-offs?
- Who will coordinate between my endocrinologist and my obstetric team once I am pregnant?
One question deserves emphasis: the last but one. Guideline-based treatment for low-risk thyroid cancer has become less intensive over the past decade, and the 2015 American Thyroid Association guideline explicitly supports less surgery and less radioactive iodine for many small tumors. A woman who wants to conceive soon has a legitimate interest in understanding whether a proposed step is essential or optional, and in hearing the reasoning either way. Asking is not second-guessing the team; it is the kind of shared decision-making the guidelines describe.
When to call your doctor
Most of the journey described here is measured in scheduled appointments and blood tests. A few situations should not wait for the next one.
Call promptly if you have a positive pregnancy test and you take levothyroxine. This is not an emergency, but it is time-sensitive: the NIH and the American Thyroid Association guideline both stress that replacement usually needs adjusting early in pregnancy, and the prescriber will want a blood test arranged.
Seek urgent advice after thyroid surgery if you notice tingling around the mouth or in the fingertips, muscle cramps or spasms, which can signal low calcium; or if the neck wound becomes increasingly swollen, red, hot or leaks fluid; or if you develop a fever. Difficulty breathing or a rapidly enlarging neck swelling in the days after surgery needs emergency care.
Contact the team if, at any stage, you develop a new lump in the neck, persistent hoarseness lasting more than a few weeks, difficulty swallowing, or an unexplained persistent cough. These are the kinds of changes follow-up is designed to catch early, and they should be checked rather than watched.
During pregnancy, call if you have persistent vomiting that stops you keeping your levothyroxine down, a racing or pounding heartbeat that does not settle, marked heat intolerance or tremor, or, at the other end, profound fatigue, feeling cold and constipation out of proportion to normal pregnancy symptoms. These can reflect a replacement level that has drifted and is straightforward to check.
After radioactive iodine, contact the team if you become pregnant within the advised waiting period. Do not make any decision alone; the team will assess the situation, and the physical radiation exposure is usually far lower than people fear by that point, but the discussion needs to happen with them.
Every one of these calls should end with a plan from the treating team. That is where the decisions belong.
Frequently asked questions
How long after thyroid cancer treatment can I try to get pregnant?
It depends on which treatment you had. After radioactive iodine, the NHS advises waiting at least 6 months and the American Thyroid Association guideline gives 6 to 12 months. After surgery alone, there is no fixed interval; the team looks for recovery and a stable thyroid function result. Your treating team confirms the timing for your individual case.
Is pregnancy after radioactive iodine safe for the baby?
The evidence reviewed in the 2015 American Thyroid Association guideline found no increase in birth defects, miscarriage or other adverse outcomes in pregnancies conceived after the recommended waiting period. The interval exists to let the ovaries recover from a small radiation exposure and to finish follow-up tests, not because later pregnancy carries a known risk.
Can I take levothyroxine before pregnancy and while pregnant?
Yes. Levothyroxine replaces the thyroxine your body can no longer make and is the standard treatment for hypothyroidism in pregnancy. The NIH notes the amount needed usually rises during pregnancy, so your prescriber will check blood tests and adjust it. Never stop or change it yourself; contact your prescriber as soon as you know you are pregnant.
Does thyroidectomy affect fertility or my ability to carry a pregnancy?
Removing the thyroid does not, in itself, affect fertility. Once hormone replacement is stable, a woman without a thyroid can carry a healthy pregnancy. The key difference is that a tablet cannot increase its own output the way a gland does, so thyroid levels are checked about every 4 weeks in the first half of pregnancy and adjusted by the prescriber.
What happens if thyroid cancer is found during pregnancy?
For the common differentiated types, the American Thyroid Association guideline says surgery can usually wait until after delivery, with ultrasound monitoring during pregnancy. If the nodule grows substantially or spreads to lymph nodes, surgery can be done in the second trimester. Radioactive iodine is never used in pregnancy. The surgical, endocrine and obstetric teams decide together.
Will I need to stop breastfeeding before radioactive iodine?
Yes. Lactating breast tissue concentrates iodine, so treatment would expose the breast and could pass radiation to the infant. The American Thyroid Association guideline advises stopping breastfeeding several weeks to a few months beforehand, with the exact interval set by your team. A past course of radioactive iodine does not prevent breastfeeding a future baby.
Can I have my follow-up scans while pregnant?
Neck ultrasound and thyroglobulin blood tests are safe and continue as normal. Scans using a tracer amount of radioactive iodine are avoided in pregnancy, so the team may bring one forward, delay it until after delivery, or rely on ultrasound instead. Telling the team early that you are planning a pregnancy lets them arrange this.
Does pregnancy make thyroid cancer come back?
The 2017 American Thyroid Association pregnancy guideline reviewed this and did not find that pregnancy worsens the course of differentiated thyroid cancer when hormone replacement is kept in range. Routine follow-up continues during and after pregnancy so that any change is picked up early, in the same way it would be outside pregnancy.
Why do I need to keep my TSH low if I am planning a baby?
A lower TSH reduces the growth signal to any remaining thyroid cells, which is part of the cancer plan. The American Thyroid Association pregnancy guideline says the TSH goal set by your cancer team should generally be kept during pregnancy, with the prescriber adjusting replacement as needs rise. The cancer plan and the pregnancy plan are meant to be the same plan.
Will radioactive iodine bring on early menopause?
The 2015 American Thyroid Association review noted temporary menstrual changes in a minority of women in the months after treatment, which generally resolve, and a possible slightly earlier average age of menopause after higher cumulative activity. This is one reason teams avoid unnecessary repeat courses and a fair point to raise if you are in your late thirties and planning children.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Nutrition During Liver Cancer Treatment: How Dietitians Support a Working Liver
Nutrition during liver cancer treatment focuses on protecting muscle, keeping calories steady and easing side effects such as nausea, taste changes and fluid buildup,…

What Conditioning Before a Stem Cell Transplant Does and How Those Days Are Planned
Conditioning before a stem cell transplant is the course of chemotherapy, sometimes combined with radiation or antibody treatment, given over roughly a week before…

Why Leukemia and Lymphoma Plans Are Built by Hematology and Oncology Together
Leukemia and lymphoma begin in blood-forming and immune cells, so the specialists who read blood counts and bone marrow (hematology) and those who plan…

Mouth Sores and Taste Changes During Chemotherapy: Daily Care That Makes Eating Easier
Mouth sores during chemotherapy (oral mucositis) happen because chemotherapy damages the fast-dividing cells lining the mouth. They usually appear 5 to 10 days after…

After Ureteral Tumor Surgery: Stents, Catheters and the Return to Normal Activity
After surgery for a ureteral tumor, a temporary ureteral stent (a soft tube keeping the ureter open) and a bladder catheter are common. The…

Who Is Assessed for a Stem Cell Transplant in Multiple Myeloma, and When Does It Happen?
In multiple myeloma, a stem cell transplant is usually considered for people whose overall fitness, organ function and other health conditions suggest they can…