

What to Expect After Ovarian Cyst Removal: Pathology Results, Follow-Up and Cycle Changes

Key Takeaways
- Ovarian cyst surgery results arrive in three stages: the surgeon's operative note the same day, the pathology report days to weeks later, and the follow-up review that turns both into a plan.
- The pathology report names the cyst type from the cells lining its wall, and size on the report does not indicate seriousness; most cysts removed are confirmed benign.
- After laparoscopic cyst removal the NHS notes many people resume normal activities within about five days, while recovery from larger or open operations can take up to 12 weeks.
- A late, early or heavier first period after surgery is common because the handled ovary can delay ovulation, and cycles usually settle over the following two or three cycles.
- A removed cyst does not regrow, but functional cysts can form in any ovulatory cycle and usually resolve within two to three months, while endometriomas are the type most likely to recur.
- Removing an endometrioma can reduce ovarian reserve on that side, so people planning a pregnancy should raise fertility at follow-up even if the report is benign.
After ovarian cyst removal, the cyst wall is sent to a laboratory, and the pathology report usually confirms a benign type such as a functional, dermoid or endometriotic cyst. Most people recover from keyhole surgery over days to a few weeks, periods may be late or irregular for a cycle or two, and follow-up focuses on healing, the report and whether a scan is needed.
The waiting is the strange part. The surgery itself is over in an afternoon, the small dressings come off within days, and then there is a quiet gap: a lab somewhere has a piece of you under a microscope, and nobody has said much beyond “it looked fine.” People in this gap tend to search at two in the morning. They want to know what ovarian cyst surgery results actually consist of, who reads them, and whether a late period three weeks later is part of the plan.
This explainer walks through that gap in order. It covers what the pathologist is looking for, why the words on the report matter more than the size of the cyst, what the first weeks usually feel like, and how the remaining ovary tends to behave once it has been handled.
One honest note before we start: the pattern is reassuring for most people, but your own report, scan and surgeon’s notes always outrank anything written here.
What ovarian cyst surgery results actually include
“Results” sounds like a single document. In practice it is three separate things arriving at different times, and understanding that order removes a lot of the anxiety.
The first result is the operative note. Your surgeon writes it the same day, and it records what was seen: the size of the cyst, whether it was intact or had leaked, the state of the other ovary, the tubes and the lining of the pelvis, and whether anything unexpected such as endometriosis was found. Much of what you were told in the recovery room comes from this note.
The second result is the pathology report. The removed tissue is placed in preservative, processed into thin slices and examined under a microscope by a pathologist, a doctor who specializes in diagnosing disease from tissue. This is the document that names the cyst type and states whether the cells are benign. The NHS explains that a sample is routinely tested after removal so the type can be confirmed, which is why even a cyst that “looked simple” still goes to the lab.
The third result is the follow-up assessment. This is your review appointment, sometimes with a scan, where the operative note, the pathology report and how you are healing are pulled together into a plan: discharge from clinic, a repeat ultrasound, or further referral.
Think of it as a relay rather than a verdict. Each stage answers a different question. The operative note answers “what did you find,” the pathology report answers “what is it,” and the follow-up answers “what, if anything, happens next.” Knowing which one you are waiting for makes the waiting easier.
How ovarian cyst removal works, in plain language
An ovarian cyst is a fluid-filled sac that forms on or inside an ovary. The operation to remove one while leaving the ovary in place is called an ovarian cystectomy. Removing the whole ovary, usually with its tube, is an oophorectomy. Which one you had, or will have, shapes everything that follows.
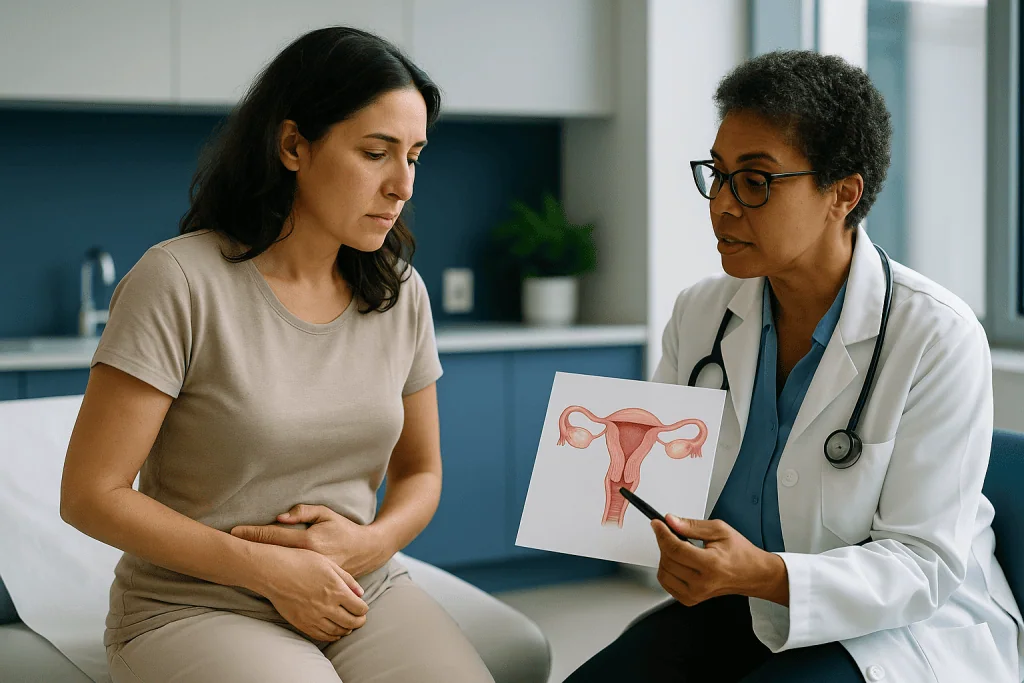
Most cystectomies today are done by laparoscopy, meaning keyhole surgery. The NHS describes the basics: under general anesthetic, a small cut is made near the navel, carbon dioxide gas is used to lift the abdominal wall away from the organs, and a thin camera is passed in. One to three additional small cuts allow instruments through. The surgeon opens the ovary’s surface, peels the cyst wall away from the healthy tissue, and removes it, often inside a bag so the contents do not spill into the pelvis.
Open surgery, through a larger cut across the lower abdomen (a laparotomy), is reserved for situations where keyhole access is unsafe or impractical: a very large cyst, concern about cancer, or dense scarring from previous surgery or endometriosis. Mayo Clinic notes that the choice depends on the size and appearance of the cyst, your symptoms and your age.
Two details matter for your results. First, the cyst wall is what the pathologist needs; fluid alone is rarely enough to name the type, which is why surgeons aim to remove the sac intact. Second, the ovary is a dense little organ roughly the size of an almond, and separating a cyst from it inevitably removes a sliver of surrounding tissue. That sliver is why cycle and hormone questions come up later, and we will return to it.
Who is usually offered surgery, and who is asked to wait
Not every cyst earns an operation, and “wait” is often the correct medical answer rather than a brush-off. The NHS and Mayo Clinic both describe watchful waiting as the first step for many cysts, particularly the functional cysts that come and go with the menstrual cycle.
Surgery tends to be discussed when one or more of the following apply:
- The cyst is large, or growing on repeat ultrasound rather than shrinking.
- It is causing persistent pain, pressure or bloating.
- Its appearance on ultrasound is not simple: solid areas, thick walls or internal partitions.
- Blood tests or imaging raise a question about cancer risk, which rises after menopause.
- It has caused, or looks at risk of, torsion (twisting of the ovary) or rupture.
People commonly asked to wait are those with a small, simple, fluid-only cyst and few symptoms, especially before menopause. Mayo Clinic notes that functional cysts usually disappear on their own within two to three months, so a repeat scan after that interval is standard. Pregnancy changes the calculation again: many cysts found in early pregnancy are watched because surgery carries its own risks, and most resolve.
There is also a middle group. Someone with an endometrioma, a cyst formed by endometriosis tissue, may be offered surgery, hormonal management, or observation depending on symptoms and fertility plans. Here the honest answer is that guidelines accept more than one reasonable path.
What this means for you: if you were operated on, something tipped the balance, and the pathology report will usually tell you what it was. If you are still in the waiting group, the follow-up scan is not a formality; it is the test that decides whether surgery is ever needed.
How long does ovary cyst surgery take?
Shorter than most people imagine, longer than the surgeon’s time in the room. Those are two different clocks and both are worth knowing.

The operating clock covers only the cutting and sewing. The NHS states that a diagnostic laparoscopy, where the camera is used to look rather than remove, usually takes 30 to 60 minutes. Removing a cyst adds the time needed to free it from the ovary, place it in a retrieval bag, check for bleeding and close the small incisions. Large cysts, endometriosis scarring or a second cyst on the other ovary all add minutes. Your surgeon can give you a realistic estimate for your case, and it is a fair question to ask before you go in.
The patient clock is longer. It starts when you arrive, continues through anesthetic checks, the operation, and a recovery-room stay while you wake and your pain is settled. The NHS notes that after laparoscopy you can often go home the same day or the next, and MedlinePlus describes a similar pattern for pelvic laparoscopy, with an overnight stay more likely after open surgery or if there were complications.
Why this matters for results: an operation that ran long is not, by itself, a bad sign. Surgeons take more time when they are being careful, when a cyst is stuck, or when they are deliberately keeping it intact so the pathologist has clean tissue to read. Equally, a quick operation does not mean anything was missed. Ask your team what the time reflected; the operative note will usually say.
Understanding ovarian cyst pathology results: what the report is looking for
A pathology report is written for other doctors, so it reads like a form filled out by someone in a hurry. Three lines on it carry nearly all the meaning.
The first is the specimen description: what was received, its size and what it looked like to the naked eye. Fluid color, wall thickness and the presence of hair, fat or teeth (yes, really, in a dermoid cyst) are recorded here. This is the “gross” examination, and gross in this context simply means visible without a microscope.
The second is the microscopic description. The pathologist describes the cells lining the cyst wall. The lining is the fingerprint: cells that look like the surface of the ovary, cells that look like the lining of the womb, or a mixture of tissue types each point toward a specific cyst family.
The third, and the one to read first, is the diagnosis line. It will name the cyst type and almost always include the word benign, meaning not cancerous. Cleveland Clinic and Johns Hopkins both note that the great majority of ovarian cysts are benign, which is why most reports end in a sentence or two.
Occasionally a report uses the word borderline. A borderline tumor has cells that are abnormal but lack the invasive behavior of cancer. It is not the same as a cancer diagnosis, but it does mean closer follow-up and a specialist discussion, and no article can replace that conversation.
Timing varies from lab to lab, and complex specimens can take longer because extra stains are sometimes needed. Ask at discharge when the report is expected and who will contact you. Chasing a result is not a nuisance; it is good practice.
What the cyst types on a pathology report mean
The table below summarizes the cyst types that appear most often on reports after surgery. It is a map, not a diagnosis; the names on your own report always take precedence.
| Report wording | Plain meaning | Usual pattern after removal |
|---|---|---|
| Follicular or corpus luteum cyst (functional) | Formed by the normal monthly egg cycle | Benign; new ones can form in later cycles |
| Mature cystic teratoma (dermoid) | Contains skin, hair, fat or other tissue types | Benign; can occur on either ovary over time |
| Endometrioma | Cyst formed by endometriosis tissue | Benign; recurrence is possible, so endometriosis is managed as a condition |
| Serous or mucinous cystadenoma | Cyst that grows from the ovary’s surface cells | Benign; follow-up usually based on symptoms and scan |
| Borderline tumor | Abnormal cells without invasive growth | Not cancer; needs specialist follow-up |
Two reading tips. First, size on the report does not track with seriousness. A large functional cyst and a small borderline tumor are very different problems, which is exactly why tissue is examined rather than measured. Second, a diagnosis of endometrioma reclassifies the conversation: the cyst was a symptom of endometriosis, and the NHS notes that cysts linked to endometriosis are among those most likely to return. Follow-up for that group is about the condition, not just the cyst.
If your report lists a term not shown here, that is common; the pathology vocabulary is long. Ask your team to translate the diagnosis line into one sentence and to tell you whether anything on it changes your follow-up.
Ovarian cystectomy recovery time: the first days and weeks
The first evening is mostly about two things: the shoulder-tip ache from the gas used during laparoscopy, which the NHS notes can last a day or two as the body absorbs it, and a general sense of having been through something. Walking around the house, even slowly, helps move the gas along.
Days two to five usually bring the bruised, pulled feeling at the incision sites and tiredness that surprises people. Light spotting from the vagina can occur if instruments were used to position the womb; it typically settles within days. The NHS advises that after minor laparoscopic procedures, many people are back to normal activities within about five days, while recovery from larger operations can take up to 12 weeks. Cyst removal sits between those two ends depending on how much was done.
Weeks two to six are the stretch where people overdo it. Driving, lifting and vigorous exercise are usually reintroduced once you can move freely without pain and are no longer taking medicines that affect alertness; your team’s discharge sheet gives the specifics for your case, and it outranks any general figure. Open surgery through a larger incision means a slower, more cautious version of all of this.
A few patterns are worth normalizing: appetite drifting back over days rather than hours, a bowel movement that takes longer than usual to arrive, and energy that dips in the afternoon for a week or two. None of these are results in the pathology sense, but they are part of what the body reports after a cystectomy, and they tend to improve in a steady, if not perfectly straight, line.
Period after ovarian cyst surgery: what cycle changes are typical
Here is the question people most often feel silly asking and most often need answered. Yes, your cycle may misbehave for a while, and the reasons are mechanical rather than mysterious.
The ovary that was operated on has been handled, cut and often stitched or sealed. It is temporarily inflamed. Because the ovaries drive the hormone rhythm that produces a period, a disturbed ovary can delay ovulation, and a delayed ovulation means a late period. Anesthetic, pain, poor sleep and the stress of surgery all nudge the same system. The result, commonly, is a first period that arrives late or early, is heavier or lighter than usual, or carries more cramping. A second cycle that is still a little off is not unusual. By the third cycle most people are close to their own normal, though this is a typical pattern rather than a guarantee, and anyone with an underlying condition such as endometriosis or polycystic ovary syndrome may see their pre-existing pattern return instead.
If the cyst was a functional one, it may itself have been causing the irregularity, and some people find their cycle settles after removal.
The longer-term question is about ovarian reserve, meaning the supply of eggs remaining. Removing a cyst takes a small amount of ovarian tissue with it, and this is most relevant for endometriomas, whose walls are closely bound to healthy ovary. Guidelines are candid that cystectomy for an endometrioma can reduce reserve on that side. Your remaining ovary, and the ovary that was operated on, usually continue to function, but if fertility is a priority this is a conversation to have before surgery where possible, and at follow-up regardless.
Can ovarian cysts come back, and how quickly?
The honest answer is that a removed cyst does not grow back, but a new cyst can form, and whether it does depends almost entirely on the pathology type.
Functional cysts are the clearest example. They are a by-product of ovulation: each month a follicle swells to release an egg, and sometimes that follicle, or the structure left behind, fills with fluid instead of shrinking. As long as you ovulate, a new functional cyst can appear in any cycle. Mayo Clinic describes these as typically resolving within two to three months without treatment, so a small one found on a follow-up scan is usually watched rather than operated on again.
Dermoid cysts and cystadenomas can occur again, including on the other ovary, but they are not tied to the monthly cycle in the same way, and most people who have one removed do not have another.
Endometriomas are the type the NHS specifically flags as prone to return. The cyst is one expression of endometriosis, a condition in which tissue similar to the womb lining grows outside the womb, and removing the cyst does not remove the condition. For this group the follow-up plan usually involves managing endometriosis itself, sometimes with hormonal treatment whose job is to quiet the cycle that feeds the disease. That decision sits with your gynecologist and depends on symptoms and fertility plans.
How quickly can a cyst reappear? For functional cysts, within a cycle; for others, it is measured in years if it happens at all. A scan showing a small simple cyst months after surgery is therefore not evidence that the operation failed. It is usually evidence that your ovary is doing its job.
Potential side effects of ovarian cyst removal surgery
Every operation has a side-effect list, and ovarian cystectomy’s is short but worth reading properly rather than skimming.
Expected and temporary effects, described by the NHS and MedlinePlus, include pain at the incisions, shoulder-tip pain from the laparoscopic gas, bloating, nausea from the anesthetic, tiredness, light vaginal bleeding and bruising around the cuts. Constipation is common for a few days.
Less common complications include:
- Infection at an incision or inside the pelvis.
- Bleeding, occasionally requiring a return to theatre.
- Injury to nearby structures such as the bowel, bladder or blood vessels, which is rare but is the main reason surgeons sometimes convert a keyhole procedure to open surgery.
- Blood clots in the leg or lung, the risk of which is why early walking is encouraged.
- Reaction to the anesthetic.
- Adhesions, which are bands of scar tissue that can form inside the pelvis after any surgery and occasionally cause pain or fertility difficulty later.
Effects specific to the ovary deserve their own line. Reduced ovarian reserve on the operated side, as discussed above, is most relevant for endometriomas. If an entire ovary was removed and you have only one remaining, you are usually still able to ovulate and conceive, and hormone levels are typically maintained by the remaining ovary. If both ovaries were removed before menopause, menopause begins immediately, and your team will have discussed hormone management in advance.
A fair way to hold this list: the temporary effects affect nearly everyone, the complications affect few, and the ovary-specific effects depend on what was removed. Your consent form will have covered your own version of this, and your follow-up is where you check how it played out.
Follow-up after ovarian cyst surgery: what the appointments and scans are for
Follow-up is often the least explained part of the whole pathway, which is odd because it is where the results are actually used.
The first contact is often a wound and wellbeing check, sometimes by phone, within the first week or two. It confirms the incisions are healing, pain is manageable and bowels and bladder are working. This is also the moment to ask whether the pathology report is back.
The main review, usually a few weeks later, has three jobs. It confirms the pathology diagnosis in plain words. It assesses recovery against what was done: a simple cystectomy is reviewed differently from an operation that also treated endometriosis. And it sets the plan, which for a benign simple cyst is often discharge back to routine care with advice on symptoms to watch.
A repeat ultrasound is not automatic. It tends to be arranged when there was a cyst on the other ovary, when the cyst type is one that can recur, when symptoms persist, or when the report raised a question. Mayo Clinic notes that ultrasound is the main tool for following ovarian cysts, so if a scan is booked it is usually to establish a new baseline rather than because anything is wrong.
Blood tests, including a tumor marker called CA-125, are sometimes part of follow-up after menopause or when the report was anything other than clearly benign. CA-125 is a protein that can rise in ovarian cancer but also in benign conditions such as endometriosis, so it is interpreted alongside everything else rather than alone.
If you are discharged without a follow-up appointment, ask what that means and what would bring you back. Discharge is a result too; it means the team is satisfied, and you are entitled to hear why.
Pain, pressure and the cyst that was there before: what settles and what lingers
Can an ovarian cyst cause pain? Yes, in several distinct ways, and sorting out which kind you had helps you judge whether surgery addressed it.
Mayo Clinic and the NHS describe cyst pain as typically a dull ache or pressure low in the pelvis, sometimes on one side, that can worsen with sex, exercise or bowel movements. A larger cyst can press on the bladder, causing frequent urination, or create a sense of fullness. Sudden, severe pain is different: it suggests rupture, where the cyst bursts and fluid irritates the pelvic lining, or torsion, where the weight of the cyst makes the ovary twist on its blood supply. Torsion is a surgical emergency because the ovary can be lost if blood flow is not restored.
After surgery, pain that was caused by the cyst’s size or pressure usually eases as the pelvis recovers, though surgical soreness overlaps with it for the first weeks and can make this hard to judge. Pain from endometriosis is a separate story. If your pathology report names an endometrioma, the cyst was one source of pain among several, and removing it may improve but not abolish the symptom. That is not a failed operation; it is the nature of the condition, and it is why the follow-up conversation shifts toward managing endometriosis long term.
A small number of people develop new pain weeks or months after surgery from adhesions, the internal scar tissue mentioned earlier. It is worth reporting rather than enduring.
A practical suggestion: note, before your review, how the pain you had before surgery compares with how you feel now. Patients who bring that comparison get a more useful appointment than those who are asked to recall it on the spot.
What people often get wrong about ovarian cyst surgery results
Some beliefs are repeated so often they sound like medicine. Here are the ones that cause the most unnecessary worry.
“A big cyst means a dangerous cyst.” Size does not equal risk. Some of the largest cysts removed are benign cystadenomas or dermoids, while ultrasound features such as solid areas matter far more. The pathology report, not the measurement, carries the meaning.
“If it was benign, they would not have operated.” Most cystectomies are done for benign cysts. Pain, size, growth, torsion risk and the need to be sure are all legitimate reasons. Cleveland Clinic and Johns Hopkins both note that the vast majority of cysts are not cancerous.
“The cyst came back, so the surgery failed.” A new functional cyst is a sign of a working ovary, and Mayo Clinic notes these typically resolve within two to three months. Only certain cyst types, particularly endometriomas, are genuinely prone to recurrence.
“Having one ovary removed halves your fertility.” The remaining ovary usually continues to ovulate, and many people conceive with one ovary. The more relevant question is ovarian reserve, which your team can discuss with you.
“A late period after surgery means something went wrong.” A disturbed first cycle is common and mechanical, as described earlier.
“Supplements or diets can dissolve cysts or stop them returning.” There is no reliable evidence that any diet, herb or supplement removes an ovarian cyst or prevents a new one. Watchful waiting works for functional cysts because the cyst resolves on its own, not because of anything taken alongside it.
If you recognize one of these from a conversation or a forum, the fix is simple: ask your care team to confirm what your own report and scan actually show.
Questions to ask your care team
A good follow-up appointment is short on surprises and long on specifics. Bring this list, cross off what is already answered, and write down the replies.
- What exactly did the pathology report say, in one sentence, and is there anything on it that changes my follow-up?
- Was the cyst removed intact, and was the ovary kept? If the whole ovary was removed, why?
- Did you see anything else in the pelvis, such as endometriosis, adhesions or a cyst on the other ovary?
- Is this a cyst type that can come back, and what would that look like for me?
- Do I need a repeat ultrasound or blood test, and if so, when and what is it checking?
- How long should I expect my period to be irregular, and when would an irregular cycle become something to report?
- Does this operation affect my fertility or ovarian reserve, and if I am planning a pregnancy, is there anything I should do differently?
- What are the specific signs that should make me contact you, and how do I reach the team out of hours?
- When can I drive, lift, exercise and return to work, based on what was done to me rather than a general leaflet?
- If I was discharged from clinic, what would bring me back under your care?
Two habits make these questions more productive. Ask for a copy of the pathology report and operative note for your own records; you are entitled to them and they are useful for any future doctor. And if an answer uses a term you do not understand, say so. Pathology vocabulary is not intuitive, and clinicians would rather translate than have you go home and guess.
When to call your doctor
Most recoveries are uneventful, and most results are reassuring. The following signs are the exceptions that need a same-day call to your surgical team, or emergency care if they are severe. This guidance draws on the NHS and MedlinePlus post-laparoscopy advice.
- Severe or worsening abdominal pain that is not controlled by the pain relief you were given.
- A fever, chills or feeling generally unwell.
- Redness, swelling, warmth, increasing pain or discharge at an incision, or an incision that opens.
- Heavy vaginal bleeding, meaning soaking through pads hourly, or bleeding that increases rather than fades.
- Persistent vomiting, inability to keep fluids down, or a swollen, tight abdomen.
- Pain or burning when passing urine, or being unable to pass urine.
- Pain, swelling or redness in a calf, which can signal a blood clot.
- Sudden shortness of breath, chest pain or coughing up blood, which can signal a clot in the lung and is an emergency.
- Fainting, dizziness on standing, or a racing heartbeat.
Beyond the recovery window, two further situations warrant contact. If sudden, sharp, one-sided pelvic pain arrives, especially with nausea or vomiting, it could indicate a new cyst that has ruptured or an ovary that has twisted, and it should be assessed promptly. And if the pathology report has not reached you by the time you were told to expect it, call and ask; results occasionally sit in a system longer than they should.
None of this means hovering over every twinge. It means knowing the handful of signs that change the picture, and trusting the team that operated on you to tell you what they mean.
Frequently asked questions
What are the potential side effects of ovarian cyst removal surgery?
Expected short-term effects are incision pain, shoulder-tip pain from laparoscopic gas, bloating, nausea, tiredness and light vaginal bleeding. Less common complications include infection, bleeding, injury to bowel or bladder, blood clots and internal scar tissue called adhesions. Removing an endometrioma can reduce the egg supply on that ovary. Your consent discussion and follow-up appointment cover which of these apply to your operation.
Can an ovarian cyst cause pain?
Yes. A cyst can cause a dull ache or pressure low in the pelvis, often on one side, that worsens with sex, exercise or bowel movements, and a large cyst can press on the bladder. Sudden, severe one-sided pain suggests rupture or torsion, where the ovary twists on its blood supply, and needs urgent assessment. Pain from an endometrioma may persist after removal because the underlying endometriosis remains.
How long does ovary cyst surgery take?
The operation itself is usually measured in an hour or two rather than a full day. The NHS states that a diagnostic laparoscopy takes about 30 to 60 minutes, and removing a cyst adds time for freeing it from the ovary and checking for bleeding. Large cysts or endometriosis scarring take longer. Including anesthetic preparation and recovery, plan for most of a day, with discharge often the same day or the next.
How quickly can ovarian cysts grow back?
A removed cyst does not regrow, but new cysts can form. Functional cysts can appear in any ovulatory cycle, so one may be seen on a scan within months; Mayo Clinic notes these usually resolve within two to three months without treatment. Dermoids and cystadenomas recur uncommonly and over years. Endometriomas are the type the NHS highlights as most likely to return, which is why endometriosis itself is managed after surgery.
What do ovarian cyst pathology results show?
The report describes the removed tissue, examines the cells lining the cyst wall under a microscope, and gives a diagnosis naming the cyst type, almost always with the word benign. Common findings are functional cysts, dermoid cysts, endometriomas and cystadenomas. Occasionally the report uses the term borderline, which is not cancer but requires specialist follow-up. Ask your team to translate the diagnosis line into one plain sentence.
What is a typical ovarian cystectomy recovery time?
It depends on how much was done. The NHS advises that after minor laparoscopic procedures many people are back to normal activities within about five days, while recovery from major surgery can take up to 12 weeks. A straightforward keyhole cystectomy usually sits toward the shorter end, with tiredness lasting a week or two. Open surgery through a larger incision means a slower timeline. Your discharge instructions override any general figure.
Is it normal to have an irregular period after ovarian cyst surgery?
Yes, a first period that is late, early, heavier, lighter or more painful than usual is common. The operated ovary is inflamed and can delay ovulation, and anesthetic, pain and stress affect the same hormone rhythm. Most people are close to their own normal within two or three cycles. Persistent irregularity beyond that, or very heavy bleeding, is worth reporting to your gynecologist.
Can ovarian cysts come back on the other ovary?
They can. Functional cysts form wherever ovulation happens, so either ovary can produce one in any cycle. Dermoid cysts and endometriomas can also occur on the opposite ovary. Surgeons routinely inspect the other ovary during the operation and record it in the operative note, and a follow-up ultrasound is sometimes arranged to establish a new baseline for both ovaries rather than because anything is wrong.
Does removing an ovarian cyst affect fertility?
Usually not in a way that prevents pregnancy, but it can reduce ovarian reserve on the operated side because a small amount of healthy ovarian tissue is removed with the cyst wall. This matters most for endometriomas, whose walls are closely bound to the ovary. If a whole ovary was removed, the remaining one typically continues to ovulate. Raise fertility plans with your team before surgery where possible and at follow-up.
Do I need a follow-up scan after ovarian cyst removal?
Not always. A repeat ultrasound is usually arranged when a cyst was seen on the other ovary, when the cyst type can recur, when symptoms persist or when the pathology report raised a question. For a benign simple cyst with a smooth recovery, many people are discharged to routine care with advice on symptoms to watch. If no scan is planned, ask what would bring you back under the team’s care.
References
- NHS: Ovarian cyst, treatment
- NHS: Laparoscopy (keyhole surgery)
- MedlinePlus: Pelvic laparoscopy
- Cleveland Clinic: Ovarian cysts
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Ovarian Cysts During Pregnancy: How They Are Monitored and When Treatment Is Considered
An ovarian cyst found during pregnancy is usually a simple, fluid-filled cyst that goes away on its own and is followed with repeat ultrasound…

Preparing for a Hysterectomy: Imaging, Lab Tests, Medicines to Pause and Fasting Rules
Hysterectomy preparation usually includes a pre-operative assessment with blood tests, sometimes an ECG, and imaging such as pelvic ultrasound to plan the operation. Your…

Preparing for Endometriosis Laparoscopy: Fasting, Medicine Review and Fertility Goals
Preparing for an endometriosis laparoscopy usually means three things: following the fasting instructions your anesthesia team gives you (commonly around six hours without food,…

How Laparoscopic Endometriosis Surgery Works: Excision, Incisions and How Long It Takes
Laparoscopic endometriosis surgery is keyhole surgery under general anesthesia. A surgeon makes a few small abdominal cuts, usually around 1 to 1.5 cm, inflates…

Can You Have a Smear Test on Your Period? What Clinics Advise and When to Rebook
Yes, a smear test (Pap or cervical screening) can usually still be done during a period, and many clinics will go ahead if bleeding…

Living With PCOS: Periodic Glucose, Cholesterol and Hormone Checks Your Doctor Will Plan
Living with PCOS usually means a planned cycle of checks rather than a one-off diagnosis. Doctors typically repeat glucose testing (an HbA1c or oral…