

How Trabeculectomy Lowers Eye Pressure: The Tiny Flap, the Bleb and the Operating Room Steps

Key Takeaways
- Trabeculectomy lowers pressure by building a new drain: a partial-thickness scleral flap over a small window, with fluid collecting in a bleb under the conjunctiva where it is absorbed.
- The flap is deliberately stitched a little tight on the day and loosened afterward in clinic with laser suture lysis or releasable stitches, which is why early follow-up visits are so frequent.
- Scar tissue is the main reason a trabeculectomy stops working, so antimetabolites such as mitomycin C or 5-fluorouracil are commonly applied during surgery to slow healing around the bleb.
- In the randomized Tube Versus Trabeculectomy study, trabeculectomy achieved pressures in the low teens but had more early complications and a higher five-year failure rate than tube shunts in previously operated eyes.
- Recovery is measured in weeks, with vision often blurrier at first, strenuous activity and swimming restricted, and the bleb's long-term shape largely set within the first two months.
- A bleb carries a small lifelong infection risk, so a red, painful, discharging eye in anyone who has had filtration surgery is an emergency at any interval after the operation.
Trabeculectomy lowers eye pressure by creating a new, controlled exit for the fluid inside the eye. The surgeon lifts a tiny trapdoor in the white of the eye, removes a small piece of tissue beneath it, and lets fluid seep out under the clear surface membrane, where it collects in a small blister called a bleb and is absorbed. How much pressure falls, and for how long, depends on healing and follow-up care.
The appointment usually ends with a sentence that is hard to hear in a dimly lit room: the drops are no longer enough. A person who has been faithfully squeezing a bottle into each eye for years learns that the pressure is still nudging the optic nerve, and the next step is an operation with a name that sounds like a tongue-twister.
Trabeculectomy has been the workhorse of glaucoma surgery for more than half a century, and yet most people meet it for the first time in that chair. Understanding how trabeculectomy works turns an abstract worry into a mechanical idea: a plumbing fix for an eye whose drain has slowed down.
This explainer walks through the fluid that builds the pressure, the tiny flap the surgeon makes, the blister that does the quiet work afterward, and the weeks of fine-tuning that matter as much as the operation itself.
What is trabeculectomy, in plain language?
A trabeculectomy is an operation that gives the fluid inside the front of the eye a second way out. The name comes from the trabecular meshwork, the spongy tissue in the angle where the colored iris meets the clear cornea, which is the eye’s natural drain. In most forms of glaucoma that drain works poorly, fluid backs up, and pressure rises against the optic nerve at the back of the eye.
Rather than trying to repair the clogged drain, the surgeon bypasses it. A thin trapdoor is cut partway through the sclera, the tough white outer coat of the eye, near the top of the eye under the upper lid. Beneath that flap, a small opening is made into the front chamber. Fluid then trickles through the opening, under the flap, and into the space beneath the conjunctiva, the thin transparent membrane that covers the white of the eye. There it pools as a low blister and is slowly absorbed into surrounding tissue and small blood vessels.
That is the whole principle of how trabeculectomy works. The flap acts as a valve: stitched down firmly enough that fluid cannot gush out, loosely enough that it can seep. The blister, called a bleb, acts as a reservoir. The operation does not restore vision already lost, and it does not treat the underlying tendency toward glaucoma. It lowers pressure, and lowering pressure is, according to the National Eye Institute and the NHS, the only intervention shown to slow glaucoma damage.
People sometimes hear it described as filtration surgery. The term is accurate: the eye is being given a filter that lets fluid leave under control. Everything else in this article is a detail of how that filter is built, protected and adjusted.
Why eye pressure matters: the fluid your eye makes every day
The eye is not a sealed balloon. A structure behind the iris called the ciliary body continuously produces a clear liquid, aqueous humor, that nourishes the lens and cornea, neither of which has a blood supply. That fluid circulates through the pupil into the front chamber and leaves mainly through the trabecular meshwork into a drainage canal and then into veins on the surface of the eye.

Production and drainage normally stay balanced, and the resulting intraocular pressure sits, for most people, somewhere in a range of roughly 10 to 21 millimeters of mercury, the same unit used for blood pressure. Johns Hopkins Medicine and Mayo Clinic both describe this range as a guide rather than a strict line; some optic nerves are damaged at lower pressures, and some tolerate higher ones for years.
Pressure matters because the optic nerve leaves the eye through a sieve-like opening at the back, and the delicate nerve fibers there are compressed and starved when pressure stays high. The damage is painless and begins in peripheral vision, which is why glaucoma earns its reputation for silence. The NHS notes that lost vision cannot be regained, so every treatment, from drops to laser to surgery, aims at the same single lever: bring the pressure down to a level the nerve can live with, often called a target pressure.
Eye drops reduce fluid production or coax more out through existing channels. Laser treatments stimulate the natural drain. Trabeculectomy is different in kind. It accepts that the drain cannot be made to work well enough and builds a new one. That is why it is usually reached for when the gentler options have been tried, or when pressure is so high, or damage so advanced, that the treating team judges there is no time to climb the ladder slowly.
How trabeculectomy works: the flap, the window and the bleb
Picture the top of the eye, hidden under the upper eyelid. Three layers matter here. The outermost is the conjunctiva, a transparent, slightly loose membrane. Beneath it lies a thin fibrous layer, and beneath that the sclera, the firm white shell about the thickness of a credit card.
The surgeon first opens the conjunctiva and lifts it away, like peeling back wallpaper without tearing it. This creates a pocket that will later hold the drained fluid. The conjunctiva must be handled gently and closed watertight, because a leak here is one of the commonest early problems.
Next comes the flap. Using a fine blade, the surgeon outlines a small square or triangle on the exposed sclera and shaves a partial-thickness layer forward toward the cornea, leaving it hinged at the front. This trapdoor is the pressure regulator of the whole operation. Beneath it, a tiny block of deep tissue is removed, creating a window into the front chamber of the eye, and a small piece of the iris is usually removed as well so that iris tissue cannot plug the window from inside.
The flap is then laid back and stitched. The tension of those stitches sets how freely fluid escapes. Too tight and the pressure barely falls; too loose and the chamber can collapse. Many surgeons place extra stitches that can be loosened or released in the weeks after surgery, which is covered later in this article.
Finally the conjunctiva is drawn back over the flap and sewn down. Fluid now seeps through the window, around the edges of the flap, and lifts the conjunctiva into a bleb. The bleb’s thin wall lets fluid pass into surrounding tissue and tiny vessels, which carry it away. Cleveland Clinic describes the end result as a permanent, controlled drainage route; how well it keeps working depends on how the body heals around it.
What happens in the operating room, step by step
The operation itself is shorter than most people expect, typically well under an hour, and the NHS describes it as usually done as a day case under local anesthetic, with sedation available for comfort. General anesthetic is used for some people, including children and those who cannot lie still.
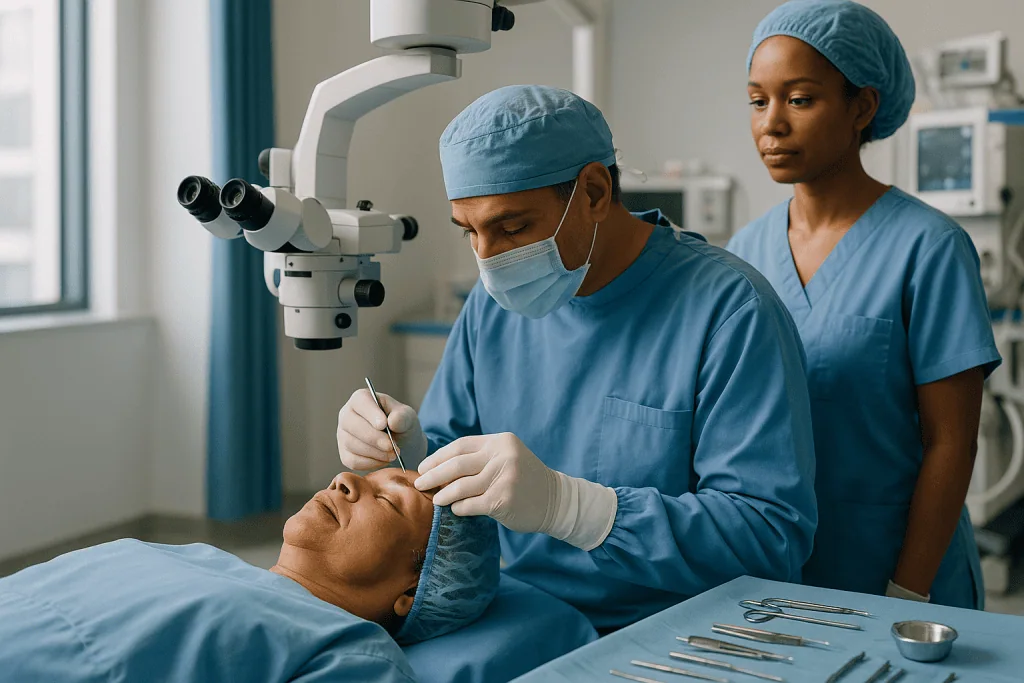
The sequence runs roughly like this. Numbing is given with drops and an injection around the eye, so the eye does not move or feel pain; pressure and touch may still be sensed. A sterile drape covers the face with an opening for the eye, and a small clip holds the lids apart. A soft breeze of oxygen under the drape keeps breathing comfortable.
Working through an operating microscope, the surgeon opens the conjunctiva and, in most modern cases, applies a scar-slowing medicine to the exposed tissue for a measured time before rinsing it away thoroughly. The scleral flap is cut and lifted. A small paracentesis, a pinprick entry at the edge of the cornea, is made so the chamber can be refilled or tested later. The inner window is cut, the small iris opening is made, and the flap is stitched.
The surgeon then tests the plumbing by injecting fluid through the paracentesis and watching how briskly it emerges around the flap, tightening or loosening stitches until the flow looks right. The conjunctiva is closed with very fine sutures and checked for leaks with a dye.
An antibiotic and an anti-inflammatory medicine are commonly placed on or around the eye at the end, and a pad and shield are taped over it. Most people go home the same day with instructions to rest, keep the shield on overnight, and return the next morning so the team can measure pressure and inspect the bleb. That first-day visit is where the real adjustment phase begins.
What is a bleb after glaucoma surgery, and why does it matter?
A bleb is the small, pale, slightly raised blister that forms on the white of the eye above the surgical flap. It is hidden under the upper eyelid, so most people never see their own bleb in a mirror, but the surgeon examines it at every visit because its appearance tells the story of how the operation is doing.
A healthy functioning bleb tends to look low, diffuse and a little translucent, with scattered tiny cysts in its wall where fluid is passing through. Cleveland Clinic and Mayo Clinic both describe the bleb as the reservoir that collects aqueous fluid before it is absorbed. Its wall must stay thin enough to let fluid through yet tough enough to hold together for years.
Two things can go wrong with a bleb, in opposite directions. The first is scarring. The body treats the surgical site as a wound and lays down fibrous tissue; if that tissue thickens the bleb wall or seals the space beneath it, fluid can no longer escape and pressure creeps back up. This is the main reason trabeculectomies lose effect over time, and it drives both the use of scar-slowing medicines during surgery and the needling procedures sometimes performed afterward.
The second is a bleb that is too thin or leaking. A very thin-walled bleb can weep fluid onto the surface of the eye or let bacteria in. An infected bleb can progress to infection inside the eye, which is an emergency. Because of this, a person with a bleb carries a small lifelong risk that does not expire, and the NHS and Mayo Clinic both emphasize reporting a red, painful or sticky eye promptly for the rest of life, not just in the first months.
In short, the operation builds the bleb, but the bleb’s behavior over months and years decides whether the pressure stays controlled.
Why surgeons use scar-slowing medicines during the operation
The body is extremely good at healing holes, and that talent works against a trabeculectomy. Left to itself, the tissue under the conjunctiva produces fibroblasts, the cells that build scar, and within weeks they can wall off the new drainage route. Early trabeculectomies in the 1960s and 1970s failed often for exactly this reason.
The answer, adopted widely from the 1980s onward, was to apply an antimetabolite during surgery. An antimetabolite is a medicine that interferes with cell division, so it slows the fibroblasts that would otherwise close the filter. The two used in glaucoma surgery are mitomycin C and 5-fluorouracil. Both are mentioned here only to explain the mechanism; the choice of agent, whether to use one at all, and the way it is applied are decisions for the operating surgeon based on the individual eye.
In practice a small sponge or an injection delivers the medicine to the surgical bed for a controlled period, after which the area is rinsed thoroughly. The effect is local and lasting: tissue exposed to the medicine scars less, so the bleb stays thin and functional for longer.
There is a trade-off, and honest explainers say so. Thinner, less scarred blebs can be too thin. Mayo Clinic and the NHS list bleb leaks, very low pressure, and late bleb infection among the recognized complications of filtration surgery, and these are somewhat more likely when healing has been strongly suppressed. Surgeons therefore judge each eye’s scarring risk. Younger people, people with darker irises or heavily pigmented skin, people who have had previous eye surgery or long-term drop use, and people with inflammatory eye disease tend to scar more aggressively and are more likely to receive an antimetabolite; the exposure is tailored accordingly.
Research continues into alternatives that modulate healing more selectively, but as of the mainstream guidance these two medicines remain the standard tools, used because the evidence shows they improve the chance that the filter keeps working.
Who is trabeculectomy usually for, and who is usually asked to wait?
Trabeculectomy is not a first step. The NHS describes surgery as an option when drops or laser have not controlled pressure well enough, or when they are not suitable. The National Eye Institute lists it among the procedures considered when medicines are insufficient. In practice the people who most often reach the operating table share one of a few situations.
The first is progressive damage despite treatment: visual field tests or optic nerve scans show the disease advancing even on a full regimen of drops, and the target pressure is not being met. The second is intolerance, where drops cause so much surface irritation, allergy or systemic side effect that they cannot realistically be used for decades. The third is very high pressure or advanced loss at diagnosis, where the team judges that waiting for drops to prove themselves carries too much risk to the remaining nerve. A fourth is practical: people who cannot manage multiple daily drops reliably, for reasons of memory, dexterity or circumstance.
Equally important is who is usually asked to wait, or offered something else. People with mild disease well controlled on one or two drops generally are not candidates, because the risks of surgery outweigh the benefit. Eyes with active inflammation are usually settled first, since inflammation drives scarring. Eyes with extensive scarring of the conjunctiva from previous surgery, or with certain forms of glaucoma driven by abnormal blood vessels, often do better with a tube shunt instead. Someone who needs cataract surgery soon may be steered toward a combined or sequenced plan.
Age by itself is not a barrier. Health conditions that make lying flat difficult, blood-thinning medicines, and the ability to attend frequent follow-up visits all enter the discussion, because a trabeculectomy without close aftercare is only half an operation. None of these factors is a rule; each is a weight on a scale that the treating team balances with the person in front of them.
Trabeculectomy vs tube shunt, laser and minimally invasive options
Trabeculectomy sits in a family of pressure-lowering procedures, and people naturally ask how it compares. The table summarizes the main options in neutral terms; which one fits a given eye is a clinical judgment.
| Approach | How it lowers pressure | Typically considered when | Notable trade-offs |
|---|---|---|---|
| Trabeculectomy | Scleral flap and window drain fluid into a bleb under the conjunctiva | Drops and laser insufficient; low target pressure needed | Largest potential pressure drop; needs intensive follow-up; lifelong bleb-related risks |
| Tube shunt (aqueous drainage device) | Small silicone tube carries fluid to a plate stitched further back on the eye | Previous failed filtration, scarred conjunctiva, neovascular or uveitic glaucoma | Fewer early complications in trials; final pressures often somewhat higher; tube and plate can erode or touch the cornea |
| Laser trabeculoplasty | Light energy stimulates the natural drain to work better | Early or moderate open-angle glaucoma, as first-line or add-on | Office procedure, few risks; effect may wear off and can be repeated |
| Minimally invasive glaucoma surgery (MIGS) | Tiny stents or incisions bypass or open the natural drainage angle, often combined with cataract surgery | Mild to moderate disease, especially with a cataract | Faster recovery; smaller pressure reduction than trabeculectomy |
The most-cited head-to-head evidence is the Tube Versus Trabeculectomy study, a randomized trial in eyes that had already undergone cataract or glaucoma surgery. At five years, published in the American Journal of Ophthalmology, cumulative failure was lower with the tube (about 30 percent) than with trabeculectomy using mitomycin C (about 47 percent), while both groups achieved similar average pressures in the low teens; early postoperative complications were more frequent after trabeculectomy, and reoperation for glaucoma was more common in the trabeculectomy group. Those findings apply to that specific population and should not be read as a verdict for every eye. Trabeculectomy still tends to be chosen when the lowest possible pressure is the priority in an eye with healthy conjunctiva, and the tube when scarring or unusual glaucoma types make a bleb unreliable. The treating team weighs the pattern of the disease, the state of the eye’s surface, and how the person can manage aftercare.
Trabeculectomy recovery time: what the first days and weeks usually look like
Recovery after trabeculectomy is less about pain and more about patience. The eye is usually gritty and watery rather than painful, and vision is often blurrier than before for a while, partly because the eye is softer and partly because of the drops. The NHS advises that it can take several weeks for vision to settle, and that people should expect to avoid driving until the team confirms it is safe.
The first day: the pad comes off at the morning visit, pressure is measured, and the bleb and the stitch line are inspected under the microscope. Two kinds of drops are usually started, an antibiotic to prevent infection and an anti-inflammatory steroid to calm healing and slow scarring. The steroid is used more intensively and for longer than after cataract surgery, precisely because scarring is the enemy of the bleb. How often and for how long is set by the surgeon and tapered according to what the eye is doing.
The first two weeks: visits are frequent, often weekly or more. The shield is worn at night to prevent rubbing in sleep. Bending, lifting, straining and vigorous exercise are typically limited because they raise pressure in the head and eye and can disturb the flap. Swimming and eye make-up are off the list until the surface has sealed, and water should be kept out of the eye. Reading and screens are allowed; they tire the eye but do not harm it.
Weeks two to eight: this is the window in which the bleb takes its long-term shape, and the window in which stitch adjustment or needling is most often performed. Cleveland Clinic frames full healing in terms of about a month or two, with routine activities returning gradually as the team allows. Glasses may need updating once the eye stabilizes. Throughout, the single most useful thing a person can do is keep every appointment, because the operation is being tuned in real time.
How follow-up visits fine-tune the pressure after surgery
One idea surprises almost everyone: the surgeon deliberately leaves the flap a little tight on the day and loosens it afterward. The reason is safety. A flap that drains too freely in the first days can let the pressure fall so low that the front chamber shallows or the retina’s blood-rich lining swells. It is far easier to open a tight flap gradually than to rescue an eye that has emptied itself.
Three techniques do the tuning. The first is suture lysis, in which a laser is aimed through a small contact lens at one of the flap stitches to cut it, so the flap lifts slightly and more fluid escapes. The second uses releasable sutures, stitches with a tail buried under the surface that can be pulled out at the slit lamp with forceps. Both are done in the clinic with numbing drops, take minutes, and the pressure is rechecked afterward. The timing depends on the eye’s response, and most surgeons prefer to act within the early weeks before scar tissue fixes the flap in place.
The third technique is bleb needling. If the bleb is becoming walled off, a fine needle is passed under the conjunctiva to break the forming scar and reopen the space, usually with a small injection of an antimetabolite beside it to discourage the scar from reforming. This can be repeated if needed.
Some surgeons also teach digital massage, pressing gently through the lower lid in a prescribed way to push fluid through the flap. It is only ever done if the surgeon specifically shows the technique, because the same pressure applied wrongly can harm a fresh eye.
Each of these interventions is a nudge rather than a redo. Together they explain why the schedule of visits in the first two months is so dense, and why the eventual pressure is a product of surgery plus aftercare rather than the operation alone.
Trabeculectomy risks and complications: what the evidence actually shows
Any operation that opens the eye carries risk, and trabeculectomy’s risks are specific to the drainage it creates. The NHS, Mayo Clinic and Cleveland Clinic each list a similar set, and it helps to group them by when they tend to appear.
Early, in days to weeks: pressure that is too low, called hypotony, which can make vision blurry and in some cases allow fluid to collect behind the choroid, the eye’s vascular layer; a shallow or flat front chamber; a leaking conjunctival wound; bleeding inside the eye; and a transient rise in pressure if the flap is too tight. Most of these are managed in clinic with drops, pressure patches, stitch adjustment or a small revision, and most settle.
Intermediate, in weeks to months: scarring that reduces or stops the filter, which is the most common reason for inadequate pressure lowering and may call for needling, additional drops or a further operation. Cataract formation is accelerated after trabeculectomy, and many people who did not already have one will develop a cataract in the following years; it can be removed in the usual way, though cataract surgery itself can nudge a bleb toward scarring.
Late, at any time: bleb-related infection, which begins as a localized infection of the bleb and can spread inside the eye as endophthalmitis, a sight-threatening emergency; a late leak from a thin bleb; and a large or overhanging bleb that causes dryness and irritation. The lifelong nature of this risk is the reason a person with a bleb needs to be able to reach eye care quickly at any point in the future.
Vision can be permanently worse after surgery, including, rarely, a sudden unexplained loss of central vision in eyes with very advanced damage. The randomized Tube Versus Trabeculectomy study found early complications in roughly a third of trabeculectomy eyes, most of them self-limiting. Those numbers come from a specific population; the surgeon will put the risks in the context of the individual eye, and the decision to proceed always rests with that conversation.
What people often get wrong about trabeculectomy
“The surgery will bring my sight back.” It will not. Optic nerve fibers lost to glaucoma do not regrow, and no mainstream guidance suggests otherwise. The goal is to protect what remains. Vision is frequently a little worse for weeks after surgery before settling, and some people end up needing a different glasses prescription.
“Once it is done, I am finished with drops.” Many people do use fewer or no pressure-lowering drops afterward, but a course of anti-inflammatory and antibiotic drops is routine in the recovery period, and some eyes need pressure drops added back later if the filter partially scars. The number of long-term medicines is an outcome the team watches, not a guarantee.
“It is a laser.” Laser trabeculoplasty and laser iridotomy are office procedures that take minutes and need little aftercare. Trabeculectomy is an incisional operation under the microscope, with stitches and a bleb. Confusing the two leads people to underestimate the recovery.
“The bleb is a complication.” The bleb is the point. A trabeculectomy without a bleb is a trabeculectomy that has scarred shut. Its presence under the lid, and its slight bumpiness if touched, are signs of a working filter.
“The pressure after surgery is what I will have forever.” Pressure typically moves during the first two months as the flap is adjusted and healing settles, and it can drift over years as tissue slowly remodels. Lifelong monitoring continues.
“If my eye looks fine, I can skip visits.” The early visits are where the surgeon loosens stitches or needles a bleb to rescue a filter before scar fixes it. Missing them can turn a salvageable eye into one needing another operation.
“Infection risk ends once the eye heals.” Bleb-related infection can occur years later. A red, aching eye with discharge in a person who has had filtration surgery is treated as urgent at any age and any interval.
Questions to ask your care team before trabeculectomy
A good consultation is a conversation, and arriving with specific questions turns a nervous ten minutes into a useful one. These are the ones that tend to matter most; write the answers down, because the details blur afterward.
- What is my target pressure, and why is that the number for my eye rather than a general one?
- Why trabeculectomy for me rather than a tube shunt, laser or a minimally invasive procedure, and what would change that choice?
- Will a scar-slowing medicine be used during the operation, and what does that mean for my particular healing risk?
- What kind of anesthetic do you plan, and what will I feel or hear during the procedure?
- How many follow-up visits should I expect in the first two months, and how far apart will they be?
- What drops will I use afterward, how will they be reduced, and who adjusts that schedule if the eye reacts differently than expected?
- Which of my current medicines, including blood thinners and other eye drops, need to be discussed before the day?
- What activities are limited, for how long, and when might I drive, work, exercise and swim again?
- If the bleb starts to scar, what are the next steps, and how will I know it is happening?
- What exactly should make me call the same day, and what number do I call outside clinic hours?
- What are the chances, for an eye like mine, that I will need further surgery later, and what might that involve?
- Do I have a cataract now, and how might the operation affect it or future cataract surgery?
- How will this affect my other eye’s management, and would it ever need the same procedure?
The answers will be individual, and some will honestly be “it depends on how you heal.” That is not evasion; it is the nature of a filter that the body finishes building after the surgeon has gone home. The decision to proceed, to wait, or to choose a different route belongs to the person and the treating team together.
When to call your doctor after trabeculectomy
Most of recovery is uneventful, which makes it easy to dismiss the rare symptom that is not. After filtration surgery, certain signs call for same-day contact with the eye team, or emergency eye care if the clinic is closed. The NHS and Mayo Clinic give consistent guidance on the warning signs below.
Call the same day, or go to emergency eye care, if any of the following occurs:
- Increasing pain in or around the eye, especially a deep ache that worsens over hours rather than easing.
- A sudden drop in vision, a new dark curtain or shadow, or a shower of new floaters or flashes of light.
- Redness that is spreading or deepening, particularly with a sticky or pus-like discharge, or a white or yellow spot visible on the eye.
- A gush of clear fluid from the eye, or persistent watering that feels different from ordinary tearing, which may signal a leaking wound or bleb.
- Marked sensitivity to light that is new or worsening.
- Nausea or vomiting together with eye pain or a hard, aching eye, which can accompany a sharp rise in pressure.
- Any direct blow to the eye, or accidental rubbing or pressure on it, even without symptoms.
The same list applies for life, not only in the first weeks. Bleb-related infection can appear years after a successful operation, and it can progress within hours. A person who has had a trabeculectomy and develops a red, painful, discharging eye should say so plainly when seeking care: “I have had glaucoma filtration surgery.” That sentence changes how quickly the eye is examined.
Minor grittiness, mild redness that is slowly improving, and blur that fluctuates through the day are expected in early recovery and can wait for the next scheduled visit. When in doubt, the team would rather hear about a false alarm than miss a true one; a quick pressure check costs little, and an infected bleb caught early is a very different problem from one found late.
Frequently asked questions
How does trabeculectomy actually lower eye pressure?
It creates a controlled leak. The surgeon makes a hinged flap in the white of the eye, removes a tiny piece of tissue beneath it to open a window into the front chamber, and closes the overlying membrane. Fluid seeps through the window, under the flap, and into a blister called a bleb, where it is absorbed into surrounding tissue. Less fluid trapped inside means lower pressure on the optic nerve.
What is a bleb after glaucoma surgery and will I be able to see it?
A bleb is the small, pale, slightly raised reservoir of fluid that forms under the clear membrane covering the white of the eye, directly above the surgical flap. It sits under the upper eyelid, so it is usually invisible in a mirror and most people never notice it. The surgeon checks its height, thickness and vascularity at every visit because a healthy bleb is the sign of a working filter.
How long is trabeculectomy recovery time?
Most people are home the same day, but the eye takes weeks to settle. The NHS advises expecting blurred vision for several weeks, avoiding driving until cleared, and limiting bending, lifting, exercise and swimming during early healing. Follow-up visits are frequent in the first two months, when stitch adjustments are made. Full stabilization is often described in terms of one to two months, though individual timelines vary with healing.
Trabeculectomy vs tube shunt: which is better?
Neither is better in every eye. Trabeculectomy tends to reach lower pressures in eyes with healthy surface tissue, while tube shunts are often chosen when the conjunctiva is scarred from prior surgery or the glaucoma is driven by inflammation or abnormal vessels. The Tube Versus Trabeculectomy trial found fewer early complications and lower five-year failure with tubes in previously operated eyes. The treating team matches the procedure to the eye.
What are the main trabeculectomy risks and complications?
Early risks include pressure that falls too low, a shallow front chamber, a leaking wound and bleeding. Over months, scarring can reduce the filter’s effect, and cataract often develops sooner. At any time in life, the bleb can leak or become infected, which can threaten sight if not treated quickly. Vision may be permanently worse in some cases. Most early problems are managed in clinic and settle.
Is trabeculectomy painful?
The operation itself is done under local anesthetic with numbing drops and an injection, often with sedation, so pain during surgery is not expected, though pressure and touch may be felt. Afterward the eye is typically gritty, watery and light-sensitive rather than painful. Increasing pain, especially a deepening ache in the days after surgery, is not normal and should be reported to the eye team the same day.
Will I still need eye drops after trabeculectomy?
In the recovery period, yes: antibiotic drops to prevent infection and anti-inflammatory steroid drops to slow scarring are routine, with the schedule set and tapered by the surgeon. Many people need fewer or no pressure-lowering drops afterward, but some require them again if the filter partially scars. Whether to continue, reduce or stop any drop is always decided by the treating clinician, never on one’s own.
Why is mitomycin C used during trabeculectomy?
Mitomycin C is an antimetabolite, a medicine that slows cell division. Applied briefly to the surgical site and then rinsed away, it reduces the scar-forming activity that would otherwise seal the new drainage route within weeks. It improves the chance the bleb keeps functioning, at the cost of a somewhat higher risk of thin, leaking or infected blebs. Whether and how it is used is the surgeon’s clinical decision.
Can trabeculectomy restore vision lost to glaucoma?
No. Optic nerve fibers damaged by glaucoma do not regenerate, and no surgery, including trabeculectomy, brings back lost field of vision. The purpose of the operation is to lower pressure so that remaining nerve tissue is protected and further loss is slowed. People should expect vision to be similar to before once the eye has healed, sometimes temporarily blurrier, and occasionally in need of a new glasses prescription.
What happens if the trabeculectomy stops working years later?
Filters can gradually scar, and pressure can rise again months or years after surgery. Options the team may discuss include restarting pressure-lowering drops, needling the bleb to reopen it, revising the original site, performing a second trabeculectomy at a different location, placing a tube shunt, or using laser to reduce fluid production. The right step depends on the eye’s condition and is decided with the treating specialist.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Is PRK or SMILE Better for You? No Flap in Either, Very Different Recoveries
Neither PRK nor SMILE is better for everyone. Both reshape the cornea without a LASIK-style flap, but PRK removes the eye's surface layer and…

When a Chalazion Keeps Coming Back: Repeat Treatment and Why a Biopsy May Be Advised
A recurring chalazion is an eyelid oil-gland blockage that returns after it has settled or been drained. Repeat episodes are usually linked to ongoing…

When Does a Damaged Cornea Need Surgical Repair? Injuries, Infections and Thinning Explained
A damaged cornea needs surgical repair when the injury, infection or thinning threatens the eye's structure or cannot heal with medicines alone: a full-thickness…
Pain, Light Sensitivity or Blurred Vision With Pink Eye: Why These Need Same-Day Review
Most pink eye is mild conjunctivitis that settles on its own, but eye pain, sensitivity to light, or blurred vision that does not clear…

Oculoplastic Surgery Recovery: Cold Compresses, Sleeping Propped Up and Bruise Timelines
Oculoplastic surgery recovery, including eyelid procedures such as blepharoplasty, usually brings the most swelling and bruising in the first two to three days, with…

Is Your Keratoconus Progressing? How Specialists Read the Topography Map
Keratoconus is considered progressing when repeated corneal scans show a consistent trend rather than a single change: steepening of the front surface (often tracked…