

Is a Robotic Partial or Radical Nephrectomy Right for Your Kidney Tumor? How Surgeons Decide

Key Takeaways
- Partial nephrectomy removes the tumor with a thin margin of kidney, while radical nephrectomy removes the entire kidney and often surrounding fat, and sometimes the adrenal gland and lymph nodes.
- Tumor size, with a common dividing line around 4 centimeters, and how close the tumor sits to the kidney's central vessels drive the choice more than any other factors.
- Nephrons do not regenerate, so kidney tissue removed at surgery is gone for good, though remaining nephrons enlarge and work harder to compensate.
- During a partial nephrectomy the renal artery is usually clamped, and surgeons minimize this warm ischemia time because oxygen-starved nephrons can be permanently lost.
- MedlinePlus puts the hospital stay for kidney removal at roughly one to seven days, with robotic and laparoscopic operations at the shorter end and heavy lifting typically restricted for about six weeks.
- The pathology report, not the type of operation, determines how intensively kidney cancer is monitored afterward, since spread risk depends mainly on tumor stage and grade.
Surgeons usually favor a partial nephrectomy, which removes only the tumor and a rim of kidney, for smaller tumors confined to one part of the kidney, because it preserves kidney function. A radical nephrectomy, removing the whole kidney, is generally chosen for larger, central or locally advanced tumors. Tumor size, location, the health of the other kidney and the patient's overall fitness guide the decision, which rests with the treating team.
The scan was ordered for something else entirely: a nagging pain under the ribs, a routine check on a gallbladder. Then the radiologist’s report mentioned a “renal mass,” and a stranger in a urology office started sketching a kidney on the back of a form. Two arrows. One says remove part. The other says remove all.
That sketch is where most people first meet the question of partial vs radical nephrectomy, and it arrives with an odd emotional twist. You feel fine. The tumor was a coincidence. Yet the choice on that form could shape how well your kidneys filter blood for the rest of your life.
Surgeons do not flip a coin here. They follow a fairly consistent logic built on tumor size, where it sits, what the rest of your kidneys can do, and what the robot on the operating table makes possible. This is that logic, explained the way a good surgeon would if the clinic ran on time.
What does partial vs radical nephrectomy actually mean?
A nephrectomy is surgery to remove some or all of a kidney. The two words in front of it describe how much comes out.
A partial nephrectomy removes the tumor together with a thin margin of healthy tissue around it, leaving the rest of the kidney in place and working. Urologists also call this nephron-sparing surgery, because it protects the nephrons, the roughly one million microscopic filtering units packed into each kidney. A radical nephrectomy removes the entire kidney, usually with the fatty tissue around it and sometimes the adrenal gland that sits on top and nearby lymph nodes, according to MedlinePlus and Mayo Clinic descriptions of the operation.
Both can be done through one long incision (open surgery) or through several small ports with a camera (laparoscopic surgery), often with robotic instruments that the surgeon controls from a console a few feet away. The robot does not decide anything; it translates the surgeon’s hand movements into finer, steadier motions inside the abdomen.
It helps to hold one idea firmly from the start. The debate is not really “robot versus no robot.” It is “how much kidney can safely stay.” The robotic approach simply widened the range of tumors for which a partial operation is technically achievable, because stitching a bleeding kidney back together through keyhole ports is far easier with wristed instruments and a magnified three-dimensional view.
One more definition, because it comes up constantly: a renal mass is any abnormal growth seen on imaging. Most solid renal masses that get referred to surgeons turn out to be kidney cancer, but a meaningful share are benign, and scans cannot always tell the difference in advance. That uncertainty is baked into every decision that follows.
How does a robotic partial nephrectomy work, step by step?
Picture the kidney as a firm, bean-shaped organ the size of a fist, fed by a single main artery and drained by a single vein. That plumbing is the whole challenge. Kidneys receive a large share of the heart’s output, so cutting into one without controlling the blood supply is not an option.
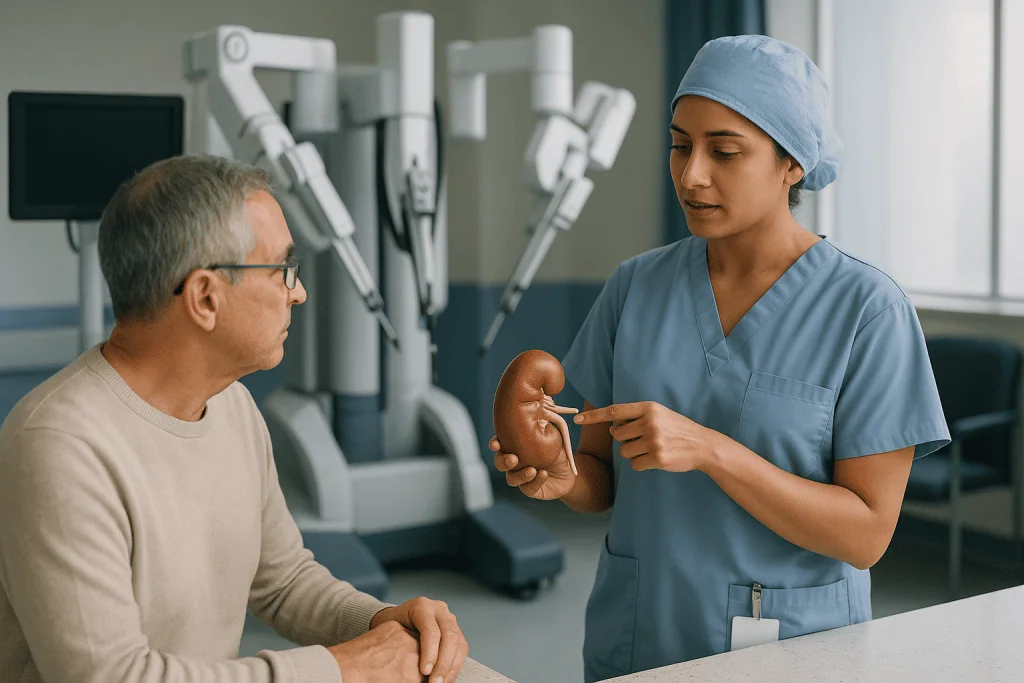
Under general anesthesia, the surgeon places several small ports in the abdomen or flank and docks the robotic arms. After freeing the kidney from surrounding fat, the team identifies the renal artery and, in most partial operations, places a temporary clamp on it. The clock now matters. The period without blood flow is called warm ischemia time, and surgeons work to keep it short because nephrons tolerate only limited time without oxygen before some are permanently lost.
With the kidney briefly bloodless, the tumor is cut out along with a rim of normal tissue. Any opened urine-collecting channels are stitched closed, the raw surface is sewn together in layers, the clamp is released, and the surgeon checks for bleeding before closing. Some teams use ultrasound on the kidney’s surface during the operation to map the tumor’s depth, and some avoid clamping altogether for very shallow tumors.
A robotic radical nephrectomy follows a simpler script. The artery and vein are sealed and divided, the ureter is cut, and the kidney is placed in a bag and removed through one slightly enlarged incision. No stitching of kidney tissue, no ischemia clock.
Which is exactly why the radical operation is technically easier and the partial one demands more from the surgeon and the patient’s anatomy. The extra difficulty is the price of keeping working tissue.
Why tumor size and location matter more than anything else
Ask a urologist what they look at first and most will say the images, not the biopsy. Kidney tumors are graded by size and position long before they are graded under a microscope.
Size comes first. Kidney cancer staging groups tumors that are confined to the kidney into a smaller category and a larger one, with a commonly used dividing line at roughly 4 centimeters, about the width of two fingers, as outlined in Mayo Clinic’s overview of kidney cancer stages. Smaller tumors are strong candidates for partial removal. Tumors between that line and about 7 centimeters are often still removed partially in experienced hands, while larger ones tilt toward radical surgery.
Location is the quieter but often decisive factor. A tumor perched on the outer edge of the kidney, well away from the central plumbing, is like an apple on the end of a branch: easy to take without harming the tree. A tumor sitting deep in the middle, wrapped around the main vessels or the urine-collecting system, is like an apple growing out of the trunk. Removing it while leaving a functioning kidney becomes technically demanding and sometimes unwise.
Surgeons formalize this with scoring systems that rate a tumor’s size, how deep it sits, how close it is to the collecting system, and whether it faces the front or back of the kidney. A low score predicts a straightforward partial operation; a high score warns of longer clamp times, higher bleeding risk and a greater chance the team converts to removing the whole kidney.
Multiple tumors in one kidney, or a tumor that appears to have grown into the renal vein, push the decision further toward radical removal, because the goal shifts from saving tissue to clearing disease cleanly.
Who is a partial nephrectomy usually for, and who is asked to wait?
The clearest candidate is someone with a single, smaller tumor on the edge of the kidney and otherwise reasonable health. For that person, keeping the kidney is almost always the default, and it takes a specific reason to remove the whole organ.

Certain situations make preserving tissue not just preferable but close to essential. People who have only one kidney, whose other kidney is already weakened, who have diabetes or high blood pressure that threatens kidney function over time, or who carry inherited conditions that cause tumors in both kidneys all fall into this group. Losing a whole kidney in those circumstances raises the long-term likelihood of chronic kidney disease, a gradual loss of filtering capacity that can eventually require dialysis.
Then there are people asked not to operate at all, at least for now. Active surveillance, which means monitoring a small tumor with repeat scans rather than removing it, is an accepted option for very small masses, particularly in older adults or people whose other medical conditions make any operation riskier than the tumor itself. Many small kidney tumors grow slowly, and some never cause harm, as the NHS and Mayo Clinic both note in their treatment guidance. Surveillance is not neglect; it is a deliberate decision with a plan to act if the tumor grows or changes.
Frailty, poorly controlled heart or lung disease, and blood-thinning medicines that cannot be safely paused are all reasons a team may recommend waiting, optimizing health first, or choosing a less invasive tumor-destroying technique such as heat or freezing delivered through a needle. Those techniques have their own trade-offs, and a treating team weighs them alongside surgery rather than as a fallback.
When do surgeons choose radical nephrectomy instead?
Removing a whole kidney sounds drastic, and there was a period when it was the standard for nearly every kidney tumor. Today it is reserved for specific circumstances, but those circumstances are not rare.
Large tumors lead the list. When a mass occupies most of the kidney, the amount of healthy tissue that could be saved is often too small to be worth the added bleeding and leak risk of a partial operation. Central tumors that sit on the main vessels, tumors that have grown into the renal vein or the large vein returning blood to the heart, and tumors that appear to have spread to nearby lymph nodes are all usually managed by taking the kidney out, sometimes with additional structures.
The health of the opposite kidney changes the math in both directions. If the other kidney is normal, a person can live a full life with one, and surgeons are more comfortable recommending radical removal when a partial operation would be difficult. If the other kidney is compromised, the team will stretch much harder to preserve tissue.
Suspected aggressive biology also matters. Imaging features suggesting an unusually fast-growing or infiltrative tumor, or a biopsy showing a high-grade subtype, push toward wide removal, because the priority becomes clean margins and complete clearance.
There is a practical dimension, too. A partial nephrectomy that runs into trouble can require a long clamp time, heavy bleeding, or conversion to full removal mid-operation. For an older patient with a large, deep tumor and a healthy opposite kidney, a planned radical nephrectomy may be the safer, more predictable route. Surgeons describe this frankly during consent, and it is a legitimate question to raise if your case sits in that gray zone.
Partial vs radical nephrectomy: a side-by-side comparison
Seeing the two operations lined up makes the trade-offs easier to hold in your head. These are typical patterns described in patient resources from Mayo Clinic, Cleveland Clinic and MedlinePlus; your own surgeon’s assessment will be more specific.
| Factor | Partial nephrectomy | Radical nephrectomy |
|---|---|---|
| What is removed | Tumor plus a thin margin of kidney | Entire kidney, surrounding fat; sometimes adrenal gland and lymph nodes |
| Typical tumor | Smaller, confined, often near the kidney’s outer edge | Larger, central, multiple, or extending into veins or nodes |
| Kidney function afterward | Most of the kidney’s filtering capacity preserved | Relies entirely on the remaining kidney |
| Technical complexity | Higher: clamping, cutting, stitching under time pressure | Lower: vessels sealed, organ removed whole |
| Specific surgical risks | Bleeding from the cut surface, urine leak, positive margin | Bleeding at the vessel stumps, injury to neighboring organs |
| Long-term concern | Small chance of tumor regrowth at the site; follow-up imaging needed | Higher long-term likelihood of reduced kidney function |
| Hospital stay | Commonly one to several days | Commonly one to several days |
Two rows deserve a second look. The complexity row explains why not every surgeon offers a partial operation for difficult tumors, and why volume and experience are fair things to ask about. The long-term row captures the real heart of the decision: partial surgery trades a slightly more demanding operation and closer follow-up for a kidney that keeps working; radical surgery trades kidney tissue for a simpler, more definitive removal.
Neither column is “better.” The right column is the one that fits the tumor in front of the surgeon and the body it lives in.
What is nephron-sparing surgery, and why do kidney doctors care so much?
Nephrons are the reason this whole debate exists. Each one is a tiny filter and tube that pulls waste and excess fluid from blood into urine. You are born with a fixed supply, and once a nephron is lost to surgery, disease or aging, it is not replaced.
Kidney specialists think in terms of estimated glomerular filtration rate, or eGFR, a blood-test-based number that reflects how much filtering your kidneys do each minute. Removing a kidney takes away roughly half the nephrons in one stroke. The remaining kidney enlarges and works harder, so eGFR does not fall by half, but it does fall, and the reserve that protects you against future insults shrinks.
Why does that reserve matter if you feel fine? Because kidney function declines slowly with age for everyone, and faster in people with high blood pressure, diabetes, or heart disease, conditions that are common in the age group most likely to develop kidney tumors. Starting that decline from a lower baseline means reaching the threshold of chronic kidney disease sooner. Chronic kidney disease, in turn, is linked with cardiovascular problems and, at its most advanced, the need for dialysis or transplant.
This is the argument for sparing nephrons whenever oncologically reasonable, and it is the argument that shifted guidelines away from routine radical nephrectomy. It is not an argument that partial surgery is always right. Guidelines from urological societies frame it as the preferred option for smaller confined tumors when technically feasible, with radical removal remaining appropriate for larger or complex disease.
What you can take from this: if a surgeon recommends taking the whole kidney, asking “what will my kidney function look like afterward, and what is my baseline now?” is a fair and important question.
Is radical nephrectomy a high-risk surgery?
People search this question late at night, and the honest answer has two halves. Radical nephrectomy is major abdominal surgery under general anesthesia, and it carries the risks that come with any major operation. It is also a well-established procedure performed routinely, and for most otherwise healthy people the operation itself is not the most dangerous part of their kidney cancer journey.
The risks that matter, described in patient information from Mayo Clinic and MedlinePlus, fall into a few groups. Bleeding is the main intraoperative concern, because the kidney’s vessels are large and carry high flow. Injury to neighboring structures, including the bowel, spleen, pancreas or the lining of the lung, is uncommon but possible given how snugly the kidney is packed. Infection at the wound or in the urine, blood clots in the legs that can travel to the lungs, pneumonia, and heart or breathing complications from anesthesia round out the general surgical risks.
Then there is the risk specific to this operation: living with one kidney. Most people manage well, but the long-term chance of reduced kidney function is higher than after a partial operation, particularly for those who already had borderline kidney function or conditions that damage kidneys.
Robotic and laparoscopic approaches tend to mean less blood loss, smaller wounds and shorter hospital stays than open surgery, according to Cleveland Clinic’s description of the procedure, though the internal operation is the same and the anesthesia risks do not change with the size of the incision.
Your personal risk is shaped by age, heart and lung health, weight, diabetes, smoking and how complex the tumor is. Anesthesia teams assess these before surgery, and the number they care about is yours, not the average.
What partial nephrectomy recovery time usually looks like, week by week
Recovery is where the robotic approach earns most of its reputation. Small incisions heal faster than a long flank cut, and most people are walking within a day. Timelines below are typical ranges drawn from MedlinePlus, Mayo Clinic and Cleveland Clinic patient guidance; your team’s instructions override them.
The first few days. MedlinePlus puts the hospital stay for kidney removal at roughly one to seven days depending on the type of surgery, with laparoscopic and robotic operations at the shorter end. Expect a urinary catheter for a day or so, a possible small drain, gas pain in the shoulders from the abdomen being inflated during surgery, and encouragement to walk the corridors early to lower clot risk.
Weeks one and two. Fatigue dominates. Incisions are tender; many people can shower, climb stairs and manage light household tasks. Blood tests check kidney function, and the pathology report on the removed tumor usually arrives in this window.
Weeks two to six. Energy returns in steps. Mayo Clinic and Cleveland Clinic guidance describes avoiding heavy lifting and strenuous activity for around six weeks, longer after open surgery. Desk-based work often resumes sooner than physical work. After a partial nephrectomy specifically, surgeons may extend the lifting restriction, because the stitched kidney needs time to heal and a late bleed, though uncommon, can occur.
Beyond six weeks. Most people feel close to normal. A follow-up visit reviews the pathology, kidney function and the imaging schedule for the years ahead.
Radical nephrectomy recovery follows a similar arc, without the stitched-kidney precautions but with the same attention to kidney function blood tests. Anyone told their recovery would be a matter of days rather than weeks has been given a marketing timeline, not a medical one.
Do kidneys grow back after partial nephrectomy?
Not in the way people hope, and the truth is more interesting than a simple no.
Kidney tissue does not regenerate like liver or skin. Nephrons removed with a tumor are gone, and the stitched edge heals with scar tissue rather than new filters. What remains, however, adapts. The surviving nephrons in the operated kidney and in the opposite kidney enlarge and increase their filtering work, a process called compensatory hypertrophy. This is why a person who loses an entire kidney typically ends up with well over half of their original filtering capacity rather than exactly half.
After a partial nephrectomy, most of the kidney was never removed, so the adjustment is modest. The bigger factor in how much function returns is the ischemia time during surgery, since nephrons deprived of blood flow for too long can be damaged even if they were not cut out. That is the entire reason surgeons obsess over clamp times and, where feasible, avoid clamping.
Kidney function blood tests taken in the first days after surgery often look worse than the eventual result, because the kidney is stunned and swollen. Many people see improvement over the following weeks as inflammation settles and compensation kicks in, which is why teams repeat the test at follow-up rather than judging by the first number.
Two practical implications follow. First, protecting the kidney you keep matters more than ever: good blood pressure control, attention to blood sugar if you have diabetes, avoiding tobacco, and checking with your care team before taking over-the-counter anti-inflammatory pain relievers, which can stress kidneys. Second, the kidney is not going to “fill back in,” so the follow-up scans that look at the operated site are checking for tumor regrowth, not for regrowth of the kidney itself.
Can kidney cancer spread after partial nephrectomy? What follow-up involves
Yes, it can, and the same is true after a radical nephrectomy. The risk depends far more on the tumor’s stage and grade than on which operation was performed. Large randomized and observational studies comparing the two approaches for smaller confined tumors have found cancer outcomes to be broadly similar, which is why guidelines feel comfortable favoring the tissue-sparing option when it is technically feasible.
There are two distinct things follow-up watches for. Local recurrence means the tumor returning in or near the operated kidney. It is uncommon after a complete partial removal with clear margins but is the one risk that is specific to keeping the kidney, and it is why imaging of the operated site continues for years. Distant spread, also called metastasis, means cancer cells that had already traveled before surgery growing elsewhere, most often in the lungs, bones, liver or brain. The chance of this is driven by how advanced the tumor was, not by whether a margin of kidney was left behind.
The pathology report, the microscopic analysis of the removed tissue, becomes the roadmap. It records the cancer type, its grade (how abnormal the cells look), whether the margins were clear, and whether the tumor had grown into fat or vessels. Low-stage, low-grade tumors with clear margins earn a lighter surveillance schedule; higher-risk features earn more frequent scans and, in some cases, a discussion about additional treatment after surgery.
Follow-up typically combines periodic imaging, blood tests of kidney function, and a clinical check. The NHS describes this monitoring continuing for several years after treatment. If a scan shows something new, options range from repeat surgery to needle-based tumor destruction to drug therapies that act on the immune system or on the blood supply tumors depend on, all decided by the treating team based on the specifics.
What is the most aggressive form of kidney cancer, and does it change the operation?
Most kidney cancers are renal cell carcinoma, which begins in the lining of the kidney’s tiny tubes. Within that family, clear cell carcinoma is by far the most common type, as Mayo Clinic’s overview notes, and behaves across a wide spectrum from slow-growing to aggressive depending on its grade and stage.
Several rarer subtypes are recognized for behaving more aggressively as a group. Collecting duct carcinoma arises in the deep, central part of the kidney and often presents at an advanced stage. Renal medullary carcinoma, strongly associated with sickle cell trait, is rare, tends to affect younger people and is known for early spread. Any subtype that develops sarcomatoid features, meaning the cells take on a spindle-shaped appearance resembling connective-tissue cancer, is treated as high-risk regardless of its original type. Kidney cancer in children is a different disease altogether, most often Wilms tumor, with its own pathway.
Does aggressive biology change the surgical choice? Sometimes. If imaging or a biopsy raises strong suspicion of one of these subtypes, or the tumor is large and infiltrative, surgeons lean toward radical removal to secure wide margins, and may sample lymph nodes for staging. The conversation also widens to include medical oncologists earlier, because these cancers are the ones most likely to need treatment beyond surgery.
Two reassurances belong here, offered without softening the facts. First, these aggressive types make up a small minority of kidney tumors found today, most of which are discovered incidentally while still small. Second, “aggressive” describes a tendency across a group, not a verdict for an individual. Stage at diagnosis, completeness of removal and the pathology report tell you far more about your own situation than the subtype name alone.
What people often get wrong about kidney tumor surgery
Myths cluster around this decision, partly because kidney tumors are often found by accident and people have little time to learn before being asked to choose.
“Taking the whole kidney is safer because it gets everything.” For smaller confined tumors, studies comparing the two operations have not shown a cancer-control advantage for radical removal, while the kidney-function cost is real. “More surgery” is not automatically “more thorough.”
“Partial surgery is always the modern choice.” A large, central or vein-invading tumor is often best handled by removing the kidney. Insisting on a partial operation in that setting raises bleeding and incomplete-removal risks without a clear benefit.
“The robot does the surgery.” It is a set of instruments controlled entirely by the surgeon. Outcomes track the surgeon’s experience and the tumor’s complexity, not the presence of a machine.
“A biopsy is always needed first.” Many kidney tumors go to surgery on imaging alone, because biopsies can miss the diagnosis and the scan appearance is often persuasive. Biopsy is used selectively, for example before surveillance or needle-based treatments, or when a benign or non-kidney cause is suspected.
“You cannot live normally with one kidney.” Millions do, including living kidney donors. The caveat is a smaller reserve, which is why protecting the remaining kidney matters.
“A small tumor must come out immediately.” Active surveillance is an accepted, guideline-supported option for very small masses in the right person, and many such tumors grow slowly or not at all.
“Feeling fine means the tumor is harmless.” Most kidney tumors cause no symptoms until they are large. The absence of symptoms says little about stage, which is why the pathology report, not how you felt, guides follow-up.
Questions to ask your care team
A consultation about kidney surgery moves fast, and the most useful questions are the ones that reveal the reasoning behind a recommendation rather than just the recommendation itself. Consider bringing these, in your own words.
- How large is the tumor, where exactly does it sit, and how does that shape your recommendation for a partial or radical operation?
- What is my current kidney function, and what do you expect it to be after each option?
- Is my other kidney healthy? Would that change your advice?
- Is active surveillance a reasonable option for me, and what would prompt a change of plan?
- Are needle-based treatments such as heat or freezing suitable for my tumor, and how do their trade-offs compare with surgery?
- If you plan a partial nephrectomy, how likely is it that you would need to remove the whole kidney during the operation, and what would lead to that?
- Will you use robotic, laparoscopic or open surgery, and why is that approach right for my tumor?
- How many of these operations does your team perform, and what complications do you see most often?
- Will lymph nodes or the adrenal gland be removed? What decides that?
- Which of my regular medicines need to pause before surgery, and who coordinates that?
- What will recovery look like for me specifically, and when can I return to work, driving and exercise?
- What will the pathology report tell us, and when will we discuss it?
- What follow-up imaging and blood tests will I need, and for how long?
- What symptoms after surgery should make me call you the same day?
Write the answers down or bring someone who will. The value of this conversation is not in getting a “yes” to a particular operation; it is in understanding why your team believes one path fits your tumor and your body better than the other.
When to call your doctor
Before surgery, most kidney tumors are silent, but some symptoms should never wait for a scheduled appointment. Blood in the urine, whether pink, red or cola-colored, warrants prompt medical assessment even if it appears once and clears. Persistent pain in the side or back that does not shift with position, a lump you can feel in the flank, unexplained weight loss, fevers without an obvious cause, or new swelling in one leg all deserve a same-week conversation with a clinician, according to Mayo Clinic and NHS symptom guidance.
After a partial or radical nephrectomy, your team will give written instructions. The signs below are the ones that generally mean contact them the same day or seek urgent care:
- Fever or shaking chills, which can signal a wound, urine or deep infection
- Heavy or increasing blood in the urine, or urine that stops flowing
- Worsening abdominal or flank pain that pain relief does not touch, or a belly that becomes swollen and hard
- Redness, warmth, spreading swelling or pus at an incision, or a wound edge that opens
- Calf pain or swelling in one leg, a possible blood clot
- Sudden shortness of breath, chest pain or coughing up blood, which can indicate a clot traveling to the lungs and are emergency symptoms
- Persistent vomiting or inability to keep fluids down
- Passing very little urine over a day, or a drop in urine output your team asked you to watch for
- Dizziness, fainting or a racing heartbeat, which can accompany internal bleeding
None of these means something has certainly gone wrong. Each is a signal that a trained person should look, and looking early is almost always simpler than looking late. Keep the surgical team’s contact number where you can find it in the middle of the night, and use it. Surgeons would far rather hear about a false alarm than discover a real problem at the six-week visit.
Frequently asked questions
Do kidneys grow back after partial nephrectomy?
No, kidney tissue removed during surgery does not regrow. Nephrons, the kidney’s filtering units, are a fixed supply, and the cut edge heals with scar tissue. The remaining nephrons in both kidneys do enlarge and increase their work, a process called compensatory hypertrophy, which is why function usually recovers to close to its previous level after a partial operation, provided clamp time was short.
What is the most aggressive form of kidney cancer?
Rare subtypes such as collecting duct carcinoma and renal medullary carcinoma, along with any kidney cancer showing sarcomatoid features, are generally considered the most aggressive. They make up a small minority of cases. Most kidney cancers are clear cell renal cell carcinoma, whose behavior ranges widely depending on stage and grade. Your pathology report describes your own tumor’s type and grade.
Can kidney cancer spread after partial nephrectomy?
Yes, it can, just as it can after radical nephrectomy. The likelihood depends mainly on the tumor’s stage and grade at the time of surgery rather than on which operation was done. Follow-up imaging watches for both local recurrence at the operated site and distant spread, most often to the lungs or bones, with the schedule set by the pathology findings.
Is radical nephrectomy a high-risk surgery?
It is major surgery with the general risks of bleeding, infection, blood clots and anesthesia complications, but it is a routine, well-established operation that most otherwise healthy people tolerate well. The main long-term consideration is living with one kidney, which reduces filtering reserve. Individual risk depends on age, heart and lung health, diabetes, weight, smoking and tumor complexity, which your anesthesia and surgical teams assess beforehand.
How long is partial nephrectomy recovery time?
Typical ranges from MedlinePlus, Mayo Clinic and Cleveland Clinic guidance describe a hospital stay of about one to several days for robotic or laparoscopic surgery, a return to light activity within one to two weeks, and avoidance of heavy lifting and strenuous exercise for around six weeks. Open surgery usually takes longer. Your surgeon may extend restrictions after a partial operation while the stitched kidney heals.
Is robotic partial nephrectomy better than open surgery?
Robotic surgery generally means smaller incisions, less blood loss and a shorter hospital stay, but the operation performed inside the body is the same, and outcomes depend on the surgeon’s experience and the tumor’s complexity rather than on the robot itself. Open surgery remains appropriate for some very large or complex tumors. The choice of approach is made by your surgical team based on your anatomy.
What is nephron-sparing surgery?
Nephron-sparing surgery is another name for partial nephrectomy. It removes the tumor with a thin rim of normal kidney while preserving the rest of the organ and its nephrons, the microscopic filtering units you cannot regrow. Guidelines favor it for smaller confined tumors when technically feasible, because keeping kidney tissue lowers the long-term likelihood of chronic kidney disease compared with removing the whole kidney.
Can I live a normal life with one kidney?
Most people can. A single healthy kidney enlarges and takes on additional work, and living kidney donors demonstrate that a normal, active life with one kidney is common. The trade-off is reduced reserve, so protecting the remaining kidney matters: blood pressure control, attention to blood sugar, avoiding tobacco, and checking with your care team before regular use of anti-inflammatory pain relievers.
Do I need a biopsy before kidney tumor surgery?
Not always. Many kidney tumors are removed based on imaging alone because CT or MRI appearances are often persuasive and biopsies can miss the diagnosis. Biopsy is used selectively, for example before choosing active surveillance or a needle-based treatment, when a benign tumor or a cancer from elsewhere is suspected, or when the result would genuinely change the plan. Your team will explain their reasoning.
What are the main radical nephrectomy risks compared with partial?
Radical nephrectomy carries a higher long-term chance of reduced kidney function because the whole organ is removed. Partial nephrectomy carries more procedure-specific risks, including bleeding from the cut surface, urine leak from the collecting system, a positive margin, and a small chance of local recurrence. Both share general surgical risks such as infection, blood clots and anesthesia complications, which your team weighs against your tumor and overall health.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
What Recovery From Stomach Cancer Surgery Looks Like Week by Week
Recovery from stomach cancer surgery usually means one to two weeks in hospital, followed by several months of gradual rebuilding at home. The early…
Skin Care During IMRT: Fragrance-Free Products, Sun Protection and Daily Habits
Skin care during IMRT centers on a few evidence-based habits: wash the treated area gently with lukewarm water and a mild, fragrance-free cleanser, pat…
Supporting a Family Member Through Cancer Treatment: Appointments, Nutrition and Rest
Supporting a family member through cancer treatment usually means three practical jobs: being a second set of ears at appointments, keeping food and fluids…

After TURBT: What Is Expected in the First Days and Which Symptoms Need a Call
After TURBT, it is normal to pass pink or light red urine, feel burning or urgency when you pee, have brief cramping bladder spasms,…
Questions to Ask a Surgical Oncologist Before Agreeing to a Cancer Operation
Before agreeing to a cancer operation, ask the surgical oncologist what the surgery is meant to achieve, exactly what will be removed, how the…
Preparing for Colon Cancer Surgery: Bowel Preparation, Medication Review and Fitness Checks
Bowel prep before colon cancer surgery usually means a low-residue diet, a prescribed laxative solution and, in many centers, oral antibiotics during the day…