

PRK Recovery Timeline: Hazy Days, Bandage Lens Removal and the Slow Climb to Clear Vision
Key Takeaways
- PRK removes the corneal epithelium rather than cutting a flap, and that outer layer typically regrows across the treated zone in about three to five days, which is why the bandage contact lens comes off in that window.
- Discomfort after PRK usually peaks on days one to three and then eases as the surface closes; pain that worsens after day three or four is a red flag, not a normal variation.
- Vision commonly dips for a few days right after bandage lens removal because the new epithelium is thicker and more irregular than mature tissue, and it smooths over the following weeks.
- Many eyes show a temporary shift toward farsightedness in the early weeks after PRK that drifts back toward target, so near tasks can feel oddly harder than distance around week three.
- The prescription typically stabilizes between one and three months, with some higher corrections still changing toward six months, and surgeons wait for stability before discussing glasses or any enhancement.
- Driving after PRK depends on a measured vision standard confirmed by your surgeon rather than how well you feel you see, and day five is genuinely borderline for many people.
A typical PRK recovery timeline runs in stages: the outer corneal layer regrows over roughly three to five days, during which the bandage contact lens is worn and discomfort peaks; vision is usually blurry and fluctuating for the first week or two; most people find it functional within a few weeks; and the prescription commonly settles over about one to three months, sometimes longer. Individual healing varies, so your surgeon's follow-up checks set the pace.
The morning after surgery, a woman sits at her kitchen table holding a small plastic bottle six inches from her face, trying to read which drop is which. The letters swim. Her eyes water, the window light feels like an accusation, and somewhere in the back of her mind a voice asks whether this is what she signed up for. Her surgeon had said the first days would be rough. Nobody had quite explained what rough would look like at breakfast.
That scene is close to universal for people who choose photorefractive keratectomy, and it is why the PRK recovery timeline deserves an honest telling rather than a cheerful one. Unlike LASIK, PRK removes the surface skin of the cornea, and that skin has to grow back before the eye can even begin to focus properly.
What follows is the sequence most surgeons describe, tied to mainstream evidence, with the fluctuations, the hazy patches and the slow uphill stretch included.
How PRK works: what the laser actually removes
PRK, short for photorefractive keratectomy, is a laser procedure that reshapes the front surface of the eye so that light focuses more sharply on the retina. To understand why recovery takes the shape it does, it helps to picture the cornea as a clear dome with layers. The outermost layer is the epithelium, a thin sheet of living cells that behaves much like skin: it can be scraped away and it grows back. Beneath it sits the stroma, the thick structural layer that gives the cornea its curve and does most of the focusing.
During PRK the surgeon first removes the epithelium over the treatment zone, using a diluted alcohol solution, a soft brush or the laser itself. An excimer laser, an ultraviolet laser that vaporizes tissue in extremely thin layers without heating its surroundings, then sculpts the exposed stroma to flatten, steepen or smooth it according to your prescription. Some surgeons briefly apply mitomycin C, a medicine that dampens the scarring response, to lower the chance of later haze; whether it is used is a surgical judgement, not a patient choice. A bandage contact lens goes on last, and the whole procedure is measured in minutes.
The critical difference from LASIK is that no flap is cut. LASIK lifts a hinged flap of cornea, treats underneath and lays the flap back, so the surface is nearly intact the same day. PRK leaves an open area of stroma, several millimeters across, that the epithelium must migrate over from the edges. According to a peer-reviewed StatPearls review hosted by the NIH, that migration typically closes the defect in about three to five days. Everything else in the PRK recovery timeline follows from that one biological fact.
Who PRK is usually for, and who is usually asked to wait
Surgeons tend to lean toward PRK when the cornea is thinner than they would like for a flap, when the surface has small irregularities, or when a person’s work or sport carries a real risk of a blow to the eye. A LASIK flap can, rarely, be dislodged by trauma even years later; PRK has no flap to dislodge. Military service, contact sports and some occupational safety programs have historically favored the surface approach for that reason. PRK is also considered for people who had earlier refractive surgery and now need a touch-up where cutting another flap is unwise.

Being asked to wait is common and usually sensible. The NHS notes that laser eye surgery is generally not offered to people under 21 or to anyone whose prescription is still changing, because reshaping a moving target wastes tissue and invites a second operation. Surgeons typically want evidence of a stable prescription across recent eye tests. Pregnancy and breastfeeding shift corneal hydration and hormones, so many teams defer until several months afterward. Uncontrolled dry eye, active eye infection or inflammation, poorly controlled diabetes and certain autoimmune conditions that impair wound healing all tend to push the decision back rather than off the table.
Some people are steered away altogether. Keratoconus, a condition in which the cornea thins and bulges into a cone shape, is a standard exclusion because removing further tissue can accelerate the bulging. Very high prescriptions may exceed what can safely be sculpted. A prior eye examination that maps corneal thickness and shape is where these calls are made, and the decision belongs to the treating ophthalmologist, weighing your eye against the evidence rather than against a brochure.
PRK recovery day by day: the first 72 hours
The day of surgery is often the easiest of the first three, which surprises people. Anesthetic drops keep the eye numb for a while, vision is cloudy but present, and most people are told to go home, close the curtains and sleep. Someone else drives.
By that evening or the next morning the numbing has faded and the raw surface makes itself known. The StatPearls review describes pain, light sensitivity, tearing and a foreign-body sensation as expected in the first two to three days while the epithelium is open, and it is the single feature that most separates the early PRK experience from LASIK. People describe it as sand under the lid, or the ache after staring into a welding arc. Bright screens are unpleasant, reading is hard because the eye cannot hold focus, and tears may run without warning.
Day two is frequently the low point. The epithelium is halfway across the defect, the bandage lens is doing its job, and there is little to do except keep the drop schedule, wear dark glasses even indoors if that helps, and resist rubbing. Rubbing can lift the lens or tear the fragile new cells. Cold compresses over closed lids are commonly allowed, though your team will say so specifically. Sleep shields, if issued, prevent accidental contact overnight.
Around day three many people notice the sting easing, sometimes abruptly, as the last gap closes. Vision does not leap forward at this point. It is often still poor, perhaps enough to move around the house but not to read a menu, and it changes from hour to hour. That is the ordinary texture of this stage and not a sign that something went wrong.
Bandage lens removal: what happens around day three to five
A bandage contact lens is a soft lens with no prescription in it, placed over the cornea purely as a dressing. It shields the healing surface from the lid, reduces pain by keeping the exposed nerve endings covered, and gives the migrating epithelial cells a smooth roof to grow beneath. It is not there to help you see.
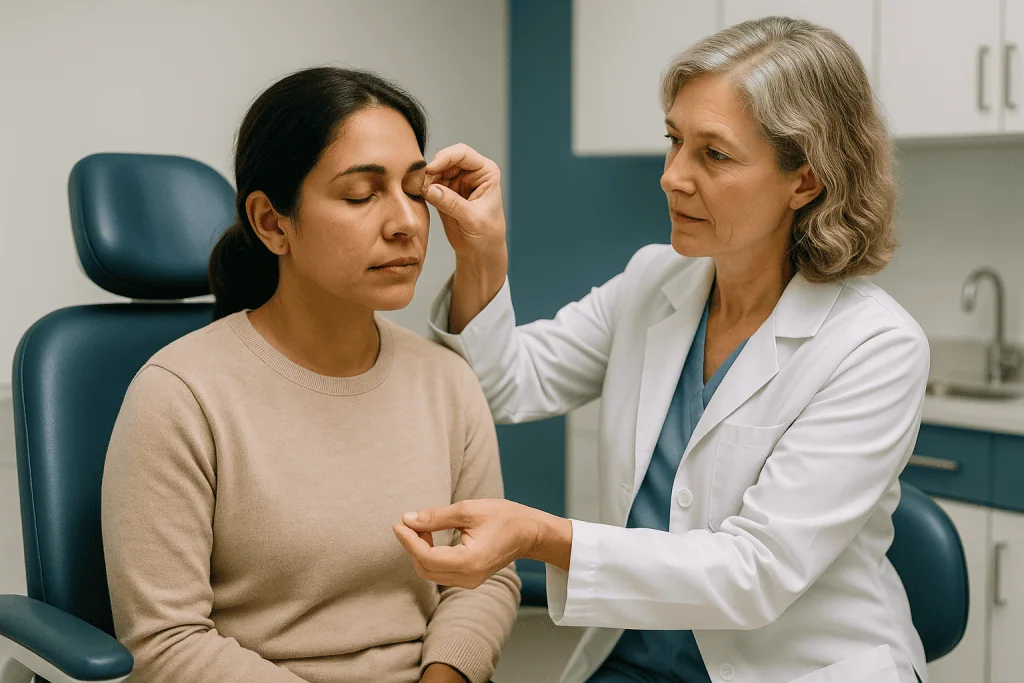
The removal visit usually falls between the third and fifth day, matching the epithelial closure window cited in the StatPearls review. The surgeon or a technician will put a drop of fluorescein, a yellow-orange dye that pools in any gap in the epithelium and glows under blue light, then look through a slit lamp, the tabletop microscope used in eye clinics. If the surface is fully covered, the lens is slid off with fine forceps or a fingertip in a moment. If a small area is still open, the lens may stay on another day or two.
Vision often gets briefly worse after the lens comes off, and this is the moment that unsettles people most. The lens had been smoothing over an uneven surface; without it, the new epithelium, which is thicker and more irregular than mature tissue, is exposed to the tear film directly. Light scatters. Letters double or blur. This stage typically improves over the following days as the cells reorganize, but it is a genuine dip in the curve.
Two practical points matter here. Never remove the lens yourself, even if it feels loose or scratchy, because the surface beneath may not be ready. And if the lens falls out on its own, call the clinic rather than trying to reinsert it or waiting for the scheduled visit, since an unprotected, partially healed surface is more vulnerable to infection.
Why vision goes hazy in week one
The haze most people notice in the first week is not the same thing as the corneal haze surgeons worry about, and separating the two saves a great deal of anxiety.
Early haze is a surface phenomenon. Freshly regrown epithelium is a patchwork of young cells of uneven height, and the tear film that normally forms a glass-smooth optical layer cannot lie flat over it. The effect is like looking through a window in light rain: the glass is fine, the water on it is not. Vision fluctuates with blinking, with time of day, with how dry the room is and with how long the eyes have been open. MedlinePlus notes that vision after PRK is blurry at first and improves over several weeks, and this surface smoothing is a large part of why.
True corneal haze, sometimes called subepithelial haze, is different. It is a faint clouding within the front of the stroma caused by activated wound-healing cells laying down disorganized collagen. The StatPearls review places its usual appearance at weeks to months after surgery, with a tendency to fade over the following year, and notes that modern laser profiles and the intraoperative use of mitomycin C have made visually significant haze uncommon. Your surgeon grades it at follow-up visits with the slit lamp; you cannot assess it yourself by how blurry things look.
During this week, preservative-free lubricating drops, used as often as your team suggests, help by rebuilding that optical tear layer. Blinking deliberately during screen use helps too. Squinting, rubbing or straining to force focus does nothing for the biology and tires the eye. Most people find the fluctuations narrow noticeably by the end of the second week, though some sharp days and some soft days remain.
Weeks two to six: the slow climb
This is the stretch that online day-by-day diaries tend to compress into a single line, and it is where patience is tested most. The pain is gone, the lens is out, the surface has closed, and yet vision refuses to behave. One morning a street sign is crisp; by afternoon it has softened. Night driving shows halos around headlights. Reading fine print takes effort.
Several things are happening at once. The epithelium is thinning back toward its normal architecture. The stroma is remodeling around the new curve. And there is a well-documented temporary overshoot: the StatPearls review describes an early shift toward farsightedness in many eyes after PRK that drifts back toward the intended target over the following weeks as healing settles. If you were nearsighted before surgery and find that near work is oddly harder than distance in week three, that overshoot is often the reason, and it is expected rather than a miscalculation.
Anti-inflammatory steroid drops are usually still in use during this phase, tapered on a schedule your prescriber sets. They exist to calm the wound-healing response and reduce haze risk, and the taper is deliberate; stopping early because vision seems fine, or continuing longer because it seems slow, are both decisions for the clinician, who will also be checking eye pressure, since steroids can raise it in some people.
Functionally, many people are back at desk work, cooking, walking outdoors and watching television by the second or third week, with lubricants at hand and sunglasses outside. What they are generally not yet doing is judging the final result. The NHS advises that it can take weeks to months for vision to fully settle after laser eye surgery, and this window sits squarely inside that range.
Months one to three and beyond: when the prescription settles
By about the one-month visit, most surgeons expect the surface to look smooth under the slit lamp and the vision to be steadily useful, even if not yet final. Between the first and third months the daily fluctuations usually dampen, the farsighted overshoot fades, and night halos shrink as the epithelium finishes remodeling. MedlinePlus describes full visual recovery from PRK as taking up to several months, in contrast to the days typical after LASIK, and the StatPearls review places refractive stability for most eyes in the same one-to-three-month range, with some, particularly higher prescriptions, continuing to shift toward six months.
Stability is the point at which the prescription measured at two visits a few weeks apart is essentially the same. It matters because two important decisions hang on it. The first is whether any residual prescription exists and, if so, whether glasses for specific tasks or a further laser enhancement might be discussed. Surgeons generally will not consider an enhancement until the measurements have stopped moving, because treating a still-healing cornea risks chasing a number that would have corrected itself. The second is the formal haze check, since the haze that matters clinically tends to peak in this window before slowly fading.
Dry eye symptoms often lag the visual recovery. The corneal nerves severed by epithelial removal regenerate slowly, and reduced nerve signaling means the eye does not always recognize it is dry. Many people continue lubricants well past the point where their vision satisfies them, and this is ordinary.
None of these timelines is a promise. Some people are sharp by week two and some are still noticing small changes at month five. Your follow-up schedule, typically day one, lens removal, one week, one month and three months, exists precisely to catch where you sit on that spread and to adjust care accordingly.
PRK vs LASIK recovery: is PRK as risky as LASIK?
People ask this question backwards more often than not. The honest answer is that PRK and LASIK carry different risk profiles rather than a simple more-or-less, and that the long-term visual results, according to the StatPearls review and MedlinePlus, are broadly comparable once healing is complete. What differs is the road, not the destination.
| Feature | PRK | LASIK |
|---|---|---|
| Corneal flap | None; surface layer removed and regrows | Hinged flap cut, lifted and replaced |
| Early discomfort | Moderate to significant for 2-3 days | Usually mild, hours to a day |
| Functional vision | Often 1-3 weeks; fluctuating | Often within 24-48 hours |
| Bandage contact lens | Worn about 3-5 days | Not usually needed |
| Flap-related complications | Not applicable | Possible: wrinkles, dislocation, ingrowth |
| Corneal haze | Small risk, mostly weeks to months out | Rare |
| Infection window | While epithelium is open | Brief; surface largely intact |
| Preferred when | Thinner cornea, trauma-prone activities | Adequate thickness, faster return needed |
Reading down the table, PRK front-loads its downsides: the pain, the days of blur and the open-surface infection window all arrive in week one. LASIK spreads its risks differently, with a smoother first week but a permanent flap interface. Neither column is a recommendation. Corneal thickness, prescription, lifestyle and the surgeon’s assessment decide which fits an individual eye, and that conversation belongs in the examination room.
How long to rest after PRK? Work, screens and TV
The rest most people actually need is concentrated in the first three to five days, the period the StatPearls review identifies as the epithelial healing window. During those days the eye is open to infection, uncomfortable in light and unable to focus, so the practical advice is simple: stay home, keep the room dim, sleep as much as you can, and let someone else handle driving and cooking.
Television sits in an odd place in people’s worries. Watching a screen does not damage the healing cornea; there is no mechanism by which light from a television slows epithelial growth. What it does is reduce your blink rate and hold your eyes open in one position, which dries the surface and feels miserable while the epithelium is raw. Most people find television intolerable on day one, tolerable in short stretches with the brightness turned down by day three or four, and normal once the lens is out and the sting has passed. Phones and laptops are similar but worse, because they sit closer and demand fine focus that the eye cannot yet deliver. Frequent lubricating drops, deliberate blinking and breaks every twenty minutes or so make screen time easier when your team says it is fine to resume.
Desk work is often possible after lens removal, sometimes with larger fonts and shorter days for the first week or two. Physically light exercise such as walking is usually permitted within days. Activities that risk sweat, water or debris in the eye are held back longer: the NHS advises avoiding swimming and contact sports for a period after laser eye surgery while the surface heals, and many surgeons ask for several weeks before pools, hot tubs, eye makeup or dusty environments. Your own clinic’s instructions override any general timeline here.
When can I drive after PRK, and is day five realistic?
Driving is the question with the least wiggle room, because it is governed by law as well as biology. In the United States, licensing standards vary by state, but most require corrected vision around the 20/40 level in at least one eye for an unrestricted daytime license. After PRK, you should drive only when your surgeon has measured your vision and confirmed you meet the standard that applies to you. Feeling that you can see well enough is not the test.
Day five, the date people ask about most, is genuinely borderline. The bandage lens has usually just come off, and as described earlier, vision often dips for a few days after removal while the new epithelium smooths. Some people do read a 20/40 line at that visit; many do not, or do so only in bright light with a good tear film. A surgeon who says not yet at day five is reporting a measurement, not being cautious for its own sake.
Night driving deserves its own timeline. Halos and glare around headlights are common in the early weeks because the newly healed surface scatters light and the pupil widens in the dark, sometimes beyond the treated zone. These effects typically shrink over the first one to three months as the cornea settles. Plenty of people are cleared for daytime driving well before they feel comfortable on an unlit highway, and it is reasonable to hold back at night until you do.
Practically, arrange rides for the surgery day, the day-one check and the lens-removal visit, and treat any clearance to drive as a starting point that still depends on how your eyes feel that particular morning.
Eye drops during PRK recovery: what each class does
A PRK drop regimen usually involves three or four bottles, each with a distinct job, and understanding the jobs makes the schedule easier to follow. Doses, timings and tapering belong to your prescriber; what follows is mechanism and typical purpose only.
Antibiotic drops are used while the epithelium is open and often until shortly after the bandage lens is removed. Their purpose is preventive: bacteria that normally sit harmlessly on the lid margin can colonize an exposed stroma, and the lens itself provides a surface for them. Once the epithelium has sealed, the risk falls sharply and the antibiotic is generally stopped.
Corticosteroid drops are the longest-running part of the regimen. They suppress the inflammatory wound-healing cascade that, left unchecked, can produce disorganized collagen and haze in the front of the stroma. Because they work on a process that unfolds over weeks, they are tapered gradually rather than stopped, commonly over one to several months depending on the surgeon’s assessment of haze risk. Steroids can raise eye pressure in susceptible people, which is one reason follow-up visits include a pressure check.
Non-steroidal anti-inflammatory drops are sometimes given for pain in the first days. They are effective but are kept short because prolonged use has been associated with slowed epithelial healing and, rarely, corneal thinning.
Lubricating drops, ideally preservative-free, are the workhorse. They rebuild the tear layer over the irregular surface, improve vision minute to minute and ease the dryness that follows nerve disruption. Many people use them for months. If any drop stings badly, seems to worsen redness or you are unsure whether to continue after the lens is out, ask the clinic before changing anything.
Dry eye, glare and halos: the side effects that linger
Three complaints tend to outlast the visual recovery itself, and each has a mechanism worth knowing so it can be recognized rather than feared.
Dry eye is the most common. Removing the epithelium also cuts the fine nerve endings that run through it, and those nerves do more than register pain: they drive the reflex that tells the tear glands to produce fluid and the lids to blink. With signaling reduced, the eye can be dry without feeling dry, and the tear film breaks up faster between blinks. Mayo Clinic describes this post-refractive-surgery dryness as usually improving over months as the nerves regrow, though for a minority it persists longer. Symptoms include burning, fluctuating blur that clears with a blink, and eyes that feel worse in wind, air conditioning or after screen use. Lubricants, humidifiers and deliberate blinking are the mainstays; anything beyond that is a conversation with your team.
Glare and halos, rings or starbursts around lights at night, arise when the healing surface scatters light and when the pupil in dim conditions opens wider than the treated zone. Both effects shrink as the epithelium smooths and the stroma remodels, typically over the first few months, and are more noticeable in people with larger pupils or higher corrections.
Undercorrection or regression, in which some prescription returns as the cornea heals, is possible, particularly with higher starting prescriptions. Visually significant corneal haze is uncommon with current techniques but is the complication surgeons watch for most closely in the one-to-three-month window. Whether any of these warrants further treatment is judged only after the prescription has been stable across visits, and glasses for specific tasks remain a reasonable option in the meantime.
What people often get wrong about the PRK recovery timeline
The first misunderstanding is treating LASIK stories as a benchmark. Friends who saw clearly the next morning had a flap procedure; the PRK recovery timeline is measured in weeks because the surface must regrow. Blur at day five is the expected course, not a failed operation.
The second is assuming that once the bandage lens is out, healing is over. The lens removal marks epithelial closure, which is the end of the infection-vulnerable phase, but the cells beneath are still thick and irregular, the stroma is still remodeling and the prescription is still drifting. Vision frequently dips right after removal before climbing.
A third error is equating pain with damage. The discomfort of days one to three reflects exposed nerve endings, not harm being done. The reverse also matters: an eye that feels comfortable can still be dry, because the nerves that would report dryness have been disrupted. Feeling normal is not the same as being healed.
People also stop steroid drops early because vision seems fine, or hoard lubricants for bad days only. The steroid schedule targets haze that has not appeared yet; the taper is the treatment. Lubricants work best used regularly while the surface is remodeling, not rationed.
Finally, there is a persistent belief that PRK is the inferior option chosen only when LASIK is impossible. Surgeons select PRK for thin corneas and trauma-prone lifestyles because it avoids a flap, and mainstream reviews report comparable long-term visual outcomes between the two. The trade is a harder first fortnight for the absence of a permanent flap interface. Whether that trade suits a given eye is a clinical judgement, and the timeline that follows is the price of the choice, not a sign the choice was wrong.
Questions to ask your care team
A good pre-operative consultation leaves you with a written plan and a phone number, not just a date. These questions help fill the gaps that patients most often say they wished they had asked.
- Why is PRK being suggested for my eyes rather than a flap procedure, and what in my corneal measurements drove that choice?
- Will both eyes be treated on the same day, and how will I manage at home if so?
- What is your usual day for removing the bandage contact lens, and what should I do if it falls out beforehand?
- How much pain should I expect on days one to three, what is the plan for managing it, and at what point does pain become a reason to call?
- Which drops am I being given, what does each one do, and for how long will the steroid taper run?
- Will you be applying mitomycin C during surgery, and what is your reasoning either way?
- When do you expect to measure my vision for driving, and what standard applies where I live?
- How many days off work do you recommend for someone in my job, and when can I return to screens, exercise, swimming and eye makeup?
- At what visit will you consider my prescription stable, and what happens if some prescription remains?
- How do you monitor for corneal haze and raised eye pressure, and how often will I be seen in the first three months?
- What is the out-of-hours contact route if I develop a red flag at night or over a weekend?
Write the answers down or ask for them in print. Your vision will be poor for the first several days, and instructions you cannot read are instructions you cannot follow. A family member at the consultation can help hold the details.
When to call your doctor
Most of the PRK recovery timeline is uncomfortable but benign. A small number of signs mean the ordinary course has been left and the clinic needs to hear from you the same day, or an emergency eye service if the clinic is closed.
Pain that worsens after the third or fourth day, rather than easing, is the most important. The expected arc is peak discomfort in the first two to three days and then relief as the epithelium closes; a reversal can signal infection or a surface that has not healed. Increasing redness, thick or colored discharge, or a lid that is swollen and hot points the same way. A new white or gray spot on the cornea, visible in a mirror, warrants an urgent same-day examination because it may represent an infiltrate, an area where infection or inflammation has taken hold in the stroma.
A sudden drop in vision after a period of improvement is not part of normal fluctuation and should be reported. So should the bandage lens falling out, becoming displaced or feeling suddenly very scratchy, since the surface beneath may still be open. Extreme light sensitivity that returns after having faded, a sensation that something is stuck in the eye that does not settle with lubricants, or any direct blow or splash to the eye in the first weeks are all reasons to call.
Flashes of light, a curtain over part of the vision or a sudden shower of floaters are not typical PRK effects at all and require urgent assessment regardless of the surgery. If in doubt about whether a symptom counts, call anyway; eye teams would rather hear about a false alarm at hour one than a real problem at day three.
Frequently asked questions
How long to rest after PRK?
Most people need about three to five days of genuine rest, matching the time the corneal epithelium takes to regrow according to peer-reviewed reviews. During those days vision is blurry, light hurts and the eye is open to infection, so staying home in a dim room is sensible. Desk work often resumes after the bandage lens is removed, while swimming, contact sports and dusty environments are usually held back for several weeks on your surgeon’s instruction.
Is PRK as risky as LASIK?
PRK and LASIK carry different risks rather than one being clearly riskier. PRK involves more early pain, a longer blurry period and a brief infection window while the surface is open, plus a small risk of corneal haze. LASIK has a smoother first week but creates a permanent flap that can wrinkle, dislodge or develop cell ingrowth. Mainstream reviews report comparable long-term visual outcomes, and the choice depends on corneal thickness, prescription and lifestyle.
Can I drive 5 days after PRK?
Only if your surgeon has measured your vision at that visit and confirmed it meets the legal standard where you live, which in most US states is around 20/40 in at least one eye. Day five usually falls just after bandage lens removal, when vision often dips temporarily, so many people are not yet there. Night driving typically comes later still because halos and glare take weeks to months to fade.
How long after PRK can I watch TV?
Television does not harm the healing cornea, so the question is comfort rather than safety. On the first day or two the raw surface makes any screen unpleasant and reduces blinking, which dries the eye. Most people manage short stretches with the brightness lowered by day three or four and watch normally once the bandage lens is out. Use lubricating drops, blink deliberately and stop when it stings, following your clinic’s specific advice.
When is the bandage contact lens removed after PRK?
Usually between the third and fifth day, once the surgeon confirms with fluorescein dye under the slit lamp that the epithelium has fully closed. The lens is a non-prescription soft lens that acts as a dressing, protecting the healing surface and reducing pain. It is removed in the clinic in seconds. If it falls out or shifts before your visit, call the clinic rather than reinserting it or waiting.
Why is my vision worse after the bandage lens came off?
The lens had been smoothing over an uneven surface. Once removed, the newly regrown epithelium, which is thicker and more irregular than mature tissue, meets the tear film directly and scatters light, so letters blur or double for a few days. This dip is a normal part of the PRK recovery timeline and typically improves through the second week as the cells reorganize. A sudden, marked drop in vision or new pain is different and should be reported.
How long does PRK pain last?
Significant discomfort typically lasts two to three days, peaking around the second day while the epithelium is still open, then easing noticeably as the last gap closes. People describe grittiness, burning, light sensitivity and watering rather than sharp pain. Pain that increases after day three or four, or returns after settling, is not expected and warrants a same-day call, since it can signal infection or a surface that has not healed.
What is PRK recovery like day by day in the first week?
Day zero is cloudy but often comfortable while numbing drops last. Days one to three bring the peak of grittiness, light sensitivity and tearing as the epithelium regrows. Around days three to five the bandage lens is removed, often followed by a short dip in vision. By the end of week one most people are more comfortable, with vision that fluctuates through the day and is usable around the house but not yet sharp.
When does vision stabilize after PRK?
For most eyes the prescription settles between about one and three months after surgery, with higher corrections sometimes continuing to shift toward six months, according to peer-reviewed reviews and MedlinePlus. Stability means the measurement is essentially unchanged across two visits a few weeks apart. Surgeons wait for that point before judging the final result, discussing task-specific glasses or considering any enhancement, because treating a still-changing cornea risks overcorrecting.
Can I use my phone after PRK?
Phones are safe for the cornea but harder to tolerate than television because they sit close and demand fine focus the healing eye cannot yet deliver. Expect the first two or three days to be largely phone-free, then short sessions with enlarged text and brightness turned down once the sting fades. Lubricating drops, frequent blinking and breaks every twenty minutes ease the dryness that screens cause. Follow your clinic’s timeline for returning to sustained screen work.
References
- MedlinePlus: Photorefractive keratectomy (PRK)
- MedlinePlus: Laser Eye Surgery
- NIH National Library of Medicine (StatPearls): Photorefractive Keratectomy
- NHS: Laser eye surgery and lens surgery
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Dry vs Wet Macular Degeneration: How Each Form Progresses and Why Treatment Plans Differ
Dry macular degeneration is the slow form: waste deposits called drusen and thinning of the retina's light-sensing cells gradually blur central vision over years,…

Chalazion Surgery Recovery: Bruising, Ointment and When Makeup and Contacts Return
Chalazion surgery recovery is usually brief. Most people wear a pad over the eye for a few hours, use a prescribed antibiotic eye ointment…
Visual Field Tests and Optic Nerve Scans in Glaucoma: What the Results Tell Your Doctor
A glaucoma visual field test maps how well each eye sees across its whole field, especially at the edges where glaucoma usually starts. An…

Which Eye Surgery Treats Which Problem? Cataract, Laser, Glaucoma, Retina and Cornea Explained
Different eye surgeries treat different parts of the eye. Cataract surgery replaces a clouded natural lens; laser vision correction reshapes the cornea to reduce…

Is Cataract Surgery Painful? Numbing Drops, Sedation and What You Actually Feel
Cataract surgery is not usually painful. The eye is numbed with anesthetic drops or gel, sometimes with a small injection around the eye, and…

Why a Tear Duct Gets Blocked: How Watering, Discharge and Repeat Infections Develop
A tear duct becomes blocked when the narrow drainage channel from the inner corner of the eye into the nose fails to open at…