

What a Skin Cancer Biopsy Report Tells Your Team and How It Shapes Treatment
Key Takeaways
- Breslow thickness, the depth of a melanoma in millimeters, is the single most influential line on a melanoma report and sets the width of the follow-up excision.
- Ulceration seen under the microscope moves a melanoma into a higher risk group at every thickness, which is why it sits beside Breslow depth in staging.
- A positive margin on a diagnostic punch or shave biopsy is expected and simply tells the surgeon where to cut; it is not a sign the procedure failed.
- Sentinel lymph node biopsy is usually discussed for melanomas thicker than about 1 mm, or thinner ones with ulceration, and is a staging test rather than a treatment.
- For basal cell carcinoma, an infiltrative, morpheaform or micronodular subtype, or a central facial location, is the usual reason Mohs surgery is considered.
- Formal stage is assigned only after the definitive excision and any node sampling, so the first biopsy report gives a provisional picture that can change.
A skin cancer biopsy report names the cancer type (most often basal cell carcinoma, squamous cell carcinoma or melanoma), describes how deeply it grows, whether its surface is ulcerated, how fast its cells are dividing and whether the edges of the sample are clear. Your treating team uses these findings, along with your overall health, to decide whether further surgery, lymph node assessment, imaging or simple monitoring comes next.
The envelope, or more often the patient-portal notification, arrives before the appointment does. You open it on your phone in a parking lot and meet a wall of words: nodular, Breslow, mitoses, margins, perineural. Somewhere in that paragraph is the answer to the only question you actually have, and it is written in a language you were never taught.
That gap is what this guide closes. Think of it as skin cancer biopsy results explained by a colleague who has read thousands of these reports and knows which lines change the plan and which are routine description. Pathologists write for surgeons and oncologists, not for the person whose skin it was, so the report rewards a translator.
One reassurance up front: a long report is not a worse report. Detail is how a pathologist shows their work. The sections below walk through that work in the order your care team reads it, and explain how each finding nudges the treatment conversation.
How a skin cancer biopsy works, from your skin to a microscope slide
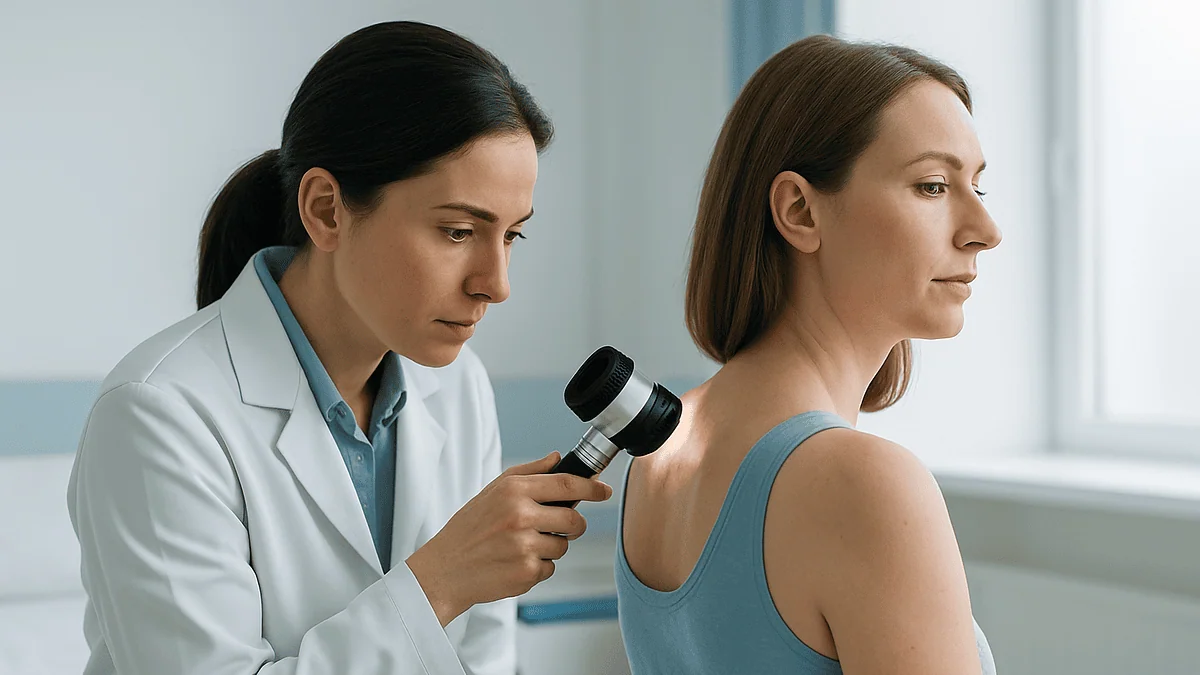
A skin biopsy is the removal of a small piece of skin so that a pathologist, a doctor who diagnoses disease by examining tissue, can look at it under a microscope. The clinician numbs the area with a local anesthetic and takes the sample in one of three main ways: a shave biopsy, which slices off the surface and upper dermis; a punch biopsy, which uses a small circular blade to remove a full-thickness cylinder; or an excisional biopsy, which cuts out the whole visible lesion with a rim of normal skin. MedlinePlus describes each of these as an outpatient procedure that usually takes minutes.
What happens next is where the report is born. The tissue is fixed in preservative, embedded in paraffin wax, sliced into sections a few thousandths of a millimeter thick and stained so that cell nuclei and surrounding structures show up in contrast. The pathologist studies these sections, measures what needs measuring and, when the cells are ambiguous, orders immunohistochemistry: special stains that tag proteins specific to pigment cells or to squamous cells, helping confirm which cell line the tumor came from.
The method of biopsy matters for interpretation. A shave biopsy can leave the deepest part of a melanoma in the skin, so a thickness measured on a shave may be labeled “at least” rather than a final figure. A punch gives depth but may miss the widest edge. Your team already knows this, and it is one reason a second, wider procedure is so often planned after a diagnosis rather than being a sign something went wrong the first time.
Results are typically available within days to a few weeks, depending on whether extra stains were needed, according to MedlinePlus and the NHS.
Skin cancer biopsy results explained: the three main diagnoses and what each means
The first line that matters is the diagnosis itself. The Mayo Clinic and the CDC describe three cancers that account for the large majority of skin cancer diagnoses, and your report will almost always name one of them.

Basal cell carcinoma, or BCC, arises from the cells at the base of the epidermis. It grows slowly, rarely spreads to distant organs and is treated mainly to stop local tissue damage. A BCC report focuses on growth pattern and whether the edges are clear.
Squamous cell carcinoma, or SCC, comes from the flat cells that make up most of the epidermis. It is usually confined to the skin but carries a real, if modest, capacity to reach lymph nodes, particularly when it is large, deep, poorly differentiated or growing along nerves. An SCC report therefore spends more words on depth, differentiation and nerve involvement.
Melanoma begins in melanocytes, the pigment-producing cells, and is the diagnosis with the most consequential report, because its potential to spread is closely tied to measurable features. A melanoma report is the longest and most structured of the three.
You may also see precursor terms. “Actinic keratosis” is a sun-damaged patch that can precede SCC. “Squamous cell carcinoma in situ” (Bowen disease) and “melanoma in situ” describe cancer cells confined entirely to the epidermis, with no invasion into the dermis below. In situ disease is still treated, usually by complete removal, but has essentially no route to the bloodstream or lymph nodes while it stays where it is.
Rarer entities, such as Merkel cell carcinoma or dermatofibrosarcoma protuberans, follow their own pathways; if one of those appears on your report, the sections below apply only in outline, and your team will walk you through the specifics.
How to read a melanoma pathology report line by line
Melanoma reports follow a near-standard template, which helps once you know the order. Here is what each element records and why it is there.
- Histologic subtype (superficial spreading, nodular, lentigo maligna, acral lentiginous, others): a description of growth pattern. Subtype matters less for treatment than depth, though it can hint at behavior.
- Breslow thickness: the vertical distance in millimeters from the top of the granular layer of the epidermis to the deepest cancer cell. This is the single most influential measurement, covered in detail in the next section.
- Ulceration: whether the skin surface over the tumor has broken down under the microscope, not simply whether it looked scabbed. Ulceration moves a tumor into a higher risk group at every thickness, per the National Cancer Institute’s staging summary.
- Mitotic rate: the number of dividing cells per square millimeter. A higher rate suggests faster growth. It no longer changes formal stage for thin melanomas but still informs judgment.
- Clark level: an older scale (I to V) describing which skin layer the tumor reached. Most modern guidelines treat it as secondary to Breslow thickness, and some laboratories omit it.
- Lymphovascular invasion: cancer cells seen inside small blood or lymph vessels, a sign the tumor has found a transport route.
- Regression: areas where the immune system appears to have attacked and partly cleared the tumor. Its meaning is debated and it rarely changes a plan on its own.
- Microsatellites: tiny nests of melanoma separate from the main tumor, which do affect stage.
- Margins: whether cancer reaches the edge of the removed tissue.
Read these as a set, not individually. A thin melanoma with no ulceration and clear margins is one story; the same thickness with ulceration and a positive deep margin is a different one, and your team’s plan will reflect that difference.
What does Breslow thickness mean and why does it drive the plan?
Breslow thickness is the strongest single predictor of how a melanoma is likely to behave, which is why it anchors the staging system published by the American Joint Committee on Cancer and summarized by the National Cancer Institute. The logic is anatomical: the deeper a tumor grows, the closer it sits to the dermal blood and lymph vessels that could carry cells elsewhere.

The NCI patient summary describes how thickness and ulceration combine to define early stages:
| Stage group | Breslow thickness | Ulceration | What it usually prompts |
|---|---|---|---|
| Stage 0 (in situ) | Confined to epidermis | Not applicable | Complete excision with a narrow margin |
| Stage IA | Less than 0.8 mm | Absent | Wider excision; lymph node sampling rarely needed |
| Stage IB | 0.8–1.0 mm, or 1.0–2.0 mm | Present at under 0.8 mm counts here; absent for 1–2 mm | Wider excision; discussion of sentinel node biopsy |
| Stage IIA | 1.0–2.0 mm with ulceration, or 2.0–4.0 mm without | Varies | Wider excision plus sentinel node biopsy discussion |
| Stage IIB–IIC | 2.0–4.0 mm with ulceration, or over 4.0 mm | Varies | Wider excision, node assessment, possible referral to medical oncology |
A few cautions keep this table honest. Stage is finalized only after the wide excision and, if performed, lymph node sampling, so the number in your first report may be revised. A shave biopsy can underestimate thickness if the tumor extended below the cut. And staging predicts the behavior of groups of people, not the course of any one person, which is why no reputable clinician will translate a millimeter figure into a personal forecast.
If you remember one line from the whole report, make it the Breslow thickness and whether ulceration was present or absent. Those two words shape most of what follows.
Basal cell and squamous cell carcinoma reports: the lines that change management
Non-melanoma reports are shorter, but they still contain features that decide between a simple excision and something more involved. The Mayo Clinic’s overview of basal cell carcinoma and the NCI’s summary of skin cancer treatment both describe the characteristics teams watch for.
For basal cell carcinoma, the report names a growth pattern. Nodular and superficial subtypes are the common, well-behaved ones. Infiltrative, morpheaform (sclerosing) and micronodular patterns send thin strands of tumor beyond what is visible, so they are more likely to leave cells behind after a standard excision. These “aggressive-pattern” labels, together with a location on the central face, ears or around the eyes, are the usual triggers for considering Mohs micrographic surgery: a technique in which the surgeon removes tissue in thin layers and checks each layer under the microscope the same day, continuing only where cancer remains.
For squamous cell carcinoma, your team reads differentiation (well, moderately or poorly differentiated, describing how closely cells resemble normal skin cells), depth of invasion into or beyond the dermis, tumor diameter, and whether cancer tracks along nerves (perineural invasion) or into vessels. Poorly differentiated, deep or perineural tumors are classified as higher risk, and the report may prompt an examination of nearby lymph nodes or imaging. People whose immune systems are suppressed, for instance after an organ transplant, are followed more closely because SCC behaves more aggressively in that setting, as the NCI notes.
A finding of “actinic keratosis with focal squamous cell carcinoma in situ” means the sun-damaged patch has progressed at one spot but remains in the epidermis. It is treated, but the stakes are different from invasive disease.
In both cancers, the margin status (next section) often matters more than any descriptive adjective.
Positive margins in skin cancer: what "involved", "close" and "clear" really mean
A margin is the edge of the tissue that was removed. The pathologist inks these edges before slicing, then reports whether cancer cells touch the ink. Three outcomes appear on reports.
Clear (negative) margins mean no tumor reaches the edge, and the report may state the distance in millimeters from the nearest cancer cell. Close margins mean tumor sits within a short distance of the edge without touching it; what counts as “close” depends on the cancer type and local protocol. Positive (involved) margins mean cancer extends to the edge, which implies cells probably remain in the skin.
Here is the part that surprises people: a positive margin on a diagnostic biopsy is often expected, not alarming. A punch or shave is designed to sample, not to remove with a safety zone. The NCI explains that melanoma treatment nearly always includes a wide local excision, a second operation removing a measured rim of normal-looking skin around the biopsy site, with the width of that rim set by Breslow thickness. The margin on the first biopsy therefore tells the surgeon where to cut, not whether to.
A positive margin after a definitive excision is a different matter. For basal and squamous cell carcinoma, it usually leads to further surgery, Mohs or, in selected cases where surgery is not suitable, radiation therapy. Some well-defined, low-risk basal cell carcinomas with a marginally involved edge are monitored rather than re-excised, a judgment the treating team makes using the subtype, site and the person’s wishes.
Which margin matters also varies. A positive deep margin on a melanoma shave is particularly significant because it means the true thickness is unknown. A positive lateral margin on a superficial BCC may simply mean a slightly wider excision is planned.
Who is usually offered further surgery or node testing, and who is asked to wait
Once the report is in, the team sorts findings into pathways. The decision always rests with them, but the broad patterns, drawn from the NCI treatment summaries and Mayo Clinic guidance, are predictable enough to describe.
Likely to be offered wide local excision alone: melanoma in situ and thin invasive melanomas without ulceration, most basal cell carcinomas, and low-risk squamous cell carcinomas. The goal is a clear margin, and for most people this is the only treatment required.
Likely to be offered a conversation about sentinel lymph node biopsy: people with melanoma thicker than about 1 mm, and those between roughly 0.8 and 1 mm when ulceration or other adverse features are present, according to the NCI and Mayo Clinic. A sentinel node biopsy identifies the first lymph node that drains the tumor site, using a tracer, and removes it for examination. It is a staging tool; whether a positive node leads to further treatment is a separate discussion.
Likely to be offered Mohs surgery: aggressive-pattern or recurrent basal cell carcinoma, high-risk squamous cell carcinoma, and tumors on the face where sparing normal tissue matters.
Likely to be asked to wait or to be monitored: people whose report shows a benign or atypical lesion, where the next step is a planned skin check rather than surgery; those with a small, low-risk BCC fully removed by the biopsy itself; and, occasionally, people with other serious health conditions for whom the risks of a larger procedure outweigh the slow threat of a small tumor.
Where risk is higher, the NCI notes that imaging such as CT or PET is reserved for melanoma that has reached lymph nodes or shows symptoms, not for thin early tumors, where scans tend to generate false alarms rather than useful information.
How the biopsy report shapes treatment decisions in the clinic
The report rarely travels alone to the decision. In most cancer services, melanoma and complex non-melanoma cases are reviewed at a multidisciplinary meeting, where dermatologists, surgeons, pathologists, oncologists and specialist nurses look at the slides, the clinical photographs and the person’s health history together. The NHS describes this team approach as standard for melanoma.
Three questions dominate that conversation. First, is the diagnosis secure, or do the slides need a second pathologist or extra stains? Second, how much tissue still needs to come out, and by what technique? Third, does anything in the report suggest the cancer may have moved, and if so, how should that be checked?
The report answers the second and third questions in a fairly mechanical way. Breslow thickness sets the width of the melanoma excision margin, as the NCI explains. Ulceration and thickness together determine whether sentinel node biopsy is raised. For SCC, perineural invasion and poor differentiation move a tumor into a high-risk category that prompts closer follow-up or node examination. For BCC, subtype and site decide between standard excision and Mohs.
What the report cannot do is weigh your preferences, your other illnesses, your tolerance for a second procedure or a scar in a visible place, and your views about node testing whose main value is information rather than treatment. Those are your contributions to the meeting, delivered through your clinician.
For the small proportion of people whose melanoma has reached lymph nodes or beyond, the report also feeds molecular testing of the tumor for mutations, such as those in the BRAF gene, which can determine eligibility for targeted drug classes and immunotherapy. Those options, their timelines and their side effects are a conversation for the oncology team and depend on far more than the pathology report alone.
Skin biopsy results time: what the days and weeks after your biopsy usually look like
The waiting period is often the hardest stretch, so it helps to know what is normal.
The first few days. The biopsy wound is covered with a dressing; a punch site may have a stitch or two, a shave site heals as an open graze. MedlinePlus advises keeping the area clean, expecting mild soreness and a small amount of oozing, and watching for signs of infection, which are covered in the red-flag section below.
Days to a few weeks. The tissue is processed and read. MedlinePlus and the NHS both describe results arriving within days to a few weeks, with the longer end usually reflecting extra stains, a second pathologist’s opinion or a laboratory backlog. A delay in this window is far more often administrative than ominous.
The results appointment. This is when the report is translated and the plan outlined. Many services schedule it as a face-to-face or video visit rather than a letter precisely because the language needs interpreting.
The following weeks. If a wide local excision is recommended, it is usually arranged within weeks of the results, often with a sentinel node biopsy under the same anesthetic when indicated. Non-melanoma excisions follow a similar rhythm. Healing from a wider excision takes longer than from the biopsy, with sutures typically removed within one to two weeks depending on body site, per MedlinePlus.
Second report. The excised tissue generates another pathology report, confirming margins and finalizing stage. For many people this second report is the one that closes the active treatment chapter.
These are typical ranges from published patient guidance, not commitments. Local pathways, laboratory capacity and your own health all shift the timeline, and your team is the only source for dates that apply to you.
When the report is uncertain: atypical lesions, second opinions and molecular tests
Not every report delivers a clean answer. Some of the most anxious phone calls follow phrases like “atypical melanocytic proliferation”, “dysplastic nevus with severe atypia” or “melanocytic lesion of uncertain malignant potential”. Each describes a cluster of pigment cells that does not look fully benign and does not meet the criteria for melanoma either.
Honesty about the evidence matters here. Distinguishing an unusual mole from an early melanoma is one of the genuinely difficult tasks in pathology, and studies summarized by the NCI and in the PubMed literature show that experienced pathologists sometimes disagree on borderline cases. That is not a failing of your laboratory; it reflects a real biological gray zone.
Teams respond in several ways. The most common is complete excision of the lesion with a narrow margin, which both removes the uncertainty and provides the whole lesion for examination. A second opinion from a dermatopathologist, a pathologist with additional training in skin disease, is routine in many services and is reasonable to request. Immunohistochemistry stains can add information about cell maturation and proliferation.
Molecular tests are increasingly offered. Some examine chromosomal changes to help classify an ambiguous lesion; others measure gene expression in a confirmed melanoma to estimate risk of spread. The evidence for the first group is reasonably established as a diagnostic aid. The second group is more contested: prognostic gene expression tests have not yet been shown in prospective trials to improve outcomes when used to change surgery or follow-up, and major guidelines describe them as not routinely recommended for staging decisions. If one is proposed, it is fair to ask what decision the result would change.
An uncertain report is unsettling, but it tends to lead to a cautious plan, which is the safer direction to err in.
What people often get wrong about skin cancer biopsy results
A few misunderstandings come up so often that they deserve direct correction.
“A biopsy can spread the cancer.” There is no good evidence that cutting into a skin cancer seeds it elsewhere, and biopsy before treatment is standard practice recommended by the NCI, Mayo Clinic and NHS precisely because knowing the diagnosis improves the plan. Skipping biopsy to “avoid disturbing it” leaves the team operating blind.
“Positive margins mean the surgeon failed.” On a diagnostic punch or shave, involved margins are expected. The purpose of that sample was to answer “what is it?”, not “is it all gone?”. The wide excision that follows is planned, not corrective.
“Stage comes from the first biopsy.” Formal stage is assigned after the definitive excision and, where done, lymph node sampling. The first report gives a provisional picture that may be revised.
“Melanoma is always dark, and dark always means melanoma.” Some melanomas have little or no pigment (amelanotic), and many heavily pigmented lesions are benign. Only the microscope settles it, which is why self-diagnosis from color is unreliable in either direction.
“A thin melanoma is nothing to worry about.” Thin melanomas are usually managed with surgery alone and have a favorable outlook as a group, but they still require complete excision and ongoing skin surveillance. “Low risk” is not “no risk”.
“A clear report after excision means I am done with skin cancer.” Having one skin cancer raises the chance of developing another, as the CDC and Mayo Clinic both note. Follow-up skin examinations and sun protection remain part of care, not an optional extra.
“Scans are the thorough option.” For early-stage disease, whole-body imaging more often finds incidental, unrelated findings that trigger anxiety and further tests than it finds spread. Guidelines reserve scans for higher-risk or symptomatic situations.
Questions to ask your care team about your biopsy report
Bringing a short written list to the results appointment changes the quality of the conversation. These questions are the ones that most reliably unlock useful answers.
- What exactly is the diagnosis, and how confident is the pathologist? Was a second pathologist or special stain involved?
- If this is melanoma, what is the Breslow thickness, and was ulceration present? Was the thickness measured on a complete sample, or could the true depth be greater?
- What is the provisional stage, and what would change it?
- Were the margins clear, close or involved, and which edge? Does that matter given the biopsy method used?
- What is the recommended next step, and what are the alternatives, including doing less?
- If a wide excision is planned, how wide a margin, and what will the scar be like at this site?
- Is sentinel lymph node biopsy being considered? What would a positive result change in my treatment, and what would a negative result tell us?
- Are any molecular or genetic tests being proposed on the tissue? What decision would the result inform?
- Do I need any imaging or blood tests, and if not, why not?
- How will I be followed up, how often, and for how long?
- Should my close relatives be aware of anything, given this diagnosis?
- Who do I contact if I notice something new before my next appointment?
It is reasonable to ask for a copy of the full pathology report and to request that the team mark the lines that drove their recommendation. Many people find it helpful to bring someone to the appointment to listen and take notes, since detail tends to blur under stress.
If anything in the plan is unclear after the visit, a follow-up message or call to the specialist nurse is an ordinary part of care, not an imposition.
When to call your doctor: red-flag signs after a skin biopsy or diagnosis
Most biopsy sites heal uneventfully, and most skin cancers are managed without complication. A small number of situations do need prompt contact with your team, and MedlinePlus and the Mayo Clinic describe them consistently.
Contact your clinician the same day, or seek urgent care, if you notice:
- Bleeding from the biopsy or excision site that does not stop after firm pressure for 15 to 20 minutes.
- Spreading redness, increasing warmth, swelling or pus at the wound, especially with fever or chills, which can indicate infection.
- Pain that worsens after the first two or three days rather than easing.
- Wound edges that open or sutures that come loose before the planned removal.
- Signs of an allergic reaction to a dressing or topical product, such as blistering or intense itching around the site.
Separately from wound healing, tell your team without waiting for a scheduled appointment if you notice:
- A new lump near the original site, along the path toward the nearest lymph nodes, or in the neck, armpit or groin.
- A pigmented spot or nodule appearing in or beside the scar after excision.
- Any mole or skin lesion that is changing in size, shape or color, bleeding, or failing to heal over several weeks.
- Unexplained persistent symptoms such as weight loss, bone pain, headaches or breathlessness, which are rarely related but should always be assessed in someone with a cancer diagnosis.
This is not a checklist for diagnosing yourself. It is a prompt to pick up the phone, which is always the correct response to uncertainty. Your care team would rather hear about a false alarm than miss something treatable, and every decision about what to do next belongs to them.
After treatment: how your report guides follow-up and future skin checks
The final pathology report does not retire once treatment ends. It becomes the reference document that sets the rhythm of your follow-up.
Thickness, ulceration and node status determine how often you are seen and for how long. The NCI and NHS describe surveillance that is more frequent in the first few years after a melanoma diagnosis, when recurrence is most likely, then tapers. Thin melanomas without adverse features generally involve less intensive schedules than thicker or node-positive disease. For basal and squamous cell carcinoma, follow-up focuses on the treated site and on detecting new primary cancers, which the Mayo Clinic notes are common in people who have had one.
Visits typically involve a full skin examination and, for higher-risk melanoma, palpation of lymph node regions. Routine blood tests and imaging in people with no symptoms are not recommended for early-stage disease by the NCI, because they rarely detect recurrence earlier than examination does and often generate false positives.
Between visits, the report shapes your own role. Knowing where the original lesion was, which node basin drained it and what the team is watching for turns vague vigilance into a specific monthly check of the scar, the surrounding skin and the relevant lymph node areas. Photographs taken at diagnosis and after excision give you and your clinician a baseline.
Sun protection is the one intervention with consistent evidence for reducing future skin cancers, as the CDC summarizes: shade in the middle of the day, clothing and hats, and broad-spectrum sunscreen reapplied as directed. It is protective rather than punitive; a prior diagnosis is not a verdict on past behavior.
Keep a copy of every pathology report. If you move, change clinicians or develop a new lesion years later, those few paragraphs, once so hard to read, become the most useful pages in your medical history.
Frequently asked questions
How long does it take to get skin biopsy results?
Typically within days to a few weeks, according to MedlinePlus and the NHS. The longer end of that range usually reflects extra immunohistochemistry stains, a second pathologist’s review of an ambiguous lesion or laboratory workload, rather than anything about the severity of the finding. If your results are overdue, a call to the clinic that performed the biopsy is appropriate.
What does Breslow thickness mean on my melanoma report?
Breslow thickness is the vertical depth of the melanoma in millimeters, measured from the top of the skin’s granular layer to the deepest cancer cell. It is the strongest predictor of how a melanoma is likely to behave and anchors the staging system described by the National Cancer Institute. Thicker tumors sit closer to vessels that could carry cells elsewhere, so they prompt wider excision and discussion of lymph node testing.
Does a positive margin on a skin cancer biopsy mean the cancer was not removed?
On a diagnostic punch or shave biopsy, yes, cancer cells likely remain, and that is expected, because the sample was taken to identify the lesion rather than remove it with a safety zone. The planned wide excision addresses this. A positive margin after a definitive excision is different and usually leads to further surgery, Mohs or occasionally radiation, as decided by your team.
Can a skin biopsy spread cancer?
There is no good evidence that biopsy spreads skin cancer, and biopsy before treatment is standard practice recommended by the National Cancer Institute, Mayo Clinic and NHS. Knowing the exact diagnosis, depth and features allows a precise plan. Delaying or avoiding biopsy to “leave it alone” removes the information the team needs and can allow a tumor to grow undetected.
How do I read a melanoma pathology report if I only have a minute?
Find three things: the Breslow thickness, whether ulceration is present or absent, and the margin status. Those lines drive most decisions. Then look for lymphovascular invasion or microsatellites, which raise concern if present. Subtype, Clark level and regression are descriptive and rarely change the plan on their own. Bring the report to your results appointment and ask your clinician to confirm your reading.
What is the difference between melanoma in situ and invasive melanoma?
Melanoma in situ means the cancer cells are confined entirely to the epidermis, the outermost skin layer, with no invasion into the dermis below. Because the epidermis has no blood or lymph vessels, in situ disease has essentially no route to spread while it stays there. It is still treated by complete excision. Invasive melanoma has crossed into the dermis and is staged by its Breslow thickness.
Why was I offered a sentinel lymph node biopsy and what will it change?
Sentinel node biopsy is usually discussed when a melanoma is thicker than about 1 mm, or between roughly 0.8 and 1 mm with ulceration or other adverse features, per the National Cancer Institute and Mayo Clinic. It identifies and removes the first lymph node draining the tumor to check for cancer cells. Its main value is more accurate staging; whether a positive result leads to further treatment is a separate discussion with your team.
What does an atypical or dysplastic nevus with severe atypia mean?
It describes a mole whose cells look unusual under the microscope but do not meet the criteria for melanoma. This is a genuine gray zone where experienced pathologists sometimes disagree. Teams commonly respond by excising the lesion completely with a narrow margin and, in some services, seeking a dermatopathologist’s second opinion. The result is uncertainty resolved by a cautious plan rather than a cancer diagnosis.
Will I need scans after a skin cancer diagnosis?
For early-stage melanoma and most basal or squamous cell carcinomas, the National Cancer Institute does not recommend routine imaging in people without symptoms, because scans rarely find spread at that stage and often produce false alarms. Imaging is reserved for melanoma that has reached lymph nodes, high-risk squamous cell carcinoma or new symptoms. Your team will explain the reasoning either way.
What are the red-flag signs after a skin biopsy that mean I should call?
Bleeding that does not stop with 15 to 20 minutes of firm pressure, spreading redness, warmth, swelling or pus at the wound, fever, worsening pain after the first few days, or a wound that opens. Separately, report any new lump near the site or in the neck, armpit or groin, a new pigmented spot in the scar, or any changing skin lesion. When unsure, calling is always the right move.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Infection Risk During Multiple Myeloma Treatment: Vaccines, Precautions and Urgent Signs
Multiple myeloma raises infection risk in two ways: the disease itself suppresses normal antibody production, and treatments such as steroids, proteasome inhibitors, anti-CD38 antibodies,…

Infection Precautions During Acute Lymphocytic Leukemia Treatment and Why Fever Is Urgent
During acute lymphocytic leukemia treatment, chemotherapy lowers neutrophils, the white cells that fight bacteria, so ordinary germs can become serious within hours. Careful hand…

The Low-Iodine Diet Before Radioiodine Treatment: What to Eat and What to Avoid
A low-iodine diet before radioiodine treatment lowers the iodine in your body so thyroid tissue takes up more of the radioactive iodine. It is…
Is a Second Opinion Worth Seeking for a Testicular Cancer Plan? What to Ask First
A second opinion is usually reasonable before a testicular cancer plan begins, and most care teams expect the request. It is most useful when…

Tingling and Dizziness After Therapeutic Apheresis: Why They Happen and What to Report
Tingling and dizziness after therapeutic apheresis are usually short-lived and traceable to two mechanisms: citrate, the anticoagulant that keeps blood from clotting in the…

Gastrectomy for Stomach Cancer: Partial or Total Removal and How Digestion Is Rerouted
A gastrectomy for stomach cancer removes part of the stomach (partial or subtotal gastrectomy) or all of it (total gastrectomy), together with nearby lymph…