

Abdominal and Carotid Ultrasounds: What Each Scan Screens For
Key Takeaways
- A complete abdominal ultrasound surveys six structures — liver, gallbladder, pancreas, spleen, kidneys, and aorta — in roughly 30 to 60 minutes with zero radiation.
- Fasting 8 to 12 hours beforehand keeps the gallbladder full and reduces bowel gas, which is why eating breakfast is the top reason these scans get rescheduled.
- The NHS offers men a one-time aortic aneurysm ultrasound at age 65 because aneurysms grow silently and elective repair is far safer than emergency surgery after rupture.
- Carotid ultrasound estimates artery narrowing from blood speed: like water through a pinched hose, flow accelerates through a plaque-narrowed segment, and Doppler measures that acceleration.
- Routine carotid screening isn't recommended for symptom-free, low-risk adults — in that group it produces more false alarms than dangerous disease.
- On your report, 'anechoic' usually means harmless fluid, 'shadowing' usually means a stone, and 'unremarkable' is radiology's way of saying normal.
An abdominal ultrasound uses sound waves to examine the liver, gallbladder, pancreas, spleen, kidneys, and abdominal aorta, detecting problems such as gallstones, cysts, fluid buildup, and aortic aneurysms. A carotid ultrasound examines the two large neck arteries for plaque and narrowing that raise stroke risk. Both scans are painless, use no radiation, and typically take 30 to 45 minutes each.
The first surprise is always the gel. It arrives cold, in a generous ribbon across your skin, and then a small handheld wand starts gliding through it while a grainy gray landscape flickers on a screen. Somewhere in that shifting static, a trained eye is reading your liver the way a sailor reads weather.
Ultrasound is the workhorse of medical imaging — the same physics that lets bats navigate a dark cave, borrowed to look inside the human body without a single ray of radiation. Two of its most common assignments sit at opposite ends of the torso: the belly and the neck.
They get confused constantly, and that’s understandable. Same machine, same gel, same dimmed room. But the two scans answer very different questions, and knowing which is which helps you understand what your doctor is actually looking for — and what the results can and cannot tell you.
What can be detected on an abdominal ultrasound?
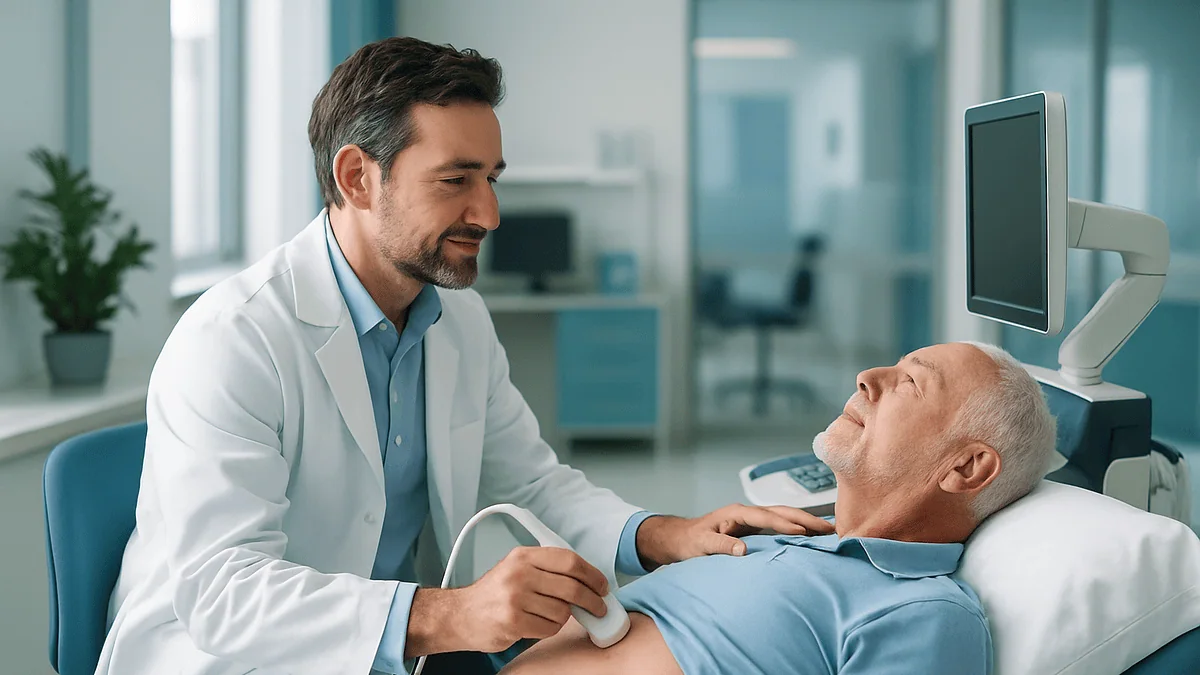
A complete abdominal ultrasound is essentially an organ-by-organ tour of the upper belly. According to Mayo Clinic and MedlinePlus, the standard exam covers the liver, gallbladder, pancreas, spleen, both kidneys, and the abdominal aorta — the body’s largest artery as it runs down toward the pelvis.
What the sonographer is hunting for varies by organ:
- Gallbladder: gallstones (which show up as bright specks casting shadows), a thickened wall, or blocked bile ducts
- Liver: changes in texture that suggest fat accumulation, scarring, cysts, or masses that need further evaluation
- Kidneys: stones, blockages, cysts, and differences in size between the two sides
- Pancreas and spleen: enlargement, cysts, and inflammation
- Aorta: widening that could signal an aneurysm
- The spaces in between: free fluid in the abdomen, which is itself an important clue
Notice the pattern: ultrasound is superb at telling fluid from solid tissue. A cyst filled with liquid looks black on screen; a stone reflects sound and looks brilliantly white. That contrast is exactly why the gallbladder — a fluid-filled sac that occasionally grows stones — is ultrasound’s signature success story. Detecting a suspicious finding, though, is not the same as diagnosing it. An ultrasound flags what looks abnormal; confirming what it actually is often takes blood work, follow-up imaging, or a specialist’s judgment.
How does an ultrasound actually work? No radiation, just echoes
The wand — technically a transducer — sends pulses of high-frequency sound into the body, far above what human ears can register. Each time those waves hit a boundary between tissues of different densities, some of the sound bounces back. The machine times each returning echo and converts it into a point of brightness on the screen, building a live moving image many times per second.
Dense structures like stones reflect nearly everything and appear white. Fluid lets sound pass straight through and appears black. Organs land somewhere in between, each with its own characteristic gray texture, and an experienced sonographer learns those textures the way a radiologist learns X-ray shadows.
Two practical consequences follow from the physics. First, there is no ionizing radiation involved — none — which is why ultrasound is the default imaging choice during pregnancy and why doctors can repeat it as often as needed without accumulating exposure, a point MedlinePlus makes plainly. Second, sound waves have enemies: air and bone. Gas in the bowel scatters the beam into useless noise, and bone blocks it entirely. That single limitation explains most of the preparation rules and most of the situations where a CT or MRI has to finish the job.
The gel, incidentally, isn’t lubricant for comfort. Air trapped between the wand and your skin would ruin the image, so the water-based gel exists to eliminate every last air pocket. Cold, yes — but doing honest work.
Why would a doctor order an abdomen ultrasound?
Usually because something specific prompted the question. Ultrasound is rarely a fishing expedition; it’s ordered to explain a symptom, follow up an abnormal test, or monitor a known condition.
Common triggers include:
- Abdominal pain, especially in the upper right belly after fatty meals — the classic gallstone pattern
- Abnormal liver blood tests, where ultrasound is often the first look at the organ itself
- Suspected kidney stones or blood in the urine
- Unexplained swelling or bloating, to check for fluid or an enlarged organ
- Jaundice — yellowing skin or eyes — to see whether bile is flowing freely
- A pulsating sensation in the abdomen or a screening check for aortic aneurysm
- Monitoring a known cyst, fatty liver, or aneurysm over time, precisely because repeat scans carry no radiation cost
Cleveland Clinic notes that ultrasound also guides procedures: when a doctor needs to sample tissue or drain fluid, real-time imaging shows the needle’s position moment by moment.
There’s a useful mental model here. Blood tests tell your doctor that something may be off; ultrasound helps show where and often what kind of problem it is. Elevated liver enzymes on their own could mean many things. Elevated enzymes plus a bright, fat-infiltrated liver on ultrasound narrows the story considerably — and points the conversation toward next steps rather than more guessing.
The screening scan worth knowing about: abdominal aortic aneurysm
Most abdominal ultrasounds investigate symptoms. One important exception screens people who feel perfectly fine.
The abdominal aorta normally measures about 2 centimeters across — roughly the width of a garden hose. In some people, usually with age, the wall weakens and balloons outward. An abdominal aortic aneurysm (AAA) typically causes no symptoms at all while it grows, which is exactly what makes it dangerous: a large aneurysm can rupture, and rupture is a life-threatening emergency that many people do not survive.
Found early, the picture changes entirely. Small aneurysms are simply measured and monitored with periodic ultrasounds. Larger ones can be repaired electively, under controlled conditions, with far better outcomes than emergency surgery.
This is why screening programs exist. In England, the NHS invites all men for a one-time ultrasound of the aorta during the year they turn 65 — a scan that takes about 10 to 15 minutes. In the United States, guidance similarly focuses on older men with a smoking history, because male sex, age over 65, and ever having smoked are the strongest risk factors. Family history of aneurysm also raises risk in both men and women.
The scan itself is as simple as imaging gets: gel, wand, a measurement of the aorta’s diameter, done. If you’re a man over 65 who has ever smoked — or anyone with a close relative who had an aortic aneurysm — this is a reasonable question to raise at your next visit.
How long does a complete abdominal ultrasound take?
Plan for about 30 minutes of actual scanning, with Mayo Clinic and Cleveland Clinic both putting the typical range at 30 to 60 minutes depending on how many organs are being examined and how clearly they show up. A focused scan — just the gallbladder, say, or just the aorta — can take 15 minutes or less.
Here’s how the appointment usually unfolds:
- You lie on a padded table, typically on your back to start
- The sonographer applies warm or room-temperature gel and moves the transducer across your abdomen with light, steady pressure
- You’ll be asked to take deep breaths and hold them — this pushes the liver down below the ribs where the sound beam can reach it
- You may roll onto your side so gravity shifts organs into better view
- Periodically the room falls quiet while the sonographer freezes images and takes measurements
A few honest notes on the experience. The pressure can feel firm, particularly over a tender spot — if you came in with gallbladder pain, pressing on the gallbladder may briefly reproduce it, and that reaction is itself diagnostic information worth mentioning aloud. The sonographer will likely not interpret findings for you during the exam; that’s not evasiveness but protocol, since a radiologist reviews the full image set afterward and writes the formal report. Silence during the scan means concentration, not bad news.
Do you take your clothes off for an abdominal ultrasound? Prep, explained
Not entirely, and often not at all. You’ll need your abdomen exposed from roughly the lower ribs to the hips, so most facilities either provide a gown or simply have you lift your shirt and fold your waistband down, with towels tucked in to protect clothing from gel. A practical tip: wear a two-piece outfit rather than a dress, and skip the complicated belt.
The preparation that actually matters is dietary:
- Fasting, usually 8 to 12 hours before a complete abdominal or gallbladder ultrasound. This isn’t ritual. Eating triggers the gallbladder to squeeze out its bile and contract into a small, wrinkled sac that’s hard to evaluate; fasting keeps it plump and full, so stones and wall thickening stand out clearly. An empty stomach also means less gas in the upper abdomen — and less gas means better pictures of the pancreas.
- Water is often fine, and for some exams (particularly those including the pelvis or kidneys) you may be asked to drink several glasses and arrive with a full bladder, which acts as a natural acoustic window. Follow the specific instructions you’re given, because they vary by exam.
- Medications can usually be taken with a small sip of water, but confirm with the ordering office rather than assuming.
If you show up having eaten breakfast before a gallbladder study, expect to reschedule. It’s the single most common reason these scans get repeated — and the easiest one to avoid.
What an abdominal ultrasound can miss — the honest version
Every imaging test has blind spots, and ultrasound’s are worth naming plainly, because a normal result doesn’t always mean a clean bill of health.
The pancreas is the classic problem child. It sits deep in the abdomen, tucked behind the stomach and draped by gas-filled bowel, and sound waves scatter in gas. On a good day the pancreas images beautifully; on a gassy day, parts of it simply vanish from view. When doctors need a definitive look at the pancreas, they frequently order CT or MRI instead.
Body composition matters too. Sound waves weaken as they travel, so in people with more abdominal tissue between skin and organ, image quality genuinely drops — a physical limitation of the technology, not a failing of the patient or the sonographer. The radiologist’s report will often note when visualization was limited, which is a signal, not a criticism.
Other honest caveats:
- Ultrasound can’t see through bone, so anything shielded by the ribs requires angling and breath-holds — and occasionally still stays hidden
- The bowel itself is poorly evaluated; ultrasound is not the test for most intestinal problems
- Small lesions, particularly in a fatty or scarred liver, can escape detection
- Findings are operator-dependent: skill and experience genuinely affect what gets seen
None of this makes ultrasound a weak test. It makes it a first test — fast, safe, inexpensive, and often sufficient. When it isn’t sufficient, its job is to point the way to the scan that will be.
What is a carotid ultrasound?
Move the wand from the belly to the neck and you have a different exam with a different mission. The carotid arteries run up either side of the neck — you can feel one pulse just beside your windpipe — and they supply most of the blood your brain uses. A carotid ultrasound examines these vessels for plaque: the waxy buildup of cholesterol, calcium, and cellular debris that narrows arteries over time.
Most carotid exams are technically duplex ultrasounds, meaning they combine two modes at once. Standard grayscale imaging shows the artery’s structure — the walls, any plaque clinging to them, the open channel remaining. Doppler ultrasound adds physiology: by measuring how sound waves shift frequency when they bounce off moving red blood cells, it calculates how fast blood is flowing at each point.
That speed measurement is the clever part. Blood behaves like water in a hose — pinch the hose and the stream speeds up through the narrowed section. When the Doppler shows blood accelerating sharply through a stretch of carotid artery, that velocity translates mathematically into an estimate of how narrowed the vessel is. Sonographers can grade a blockage without ever entering the body.
The exam experience is gentler than the abdominal version: no fasting, no full bladder, about 30 to 45 minutes on the table with your head turned slightly to each side while the transducer traces up your neck. You may hear an amplified whooshing sound during the Doppler portion — that’s your own pulse, made audible.
What does a carotid ultrasound screen for?
In a word: stroke risk. Roughly speaking, strokes happen when blood flow to part of the brain is interrupted, and one significant contributor is carotid artery disease — plaque that narrows the artery or, worse, plaque that breaks apart and sends fragments downstream into the brain’s smaller vessels.
The scan reports several things a doctor cares about:
- Presence and character of plaque — where it sits, how large it is, and whether it appears smooth or irregular
- Degree of stenosis — the percentage by which the artery is narrowed, typically grouped into ranges (for example, under 50 percent, 50 to 69 percent, or 70 percent and above), because those ranges guide how aggressively the condition is managed
- Flow direction and velocity in the carotid and vertebral arteries, which can reveal blockages elsewhere in the circulation
Here’s what matters most, in my view, and it’s a point the evidence supports: the number on the report is a risk marker, not a verdict. Plenty of people live for decades with mild carotid plaque that never causes a symptom, managed through blood pressure control, cholesterol management, not smoking, and regular follow-up scans. Severe narrowing — especially in someone who has already had warning symptoms — is a different conversation, and one to have with a physician who can weigh the full picture. The ultrasound supplies the map; it doesn’t choose the route.
Mayo Clinic notes the test is also used after a stroke or mini-stroke to search for the culprit, and to monitor arteries after a procedure has been performed on them.
Who actually needs a carotid ultrasound? (Not everyone)
This is where honest medicine parts ways with marketing. Mobile screening companies sometimes pitch carotid ultrasounds to the general public as a can’t-hurt precaution. The evidence tells a more nuanced story: for adults with no symptoms and no particular risk factors, major preventive-care guidance in the United States does not recommend routine carotid screening. The reason is practical, not stingy — in low-risk people, the test finds more false alarms and borderline findings than dangerous disease, and those findings can cascade into follow-up tests and procedures that carry real risks of their own.
Carotid ultrasound earns its keep in specific situations:
- After warning symptoms — a transient ischemic attack (temporary weakness, numbness on one side, slurred speech, or vision loss in one eye that resolves) or a stroke
- When a doctor hears a bruit — a whooshing sound over the artery through a stethoscope that can indicate turbulent flow
- In people with strong risk profiles — established heart or vascular disease elsewhere, long-standing high blood pressure, diabetes, high cholesterol, or a significant smoking history — at a physician’s discretion
- For monitoring — tracking known plaque year over year, or checking an artery after surgical repair
If a screening result from an outside vendor lands in your hands showing ‘mild plaque,’ don’t panic and don’t ignore it — bring it to your regular doctor, who can put it in the context of your overall cardiovascular risk. Context is the entire game with this test.
How to make sense of your ultrasound report
Reports now arrive in patient portals within days — often before anyone has explained them — so a small vocabulary lesson prevents a lot of midnight worry.
Ultrasound reports describe how tissue reflects sound, using the root echo:
- Anechoic — no echoes, appears black; this usually means simple fluid, and a ‘simple anechoic cyst’ is among the most benign phrases in radiology
- Hypoechoic — darker than surrounding tissue; a descriptive term, not a diagnosis, covering everything from harmless findings to things needing follow-up
- Hyperechoic / echogenic — brighter than surrounding tissue; a diffusely echogenic liver, for instance, often reflects fat accumulation
- Shadowing — a dark stripe behind a bright object, the classic signature of a stone blocking the sound beam
- Unremarkable — the anticlimactic word you actually want; it means normal
Two phrases deserve special mention. ‘Clinical correlation recommended’ means the radiologist is asking your doctor to match the image with your symptoms and labs — routine language, not alarm. ‘Limited by bowel gas’ or ‘limited by body habitus’ means part of the exam couldn’t be fully seen, which sometimes prompts a different test rather than signaling anything found.
On carotid reports, look for the stenosis percentage and the peak systolic velocity figures; your doctor uses the velocity numbers to derive the percentage. And a general rule that holds across all imaging: the report’s impression section at the end is the summary that matters. The dense paragraphs above it are documentation, written for other clinicians, not messages aimed at you.
Abdominal vs. carotid ultrasound at a glance
Same machine, different missions. Here’s the side-by-side that patients most often ask for:
| Abdominal ultrasound | Carotid ultrasound | |
|---|---|---|
| What it examines | Liver, gallbladder, pancreas, spleen, kidneys, abdominal aorta | Carotid (and often vertebral) arteries in the neck |
| Main question it answers | Is an organ inflamed, obstructed, enlarged, or harboring stones, cysts, or masses? Is the aorta widened? | Is plaque narrowing the arteries that feed the brain, and by how much? |
| Typical reasons ordered | Abdominal pain, abnormal liver tests, jaundice, suspected stones, AAA screening | TIA or stroke workup, a bruit heard on exam, monitoring known plaque |
| Preparation | Usually fast 8–12 hours; sometimes arrive with a full bladder | None; avoid turtlenecks and necklaces |
| Duration | About 30–60 minutes (10–15 for aorta-only screening) | About 30–45 minutes |
| Radiation | None | None |
| Key limitation | Bowel gas and body composition can hide deep structures, especially the pancreas | Estimates narrowing indirectly from flow speed; borderline results may need CT or MR angiography |
One more distinction worth internalizing: the abdominal exam is mostly about organs — their size, texture, and contents — while the carotid exam is mostly about flow. That’s why the abdominal scan is quiet and the carotid scan whooshes: Doppler makes your bloodstream audible, and in the neck, the bloodstream is the whole point.
When to see a doctor: symptoms that shouldn't wait for a scan
Some symptoms deserve a medical appointment, and a few demand an emergency room. Knowing the difference matters more than knowing anything about ultrasound machines.
Call emergency services or go to the ER immediately for:
- Sudden weakness or numbness on one side of the body, facial drooping, slurred speech, sudden vision loss, or sudden severe confusion — these are possible stroke signs, and every minute of delay costs brain tissue. This applies even if symptoms fade within minutes; a transient episode is a warning shot, not a false alarm.
- Sudden, severe abdominal or back pain — especially a tearing or ripping sensation — with lightheadedness or a rapid pulse, which can signal an aortic emergency
- Intense abdominal pain with fever, persistent vomiting, or a rigid, board-like belly
Make a prompt appointment (days, not months) for:
- Recurring upper-right abdominal pain after meals, particularly fatty ones
- Yellowing of the skin or eyes, dark urine, or pale stools
- Unexplained weight loss alongside abdominal discomfort or persistent bloating
- Blood in the urine, or flank pain that comes in waves
- A new pulsating sensation in the abdomen, especially if you’re over 65 with a smoking history
A pattern worth noticing in that first list: stroke symptoms are painless. People wait them out precisely because nothing hurts, and that waiting is the costliest mistake in cerebrovascular medicine. The abdominal emergencies announce themselves loudly; the neurological ones whisper. Treat the whisper with the same urgency.
Are ultrasounds safe — and what about surprise findings?
On safety, the evidence is about as reassuring as medical imaging gets. Diagnostic ultrasound uses no ionizing radiation, involves no contrast injection for these standard exams, and has been used for more than half a century — including routinely in pregnancy — without demonstrated harm at diagnostic power levels, a track record MedlinePlus and Mayo Clinic both describe. The realistic downsides are mundane: gel in your waistband, firm pressure on a sore spot, and the small tedium of holding your breath on command.
The subtler issue is the incidental finding — the thing nobody was looking for. Scan enough abdomens and you will find plenty of them: simple kidney cysts (increasingly common with age and overwhelmingly harmless), small liver hemangiomas (benign tangles of blood vessels), tiny gallbladder polyps. Radiologists have standardized criteria for which of these need follow-up imaging and which can be safely left alone, and most fall into the second category.
Two pieces of grounded advice for when your report mentions one:
- Read the impression section for words like ‘benign,’ ‘simple,’ or ‘no follow-up needed’ — radiologists use them deliberately, and they mean what they say
- If follow-up is recommended, put the date on your calendar the day you read the report; surveillance intervals exist because they work, and missed follow-ups are how manageable findings become unmanaged ones
The scan that finds nothing wrong still did its job. And the scan that finds something small and benign did its job too — even if it costs you one evening of unnecessary worry before the follow-up conversation sorts it out.
Frequently asked questions
What can be detected on an abdominal ultrasound?
An abdominal ultrasound can detect gallstones, kidney stones, cysts, fluid buildup, enlarged organs, fatty changes in the liver, blocked bile ducts, and widening of the abdominal aorta that suggests an aneurysm. It examines the liver, gallbladder, pancreas, spleen, kidneys, and aorta. It excels at distinguishing fluid from solid tissue, though deep structures like the pancreas can be partially hidden by bowel gas, sometimes requiring CT or MRI follow-up.
How long does a complete abdominal ultrasound take?
About 30 to 60 minutes of scanning time is typical for a complete abdominal ultrasound, with most exams closer to 30. A focused study of one organ, or an aorta-only aneurysm screening, can take 15 minutes or less. Time varies with how many organs are examined and how clearly they image — breath-holds, position changes, and repeat measurements all add minutes. Plan for about an hour at the facility overall.
Why would a doctor order an abdomen ultrasound?
Most often to investigate a specific symptom or abnormal test: unexplained abdominal pain, elevated liver enzymes, jaundice, suspected gallstones or kidney stones, blood in the urine, or bloating. It’s also used to screen older men with a smoking history for abdominal aortic aneurysm, to monitor known cysts or fatty liver over time, and to guide needle procedures in real time. Because it uses no radiation, it’s usually the first imaging test tried.
Do you take your clothes off for an abdominal ultrasound?
Not fully. You only need the abdomen exposed, so most facilities have you lift your shirt and lower your waistband slightly, or change into a gown. Towels protect your clothes from the gel. Wearing a loose two-piece outfit makes the visit easier. The preparation that actually matters is fasting — usually 8 to 12 hours beforehand — so the gallbladder stays full and images clearly.
Can I drink water before an abdominal ultrasound?
Often yes, but follow your specific instructions, because they vary by exam. For many fasting abdominal ultrasounds, plain water is allowed. For exams that include the kidneys, bladder, or pelvis, you may actually be asked to drink several glasses of water and arrive with a full bladder, which acts as a window for the sound waves. Avoid coffee, milk, and anything with fat, since these trigger gallbladder contraction.
Can an abdominal ultrasound detect cancer?
It can detect masses that might be cancer, but it cannot diagnose cancer by itself. Ultrasound shows that a growth exists, its size, and whether it’s fluid-filled or solid — clues that shape the next step. Confirming what a mass actually is typically requires additional imaging such as CT or MRI, blood tests, or a biopsy. A normal ultrasound is reassuring but not absolute, since small lesions and gas-obscured areas can be missed.
Does an ultrasound hurt?
No — ultrasound is painless for most people. You’ll feel cool gel and steady pressure from the handheld transducer as it moves across your skin. If the sonographer presses over an already tender area, such as an inflamed gallbladder, that spot may briefly ache, and telling them so is actually useful diagnostic information. There are no needles, no radiation, and no recovery time; you can drive home and eat normally right after.
What does a carotid ultrasound show?
A carotid ultrasound shows the two main neck arteries that supply the brain, revealing plaque buildup, how much the artery is narrowed, and how fast blood is flowing through it. Doctors use it after a stroke or mini-stroke, when a stethoscope picks up abnormal turbulent sounds in the neck, or to monitor known plaque over time. The degree of narrowing helps guide decisions about risk-factor management and follow-up.
Should I get a carotid ultrasound as part of a routine checkup?
For most symptom-free adults without significant risk factors, no — routine carotid screening isn’t recommended by major US preventive-care guidance, because in low-risk people it yields more false alarms than true disease, and follow-up testing carries its own risks. It becomes valuable after stroke-like symptoms, when a doctor hears a bruit in the neck, or in people with substantial cardiovascular risk. Discuss your individual risk profile with your physician before seeking one.
When will I get my ultrasound results?
Usually within a few days. The sonographer captures the images, a radiologist interprets them and writes a formal report, and that report goes to the doctor who ordered the test — often appearing in your patient portal at the same time. Urgent findings are communicated much faster, sometimes the same day. The sonographer generally won’t discuss results during the exam; that silence is standard protocol, not a signal of bad news.
References
- MedlinePlus — Abdominal ultrasound
- MedlinePlus — Carotid duplex
- NHS — Abdominal aortic aneurysm screening
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
The MRI Visit: Duration, Preparation and What Happens in the Tube
Most MRI scans take between 15 and 90 minutes, depending on the body part, the number of imaging sequences, and whether contrast dye is…
Can a CT Scan Detect Cancer? What It Shows, What It Misses and the Tests That Follow
A CT scan can detect many tumors, especially solid masses in the lungs, liver, kidneys, pancreas, bones and lymph nodes, often when they are…

The Holter Monitor: Living With a 24-48 Hour Heart Recorder
A Holter monitor is a small, portable device that records every heartbeat for 24 to 48 hours through adhesive chest electrodes. It helps doctors…
What an Echocardiogram Shows (and the Five Abnormalities It Looks for)
An echocardiogram is an ultrasound scan of the heart that shows its size, the thickness of its walls, how strongly it pumps, and whether…
MRCP Scan: The Non-Invasive Look at Bile Ducts That Replaced Diagnostic ERCP
An MRCP (magnetic resonance cholangiopancreatography) test is a non-invasive MRI scan that creates detailed pictures of the bile ducts, gallbladder, and pancreatic duct without…

Neurophysiology Tests: EMG, EEG and Nerve Conduction in Plain Language
Neurophysiology tests measure the electrical activity of nerves, muscles, and the brain. An EMG records signals inside muscle, a nerve conduction study times impulses…