

What an Echocardiogram Shows (and the Five Abnormalities It Looks for)
Key Takeaways
- A normal left ventricular ejection fraction is roughly 50 to 70 percent, but a normal figure does not exclude heart failure caused by a stiff heart that fills poorly.
- Echocardiography does not image the coronary arteries directly; it detects the consequences of blockage as segments of heart wall that move weakly or have scarred.
- Trivial or mild leakage across one or more valves is a common finding in healthy hearts and is often reported as physiologic.
- A bubble study uses agitated saline injected into an arm vein to reveal small holes between the heart's upper chambers that ordinary imaging misses.
- A standard transthoracic echocardiogram usually takes under an hour and needs no fasting or medication changes, while a transesophageal echo requires several hours without food and someone to drive you home.
- Thickened left ventricular walls on echo are frequently the first objective evidence of long-standing high blood pressure, often before any symptoms appear.
An echocardiogram is an ultrasound scan of the heart that shows its size, the thickness of its walls, how strongly it pumps, and whether its four valves open and close properly. Clinicians use it to look for five main types of abnormality: weak pumping, valve disease, enlarged or thickened chambers, structural holes, and fluid, clots or masses around the heart. It does not directly image blocked coronary arteries.
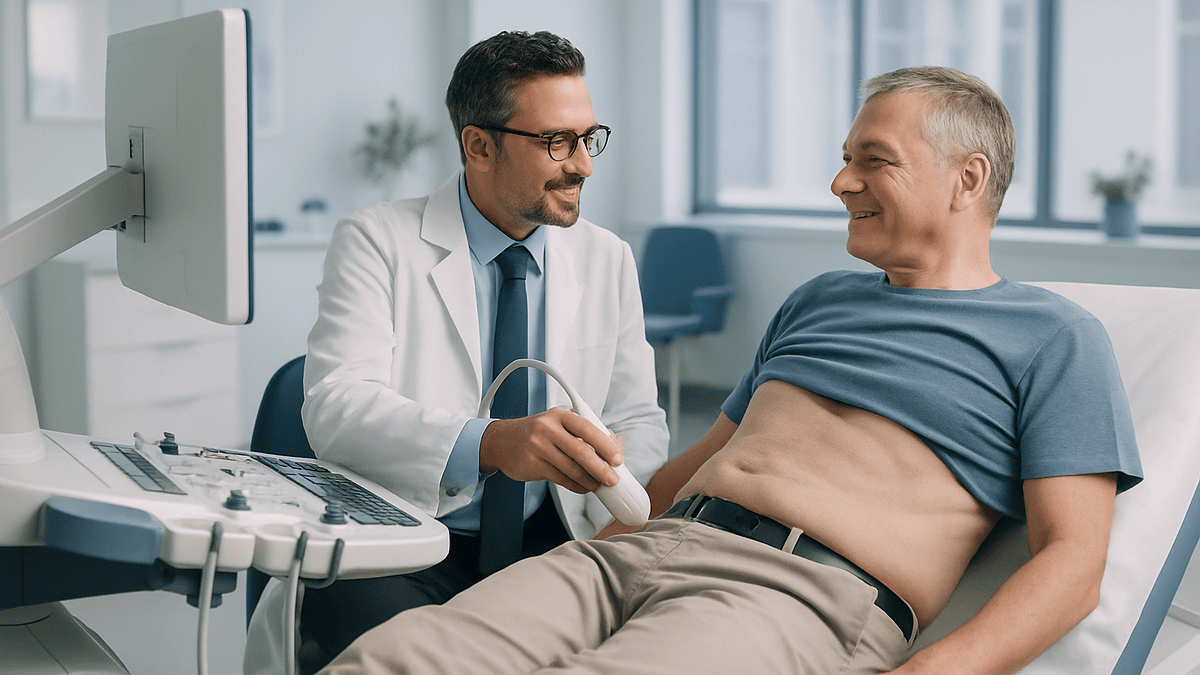
The room is dim, the gel is cold, and on a screen you were not quite prepared to look at, something is beating. It is unmistakably yours. A sonographer tilts a wand no bigger than a TV remote a few degrees, and the picture swings from a cross-section of two chambers to a view straight down the barrel of a valve, its leaflets snapping shut sixty-odd times a minute.
Most people leave that room with two feelings at once: quiet awe, and a fistful of unanswered questions. What was the technician measuring when the screen filled with red and blue? Why did they keep asking you to hold your breath? And the one that nags on the drive home: if something were wrong, would this test have found it?
This guide answers those questions plainly. It explains what the scan can see, what it genuinely cannot, and why the number everyone fixates on is rarely the whole story.
What is an echocardiogram, really?
Strip away the medical vocabulary and an echocardiogram is a sonar system pointed at your chest. A handheld probe, called a transducer, sends out sound waves pitched far above human hearing. Those waves bounce off blood, muscle and valve tissue at slightly different speeds, and a computer turns the returning echoes into a moving picture in real time.
That word moving matters. A chest X-ray freezes the heart in one frame. An echocardiogram films it, which is why clinicians can watch a valve flutter, see a wall of muscle stiffen or lag behind its neighbors, and follow blood as it swirls from one chamber to the next.
Two extra tricks make the pictures far more informative than a grainy outline. Doppler imaging measures how fast blood is moving and in which direction, painted in red and blue on the screen; it is the same physics that makes an ambulance siren change pitch as it passes. Tissue Doppler does something similar for the muscle itself, tracking how briskly the walls relax between beats.
Because the whole thing runs on sound rather than radiation, there is no exposure dose to tally. That is one reason the test is used so freely in pregnancy, in children, and for repeat monitoring over many years. According to the Mayo Clinic, a standard echocardiogram carries no known risks beyond mild skin discomfort from the probe, and MedlinePlus describes it as a routine, painless test.
What five abnormalities can be found on an echocardiogram?
Ask five cardiologists to list what they are looking for and you will get five slightly different lists, but they cluster into the same five territories. Think of them as questions the scan is trying to answer.
| Abnormality | Question the scan asks | Key measurement or view |
|---|---|---|
| Weak or uneven pumping | Is the heart squeezing hard enough, and evenly? | Ejection fraction; wall motion in each segment |
| Valve disease | Do the four valves open fully and close tightly? | Doppler flow, jet size, pressure gradients |
| Chamber size and wall thickness | Has any chamber stretched, or any wall thickened? | Diameters and wall measurements at set points in the cycle |
| Structural holes and defects | Is blood crossing where it should not? | Color Doppler across the septum; bubble study |
| Fluid, clots and masses | Is anything sitting around or inside the heart that should not be there? | Pericardial space, chamber interiors, root of the aorta |
Notice what is missing from that table: coronary artery blockages. The scan infers their consequences rather than photographing the arteries themselves, a distinction covered in its own section below.
The Cleveland Clinic and Johns Hopkins both describe the test as the workhorse for evaluating heart size, pumping strength, valve function, congenital defects and pericardial disease, which maps neatly onto these five. Each deserves a closer look, because the way a finding is described on your report shapes what happens next far more than the fact that something was found at all.
Abnormality one: how strongly the heart pumps
The single most quoted number on any echo report is the ejection fraction, usually abbreviated EF. It answers a blunt question: of the blood sitting in the left ventricle when it is full, what share gets pushed out with each beat?
The answer is never 100 percent, and it should not be. According to the American Heart Association, a normal left ventricular ejection fraction falls roughly between 50 and 70 percent, a reading of 41 to 49 percent is considered borderline, and 40 percent or lower is classed as reduced. Those bands help clinicians decide whether the heart muscle itself has weakened.
Here is where the number earns its reputation for being both useful and overrated. A heart can have a textbook ejection fraction and still fail to fill properly between beats because its walls have grown stiff. Clinicians call this diastolic dysfunction, and it is the mechanism behind heart failure with preserved ejection fraction, a condition in which the squeeze looks fine but the relaxation does not. Echo is one of the few tests that can catch it, using Doppler patterns of how blood enters the ventricle and how quickly the muscle springs back.
Equally telling is where the heart pumps weakly. Sonographers divide the left ventricle into segments and grade each one. A whole heart that squeezes gently points toward one set of causes; a single patch that barely moves while its neighbors work hard suggests that region has lost its blood supply at some point. In that sense the echo reads scar the way a geologist reads rock strata.
Abnormality two: valves that leak or narrow
Four valves keep blood moving in one direction through the heart, and each can fail in two opposite ways. It can stiffen and refuse to open fully, called stenosis, or it can fail to seal and let blood wash backward, called regurgitation or insufficiency. Some valves manage to do both.
Echo is unusually good at valves for a simple reason: they are thin, mobile structures surrounded by moving blood, exactly what ultrasound and Doppler were built to see. The color Doppler map shows a leaking valve as a plume of turbulent flow heading the wrong way. The size, length and shape of that plume, combined with pressure measurements calculated from blood speed, let the reader grade the leak as trivial, mild, moderate or severe.
Two things surprise people reading their reports. The first is how often a small amount of leakage shows up in perfectly healthy hearts; the Cleveland Clinic notes that mild regurgitation is a common and frequently harmless finding. The second is that a narrowed valve is assessed largely by how fast blood has to squeeze through the gap, since a smaller opening forces a faster jet.
Beyond grading, the scan looks at why a valve misbehaves. Leaflets can be thickened and calcified with age, floppy and prolapsing, damaged by past rheumatic fever, or infected. The valve may also be perfectly normal while the ring around it has stretched because the chamber behind it has enlarged, a distinction that changes the entire conversation about what, if anything, needs to be done.
Abnormality three: chamber size and wall thickness
Muscle responds to work. Years of pushing against high blood pressure or a narrowed valve thicken the left ventricle’s walls, a change called hypertrophy. Years of leaking valves or weakened pumping stretch a chamber wider instead, called dilation. An echocardiogram measures both in millimeters at fixed moments in the heartbeat and compares them with reference ranges adjusted for body size.
Why should you care about a few millimeters? Because those measurements often change before symptoms do. A thickened wall is a fingerprint of blood pressure that has been high for longer than anyone realized. A left atrium that has quietly expanded raises the question of whether the heart has been in an irregular rhythm at times nobody caught on a routine tracing.
Thickness also has to be interpreted in context, and this is where a good reader earns their keep. Endurance athletes can develop a modestly enlarged, slightly thicker heart that is entirely healthy. Certain inherited conditions thicken the muscle in an uneven, patchy way that looks different from the symmetrical thickening of high blood pressure. Some infiltrative diseases stiffen the walls while making them appear unusually bright on the screen. The pattern, not just the number, tells the story.
The right side of the heart gets measured too, though it is harder to see clearly from the chest. Right ventricular size and the estimated pressure in the lung circulation, derived from how fast blood leaks back across the tricuspid valve, are among the most clinically useful figures on the report for anyone with breathlessness or lung disease.
Abnormality four: holes and structural defects
Every heart starts life with openings between its chambers that are supposed to close around birth. In a meaningful minority of people, one does not, and an echocardiogram is the standard way to find out.
The most common leftover is a patent foramen ovale, a flap-like passage between the two upper chambers. Larger openings in the wall between the atria, or between the two ventricles, are classed as septal defects and may have been present since infancy without ever causing trouble. Color Doppler shows blood crossing these gaps as a streak of color where the wall should be solid.
When a small opening is suspected but not obvious, sonographers use a bubble study. Agitated saline, essentially salt water shaken to create tiny microbubbles, is injected into an arm vein while the scan runs. The bubbles light up the right side of the heart; if any appear on the left within a few beats, blood is finding a shortcut. It is an elegant, low-tech test that turns an invisible hole into something plainly visible.
Echo also maps more complex congenital anatomy: valves with two leaflets instead of three, vessels that connect in the wrong place, chambers that never fully formed. For adults who had heart surgery as children, lifelong echo follow-up is often the main way to keep watch on repairs. MedlinePlus lists congenital heart disease among the core reasons the test is ordered, and in many pediatric clinics it is the first imaging test a child with a murmur will ever have.
Abnormality five: fluid, clots and masses around or inside the heart
The heart sits inside a thin, two-layered sac called the pericardium. Normally there is barely a teaspoon of lubricating fluid between the layers. Inflammation, infection, kidney disease, cancer and certain medications can all cause that fluid to build up, and on the screen it appears as a dark crescent hugging the heart’s outline.
How much fluid matters less than how the heart is coping with it. A large but slowly accumulating effusion may cause few problems, because the sac has time to stretch. A smaller amount that arrives quickly can squeeze the chambers so they cannot fill, a situation clinicians treat as an emergency. Echo shows both the fluid and the telltale signs of compression, such as a right atrial wall that caves inward when it should not.
Inside the chambers, the scan hunts for things that ought not to be there. Blood clots can form in a sluggish, poorly contracting ventricle after a heart attack, or in a pouch of the left atrium during irregular rhythms; these appear as echo-dense lumps stuck to the wall. Growths, most often benign, and clumps of infected tissue on a valve are also visible, though small ones may need the closer view offered by a probe passed down the esophagus.
Finally, the standard views include the first few centimeters of the aorta as it leaves the heart. A widened aortic root is one of the quieter but more consequential findings a routine echo can turn up, since it may prompt surveillance for years.
Will an echocardiogram show any blockages?
Not directly, and this is the most common misunderstanding about the test. The coronary arteries that supply the heart muscle are only a few millimeters wide and run along the outer surface of the heart, and a standard echocardiogram cannot resolve them well enough to see plaque or narrowing inside.
What the scan can show is the effect of a blockage. Heart muscle deprived of blood stops contracting properly, so a segment of wall that moves weakly or not at all, or that has thinned into scar, points strongly toward a blocked or previously blocked artery feeding that region. The Mayo Clinic describes this as one of the main ways echo helps assess damage after a heart attack.
A stress echocardiogram sharpens the question. Images are taken at rest and again immediately after exercise or a medication that makes the heart work harder. A wall that moves normally at rest but falters under stress suggests an artery that keeps up with everyday demand but cannot deliver when pushed. That pattern is suggestive rather than definitive.
If the question is specifically whether an artery is narrowed and by how much, other tests are built for the job. A CT coronary angiogram uses contrast dye and X-rays to picture the arteries themselves, and an invasive coronary angiogram threads a catheter to the heart to do the same in real time. Which route makes sense, if any, depends on symptoms, risk factors and what the echo already revealed, and that judgment sits with the treating clinician.
Transthoracic, transesophageal or stress echo: which kind will you have?
Most people who are told they need an echocardiogram will have the standard version, a transthoracic echo, in which the probe rests on the chest. It is the test described in most of this article: no needles unless a bubble study is added, no sedation, and you go home immediately afterward.
A transesophageal echo takes a different route. The probe is mounted on a thin flexible tube that you swallow after the throat is numbed and, usually, a sedative is given. Because the esophagus lies directly behind the heart, the images are sharper and unobstructed by ribs or lung. According to the Mayo Clinic, this approach is chosen when the chest-surface images are unclear or when fine detail is needed, for example to look for small clots in the left atrium before a rhythm procedure, to examine an artificial valve, or to inspect a valve suspected of infection.
A stress echo, described in the previous section, pairs imaging with exertion. Sometimes you walk on a treadmill or pedal a bike; when that is not possible, a medication given through a vein temporarily makes the heart beat harder and faster to mimic exercise.
Two further variants are worth knowing by name. A fetal echocardiogram scans a baby’s heart during pregnancy, usually through the mother’s abdomen. A contrast echo uses a specially formulated agent to make the inner border of the heart chambers sharper when the plain images are hard to read, most often in people whose body build or lung disease scatters the sound waves. Your referral letter will say which type you are booked for; it is worth asking if it does not.
How long does an echocardiogram usually take?
Budget an hour, and expect to be pleasantly surprised. The Mayo Clinic notes that a standard transthoracic echocardiogram generally takes less than an hour from lying down to sitting up, and the NHS gives a similar window. The scanning itself is often the shorter part; changing, positioning and the sonographer capturing a full set of views and measurements make up the rest.
Several things stretch the clock, none of them alarming. If your ribs sit close together or your lungs hold a lot of air, the sonographer may need extra time hunting for a clear window. A bubble study adds a few minutes for the injection. Complex valve disease or a heart that has been operated on before invites more measurements. And sonographers are meticulous by training; a longer scan usually means thoroughness, not trouble.
A transesophageal echo is a different kind of appointment. The imaging portion is comparable in length, but the preparation, sedation and recovery mean you should plan on being at the facility for a good part of the day and arranging for someone to take you home. A stress echo also runs longer than a plain scan because it includes the exercise or medication phase and a monitored recovery period.
One question people rarely ask but should: when will the results come? The sonographer records the images and measurements, but a cardiologist interprets them and writes the report. In many services that happens within days, though timelines vary, and urgent findings are flagged the same day. Ask at the appointment how and when you will hear back.
What should you not do before an echocardiogram?
For a standard transthoracic echo, the honest answer is: very little. The Mayo Clinic advises that no special preparation is needed; you can eat, drink and take your usual medications as normal. Arriving well hydrated and unhurried is about the extent of it.
A few practical points still smooth the visit. Wear a top that is easy to remove, since electrodes will be stuck to your chest and the probe needs bare skin. Skip heavy lotion or oil on the chest that morning, because gel grips clean skin better. Bring a list of your medications and any previous heart test results, particularly if you have had an echo elsewhere, since comparing today’s measurements with earlier ones is often more informative than either scan alone.
The rules tighten for the other types. Before a transesophageal echo you will typically be asked not to eat or drink for several hours, because the probe passes into the esophagus and a full stomach raises the risk of vomiting during sedation. You will also be told not to drive afterward and to have someone accompany you. Before a stress echo, clinics commonly ask you to avoid caffeine for a period, eat only lightly, wear comfortable shoes, and sometimes to hold certain heart-rate-slowing medications so the heart can respond to exercise. That last instruction must come from your own clinical team; never stop a medication on your own initiative because of something you read, including here.
If instructions arrive by letter and seem unclear, call before the day. Being turned away because of a missed fasting rule is a frustrating way to lose a morning.
What happens during the scan, step by step
You undress from the waist up and put on a gown that opens at the front. Three small sticky electrodes go on your chest so the machine can time each image to your heartbeat; this is not a full electrocardiogram, just a rhythm reference. The room lights dim so the screen is easier to read.
The sonographer asks you to lie on your left side with your left arm above your head. That position lets the heart fall toward the chest wall and spreads the ribs slightly, opening acoustic windows. Cool gel goes on the skin, and the probe follows.
Over the next half hour or so the probe visits a handful of standard positions: beside the breastbone, under the left breast near the apex of the heart, just below the ribcage, and at the base of the neck. From each spot the sonographer angles the probe to capture set views, each with a name that sounds like a code word. You will be asked to breathe out and hold, sometimes repeatedly, because a still diaphragm gives a still picture.
Expect the screen to fill with color and the speakers to pulse with a whooshing sound when Doppler is switched on. That noise is your blood flow rendered as audio. Expect some firm pressure from the probe, particularly between ribs; say so if it hurts. Expect silence too, because sonographers concentrate hard and most are not permitted to interpret findings for you on the spot. Their reticence is professional protocol, not a sign that something is wrong.
How to read your echocardiogram report without panicking
Reports are written for cardiologists, and it shows. A few translation notes help.
Ejection fraction is discussed above; check the reported value against the American Heart Association’s bands, and remember that a normal figure does not rule out a stiff heart, while a modestly low one has many causes.
Trivial or mild regurgitation across one or more valves appears on a great many reports of people with no heart disease. Reader descriptions such as physiologic or within normal limits mean the same thing: not a problem.
Grade 1 diastolic dysfunction describes the mildest degree of stiffness in relaxation. It becomes more common with age and with high blood pressure, and on its own it is a prompt to keep blood pressure well controlled rather than a diagnosis of heart failure.
Suboptimal image quality or poor acoustic windows means the sonographer struggled to see clearly, often because of body build or lung disease. It explains why a measurement might be missing or why another test was suggested.
Mild left ventricular hypertrophy points toward the heart working against resistance, usually long-standing blood pressure. It is common, and it is one of the more actionable findings because the driver is often treatable.
Whatever the report says, its meaning depends on why the test was ordered, your symptoms and any earlier scans. The person who requested the echo is the right person to walk you through it, and a good question to bring is simple: has anything changed since last time, and what does that change mean for me?
Echocardiogram vs ECG vs other heart scans
The names blur, and patients are sometimes booked for one while expecting another. The distinction is worth ten seconds of clarity.
An electrocardiogram, abbreviated ECG or EKG, records the heart’s electrical activity through stickers on the skin. It takes a few minutes and produces a squiggly line on paper or screen. It excels at rhythm problems and can hint at past or ongoing heart attacks, but it shows nothing about how the heart looks or how the valves behave. An echocardiogram, by contrast, is a picture. The two are complementary, which is why they are so often ordered together, and why having one does not mean you can skip the other.
Cardiac MRI produces exquisitely detailed images without radiation and is considered the reference standard for measuring chamber volumes and detecting scar in the heart muscle. It costs more, takes longer, and is harder for people who are claustrophobic or have certain implanted devices. Cardiac CT is fast and is the test of choice for imaging the coronary arteries themselves, at the price of X-ray exposure and contrast dye. Nuclear perfusion scans map blood flow to the muscle under stress using a small radioactive tracer.
Where does echo fit? It is the first-line imaging test for most heart questions because it is quick, safe, repeatable and available almost everywhere. According to the NHS and Cleveland Clinic, it is often the test that decides whether any of the others is needed at all. Its weaknesses, chiefly image quality that depends on the person’s build and the operator’s skill, are exactly what the other modalities compensate for.
When to see a doctor: symptoms that should not wait for a scheduled scan
An echocardiogram is usually a planned test, but the symptoms that lead to one are sometimes urgent. Call emergency services right away, rather than waiting for an appointment, if you experience chest pain or pressure that lasts more than a few minutes or comes with sweating, nausea or pain spreading to the arm, jaw or back; sudden severe breathlessness, especially at rest or lying flat; fainting or near-fainting, particularly during exertion; or a racing, pounding heartbeat together with dizziness or chest discomfort. Sudden weakness on one side of the body, facial drooping or trouble speaking are stroke signs and need the same immediate response.
Book a prompt appointment, within days rather than weeks, for symptoms that are new but less dramatic: breathlessness on stairs or slopes that you managed easily a few months ago, ankles that swell by evening, a need to sleep propped up on extra pillows, unexplained fatigue, or palpitations that keep recurring. A newly noticed heart murmur at a routine check-up also warrants follow-up, and echo is typically the test used to explain it.
If you have already had an echocardiogram and were told to return for surveillance, whether for a valve, an enlarged aorta or a childhood repair, keep those dates. Many of the conditions the scan monitors progress silently, and the entire value of a follow-up study is catching a change before it announces itself. Worsening symptoms between scheduled scans are always a reason to be seen sooner; nobody will consider it an overreaction.
Frequently asked questions
What 5 abnormalities can be found on an echocardiogram?
The five main abnormalities are weak or uneven pumping, valve disease, enlarged or thickened heart chambers, structural holes between chambers, and fluid, clots or masses around or inside the heart. Each is assessed with specific measurements: ejection fraction and wall motion for pumping, Doppler flow for valves, chamber dimensions for size, color flow across the septum for holes, and direct visualization of the pericardial space and chamber interiors for the rest.
What should you not do before an echocardiogram?
For a standard chest-surface echocardiogram there are no real restrictions; you can eat, drink and take medications as usual. Avoid heavy lotions on the chest so the gel adheres. Before a transesophageal echo you will be asked not to eat or drink for several hours and not to drive afterward. Before a stress echo, clinics often ask you to avoid caffeine and eat lightly. Follow your own team’s written instructions over any general advice.
How long does an echocardiogram usually take to complete?
A standard transthoracic echocardiogram usually takes less than an hour from start to finish, according to the Mayo Clinic, with the scanning itself often shorter. Extra time may be needed if images are hard to obtain, if a bubble study is added, or if the heart has complex anatomy. Transesophageal and stress echocardiograms take longer because they include preparation, sedation or exercise, and a monitored recovery period, so plan for a longer visit.
Will an echocardiogram show any blockages?
Not directly. The coronary arteries are too small and too close to the heart’s surface for a standard echocardiogram to show plaque or narrowing inside them. The scan can reveal the effects of a blockage, such as a segment of heart wall that moves weakly or has scarred, and a stress echo can suggest an artery that cannot keep up during exertion. Imaging the arteries themselves requires CT or invasive coronary angiography.
Does an echocardiogram show heart failure?
Yes, it is the main imaging test used to diagnose and classify heart failure. It measures ejection fraction to identify a weakened pump and uses Doppler patterns to detect a stiff heart that fills poorly despite a normal ejection fraction. It also shows contributing problems such as valve disease, thickened walls or enlarged chambers. Symptoms and blood tests are weighed alongside the scan, so the diagnosis rests with the clinician interpreting everything together.
Is an echocardiogram the same as an ECG?
No. An ECG, or electrocardiogram, records the heart’s electrical signals through skin electrodes and produces a tracing that shows rhythm and electrical patterns. An echocardiogram is an ultrasound that produces moving images of the heart’s structure, pumping and valves. The ECG takes minutes; the echo usually takes under an hour. Because they answer different questions, clinicians often order both, and having one does not replace the other.
Can an echocardiogram detect a previous heart attack?
Often, yes. Heart muscle that lost its blood supply during a heart attack stops contracting normally and may thin into scar, and an echocardiogram shows these regions as segments of wall that move weakly or not at all. The pattern can also indicate which artery was likely involved. Small or older events are sometimes missed, and cardiac MRI is more sensitive for detecting scar, so a normal echo does not completely rule out past damage.
What does mild regurgitation on an echo mean?
Mild regurgitation means a small amount of blood leaks backward through a valve when it closes. It is a very common finding, appears in many people with entirely healthy hearts, and is often described on reports as trivial or physiologic. On its own it rarely requires treatment. Clinicians may suggest a repeat scan after some years to confirm it is stable, particularly if there is another reason to keep an eye on the heart.
Is an echocardiogram safe during pregnancy?
A standard echocardiogram is considered safe in pregnancy because it uses sound waves rather than radiation and involves no contrast dye or sedation. It is routinely used to assess a pregnant person’s heart when symptoms such as breathlessness or palpitations need investigating, and a separate fetal echocardiogram can examine the baby’s heart. Transesophageal and stress versions involve additional considerations, which the clinical team weighs individually.
Why did the sonographer not tell me my results?
Sonographers are trained to acquire images and measurements, but in most services a cardiologist interprets them and writes the formal report. Professional protocols usually prevent sonographers from discussing findings during the scan, so their silence is standard practice rather than a sign of bad news. Ask at the appointment how and when results will reach you; urgent findings are typically flagged to the referring clinician the same day.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
The MRI Visit: Duration, Preparation and What Happens in the Tube
Most MRI scans take between 15 and 90 minutes, depending on the body part, the number of imaging sequences, and whether contrast dye is…
Can a CT Scan Detect Cancer? What It Shows, What It Misses and the Tests That Follow
A CT scan can detect many tumors, especially solid masses in the lungs, liver, kidneys, pancreas, bones and lymph nodes, often when they are…

The Holter Monitor: Living With a 24-48 Hour Heart Recorder
A Holter monitor is a small, portable device that records every heartbeat for 24 to 48 hours through adhesive chest electrodes. It helps doctors…

Abdominal and Carotid Ultrasounds: What Each Scan Screens For
An abdominal ultrasound uses sound waves to examine the liver, gallbladder, pancreas, spleen, kidneys, and abdominal aorta, detecting problems such as gallstones, cysts, fluid…
MRCP Scan: The Non-Invasive Look at Bile Ducts That Replaced Diagnostic ERCP
An MRCP (magnetic resonance cholangiopancreatography) test is a non-invasive MRI scan that creates detailed pictures of the bile ducts, gallbladder, and pancreatic duct without…

Neurophysiology Tests: EMG, EEG and Nerve Conduction in Plain Language
Neurophysiology tests measure the electrical activity of nerves, muscles, and the brain. An EMG records signals inside muscle, a nerve conduction study times impulses…